Blog

  • Diabetic Retinopathy: Protect Your Vision With Diabetes

    Diabetic Retinopathy: Protect Your Vision With Diabetes

    Millions of Americans with diabetes are unknowingly putting their eyesight at risk — and a simple annual eye exam could change everything.

    Introduction

    Margaret, 54, had managed her type 2 diabetes for over a decade. She took her metformin faithfully, watched her carb intake, and showed up for most of her primary care appointments. But she hadn’t seen an eye doctor in four years — because her vision seemed just fine.

    Then, almost overnight, she noticed blurry patches in her right eye. By the time she finally saw an ophthalmologist, she had moderate diabetic retinopathy in both eyes and was at serious risk of permanent vision loss.

    Margaret’s story is not unusual. According to the CDC, diabetic retinopathy is the leading cause of new blindness among American adults aged 20 to 74. Yet research suggests that up to 90% of diabetes-related vision loss is preventable with timely screening and proper blood sugar management.

    In this guide, you’ll learn exactly what diabetic retinopathy is, how it develops, what symptoms to watch for, and — most importantly — how you can protect your vision starting today.

    What Is Diabetic Retinopathy?

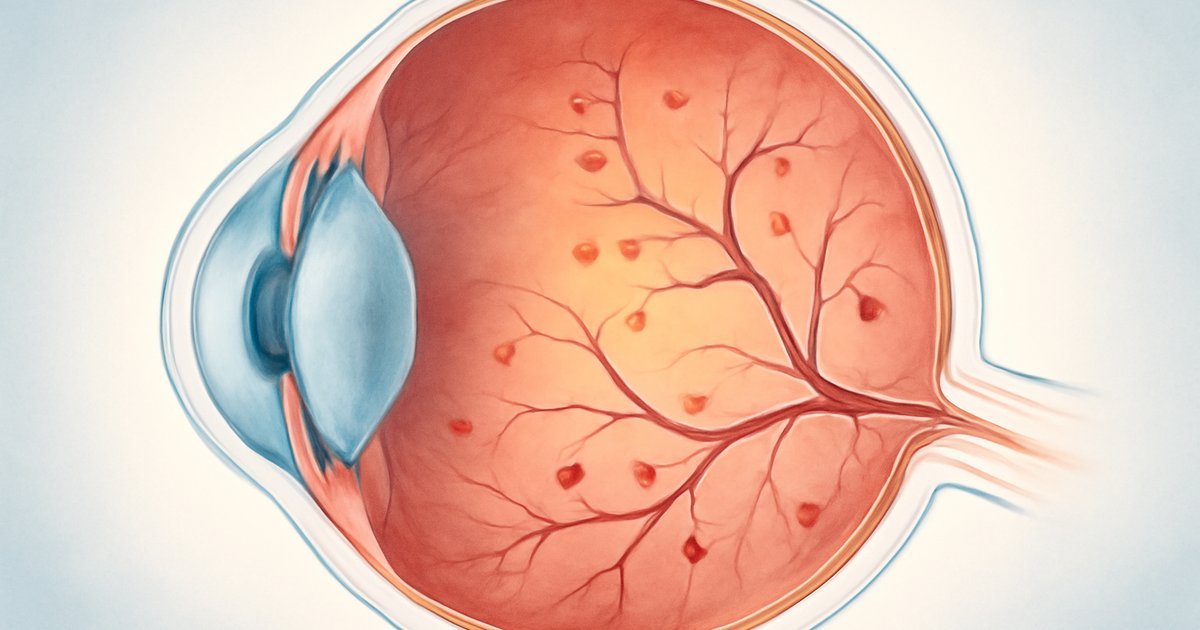
    Diabetic retinopathy is a diabetes complication that damages the blood vessels in the retina — the thin, light-sensitive layer of tissue at the back of your eye. When blood sugar levels remain chronically elevated, those tiny vessels can swell, leak fluid, or grow abnormally, all of which can distort or destroy your vision over time.

    The condition progresses in two main stages. Non-proliferative diabetic retinopathy (NPDR) is the earlier stage, where blood vessels in the retina weaken and may leak. Proliferative diabetic retinopathy (PDR) is the advanced stage, where new, abnormal blood vessels grow on the surface of the retina — a process called neovascularization — which dramatically increases the risk of severe vision loss or detachment of the retina.

    According to the National Eye Institute (NEI), an arm of the NIH, approximately 7.7 million Americans have diabetic retinopathy, and that number is projected to reach nearly 14.6 million by 2050. Both type 1 and type 2 diabetes can cause the condition, though the longer you’ve lived with diabetes, the higher your risk becomes.

    What makes diabetic retinopathy particularly dangerous is that it causes no pain and minimal early symptoms — meaning most people don’t realize anything is wrong until significant damage has already occurred.

    Signs and Symptoms: What to Watch For

    Because diabetic retinopathy often progresses silently, many people only notice symptoms once the disease has advanced. Understanding the full spectrum of warning signs — from subtle early changes to urgent red flags — can help you seek care at the right time.

    Early signs (may be subtle or absent):

    • Slightly blurry vision that comes and goes
    • Difficulty reading fine print or seeing close objects
    • Colors appearing washed out or less vibrant
    • Small dark spots or "floaters" in your field of vision
    • Difficulty seeing well in low-light conditions

    Advanced signs (require urgent medical attention):

    • Sudden or rapid vision loss in one or both eyes
    • A large number of new floaters appearing suddenly
    • Flashes of light in your vision
    • A dark curtain or shadow appearing across part of your visual field
    • Severe blurring that does not improve

    A 2021 clinical study published through the American Academy of Ophthalmology found that nearly 40% of people with type 2 diabetes who were newly diagnosed with retinopathy reported having experienced no noticeable visual symptoms before their diagnosis. This underscores why routine eye exams are so critical — your eyes may be changing even when your vision feels normal.

    Causes and Risk Factors

    The root cause of diabetic retinopathy is sustained high blood sugar. Over time, excess glucose in the bloodstream damages the walls of the small blood vessels that supply the retina. These weakened vessels may swell, develop tiny bulges called microaneurysms, or leak blood and fluid into surrounding retinal tissue.

    But not every person with diabetes develops retinopathy at the same rate or severity. Several factors can significantly increase your risk:

    • Duration of diabetes: The longer you’ve had diabetes, the higher your cumulative risk. The NIH reports that nearly all people with type 1 diabetes and more than 60% of those with type 2 diabetes will develop some degree of retinopathy after 20 years.
    • Poor blood sugar control: Chronically elevated A1C levels (a measure of average blood sugar over roughly three months) are one of the strongest predictors of retinopathy progression.
    • High blood pressure (hypertension): Elevated blood pressure compounds damage to retinal blood vessels and is extremely common among people with diabetes.
    • High cholesterol: Elevated LDL cholesterol increases the likelihood of hard exudates — fatty deposits — forming in the retina.
    • Pregnancy: Gestational diabetes or pre-existing diabetes during pregnancy can accelerate retinopathy development.
    • Smoking: Tobacco use constricts blood vessels and worsens microvascular complications throughout the body, including the eyes.
    • Ethnicity: According to the CDC, African Americans, Hispanic/Latino Americans, and Native Americans face disproportionately higher rates of diabetic eye disease.
    • Kidney disease: Diabetic nephropathy (kidney damage from diabetes) often occurs alongside retinopathy, as both stem from the same microvascular damage mechanisms.

    It’s worth noting that individual variation plays a significant role here. Two people with identical A1C levels and the same duration of diabetes may experience very different rates of retinal damage — which is why personalized care with your healthcare team matters so much.

    Diagnosis: What to Expect at the Eye Doctor

    Diagnosing diabetic retinopathy requires a comprehensive dilated eye exam — a procedure in which your eye doctor uses special drops to widen (dilate) your pupils, giving them a clear view of your retina and the blood vessels within it. This exam is painless, though your vision may remain blurry for a few hours afterward.

    Here’s what the diagnostic process typically involves:

    • Visual acuity test: A standard eye chart test to measure how well you see at various distances.
    • Dilated fundus examination: The doctor uses a special lens to examine the retina, optic nerve, and blood vessels directly.
    • Optical coherence tomography (OCT): A non-invasive imaging scan that produces detailed cross-section images of the retina, allowing detection of swelling (macular edema) and structural changes.
    • Fluorescein angiography: A dye is injected into the arm and photographs track how it flows through the retinal blood vessels, revealing leaks or abnormal growth areas.

    The American Diabetes Association (ADA) recommends that adults with type 2 diabetes get a dilated eye exam at the time of diagnosis and annually thereafter. People with type 1 diabetes should begin annual exams within five years of diagnosis. If retinopathy is detected, your ophthalmologist may recommend more frequent monitoring — sometimes every three to six months.

    If you’ve been skipping these exams, you’re far from alone. Research suggests that fewer than half of Americans with diabetes receive the recommended annual dilated eye exams. Consistent blood sugar monitoring goes hand in hand with eye exams as a cornerstone of diabetes management.

    Treatment Options for Diabetic Retinopathy

    The good news is that diabetic retinopathy responds well to treatment, especially when caught early. Your treatment plan will depend on the stage of the disease and whether diabetic macular edema (swelling at the center of the retina) is present.

    1. Blood sugar and blood pressure management
    For early-stage retinopathy, the most effective "treatment" is tighter control of blood glucose and blood pressure. Clinical evidence from the landmark DCCT (Diabetes Control and Complications Trial) and UKPDS (UK Prospective Diabetes Study) showed that intensive blood sugar control reduced the risk of retinopathy progression by 50–76% compared to conventional management. Most physicians recommend an A1C target below 7% for most adults with diabetes, though your personal target may vary.

    2. Anti-VEGF injections
    For moderate to severe retinopathy or diabetic macular edema, anti-VEGF (vascular endothelial growth factor) therapy is now the standard of care. Medications such as ranibizumab, aflibercept, and bevacizumab are injected directly into the eye to block the growth of abnormal blood vessels and reduce leakage. Clinical trials have shown these injections can significantly stabilize and even improve vision in many patients.

    3. Laser photocoagulation therapy
    Laser treatment has been used for decades to seal leaking blood vessels and shrink abnormal ones. Focal laser treatment targets specific leaking vessels, while panretinal photocoagulation (PRP) treats the peripheral retina to reduce the drive for abnormal vessel growth. While laser therapy is less commonly used as a first-line treatment since anti-VEGF injections became available, it remains an important option in many cases.

    4. Vitrectomy surgery
    In advanced cases where there is bleeding into the vitreous (the gel-like substance filling the eye) or a retinal detachment, a surgical procedure called vitrectomy may be necessary. The surgeon removes the vitreous and any scar tissue, and in some cases reattaches the retina. According to the NIH, vitrectomy significantly improves visual outcomes in patients with severe proliferative diabetic retinopathy when performed in a timely manner.

    5. Lifestyle modifications as complements
    While not a replacement for medical treatment, lifestyle changes provide meaningful support for retinopathy management. Regular physical activity, a diet low in refined carbohydrates and high in antioxidant-rich vegetables, smoking cessation, and stress reduction all contribute to better blood sugar control and vascular health. Emerging research also suggests that omega-3 fatty acids and certain antioxidant nutrients like lutein and zeaxanthin may support retinal health, though clinical evidence is still evolving.

    Living With Diabetic Retinopathy and Preventing Progression

    A diagnosis of diabetic retinopathy doesn’t have to mean inevitable vision loss. With proactive management and the right support team, many people successfully preserve their vision for years — and in some cases, decades.

    Here are practical, evidence-informed strategies for day-to-day management:

    • Keep your A1C in your target range. Work with your doctor to find the right A1C goal for your individual situation. Even a modest reduction in A1C — say, from 9% to 7.5% — can meaningfully slow retinopathy progression.
    • Control your blood pressure. The ADA recommends a blood pressure target of less than 130/80 mmHg for most adults with diabetes. High blood pressure dramatically accelerates retinal vessel damage.
    • Manage cholesterol levels. Elevated LDL cholesterol is linked to harder-to-treat retinal deposits. Statins and dietary changes are commonly recommended.
    • Never skip your annual eye exam. Even if your vision feels perfectly fine. Even if you’ve had no symptoms. This single habit may be the most important thing you can do for your long-term eye health.
    • Quit smoking — or never start. Smoking significantly worsens every diabetes complication, including retinopathy. Speak with your doctor about cessation resources.
    • Tell your eye doctor about all your medications. Some medications can affect the eyes, and your ophthalmologist needs a full picture of your health.
    • Consider adaptive aids if needed. If vision loss affects daily activities, occupational therapists and low-vision specialists can help you adapt and maintain independence.

    It’s also worth connecting your eye care with your broader diabetes management. Your ophthalmologist and endocrinologist or primary care physician should be communicating about your case — don’t hesitate to ask them to coordinate. Managing conditions like diabetes and heart disease risk alongside retinopathy requires a team-based approach.

    When to Call Your Doctor — Emergency Signs

    Some vision changes related to diabetic retinopathy require immediate medical attention. Do not wait for a scheduled appointment if you experience any of the following:

    • Sudden loss of vision in one or both eyes
    • A sudden shower of new floaters or flashes of light
    • A dark shadow, curtain, or veil appearing across any part of your vision
    • Vision that becomes rapidly and severely blurry without an obvious cause

    These symptoms may indicate a vitreous hemorrhage (bleeding inside the eye), retinal detachment, or acute macular edema — all of which are ophthalmologic emergencies that require same-day evaluation. Call your ophthalmologist immediately or go to an emergency room if you cannot reach your eye doctor.

    At your next routine visit — even if no emergencies occur — consider discussing the following with your doctor:

    • Your current A1C and whether your blood sugar management plan needs adjustment
    • Your blood pressure and cholesterol numbers and targets
    • Whether you’re due for a dilated eye exam
    • Any changes in your vision, however minor they may seem
    • Whether lifestyle changes could further reduce your retinopathy risk

    Alcohol use is another factor worth discussing — it can affect blood sugar unpredictably. You can learn more in our detailed overview of how alcohol affects blood sugar in diabetes.

    Frequently Asked Questions

    Can diabetic retinopathy be reversed?
    In some cases, early-stage diabetic retinopathy can partially improve with tighter blood sugar control. However, more advanced stages typically cannot be fully reversed — the goal becomes halting progression and preserving remaining vision. Anti-VEGF injections have shown the ability to improve vision in many patients with diabetic macular edema, but results vary from person to person.

    How fast does diabetic retinopathy progress?
    Progression varies widely depending on individual factors like blood sugar control, blood pressure, duration of diabetes, and genetics. Some people remain in the early non-proliferative stage for many years with minimal change, while others progress more rapidly — especially without consistent medical management.

    Can I develop diabetic retinopathy if my blood sugar is well controlled?
    Research suggests that good blood sugar control significantly reduces risk, but does not eliminate it entirely. Some individuals develop retinopathy even with tight glucose management, particularly if they have other risk factors like hypertension or a long duration of diabetes. This is exactly why annual eye exams remain essential even when your A1C is in range.

    Is diabetic retinopathy the same as diabetic macular edema?
    No — but they’re closely related. Diabetic macular edema (DME) is a specific complication of diabetic retinopathy in which fluid leaks into the macula, the central part of the retina responsible for sharp, detailed vision. DME can occur at any stage of retinopathy and is a leading cause of vision loss in people with diabetes.

    Do anti-VEGF injections hurt?
    Most patients find anti-VEGF eye injections less painful than anticipated. The eye is numbed with anesthetic drops before the procedure, and the injection itself typically takes only seconds. Some patients experience mild pressure or discomfort during or after the injection, but severe pain is uncommon. If you have concerns, discuss them openly with your ophthalmologist.

    Conclusion

    Diabetic retinopathy is one of the most serious — and most preventable — complications of diabetes. The science is clear: consistent blood sugar control, blood pressure management, and annual dilated eye exams are your most powerful tools for protecting your vision.

    If you’ve been putting off an eye exam, let Margaret’s story be your reminder. Vision loss doesn’t announce itself with early warning signs. But the good news is that you have the ability to stay ahead of it — with the right habits, the right care team, and the right information.

    Talk to your primary care physician or endocrinologist about coordinating care with an ophthalmologist, and don’t leave your next appointment without asking about your eye health. Your future self will thank you.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.


  • Weight Loss and Metabolism: What You Can Actually Change

    Weight Loss and Metabolism: What You Can Actually Change

    Your metabolism is not your destiny — but understanding how it works is the first step to making it work for you.

    Mark, 52, had been eating what he called "pretty healthy" for two years. He exercised three days a week, cut out most processed food, and still couldn't shed the extra 30 pounds his doctor had flagged as a cardiovascular risk. "My metabolism is just broken," he told his physician at his annual checkup. His doctor had heard it hundreds of times before — and she had a more nuanced answer.

    According to the National Institutes of Health, more than 70% of American adults are overweight or obese, and metabolic slowdown is one of the most commonly cited explanations. But clinical evidence tells a more complex story. While metabolism does change with age and body composition, research suggests that many of the factors people assume are fixed are actually modifiable.

    In this guide, you'll learn exactly what metabolism is, how it changes over time, what science says actually influences it, and what you can realistically do — with your doctor's support — to improve your body's calorie-burning efficiency as part of a sustainable weight loss plan.

    What Is Metabolism, Really?

    Metabolism refers to all the chemical processes your body uses to convert food and drink into energy. Every cell in your body requires energy to function — to breathe, pump blood, regulate temperature, repair tissue, and yes, move. The rate at which your body burns calories at rest is called your basal metabolic rate (BMR), and it accounts for roughly 60 to 75 percent of your total daily calorie expenditure, according to the Mayo Clinic.

    Your total daily energy expenditure (TDEE) has three main components:

    • Basal metabolic rate (BMR): Calories burned at complete rest, just to keep your organs functioning
    • Thermic effect of food (TEF): The energy used to digest, absorb, and metabolize what you eat — typically 10% of total calories
    • Physical activity energy expenditure (PAEE): Calories burned through deliberate exercise and everyday movement (also called NEAT — non-exercise activity thermogenesis)

    A 2021 landmark study published in Science — tracking nearly 6,500 people across 29 countries — found that metabolic rate stays remarkably stable from ages 20 to 60, then gradually declines about 0.7% per year after that. This means the dramatic "metabolic crash" many people report in their 30s and 40s is largely not a metabolism issue — it is usually a gradual decrease in physical activity and muscle mass.

    In the US, the prevalence of overweight and obesity continues to rise, with the CDC reporting that approximately 41.9% of American adults are classified as obese as of recent national survey data. Understanding the metabolic drivers behind weight gain is central to reversing this trend.

    Signs Your Metabolism May Be Running Below Optimal

    There is no simple home test for a "slow" metabolism, and many symptoms people attribute to it are actually caused by other treatable conditions. That said, clinical evidence suggests several signs are worth discussing with your doctor:

    Early or moderate signs:

    • Persistent fatigue not explained by sleep deprivation
    • Unexplained weight gain despite no significant change in diet or activity
    • Difficulty losing weight even in a caloric deficit
    • Feeling cold frequently, especially in the extremities
    • Brain fog or difficulty concentrating
    • Dry skin, brittle nails, or thinning hair
    • Constipation or sluggish digestion

    Signs that may indicate a medical condition (see your doctor):

    • Significant unintentional weight gain over weeks or months
    • Severe fatigue combined with cold intolerance and hair loss
    • Swelling in the neck, face, or limbs
    • Irregular menstrual cycles combined with weight gain
    • Blood sugar irregularities or new-onset insulin resistance symptoms

    Research published in the journal Thyroid indicates that hypothyroidism — an underactive thyroid — affects approximately 4.6% of the US population and is one of the most common medical causes of true metabolic suppression. If you have persistent symptoms above, your doctor may order a TSH (thyroid-stimulating hormone) blood test to rule this out before attributing your weight concerns to lifestyle alone.

    What Actually Causes Metabolic Slowdown?

    Understanding the true causes of metabolic change gives you real leverage over the factors within your control. Clinical evidence identifies several primary drivers:

    Muscle Mass Loss (Sarcopenia)

    Muscle tissue is metabolically active — it burns more calories at rest than fat tissue does. According to the NIH, adults typically lose 3 to 8 percent of their muscle mass per decade after age 30 if they do not engage in resistance training. This gradual loss is one of the most significant contributors to age-related metabolic decline. Building and maintaining lean muscle mass is one of the most evidence-backed strategies for preserving a healthy metabolism.

    Adaptive Thermogenesis

    This is the metabolic phenomenon that frustrates so many dieters. When you restrict calories significantly, your body responds by lowering its resting metabolic rate — essentially becoming more "efficient" to conserve energy. A landmark NIH study following contestants from the television show The Biggest Loser found that participants who lost large amounts of weight rapidly experienced measurable metabolic adaptation that persisted for years. This is why crash diets tend to backfire over time.

    Hormonal Changes

    Hormones play a central role in metabolic regulation. Insulin, cortisol, leptin, ghrelin, thyroid hormones, estrogen, and testosterone all influence how your body stores and burns energy. As women enter perimenopause and menopause, declining estrogen levels are associated with increased abdominal fat accumulation and reduced metabolic rate. In men, testosterone declines gradually after age 30, contributing to muscle loss and fat gain. The American Diabetes Association notes that insulin resistance — a condition in which cells stop responding efficiently to insulin — disrupts energy metabolism and is closely linked to both obesity and type 2 diabetes.

    Chronic Undereating and Yo-Yo Dieting

    Paradoxically, eating too little consistently can suppress your metabolism over time. Very low-calorie diets (typically below 800 calories per day) trigger hormonal and enzymatic responses that slow energy expenditure. Repeated cycles of weight loss and regain — sometimes called "yo-yo dieting" — have been associated in research with progressive metabolic adaptation, making each subsequent attempt at weight loss more difficult.

    Sedentary Lifestyle and Low NEAT

    Non-exercise activity thermogenesis (NEAT) — the calories burned through everyday movements like walking, standing, cooking, and fidgeting — can account for 200 to 700 extra calories per day depending on lifestyle. Research from the Mayo Clinic suggests that highly sedentary individuals burn dramatically fewer total daily calories than moderately active ones, even if both exercise for 30 minutes a day. A desk-bound lifestyle suppresses NEAT significantly.

    Diagnosis: What to Expect When You Talk to Your Doctor

    If you suspect a medical issue is affecting your metabolism, your doctor will likely begin with a thorough history and physical exam, followed by targeted lab work. You should not try to self-diagnose a metabolic disorder based on symptoms alone, as many conditions overlap.

    Common diagnostic tests your doctor may order include:

    • TSH and free T4: To evaluate thyroid function
    • Fasting glucose and HbA1c: To screen for prediabetes or type 2 diabetes
    • Fasting insulin level: To assess insulin resistance
    • Comprehensive metabolic panel (CMP): To evaluate kidney and liver function
    • Complete blood count (CBC): To rule out anemia as a cause of fatigue
    • Cortisol levels: If adrenal dysfunction is suspected
    • Sex hormone levels (testosterone, estrogen, DHEA): Especially in adults over 40

    In some clinical settings, indirect calorimetry — a specialized test that measures actual resting metabolic rate by analyzing your oxygen consumption — can be performed. This is considered more accurate than formula-based BMR estimates and is worth asking about if standard approaches to weight management have consistently failed.

    Evidence-Based Ways to Support a Healthy Metabolism

    This is where the science becomes genuinely empowering. While you cannot completely override genetics or aging, research consistently identifies several lifestyle strategies that meaningfully support metabolic function and weight loss outcomes.

    1. Prioritize Resistance Training

    Clinical evidence is robust here: resistance training — lifting weights, using resistance bands, or performing bodyweight exercises — is the most effective intervention for preserving and building metabolically active muscle tissue. A 2012 meta-analysis in the Journal of Applied Physiology found that progressive resistance training increases resting metabolic rate by an average of 7%, independent of weight loss. Even two sessions per week make a clinically significant difference. If you want to go deeper on how strength training integrates with weight loss, our article on Weight Loss and Stress: How Cortisol Blocks Your Progress explores how hormonal balance ties directly into exercise response.

    2. Eat Enough — Especially Protein

    Eating adequate protein is one of the most metabolically impactful dietary choices you can make. Protein has the highest thermic effect of any macronutrient — your body burns approximately 20 to 30% of protein calories during digestion, compared to 5 to 10% for carbohydrates and 0 to 3% for fats. The American Journal of Clinical Nutrition has published multiple studies showing that higher protein intake supports muscle preservation during weight loss and reduces adaptive thermogenesis. Most clinicians recommend targeting 0.7 to 1.0 grams of protein per pound of body weight, though this varies by individual. For more on how protein supports weight management, see our evidence-based guide on High-Protein Diet for Weight Loss: What Science Says.

    3. Avoid Severe Caloric Restriction

    Research supports a moderate deficit — typically 300 to 500 calories per day below your TDEE — as optimal for sustainable fat loss without triggering significant metabolic adaptation. This approach tends to preserve muscle mass and avoid the hormonal suppression that comes with crash dieting. Patience is not optional here; it is metabolically necessary.

    4. Increase Daily Movement (Boost NEAT)

    You do not need to double your gym sessions. Small, consistent increases in daily movement — taking the stairs, parking farther away, standing while on calls, taking short walks after meals — can add hundreds of calories of daily expenditure. Harvard Health Publishing reports that simply standing instead of sitting for three hours per day burns roughly 30,000 extra calories per year — equivalent to running about ten marathons.

    5. Prioritize Quality Sleep

    The CDC reports that one in three American adults does not get enough sleep. Sleep deprivation measurably disrupts the hormones that regulate hunger and metabolism — specifically, it raises ghrelin (the hunger hormone) and lowers leptin (the satiety hormone), leading to increased caloric intake and reduced fat oxidation. Research published in the Annals of Internal Medicine found that inadequate sleep reduced the proportion of weight loss coming from fat by 55%, even when total calories were controlled.

    6. Manage Chronic Stress

    Chronically elevated cortisol promotes fat storage, particularly in the abdominal region, and suppresses thyroid function — both of which negatively affect metabolic rate. Evidence-based stress management strategies including mindfulness meditation, yoga, cognitive behavioral therapy (CBT), and structured relaxation practices have all been shown to reduce cortisol levels and support healthier metabolic function over time.

    Living With a Slower Metabolism: Realistic Expectations

    One of the most important things your doctor can help you do is calibrate realistic expectations. Clinical evidence consistently shows that sustainable weight loss — typically defined as losing 5 to 10% of body weight and keeping it off for one year — produces meaningful improvements in blood pressure, blood sugar, cholesterol, and joint health, even when a person does not reach an "ideal" weight.

    This varies from person to person. Your genetic baseline, hormonal environment, gut microbiome, medication history, and stress load all influence how your body responds to metabolic interventions. What works quickly for one person may take longer for another — and that is not a failure. It is biology.

    Tracking your progress through non-scale metrics — energy levels, sleep quality, blood labs, waist circumference, strength gains — often gives a more complete picture of metabolic health than the number on a scale alone. Work with your healthcare provider to establish personalized benchmarks that reflect your whole health picture.

    When to Call Your Doctor or Seek Urgent Care

    Most metabolic concerns are non-emergency and can be addressed at a scheduled appointment. However, certain symptoms require prompt attention:

    See your doctor soon if you experience:

    • Rapid unintentional weight gain (more than 5 pounds in two weeks without diet changes)
    • New or worsening fatigue combined with cold intolerance, hair loss, or swelling
    • Blood sugar readings consistently outside your target range
    • Sudden changes in appetite or thirst

    Seek emergency care immediately if you experience:

    • Severe confusion, difficulty breathing, or chest pain alongside sudden weight changes
    • Signs of diabetic ketoacidosis (extreme thirst, vomiting, fruity breath odor, rapid breathing)
    • Sudden severe swelling of the face, hands, or ankles
    • Loss of consciousness or seizure

    Frequently Asked Questions About Metabolism and Weight Loss

    Does metabolism really slow down with age?
    Research suggests that true metabolic slowdown is more gradual than most people believe — the landmark 2021 Science study found meaningful decline does not begin until after age 60. The weight gain many adults experience in their 30s and 40s is more often linked to reduced physical activity and muscle loss than to a fundamental change in metabolic rate.

    Can certain foods "boost" metabolism?
    Some foods — such as green tea, coffee, and spicy foods — have shown modest, short-term increases in metabolic rate in clinical studies. However, these effects are small (typically 4 to 5% for caffeine) and not sufficient to produce significant weight loss on their own. No food meaningfully "transforms" metabolism in the way marketing often claims.

    Is a slow metabolism always a medical problem?
    Not necessarily. A lower-than-average metabolic rate can reflect natural variation, genetics, or prolonged caloric restriction — not always a diagnosable condition. Your doctor can help determine whether lab workup is warranted based on your specific symptoms and history.

    Will taking metabolism-boosting supplements help?
    The FDA does not regulate dietary supplements with the same rigor as prescription medications. Most commercially available "metabolism boosters" have limited clinical evidence supporting significant, lasting effects. Discuss any supplement use with your doctor before starting, especially if you take prescription medications or have a chronic condition.

    How long does it take to see metabolic improvements?
    This varies from person to person. Most clinical studies show measurable improvements in metabolic markers — including resting metabolic rate, insulin sensitivity, and hormonal balance — within 8 to 12 weeks of consistent lifestyle changes including resistance training, adequate protein intake, and improved sleep. Meaningful body composition changes typically require 3 to 6 months of sustained effort.

    Conclusion

    Your metabolism is not a fixed sentence. While it is shaped by genetics, age, and hormones, clinical evidence is clear that many of the most powerful metabolic levers — muscle mass, daily movement, protein intake, sleep quality, and stress management — are within your reach to influence.

    The most important step you can take today is to have an honest, informed conversation with your doctor. Rule out medical causes, set realistic goals, and build a plan that works with your biology — not against it. Sustainable weight loss is not about working harder against a broken system. It is about understanding the system well enough to support it.

    You have more control than you think. And you do not have to figure it out alone.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Online Therapy for Grief and Loss: Does It Really Help?

    Online Therapy for Grief and Loss: Does It Really Help?

    Losing someone you love can feel like the ground disappearing beneath your feet — and finding support should not require you to leave home.

    James, 54, lost his wife of 28 years to pancreatic cancer. For months afterward, he barely left the house. The idea of sitting in a therapist’s waiting room, holding back tears in front of strangers, felt unbearable. Then a friend mentioned online therapy. Within a week, he was speaking with a licensed grief counselor from his kitchen table — still in his flannel shirt, coffee in hand.

    Grief is one of the most universal human experiences, yet it remains one of the least talked-about mental health challenges in the US. According to the American Psychological Association, approximately 2.5 million Americans die each year, meaning millions more are left to navigate profound loss. Yet research consistently shows that fewer than one in three bereaved adults seeks professional mental health support.

    In this guide, you will learn how online therapy for grief and loss works, what the clinical evidence says, what types of therapy are most effective, and how to know when you or someone you love needs professional help.

    What Is Grief — and When Does It Become a Clinical Concern?

    Grief is the natural emotional, physical, and cognitive response to loss. It can follow the death of a loved one, but also the end of a marriage, a serious diagnosis, job loss, or any significant life change. Bereavement — specifically grief after a death — is one of the most studied forms.

    Most people move through acute grief over months to years, gradually integrating the loss into their lives. This is considered a normal, healthy process. However, clinical evidence indicates that roughly 10 to 15 percent of bereaved individuals develop what is now formally recognized in the DSM-5-TR (the Diagnostic and Statistical Manual of Mental Disorders) as Prolonged Grief Disorder (PGD) — formerly called complicated grief.

    PGD is characterized by intense, persistent grief lasting more than 12 months after a loss (6 months for children) that significantly impairs daily functioning. According to the NIH, PGD is associated with increased risk of depression, anxiety, substance use disorders, and even suicidal ideation.

    Understanding the difference between natural grief and a condition requiring professional support is one of the most important distinctions your doctor or therapist can help you make.

    Signs and Symptoms: Normal Grief vs. When to Seek Help

    Grief does not follow a rigid timeline or checklist. The classic "five stages" model — denial, anger, bargaining, depression, acceptance — is widely known but frequently misunderstood. Research from Yale and Harvard suggests grief is rarely linear, and most people cycle through these states rather than progressing in order.

    Common signs of normal grief include:

    • Intense sadness, crying, or emotional numbness
    • Difficulty concentrating or making decisions
    • Changes in appetite and sleep
    • Social withdrawal or longing for the person who died
    • Waves of emotion triggered by reminders (music, anniversaries, smells)
    • Physical symptoms such as fatigue, chest tightness, or headaches

    Signs that suggest professional support may be needed:

    • Grief that feels as intense at 12+ months as it did in the first weeks
    • Inability to carry out daily responsibilities at work or home
    • Complete social isolation lasting months
    • Persistent feelings of guilt, worthlessness, or hopelessness
    • Use of alcohol or substances to cope
    • Thoughts of self-harm or not wanting to be alive
    • Inability to accept the reality of the loss

    A 2021 study published in JAMA Psychiatry found that individuals with untreated PGD had significantly higher rates of cardiovascular events and immune dysfunction compared to those who received grief-focused therapy — underscoring why treatment matters.

    What Is Online Therapy for Grief?

    Online therapy for grief — also called teletherapy, e-therapy, or virtual counseling — delivers evidence-based psychological treatment through secure video calls, phone sessions, or asynchronous messaging platforms. You connect with a licensed therapist from wherever you feel safest and most comfortable.

    Platforms such as BetterHelp, Talkspace, and therapist directories like Psychology Today now allow users to filter specifically for grief specialists. The American Psychological Association confirmed in 2023 that the use of telehealth for mental health services had grown by more than 38 times compared to pre-pandemic levels, and utilization among adults over 50 nearly tripled.

    For those navigating grief, the accessibility of online therapy removes several significant barriers:

    • No commute when leaving home feels emotionally exhausting
    • Flexible scheduling around unpredictable emotional days
    • Access to specialists who may not be available locally
    • Continuity of care during travel or relocation
    • Reduced stigma for those who may feel shame about needing support

    This varies from person to person — some individuals strongly prefer the physical presence of an in-office therapist, and that preference is entirely valid. Online therapy is not a replacement for in-person care for everyone, but clinical evidence indicates it is an effective alternative for most.

    Evidence-Based Therapies Used in Online Grief Counseling

    Not all grief counseling is the same. Research suggests that specific therapeutic frameworks are more effective than general supportive talking, particularly for those with PGD or co-occurring depression and anxiety.

    Complicated Grief Treatment (CGT) — developed by researchers at Columbia University — is currently the most evidence-supported therapy specifically designed for PGD. A landmark clinical trial published in JAMA found that CGT outperformed standard antidepressant therapy in reducing grief symptoms in more than 80 percent of participants. CGT has been successfully adapted for telehealth delivery.

    Cognitive Behavioral Therapy (CBT) helps identify and reframe unhelpful thought patterns around loss — such as excessive guilt ("I should have done more") or catastrophic thinking ("I will never be okay again"). Multiple meta-analyses confirm CBT’s effectiveness for grief-related depression and anxiety delivered via online platforms.

    Acceptance and Commitment Therapy (ACT) focuses on accepting painful emotions rather than fighting them, and on identifying values that guide action even in the presence of grief. Research from the NIH suggests ACT is particularly helpful for older adults navigating loss and existential concerns.

    Narrative Therapy invites you to tell the story of your relationship with the person who died — including the loss — in a way that honors meaning and identity. This approach is especially valuable for those who feel their grief is not being "heard."

    Online Support Groups facilitated by licensed therapists offer peer connection alongside clinical guidance. A 2022 meta-analysis in Death Studies found that therapist-led online grief groups produced significant reductions in PGD symptoms and social isolation over 12 weeks. For more on how virtual platforms support complex mental health needs, see our guide on Online Therapy for Trauma and PTSD: Does It Really Work?

    Does Online Therapy for Grief Actually Work? What the Research Says

    This is the question most people reasonably ask before committing time and money to any form of therapy.

    The short answer: yes — clinical evidence is increasingly robust. A 2020 systematic review published in Clinical Psychology Review analyzed 17 randomized controlled trials of internet-based grief interventions and found statistically significant improvements in grief severity, depression, and anxiety compared to control groups. Effects were comparable to face-to-face therapy in most studies.

    Researchers at Johns Hopkins have noted that the therapeutic alliance — the quality of the relationship between you and your therapist — is one of the strongest predictors of treatment outcome. Early concerns that this connection would be weaker online have not been borne out. Multiple studies confirm that patients rate their therapeutic relationships with online therapists as equally strong as with in-person providers.

    That said, online therapy may be less appropriate for individuals with severe psychiatric conditions, active suicidality requiring crisis intervention, or those who lack stable internet access. Your primary care physician or a mental health professional can help determine the right level of care for your specific situation.

    If you are also navigating anxiety alongside your grief, the article on Online Therapy for OCD: Does It Really Work? offers additional context on how structured online CBT programs perform across different conditions.

    Living With Grief: Day-to-Day Strategies Alongside Therapy

    Online therapy is most effective when combined with supportive daily practices. Research suggests — and most grief therapists recommend — an integrative approach that addresses emotional, physical, and social wellbeing simultaneously.

    Maintain basic physical health routines. Sleep disruption, poor nutrition, and physical inactivity are common during bereavement and worsen psychological symptoms. The Mayo Clinic recommends prioritizing sleep hygiene and gentle movement — even 20-minute daily walks — as evidence-based mood stabilizers during grief.

    Create rituals of remembrance. Research from Harvard Medical School indicates that meaningful rituals — lighting a candle on anniversaries, creating a memory box, or writing letters to the person who died — are associated with lower grief intensity and a greater sense of continued connection.

    Limit social isolation without forcing social performance. You do not need to "be okay" around others. But gentle, low-pressure social contact — even brief check-ins with trusted friends — protects against the compounding effects of loneliness.

    Be cautious with alcohol. Many bereaved individuals use alcohol to soften emotional pain. The CDC notes that alcohol use significantly increases in the year following a major loss, particularly in men. Alcohol is a depressant and worsens grief symptoms over time. Speak with your doctor if this is a concern. You can also read more in our resource on Diabetes and Alcohol: What Every Diabetic Must Know for context on how alcohol interacts with physical health conditions that may also be present.

    Give yourself time — and professional support. One of the most harmful myths about grief is that it should resolve within a defined period. The goal of grief therapy is not to eliminate sadness, but to help you carry it in a way that allows you to live fully again.

    When to Call Your Doctor or Seek Emergency Help

    Grief is not always just emotional — it has measurable effects on cardiovascular health, immune function, and hormonal balance. Bereaved individuals face a significantly elevated risk of what researchers call the "widowhood effect" — studies published in PLOS ONE indicate that surviving spouses face a 66 percent increased risk of dying within the first three months following their partner’s death, primarily due to cardiovascular events and immune suppression.

    Contact your doctor promptly if you experience:

    • Chest pain, shortness of breath, or heart palpitations during grief
    • Significant unexplained weight loss
    • Complete inability to eat or sleep for more than several days
    • Signs of severe depression — hopelessness, inability to function, persistent emptiness
    • Concerns about someone else’s safety or your own

    Seek emergency care immediately if:

    • You are having thoughts of suicide or self-harm
    • You are experiencing a mental health crisis with disorientation or loss of reality
    • You have harmed yourself or are in immediate danger

    If you are in crisis: Call or text 988 (the Suicide and Crisis Lifeline) or go to your nearest emergency room. You can also text "HELLO" to 741741 (Crisis Text Line) for immediate support.

    Frequently Asked Questions

    Is online therapy as effective as in-person therapy for grief?
    Research suggests yes, for most people. Multiple clinical trials and systematic reviews confirm that evidence-based grief therapies delivered online produce outcomes comparable to face-to-face sessions. The therapeutic relationship — which strongly predicts success — appears equally strong in both formats.

    How long does grief therapy typically take?
    This varies significantly from person to person. Some people benefit from 8 to 12 structured sessions. Others with Prolonged Grief Disorder may work with a therapist for 6 months or longer. Complicated Grief Treatment (CGT) is typically structured as 16 sessions over approximately four months.

    Can grief therapy help with depression and anxiety too?
    Yes. Grief and clinical depression are distinct conditions, but they frequently overlap. Most licensed grief therapists are trained to identify and treat co-occurring depression and anxiety. Clinical evidence from the NIH indicates that treating grief directly often reduces depression symptoms significantly.

    Does health insurance cover online grief therapy?
    Many major insurance plans, including Medicare and Medicaid, now cover telehealth mental health services. Coverage varies by plan and provider. Contact your insurer directly to confirm which online platforms or therapist types are covered under your specific benefits. The Mental Health Parity and Addiction Equity Act requires that most plans cover mental health services at the same level as physical health services.

    What if I am not ready to talk about my loss yet?
    A good grief therapist will never force you to discuss anything before you are ready. Initial sessions often focus on building trust and understanding your experience at your own pace. Some people find that starting with messaging-based therapy — where responses are asynchronous — feels less overwhelming than live sessions. Ask your therapist what format might work best for where you are right now.

    Moving Forward: You Do Not Have to Grieve Alone

    Grief is not a problem to be fixed — it is a testament to love. But navigating it without support can prolong suffering unnecessarily and put both your emotional and physical health at risk.

    Online therapy for grief has moved well beyond an experimental option. Clinical evidence firmly supports its effectiveness, and for many adults — particularly those who are older, physically limited, or living in areas with few local specialists — it is not just a convenient choice, it is often the most practical one.

    If you or someone you care about is struggling with loss, speaking with a licensed grief therapist — whether online or in person — is one of the most evidence-supported steps you can take. Your grief deserves real professional attention, not just time.

    Talk to your primary care physician about a referral, or use a verified telehealth platform to connect with a licensed mental health professional today. You do not have to figure this out alone.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • OCD in Adults: Symptoms, Causes & Treatment Options

    OCD in Adults: Symptoms, Causes & Treatment Options

    Obsessive-compulsive disorder affects millions of Americans — yet most wait nearly a decade before receiving an accurate diagnosis.

    Introduction

    Mark, 42, spent up to three hours every morning checking whether his front door was locked — sometimes returning home from work just to be sure. He knew, rationally, that he had locked it. But the doubt was unbearable. What he was living with had a name: obsessive-compulsive disorder, or OCD.

    According to the National Institute of Mental Health (NIMH), OCD affects approximately 2.3% of the US adult population at some point in their lives. That translates to millions of people whose daily routines are disrupted — often severely — by unwanted thoughts and repetitive behaviors they feel powerless to stop.

    Despite how common it is, OCD remains one of the most misunderstood mental health conditions in America. It is frequently minimized as a quirky personality trait or confused with other anxiety disorders. In this guide, you will learn exactly what OCD is, how it is diagnosed, what the most effective treatments look like, and what you can do right now to take back control of your life.

    What Is Obsessive-Compulsive Disorder (OCD)?

    Obsessive-compulsive disorder is a chronic mental health condition characterized by two core features: obsessions and compulsions.

    Obsessions are unwanted, intrusive thoughts, images, or urges that cause significant distress. They are not simply worries about everyday problems — they are persistent, repetitive, and feel impossible to dismiss.

    Compulsions are repetitive behaviors or mental acts performed in response to an obsession — an attempt to reduce anxiety or prevent a feared outcome. Common examples include hand-washing, checking, counting, or silently repeating phrases.

    Crucially, the compulsive behavior provides only temporary relief. The obsession returns, often more intense than before, creating a self-reinforcing cycle that can consume hours of the day.

    The NIMH classifies OCD as distinct from general anxiety disorders, though anxiety is a major component. Clinical evidence indicates that OCD has a measurable neurobiological basis, involving abnormal activity in circuits connecting the orbitofrontal cortex, thalamus, and striatum — areas of the brain responsible for decision-making and response inhibition.

    OCD is not a personality quirk, and it is not caused by being a perfectionist. It is a recognized, diagnosable medical condition that responds well to evidence-based treatment.

    Signs and Symptoms of OCD

    OCD presents differently from person to person. The specific content of obsessions varies widely — but the underlying structure (intrusive thought → anxiety → compulsion → temporary relief → repeat) is consistent across presentations.

    Common Obsession Themes

    • Contamination fears — fear of germs, illness, or spreading disease to loved ones
    • Harm obsessions — intrusive thoughts about accidentally or intentionally hurting someone
    • Symmetry and order — intense discomfort when objects are not arranged "just right"
    • Forbidden or taboo thoughts — unwanted sexual, religious, or violent images
    • Doubt and checking — persistent uncertainty about whether something was done correctly (e.g., turning off the stove, locking the door)

    Common Compulsions

    • Excessive hand-washing or cleaning rituals
    • Repeatedly checking locks, appliances, or switches
    • Counting, tapping, or arranging objects in a specific order
    • Seeking reassurance from others repeatedly
    • Mental rituals such as praying, repeating words, or "undoing" a thought
    • Avoiding situations that trigger obsessions

    Early vs. Advanced Symptoms

    Early signs may include spending more than one hour per day on obsessive thoughts or compulsive behaviors, avoiding places or people that trigger anxiety, and feeling significant shame or distress about your thoughts.

    Advanced signs include being unable to maintain employment or relationships due to OCD symptoms, spending several hours daily in compulsive rituals, and experiencing depression, social isolation, or suicidal ideation linked to OCD severity.

    A landmark study published in JAMA Psychiatry found that individuals with severe OCD reported quality-of-life impairment comparable to that of schizophrenia — underscoring the serious, disabling nature of the condition when left untreated.

    Causes and Risk Factors

    OCD does not have a single known cause. Research suggests it arises from a combination of genetic, neurological, and environmental factors.

    Genetic Factors

    OCD runs in families. Clinical evidence indicates that first-degree relatives of someone with OCD are two to five times more likely to develop the condition themselves. Twin studies suggest heritability rates between 40% and 65%.

    Neurobiological Factors

    Brain imaging studies consistently show differences in the serotonin and glutamate pathways in people with OCD. This is one reason why medications targeting serotonin reuptake — specifically SSRIs (selective serotonin reuptake inhibitors) — are a cornerstone of OCD treatment.

    Environmental and Psychological Factors

    • Childhood trauma or abuse — research suggests adverse childhood experiences may increase OCD risk
    • High-stress life events — major transitions, loss, or illness can trigger or worsen symptoms
    • Streptococcal infections (PANDAS) — in some children, rapid OCD onset has been linked to strep infections; this is called Pediatric Autoimmune Neuropsychiatric Disorders Associated with Streptococcal Infections
    • Learned behavioral patterns — compulsive behaviors may be reinforced over time because they temporarily reduce anxiety

    According to the CDC, anxiety-related disorders — including OCD — disproportionately affect adults who report high levels of daily stress and those with limited access to mental health care. Women are slightly more likely than men to be diagnosed with OCD, though men tend to develop symptoms earlier in life.

    Diagnosis: What to Expect

    If you suspect you have OCD, the first step is speaking with your primary care physician or a licensed mental health professional. There is no blood test for OCD — diagnosis is clinical and based on a structured evaluation.

    The Diagnostic Process

    Your clinician will typically use criteria from the DSM-5 (Diagnostic and Statistical Manual of Mental Disorders, 5th Edition). For a diagnosis of OCD, you must have:

    • Obsessions, compulsions, or both
    • Symptoms that are time-consuming (more than one hour per day) or cause clinically significant distress or impairment
    • Symptoms not attributable to substances, medical conditions, or another mental health disorder

    A commonly used assessment tool is the Yale-Brown Obsessive Compulsive Scale (Y-BOCS), which measures the severity of both obsessions and compulsions and helps guide treatment planning.

    When to Seek Evaluation

    You should seek a professional evaluation if your intrusive thoughts or repetitive behaviors are causing you to:

    • Lose significant time each day (one hour or more)
    • Avoid work, social situations, or relationships
    • Experience worsening anxiety, depression, or feelings of hopelessness
    • Feel unable to function normally despite your best efforts

    Research from the NIMH suggests the average delay between OCD symptom onset and receiving appropriate treatment is 14 to 17 years — a sobering reminder of how important early recognition and help-seeking truly are.

    Treatment Options for OCD

    The good news is that OCD responds well to treatment. Most people experience meaningful improvement with the right combination of therapy, medication, or both.

    1. Cognitive Behavioral Therapy (CBT) with ERP

    The gold standard psychological treatment for OCD is a specific form of CBT called Exposure and Response Prevention (ERP). ERP involves gradually and systematically confronting feared situations or obsessive triggers — and deliberately refraining from performing the compulsive response.

    Over time, ERP teaches the brain that the feared outcome does not occur and that anxiety naturally diminishes without the compulsion. This is called habituation.

    A meta-analysis published in Clinical Psychology Review found that ERP produced large effect sizes across OCD presentations, with 60-85% of patients experiencing significant symptom reduction. Most clinicians recommend weekly sessions over 12-20 weeks, though this varies from person to person.

    2. Medication: SSRIs

    The FDA has approved several SSRI medications for the treatment of OCD in adults. These include fluoxetine, fluvoxamine, paroxetine, and sertraline, as well as the tricyclic antidepressant clomipramine.

    Most physicians recommend allowing 8-12 weeks at an adequate dose before assessing full response — longer than the typical antidepressant trial. Research suggests that combining SSRIs with ERP therapy produces better outcomes than either treatment alone.

    Medication decisions should always be made in partnership with your prescribing physician or psychiatrist. Never adjust or discontinue psychiatric medications without medical guidance.

    3. Acceptance and Commitment Therapy (ACT)

    ACT is an emerging, evidence-supported approach that teaches people to observe obsessive thoughts without fusing with them or responding compulsively. Rather than fighting intrusive thoughts, ACT encourages psychological flexibility — the ability to act in line with your values even when uncomfortable thoughts are present.

    Clinical evidence from multiple randomized controlled trials indicates ACT can be an effective complement or alternative for patients who do not fully respond to ERP.

    4. Transcranial Magnetic Stimulation (TMS)

    For adults with OCD that does not respond to first-line treatments, the FDA cleared deep TMS (transcranial magnetic stimulation) as an adjunct treatment. TMS uses magnetic pulses to modulate activity in specific brain circuits involved in OCD. It is non-invasive and performed in an outpatient setting.

    Lifestyle Modifications as Complements

    While lifestyle changes are not a replacement for clinical treatment, research suggests several practices can support overall mental health and reduce symptom severity:

    • Regular aerobic exercise — studies suggest 30 minutes of moderate exercise at least 4 days per week may reduce anxiety symptoms
    • Consistent sleep — poor sleep worsens anxiety and lowers resistance to compulsive urges
    • Mindfulness meditation — may increase tolerance of distressing thoughts without compulsive responding
    • Stress reduction — high stress is a known OCD trigger; structured relaxation techniques can help

    If you are navigating anxiety alongside OCD, you may also find value in our article on Online Therapy for OCD: Does It Really Work?, which explores virtual treatment options in detail.

    Living With OCD: Daily Management and Long-Term Outlook

    Managing OCD is an ongoing process — not a one-time fix. Most people with OCD learn to manage their symptoms effectively rather than eliminate them entirely, though many do achieve long periods of remission.

    Practical Day-to-Day Strategies

    • Work with your therapist on an ERP hierarchy — a ranked list of feared situations you will gradually face, from least to most anxiety-provoking
    • Delay, then resist compulsions — even delaying a compulsion by five minutes can weaken its grip over time
    • Track your symptoms — keeping a journal helps identify triggers and patterns, which you can share with your treatment team
    • Build a support network — trusted family members or friends who understand OCD (not who accommodate compulsions) can provide meaningful encouragement
    • Join a peer support group — the International OCD Foundation (IOCDF) offers local and virtual support groups across the US

    Understanding "Accommodation"

    Well-meaning family members often accommodate OCD behaviors — answering reassurance questions, completing rituals on the person’s behalf, or rearranging routines to avoid triggers. Research consistently shows that accommodation, while compassionate in intent, reinforces OCD and worsens long-term outcomes. Family therapy or psychoeducation can help loved ones provide support without fueling the disorder.

    For additional perspective on how stress and anxiety interact with physical and mental wellbeing, see our resource on Weight Loss and Stress: How Cortisol Blocks Your Progress.

    When to Call Your Doctor: Red Flags and Emergency Signs

    OCD can significantly worsen during periods of high stress, major life transitions, illness, or hormonal changes. Knowing when symptoms have crossed into a medical emergency is essential.

    Call Your Doctor or Mental Health Provider If:

    • Your symptoms have worsened significantly over the past two to four weeks
    • You are spending more than three to four hours per day in compulsive rituals
    • OCD is preventing you from working, eating, sleeping, or caring for yourself
    • You have begun using alcohol or substances to cope with obsessive thoughts
    • You are experiencing new or worsening depression alongside OCD

    Seek Emergency Care Immediately If:

    • You are having thoughts of harming yourself or others
    • You are experiencing suicidal ideation, a plan, or intent
    • You feel completely unable to care for yourself or a dependent in your care

    If you or someone you know is in crisis, contact the 988 Suicide and Crisis Lifeline by calling or texting 988. This free, confidential resource is available 24/7 across the United States.

    What to Tell Your Doctor

    At your next appointment, come prepared with:

    • A description of your most distressing obsessions and compulsions
    • An estimate of how many hours per day symptoms consume
    • Any previous treatment history, including medications tried and therapy attended
    • How symptoms have changed recently and any triggers you have identified

    Frequently Asked Questions About OCD

    Is OCD curable?

    OCD is a chronic condition, and while it may not be permanently eliminated, most people achieve significant and sustained symptom reduction with proper treatment. Many adults with OCD lead full, productive lives with the help of ERP therapy, medication, or a combination of both. Ongoing management — rather than a single "cure" — is the realistic and achievable goal.

    Can OCD develop for the first time in adulthood?

    Yes. While OCD often begins in childhood or adolescence, clinical evidence indicates that adult-onset OCD — particularly in the late 20s and 30s — is well-documented. Stress, trauma, hormonal changes, and major life transitions can trigger first-episode OCD in adults who had no prior symptoms.

    Is OCD the same as being very clean or organized?

    No. This is one of the most common misconceptions about OCD. Many people casually say they are "so OCD" about cleanliness or organization, but true OCD involves intrusive, unwanted thoughts that cause severe distress and compulsive behaviors that significantly impair daily functioning. OCD is not a preference — it is a disorder.

    Can OCD go away on its own without treatment?

    Research suggests that OCD rarely resolves fully without treatment. Untreated OCD tends to fluctuate — symptoms may ease during lower-stress periods and worsen during high-stress periods — but the underlying cycle generally persists and often worsens over time. Early intervention is strongly associated with better long-term outcomes.

    Is online therapy effective for OCD?

    Growing evidence supports the effectiveness of online or telehealth-delivered ERP for OCD. Several randomized controlled trials have found that virtual ERP produces outcomes comparable to in-person therapy for many adults. This is particularly meaningful given the national shortage of OCD specialists. You can explore this topic further in our article on Online Therapy for OCD: Does It Really Work?

    Conclusion

    Obsessive-compulsive disorder is a real, diagnosable, and highly treatable mental health condition — not a personality flaw, not a habit, and not something you can simply "think your way out of." With the right combination of evidence-based therapy, medication when appropriate, and consistent self-management strategies, most adults with OCD experience meaningful improvement in their quality of life.

    If you recognize yourself in what you have read today, please take that recognition as a first, courageous step. Talk to your primary care physician or seek a referral to a mental health professional experienced in OCD treatment. You do not have to manage this alone — and the sooner you reach out, the sooner you can begin reclaiming your days.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Health Insurance for Maternity & Newborn Care: Full Guide

    Health Insurance for Maternity & Newborn Care: Full Guide

    Understanding your maternity benefits before your due date could save you thousands of dollars — and spare you from unexpected billing surprises at the most important moment of your life.

    When Maria, 32, discovered she was pregnant, her first call was to her OB-GYN. Her second — though she didn’t realize it should have been — was to her health insurance company. Three weeks after delivering a healthy baby boy, she received a bill for $4,200 in uncovered services. No one had warned her about her out-of-network anesthesiologist.

    Maternity and newborn care is one of the most significant healthcare events most families will ever face — medically, emotionally, and financially. According to the Kaiser Family Foundation, the average cost of a vaginal delivery in the United States is approximately $14,000, while a cesarean section can exceed $26,000 before insurance. Yet millions of expectant parents navigate coverage gaps, surprise bills, and confusing plan documents every year.

    In this guide, you’ll learn exactly what your health insurance is required to cover for maternity and newborn care, what common gaps to watch for, and how to advocate for yourself and your growing family before, during, and after delivery.

    What Does Federal Law Require Health Insurance to Cover?

    Under the Affordable Care Act (ACA), maternity and newborn care is classified as one of ten essential health benefits. This means any health insurance plan sold on the individual or small-group market is legally required to cover it. However, the depth of that coverage — what you actually pay out of pocket — varies significantly from plan to plan.

    The NIH and the Centers for Medicare & Medicaid Services (CMS) confirm that compliant plans must cover prenatal visits, labor and delivery, postpartum care, and newborn care without lifetime or annual dollar limits. Plans cannot deny coverage for maternity care as a pre-existing condition, a protection that has been in place since the ACA’s passage.

    Large employer-sponsored plans (those with 50 or more employees) are generally subject to the same essential benefits requirements, though grandfathered plans — those established before March 23, 2010, and unchanged since — may have different rules. If you’re unsure whether your employer plan is grandfathered, your HR department must disclose this upon request.

    Medicaid, the federally and state-funded program, covers maternity care for eligible low-income individuals, and income thresholds are often expanded during pregnancy. According to the CDC, Medicaid finances nearly 42% of all births in the United States, making it the single largest payer of maternity care in the country.

    What Prenatal Services Are Typically Covered?

    Prenatal care — the medical care you receive throughout pregnancy — is broadly covered under most compliant insurance plans. The U.S. Preventive Services Task Force (USPSTF) designates routine prenatal screenings as preventive care, which means they must be covered at no cost to you when delivered by an in-network provider, even before you meet your deductible.

    Services that are typically covered include:

    • Routine prenatal office visits — usually every 4 weeks through week 28, every 2 weeks through week 36, then weekly until delivery
    • Blood tests and urinalysis — including complete blood count, blood type, Rh factor, and glucose screening for gestational diabetes
    • Genetic screening and counseling — such as cell-free fetal DNA testing, nuchal translucency ultrasound, and carrier screening for conditions like cystic fibrosis
    • Ultrasounds — typically covered at standard intervals, though additional scans may require prior authorization
    • Group B Streptococcus (GBS) testing — a routine late-pregnancy screening for bacterial infection
    • Tdap and flu vaccines — recommended during pregnancy and covered under preventive care guidelines
    • Folic acid supplementation counseling — and in many plans, over-the-counter prenatal vitamins with a prescription

    Research from the American College of Obstetricians and Gynecologists (ACOG) consistently shows that adequate prenatal care reduces rates of low birth weight, premature delivery, and maternal complications. Skipping visits due to cost concerns is associated with significantly worse outcomes for both mother and baby.

    One critical note: always verify that your OB-GYN, midwife, or maternal-fetal medicine specialist is in-network at the start of your pregnancy. Provider network status can change mid-year, and a single out-of-network visit can result in dramatically higher cost-sharing for you.

    Labor, Delivery, and Hospital Stay: What to Expect From Your Coverage

    The labor and delivery period is where maternity costs peak — and where coverage gaps most frequently catch patients off guard. According to the Health Care Cost Institute, inpatient maternity care accounts for the largest single category of hospital spending for women of reproductive age in the United States.

    Most insurance plans cover the following under your in-network benefits:

    • Hospital admission and facility fees for vaginal or cesarean delivery
    • Obstetric physician fees for your delivering OB-GYN or midwife
    • Anesthesia services — including epidural pain management
    • Operating room fees for cesarean sections
    • Neonatal care for a healthy newborn immediately after birth
    • Postpartum monitoring during your inpatient stay

    Federal law — specifically the Newborns’ and Mothers’ Health Protection Act — requires that insurance plans cover a minimum hospital stay of 48 hours after a vaginal delivery and 96 hours after a cesarean section. Your insurer cannot incentivize you to leave earlier or penalize your provider for recommending a longer stay when medically necessary.

    The surprise billing risk you must know about: Even when you deliver at an in-network hospital with your in-network OB-GYN, you may encounter out-of-network providers you didn’t choose — including the anesthesiologist, a neonatologist called in for your baby, or a hospitalist covering overnight shifts. The No Surprises Act, which went into full effect in 2022, offers significant federal protection against these unexpected bills. Under this law, you generally cannot be billed at out-of-network rates for emergency services or for in-network facility services where you had no meaningful choice of provider. If you receive a surprise bill that you believe violates these protections, you can file a complaint with the CMS.

    You should also confirm your hospital’s network status independently — call your insurer directly and ask them to verify in writing, not just verbally.

    Newborn Coverage: Adding Your Baby to Your Plan

    Under federal law, newborns are automatically covered under the mother’s health insurance plan for the first 30 days after birth — but this coverage is not permanent. You must formally enroll your newborn within your plan’s Special Enrollment Period, which is typically 30 to 60 days after birth depending on your insurer and plan type.

    Missing this window can result in your newborn being uninsured, with all medical costs falling entirely out of pocket. This is a critical administrative step that many new parents overlook in the exhaustion of early newborn care.

    Once enrolled, your newborn’s covered services will typically include:

    • Well-baby visits — following the AAP schedule at 2 weeks, 1 month, 2 months, 4 months, 6 months, and beyond
    • Immunizations — the full CDC-recommended childhood vaccine schedule, covered at no cost under preventive care
    • Newborn metabolic screening — standard state-mandated blood tests for conditions like PKU and congenital hypothyroidism
    • Hearing screening — required in most states and covered under preventive guidelines
    • Lactation support — breastfeeding counseling and breast pumps are covered under the ACA’s preventive services mandate for the mother

    According to the CDC, breastfeeding rates in the US have increased significantly over the past decade, partly due to improved insurance coverage of lactation support services. Research suggests that covered lactation consultant access is associated with longer breastfeeding duration and better maternal-infant health outcomes.

    For more information on how preventive services are covered across different plan types, see our detailed guide on Health Insurance for Preventive Care: What’s Covered.

    Postpartum Care: The Coverage Gap Most Parents Don’t See Coming

    Postpartum care — the medical attention a mother receives after delivery — has historically been one of the most underfunded areas of maternity coverage in the United States. The traditional model called for a single postpartum visit at 6 weeks, which most maternal health experts now regard as wholly inadequate.

    ACOG now recommends a more comprehensive postpartum care model that includes contact within the first 3 weeks after delivery and a full comprehensive visit by 12 weeks. In 2021, the American Rescue Plan Act made it easier for states to extend Medicaid postpartum coverage from 60 days to 12 months — and as of 2026, more than 40 states have adopted this extension.

    Services that should be covered under postpartum care include:

    • Postpartum depression screening and mental health referrals
    • Blood pressure monitoring (critical for detecting postpartum preeclampsia)
    • Wound care for cesarean incisions or perineal tears
    • Thyroid function testing, where indicated
    • Contraception counseling and provision
    • Pelvic floor physical therapy, increasingly recognized as medically necessary

    Postpartum depression (PPD) affects an estimated 1 in 8 women in the United States, according to the CDC. Clinical evidence strongly supports early screening and treatment, which may include therapy, medication, or both. If you’re experiencing persistent sadness, anxiety, difficulty bonding with your baby, or intrusive thoughts after delivery, contact your provider immediately — these are medical symptoms, not personal failings, and they are treatable.

    If you’re navigating mental health coverage as part of your postpartum care, our article on Health Insurance for Mental Health: What’s Actually Covered provides important detail on parity laws and your rights.

    High-Risk Pregnancies and Specialized Care

    Some pregnancies require additional monitoring or specialized care — and knowing how your insurance handles these situations in advance can prevent both medical delays and financial shock.

    Conditions that may classify a pregnancy as high-risk include gestational diabetes, preeclampsia, placenta previa, advanced maternal age (typically defined as 35 or older at delivery), multiple gestations (twins, triplets), and pre-existing chronic conditions such as hypertension, lupus, or Type 2 diabetes.

    High-risk pregnancies often involve referral to a maternal-fetal medicine (MFM) specialist, sometimes called a perinatologist. Most insurance plans cover MFM consultations when referred by your primary OB-GYN, but prior authorization is frequently required. Failing to obtain prior authorization — even for a medically urgent referral — can result in claim denial. Always confirm authorization before specialist visits.

    If your newborn requires a stay in the neonatal intensive care unit (NICU), costs escalate dramatically. The average NICU stay costs approximately $3,000 per day. Most plans cover NICU care, but review your out-of-pocket maximum carefully — this is the annual cap on what you’ll pay regardless of how high your bills climb. NICU families frequently hit their out-of-pocket maximum quickly.

    When to Call Your Doctor or Insurer: Red Flags That Can’t Wait

    Certain symptoms during and after pregnancy require immediate emergency care. Do not wait to call your insurance company or seek prior authorization for the following:

    • Sudden severe headache or visual disturbances during pregnancy — may indicate preeclampsia
    • Heavy vaginal bleeding at any point during pregnancy or postpartum
    • Decreased fetal movement after 28 weeks gestation
    • Signs of preterm labor before 37 weeks — regular contractions, pelvic pressure, or fluid leakage
    • Chest pain, shortness of breath, or leg swelling — may indicate blood clot (deep vein thrombosis or pulmonary embolism, which are more common during and after pregnancy)
    • High fever with chills or foul-smelling discharge postpartum — signs of infection
    • Thoughts of harming yourself or your baby — a psychiatric emergency requiring immediate care

    Under the Emergency Medical Treatment and Labor Act (EMTALA) and the ACA, your insurance plan must cover emergency services at any hospital — in-network or out-of-network — at in-network cost-sharing rates. You cannot be denied emergency care due to insurance status, and you cannot be required to obtain prior authorization before seeking emergency treatment.

    Frequently Asked Questions

    Q: Does health insurance cover IVF or fertility treatments before pregnancy?
    Fertility treatments such as in vitro fertilization (IVF) are not federally mandated as essential health benefits under the ACA. Coverage varies widely by state and plan. As of 2026, approximately 20 states have enacted fertility insurance mandates, but the scope differs. Check your specific plan documents and your state’s insurance commissioner website for details.

    Q: What if I lose my job and my insurance during pregnancy?
    Pregnancy qualifies as a special enrollment event, and losing job-based coverage triggers a Special Enrollment Period on the ACA Marketplace. You may also qualify for Medicaid if your income drops below threshold levels. The 60-day SEP window begins the day you lose coverage, not the day your employment ends.

    Q: Is a home birth or birth center delivery covered by insurance?
    Some plans cover licensed midwife-attended births in freestanding birth centers, but this varies significantly by insurer and state. Out-of-hospital birth is rarely covered at the same level as hospital birth. Always verify coverage specifics before choosing a birth setting.

    Q: Do I need a referral to see an OB-GYN during pregnancy?
    Most PPO plans allow you to see an OB-GYN directly without a referral from your primary care physician. HMO plans typically require a referral. Review your plan type before your first prenatal appointment to avoid unexpected out-of-pocket costs.

    Q: How does the deductible work when I have a baby?
    Your deductible applies to each person on your plan individually if you have a family deductible structure, or it may apply to the family unit collectively depending on your plan type. Your newborn, once enrolled, begins accumulating their own deductible from the date of birth. Understanding this structure helps you anticipate your true out-of-pocket exposure for the delivery year.

    Conclusion

    Maternity and newborn care is one of the most consequential — and costly — healthcare journeys an American family can take. The good news is that federal law provides meaningful protections: required coverage, minimum hospital stays, surprise billing safeguards, and postpartum mental health access.

    But the system still requires active engagement. Verify your providers are in-network early. Enroll your newborn within the enrollment window. Understand your out-of-pocket maximum. Ask questions before procedures, not after bills arrive.

    You deserve to focus on the health and joy of your growing family — not on decoding insurance paperwork at midnight. Knowing your rights and your coverage in advance puts you in the strongest possible position. When in doubt, always consult both your physician and a licensed insurance navigator or benefits coordinator who can help you interpret your specific plan documents.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Diabetes and Alcohol: What Every Diabetic Must Know

    Diabetes and Alcohol: What Every Diabetic Must Know

    Diabetes and Alcohol: What Every Diabetic Must Know

    Understanding how alcohol interacts with blood sugar could prevent a dangerous — and surprisingly common — medical emergency.

    Marcus, 54, had managed his type 2 diabetes for six years without a serious incident. Then, at a holiday party, he had a few drinks with dinner — skipped a snack before bed — and woke up at 2 a.m. in a cold sweat, confused and shaking. His wife recognized the signs of low blood sugar and acted quickly. Marcus was lucky. Not everyone is.

    According to the CDC, more than 38 million Americans are living with diabetes, and surveys from the National Institute on Alcohol Abuse and Alcoholism (NIAAA) suggest that adults with diabetes drink at rates similar to the general population. Yet many people with diabetes receive little guidance about how alcohol interacts with blood sugar, medications, and long-term complications.

    This article will walk you through exactly how alcohol affects blood sugar control, which risks matter most, how to drink more safely if you choose to, and when alcohol should be avoided entirely. If you’re managing diabetes — or caring for someone who is — this information could be lifesaving.

    How Alcohol Affects Blood Sugar: The Science Behind the Risk

    To understand why alcohol and diabetes can be a dangerous combination, it helps to know what your liver does when you drink.

    Normally, your liver has two jobs running in the background: processing substances in your blood and releasing stored glucose (glycogen) to keep blood sugar from dropping too low. When you drink alcohol, the liver prioritizes metabolizing the alcohol above everything else — including releasing that stored glucose.

    The result? Blood sugar can drop significantly, especially if you’ve taken insulin or certain oral diabetes medications. This condition — called hypoglycemia (low blood sugar, typically below 70 mg/dL) — can develop slowly over several hours and may occur while you’re asleep, making it particularly dangerous.

    A meta-analysis published in the journal Diabetes Care found that alcohol consumption was associated with a significantly increased risk of hypoglycemic episodes in people with both type 1 and type 2 diabetes, particularly when alcohol was consumed without food. Clinical evidence also indicates that the liver’s glucose-releasing function can remain impaired for up to 24 hours after drinking — meaning the risk doesn’t end when the party does.

    On the flip side, some alcoholic beverages — especially sugary cocktails, sweet wines, beer, and mixed drinks with juice — can cause a temporary spike in blood sugar before the hypoglycemic effect kicks in. This two-phase swing is one of the reasons alcohol makes diabetes management particularly unpredictable.

    Signs and Symptoms: Hypoglycemia vs. Intoxication

    One of the most dangerous aspects of alcohol and diabetes is how easily their symptoms overlap — and how often one is mistaken for the other.

    Symptoms of hypoglycemia include:

    • Shakiness or trembling
    • Sweating, especially at night
    • Dizziness or lightheadedness
    • Confusion or slurred speech
    • Rapid heartbeat
    • Irritability or sudden mood changes
    • Pale or clammy skin
    • In severe cases: unconsciousness or seizure

    Notice that confusion, slurred speech, and unsteady gait — all classic signs of low blood sugar — are also classic signs of alcohol intoxication. Friends, family members, even emergency personnel may misread a hypoglycemic episode as drunkenness, delaying critical treatment.

    Research from the American Diabetes Association (ADA) reinforces that people with diabetes should always carry fast-acting glucose (such as glucose tablets or juice) when drinking and should wear a medical ID bracelet indicating their condition so that first responders can make an accurate assessment quickly.

    If you’re experiencing confusion or shaking and you’re unsure whether it’s low blood sugar or alcohol, treat for low blood sugar first — eating 15 grams of fast-acting carbohydrates — and check your glucose if possible. Never assume it’s just the alcohol.

    Causes of Increased Risk: Who Is Most Vulnerable

    Not all people with diabetes face the same level of risk from alcohol. Several factors increase your vulnerability significantly.

    Medication type matters enormously. People taking insulin or sulfonylureas (a class of oral medications that stimulate insulin production, including glipizide and glimepiride) face the highest risk of alcohol-induced hypoglycemia. The combination of these medications with alcohol’s glucose-suppressing effect on the liver can cause blood sugar to plunge rapidly.

    Drinking on an empty stomach dramatically amplifies this effect. Without food slowing alcohol absorption and providing carbohydrates to maintain blood sugar, the liver’s impaired glucose release becomes critical.

    Additional risk factors include:

    • Long duration of diabetes — people who have had diabetes for many years may have impaired counter-regulatory hormone responses (the hormones that normally kick in to raise blood sugar)
    • Kidney disease or liver disease — both affect how alcohol and glucose are metabolized
    • Autonomic neuropathy — nerve damage affecting internal organ function can blunt the warning symptoms of hypoglycemia
    • Older age — adults over 60 tend to metabolize alcohol more slowly and may have less awareness of hypoglycemia symptoms
    • Skipping meals or eating very little — common when drinking socially

    According to the NIH, heavy alcohol use — defined as more than 14 drinks per week for men and more than 7 per week for women — is also independently associated with worsening insulin resistance and a higher risk of developing diabetic complications. This risk compounds over time.

    Diagnosis and Monitoring: What Your Numbers Tell You

    If you have diabetes and you drink alcohol, consistent blood sugar monitoring becomes even more critical. Your healthcare provider may recommend more frequent checks on days when you drink — and especially before bed.

    Most physicians recommend that people with diabetes who choose to drink alcohol should:

    • Check blood sugar before drinking
    • Check blood sugar during the event if drinking extends more than 1-2 hours
    • Check blood sugar before bed — and eat a carbohydrate-containing snack if glucose is at or below 100 mg/dL
    • Set an alarm or ask a partner to check on you overnight if you’ve consumed more than one drink

    Continuous glucose monitors (CGMs) — devices worn on the skin that track glucose levels in real time — are particularly valuable tools for people who drink. They provide alerts when blood sugar is dropping, even during sleep. For a comprehensive understanding of monitoring tools available to you, our guide on Blood Sugar Monitoring for Type 2 Diabetes covers CGMs, fingerstick devices, and how to interpret your readings.

    Your doctor may also monitor your A1C (a measure of average blood sugar over 2-3 months) more closely if you drink regularly, since chronic alcohol use is associated with greater A1C variability and harder-to-control blood sugar levels.

    Treatment and Management: Drinking More Safely With Diabetes

    The American Diabetes Association does not tell all people with diabetes to abstain from alcohol entirely — but it does provide clear guidelines for those who choose to drink. Here is what clinical evidence supports:

    Stick to moderate drinking limits. The ADA recommends no more than one drink per day for women and two drinks per day for men. One standard drink equals 12 oz of regular beer, 5 oz of wine, or 1.5 oz of spirits.

    Never drink on an empty stomach. Always consume alcohol with a meal or substantial snack containing protein, fat, and complex carbohydrates. This slows alcohol absorption and helps buffer blood sugar drops.

    Choose lower-carbohydrate options. Dry wines, light beers, and spirits mixed with sparkling water or club soda are preferable to sweet cocktails, sugary mixers, or craft beers, which can contain 20-30 grams of carbohydrates per serving and cause unpredictable blood sugar spikes.

    Avoid binge drinking entirely. Consuming four or more drinks in a short period overwhelms the liver’s capacity and dramatically increases hypoglycemia risk over the next several hours. Research suggests that even one heavy episode can destabilize blood sugar control for more than 24 hours.

    Tell someone you trust. When you’re out, let a friend or family member know you have diabetes. Make sure they know the signs of hypoglycemia and what to do — including calling 911 if you become unconscious.

    Talk to your pharmacist and doctor about your medications. Some diabetes medications interact with alcohol beyond hypoglycemia risk. Metformin, for example, carries a rare but serious risk of lactic acidosis (a dangerous buildup of lactic acid in the blood) in people who drink heavily or have liver disease. Your healthcare provider can help you understand your specific medication interactions.

    Pair these strategies with a well-structured eating plan. Our resource on Diabetes Meal Planning: Build a Plate That Controls Blood Sugar can help you build meals that provide a stable glucose foundation — especially on days when you plan to drink.

    Living With Diabetes: Long-Term Alcohol and Complication Risk

    Beyond blood sugar swings, regular alcohol use affects the long-term trajectory of diabetes and its complications in several important ways.

    Heart health: People with diabetes already face two to four times the risk of cardiovascular disease compared to those without, according to the American Heart Association. Heavy alcohol use raises blood pressure, increases triglycerides, and contributes to irregular heart rhythms — all of which worsen cardiovascular risk. Moderate alcohol consumption has been studied for potential heart-protective effects, but most cardiologists and endocrinologists advise against drinking for heart health, particularly in people who already have elevated risk.

    Liver health: The liver plays a central role in both glucose metabolism and detoxification. Non-alcoholic fatty liver disease (NAFLD) — which is closely linked to insulin resistance — is already common in people with type 2 diabetes. Adding alcohol to the equation can accelerate liver damage and worsen insulin resistance further.

    Nerve health: Diabetic peripheral neuropathy (nerve damage, often in the feet and legs) is a complication affecting up to 50% of people with diabetes over their lifetime, according to the NIH. Alcohol is itself a neurotoxin and can accelerate nerve damage independently of blood sugar control — making it a particularly harmful combination for people already managing neuropathy.

    Mental health: Research published in Diabetes Care found that depression is two to three times more common in people with diabetes than in the general population. Alcohol is a central nervous system depressant, and while it may feel like it reduces stress or anxiety in the short term, regular use worsens depression and anxiety over time — making diabetes self-management harder. Stress itself worsens blood sugar control, as explored in our article on how cortisol and stress affect metabolic health.

    When to Call Your Doctor — and When to Call 911

    Some situations require immediate emergency response. Do not wait to call 911 if someone with diabetes who has been drinking shows any of the following:

    • Loss of consciousness or unresponsiveness
    • Seizure
    • Extreme confusion or inability to communicate
    • Blood sugar below 50 mg/dL that does not respond to oral glucose treatment
    • Severe vomiting that prevents oral treatment for low blood sugar

    Call your doctor — non-emergently but promptly — if you notice:

    • Repeated hypoglycemic episodes after drinking, even mild ones
    • Greater-than-usual difficulty controlling blood sugar on days following alcohol use
    • Signs of worsening neuropathy, such as increased numbness or tingling in the feet
    • Any signs of liver problems: yellowing skin, dark urine, abdominal pain
    • You feel you cannot reduce or stop drinking even when you want to

    That last point matters significantly. The NIAAA estimates that approximately 14.5 million Americans aged 12 and older have alcohol use disorder. If alcohol has become difficult to control, speaking honestly with your doctor opens the door to effective, evidence-based treatment options — including behavioral therapy and FDA-approved medications — without judgment.

    Frequently Asked Questions

    Can people with type 2 diabetes drink alcohol at all?
    Many people with well-controlled type 2 diabetes can consume alcohol in moderation — one drink per day for women, two for men — according to ADA guidelines. However, this varies significantly depending on your medications, kidney and liver health, and current blood sugar control. Always discuss this with your physician before drinking.

    Does alcohol raise or lower blood sugar?
    Both, depending on timing and what you drink. In the short term, sugary alcoholic beverages can raise blood sugar. Over the following hours, alcohol suppresses the liver’s ability to release stored glucose, which can cause a significant and dangerous drop in blood sugar — especially overnight. This two-phase effect makes monitoring critical.

    What is the safest alcoholic drink for someone with diabetes?
    Clinical evidence suggests that dry wines, light beers, and spirits mixed with zero-calorie mixers (like sparkling water or diet soda) have less impact on blood sugar than sweet cocktails, regular beer, or sugary mixed drinks. However, no alcohol is entirely safe, and individual responses vary significantly. This varies from person to person based on metabolism, medications, and overall health.

    How long does alcohol affect blood sugar after drinking?
    Research suggests the liver’s glucose-releasing function can be impaired for up to 12-24 hours after drinking. This means a person with diabetes may experience hypoglycemia the morning after a night of drinking — even without feeling intoxicated. Monitoring blood sugar the following morning is strongly recommended.

    Should I adjust my diabetes medication when I drink?
    Never adjust your medication dose on your own based on alcohol consumption. Speak with your doctor or pharmacist about your specific situation. Some adjustments may be appropriate, but this decision requires medical supervision and depends on your specific drug regimen, kidney function, and glucose control history.

    Conclusion

    Alcohol and diabetes can coexist — but only with knowledge, planning, and honest conversations with your healthcare team. The risks are real and specific: hypoglycemia that looks like intoxication, overnight blood sugar crashes, worsening nerve damage, and harder-to-control A1C levels. But the risks are also manageable when you understand them.

    You don’t have to feel isolated or uncertain about this topic. Bring your questions about alcohol to your next doctor’s appointment. Be honest about how much and how often you drink. Ask about your specific medications and what interactions matter for you.

    With the right information and the right support team, you can make informed choices that protect your health — without sacrificing your quality of life.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Weight Loss and Stress: How Cortisol Blocks Your Progress

    Weight Loss and Stress: How Cortisol Blocks Your Progress

    Weight Loss and Stress: How Cortisol Blocks Your Progress

    Chronic stress doesn’t just exhaust your mind — it triggers a hormonal cascade that can make losing weight feel nearly impossible.

    Introduction

    Mark, 47, had been eating clean and exercising five days a week for three months. The scale barely moved. His doctor ran labs, adjusted his approach, and eventually asked a question that changed everything: “How’s your stress level at work?”

    According to the American Psychological Association, more than 75% of American adults report experiencing moderate to high levels of stress regularly. What most people don’t realize is that chronic stress — the kind that lingers for weeks, months, or even years — has a direct physiological impact on weight loss. It disrupts hormones, increases fat storage, triggers cravings, and undermines even the most disciplined diet and exercise plan.

    In this guide, you’ll learn exactly how chronic stress and cortisol affect your body weight, what the latest clinical research says about the stress-fat connection, and evidence-based strategies to manage stress so your weight loss efforts can actually work.

    What Is the Stress-Weight Connection?

    When your body perceives a threat — whether it’s a deadline, a difficult relationship, financial pressure, or physical pain — it activates what scientists call the hypothalamic-pituitary-adrenal (HPA) axis. This is your body’s built-in alarm system.

    Part of that response involves releasing a hormone called cortisol from the adrenal glands. In short bursts, cortisol is actually protective — it sharpens your focus, mobilizes energy, and helps you respond to danger.

    The problem is chronic stress. When stress persists day after day, cortisol levels remain elevated. And sustained high cortisol has been linked to increased appetite, preferential fat storage around the abdomen, disrupted sleep, muscle breakdown, and insulin resistance — a combination that directly opposes healthy weight loss.

    According to research published by the NIH, elevated cortisol is associated with significantly higher body mass index (BMI) and waist circumference, particularly in adults over 35. This is not a willpower issue — it is a hormonal and metabolic one.

    Signs and Symptoms That Stress Is Affecting Your Weight

    Stress-related weight challenges don’t always look the way you’d expect. Here are common signs that your weight struggles may have a stress component:

    Early and moderate signs:

    • Cravings for high-fat, high-sugar, or salty foods — especially in the evening
    • Difficulty losing weight despite a caloric deficit
    • Belly fat that accumulates even with regular exercise
    • Feeling hungry shortly after eating a full meal
    • Low motivation or energy for physical activity
    • Disrupted sleep patterns (trouble falling or staying asleep)
    • Mood swings that trigger emotional or binge eating

    Advanced or chronic signs:

    • Persistent weight gain over months despite dietary efforts
    • Fatigue that doesn’t improve with rest
    • Signs of insulin resistance (increased thirst, energy crashes after meals)
    • Elevated fasting blood glucose on routine labs
    • High blood pressure alongside weight gain

    A 2022 meta-analysis in Obesity Reviews found that individuals with clinically elevated stress markers were significantly more likely to experience weight regain after intentional weight loss — even when their dietary behaviors were otherwise consistent. This varies from person to person, but the pattern is well-documented across multiple studies.

    Causes and Risk Factors: Why Stress Promotes Fat Storage

    Understanding the biology helps you stop blaming yourself and start targeting the actual problem. Here’s what happens in your body when stress is chronic:

    1. Cortisol increases appetite and cravings. Research from the University of California, San Francisco, found that cortisol directly stimulates the brain’s reward center, increasing cravings for calorie-dense, palatable foods — the so-called “comfort foods.” This is not weakness. It’s brain chemistry.

    2. Cortisol promotes visceral fat storage. Visceral fat is the deep abdominal fat that surrounds internal organs. Cortisol increases the activity of an enzyme called lipoprotein lipase in abdominal fat cells, which tells your body to preferentially store fat in the belly. The CDC identifies excess visceral fat as a major risk factor for heart disease, type 2 diabetes, and metabolic syndrome.

    3. Stress disrupts insulin signaling. Cortisol raises blood glucose to prepare the body for fight-or-flight. Over time, this repeated glucose spike can blunt insulin sensitivity — a condition known as insulin resistance — which makes fat loss more difficult and increases type 2 diabetes risk.

    4. Stress impairs sleep, which impairs metabolism. Poor sleep is independently linked to increased ghrelin (the hunger hormone) and decreased leptin (the satiety hormone). When you’re sleep-deprived due to stress, you’re physiologically set up to overeat the next day.

    5. Stress reduces physical activity. When cortisol is chronically high, fatigue, brain fog, and low mood follow — all of which reduce the motivation and energy needed to exercise consistently.

    Risk factors that amplify the stress-weight connection include being over 40 (when cortisol sensitivity increases), having a history of anxiety or depression, working high-pressure jobs, experiencing relationship conflict, or managing caregiving responsibilities — all common realities for adults aged 30 to 70 in the US.

    Diagnosis: What to Expect When You Talk to Your Doctor

    If you suspect that chronic stress is contributing to your weight challenges, a visit to your primary care physician is the right starting point. There is no single “stress test,” but your doctor can evaluate several key markers:

    • Fasting cortisol blood test: Measures morning cortisol levels, which are highest in healthy individuals and may be dysregulated under chronic stress
    • DHEA-S levels: An adrenal hormone that often becomes imbalanced with chronic HPA axis activation
    • Fasting insulin and glucose: To screen for insulin resistance or prediabetes linked to stress-driven blood sugar dysregulation
    • Thyroid panel: Chronic stress can suppress thyroid function, further slowing metabolism
    • Lipid panel and blood pressure: Both affected by prolonged cortisol elevation
    • Mental health screening tools: Tools like the PHQ-9 for depression or GAD-7 for anxiety are commonly used to assess psychological stress

    Be honest with your doctor about your stress levels, sleep quality, and eating patterns. Clinical evidence consistently shows that patients who report their full lifestyle picture receive more targeted and effective treatment plans. Most physicians recommend annual preventive labs that include many of these markers — ask specifically if your results may relate to stress and metabolism.

    Treatment Options: Managing Stress to Support Weight Loss

    Treating the stress-weight connection requires a multi-pronged approach. Here is what clinical evidence supports:

    Cognitive Behavioral Therapy (CBT): Research from Harvard Medical School suggests that CBT is one of the most effective interventions for chronic stress, anxiety, and the emotional eating patterns that accompany them. CBT helps you identify and reframe thought patterns that trigger stress responses. Many programs are now available through telehealth platforms, making access easier than ever.

    Mindfulness-Based Stress Reduction (MBSR): A structured program developed at the University of Massachusetts, MBSR has been shown in multiple clinical trials to reduce cortisol levels, lower emotional eating frequency, and improve weight outcomes when combined with dietary changes. You can explore related strategies in our article on Mindful Eating for Weight Loss: What Science Really Says.

    Regular aerobic exercise: Exercise is one of the most powerful cortisol regulators available. A 2021 study in Psychoneuroendocrinology found that moderate-intensity aerobic exercise (30 minutes, five days per week) significantly reduced both perceived stress and morning cortisol over 12 weeks — while also improving body composition.

    Sleep optimization: Treating sleep disorders is a critical but often overlooked component of stress and weight management. The American Academy of Sleep Medicine recommends 7–9 hours of quality sleep for adults. If stress is disrupting your sleep, discuss options with your doctor, including sleep hygiene strategies, CBT for insomnia (CBT-I), or medication evaluation if appropriate.

    Dietary support: Research suggests that diets high in protein and fiber help stabilize blood sugar and reduce cortisol-driven cravings. Reducing ultra-processed food intake and increasing whole food consumption supports both mood regulation and weight management. For practical guidance on protein’s role in weight loss, see our article on High-Protein Diet for Weight Loss: What Science Says.

    Pharmacological options: In some cases, your physician may discuss medications that address anxiety, depression, or sleep disorders as part of a comprehensive plan. These decisions should always be made in partnership with your healthcare provider, based on your individual medical history.

    Living With Chronic Stress: Day-to-Day Management Strategies

    Managing the stress-weight connection is not a short-term fix — it’s a lifestyle recalibration. Here are evidence-based practices that support long-term success:

    Build a consistent sleep routine. Going to bed and waking at the same time daily stabilizes cortisol’s natural rhythm. Avoid screens for at least 30 minutes before bed and keep your bedroom cool and dark.

    Practice diaphragmatic breathing. Deep, slow breathing activates the parasympathetic nervous system, counteracting the fight-or-flight stress response. Even five minutes of intentional breathing before meals can reduce cortisol and improve digestion.

    Prioritize social connection. Research from Brigham Young University found that social isolation increases cortisol and mortality risk. Regular, meaningful interaction with friends, family, or support groups acts as a biological buffer against chronic stress.

    Set realistic weight loss goals. The pressure of an aggressive weight loss target can itself become a stressor. Most physicians recommend aiming for 0.5 to 1 pound of loss per week as a sustainable, physiologically reasonable target that doesn’t activate additional stress biology.

    Limit caffeine and alcohol. Both can elevate cortisol and disrupt sleep. Clinical evidence indicates that reducing alcohol intake alone often leads to measurable improvements in cortisol levels and body weight within four to eight weeks.

    Work with a registered dietitian. A dietitian who understands the stress-metabolism relationship can help you build an eating plan that supports cortisol balance — rather than one that adds more pressure to your plate.

    When to Call Your Doctor or Seek Emergency Care

    Most stress-related weight challenges are manageable with lifestyle interventions and primary care support. However, certain signs require prompt medical attention:

    Schedule an appointment promptly if you notice:

    • Unexplained rapid weight gain (more than 5 pounds in one to two weeks without dietary changes)
    • Persistent fatigue that does not improve with rest
    • Symptoms of depression lasting more than two weeks (low mood, hopelessness, loss of interest)
    • Blood glucose readings consistently above 130 mg/dL fasting
    • Signs of adrenal dysfunction: extreme fatigue, salt cravings, dizziness on standing, or unusual skin changes

    Seek emergency care immediately if you experience:

    • Chest pain or pressure, especially with stress or exertion
    • Sudden severe headache or vision changes (possible hypertensive crisis)
    • Thoughts of self-harm or suicide — call 988 (Suicide and Crisis Lifeline) immediately
    • Loss of consciousness or extreme confusion

    Always tell your doctor if you’ve been under significant stress for an extended period. It is clinically relevant information that affects your care plan.

    Frequently Asked Questions

    Can stress alone cause weight gain even if I’m eating healthy?
    Yes. Clinical evidence indicates that chronically elevated cortisol can cause the body to store fat more efficiently — particularly in the abdominal area — even in the presence of a healthy diet. Hormonal factors like insulin resistance and disrupted hunger signaling can compound this effect. That said, this varies from person to person, and a medical evaluation can help clarify whether stress is a primary driver in your specific case.

    How long does it take for stress reduction to impact weight?
    Research suggests that meaningful reductions in cortisol can occur within four to eight weeks of consistent stress management practices, such as daily exercise, improved sleep, and mindfulness. However, visible weight loss changes may take longer and depend on other lifestyle factors. Patience and consistency are key.

    Is cortisol testing worth doing?
    A fasting morning cortisol test can provide useful information, but its interpretation requires clinical context. Your doctor may order it if your symptoms suggest HPA axis dysregulation. It is rarely the first test ordered unless adrenal disease (such as Cushing’s syndrome) is suspected. Discuss whether this test is appropriate for your situation.

    Does exercise reduce cortisol or make it worse?
    Moderate-intensity exercise — such as brisk walking, cycling, or swimming — consistently reduces cortisol and supports weight loss. However, very high-intensity or excessive exercise can temporarily spike cortisol. Most physicians recommend prioritizing moderate, enjoyable movement over extreme workouts if you’re managing chronic stress.

    Can medications help with stress-related weight gain?
    In some cases, medications that treat underlying anxiety or depression may indirectly support weight management by normalizing cortisol patterns and improving sleep. However, some medications in these categories can also affect body weight. This is a highly individualized conversation to have with your prescribing physician — never start or stop medications without medical guidance.

    Conclusion

    Chronic stress is one of the most underestimated obstacles to successful weight loss in American adults. If you’ve been doing “everything right” and still struggling to lose weight, the missing piece may not be your diet or your workout — it may be your nervous system.

    The good news is that the stress-weight connection is well understood, and there are evidence-based tools that work. From CBT and mindfulness to sleep optimization and movement, you have real options. The most important step is talking openly with your healthcare provider so you can build a plan that addresses the full picture — not just calories in and calories out.

    Your health is worth that conversation.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Online Therapy for OCD: Does It Really Work?

    Online Therapy for OCD: Does It Really Work?

    Online Therapy for OCD: Does It Really Work?

    Obsessive-compulsive disorder affects millions of Americans — and evidence-based online therapy is changing how people access life-changing treatment.

    Introduction

    Marcus, 41, spent nearly two hours every morning checking the locks on his front door before leaving for work. He knew, rationally, that the door was locked — but the anxiety wouldn’t let him go until he checked again and again. He had struggled with obsessive-compulsive disorder for over a decade but never sought professional help, partly because finding an OCD specialist near him felt impossible.

    That changed when he started online therapy with a licensed therapist trained in Exposure and Response Prevention (ERP), the gold-standard treatment for OCD. Within four months, his morning ritual had shrunk to under ten minutes.

    According to the National Institute of Mental Health (NIMH), OCD affects approximately 2.3% of American adults at some point in their lives — yet fewer than half ever receive adequate, evidence-based treatment. Online therapy platforms are working to close that gap. In this guide, you’ll learn how online therapy for OCD works, what treatment approaches are most effective, and what to look for when choosing a provider.


    What Is OCD and Why Is It Often Undertreated?

    Obsessive-compulsive disorder (OCD) is a chronic mental health condition characterized by two core features: obsessions and compulsions. Obsessions are unwanted, intrusive thoughts, images, or urges that cause significant distress. Compulsions are repetitive behaviors or mental acts performed in an attempt to reduce that distress or prevent a feared outcome.

    Common obsession themes include fears of contamination, harm, symmetry, or forbidden thoughts (such as religious or sexual intrusive thoughts). Compulsions often include excessive washing, checking, counting, arranging, or mental rituals like silently repeating phrases.

    Critically, OCD is not about being “neat” or “a little OCD.” For those living with it, the cycle of obsessions and compulsions can consume hours each day and severely impair work, relationships, and quality of life.

    The NIMH reports that the average person with OCD waits 14 to 17 years before receiving an accurate diagnosis and appropriate treatment. Two major barriers explain this delay: the stigma around intrusive thoughts, and the scarcity of clinicians specifically trained in ERP — the frontline behavioral treatment for OCD. Online therapy directly addresses both of these barriers.


    Signs and Symptoms: Recognizing OCD in Adults

    OCD can look very different from one person to the next. Many adults are surprised to learn their long-standing behaviors or thought patterns meet the clinical criteria. Here are the most common presentations:

    Early or Mild Signs

    • Intrusive, repetitive thoughts that feel distressing and out of character
    • Mild rituals that provide short-term relief (e.g., re-reading texts multiple times before sending)
    • Avoidance of triggering situations (e.g., avoiding sharp objects due to harm obsessions)
    • Excessive doubt or difficulty making decisions
    • Need for reassurance from others repeatedly

    More Severe or Advanced Signs

    • Rituals consuming more than one hour per day
    • Significant interference with work, school, or relationships
    • Extreme avoidance of everyday activities
    • Depression or secondary anxiety stemming from OCD
    • Social isolation due to shame or time lost to rituals

    A 2023 meta-analysis published in JAMA Psychiatry found that adults with untreated OCD had significantly higher rates of depression, anxiety disorders, and functional impairment compared to the general population — reinforcing the urgency of early intervention.


    What Types of Online Therapy Work Best for OCD?

    Not all therapy approaches are equally effective for OCD. This distinction is especially important when choosing an online therapy provider, because the type of therapy matters as much as the format of delivery.

    Exposure and Response Prevention (ERP)

    ERP is considered the gold-standard psychological treatment for OCD and is recommended by the American Psychological Association (APA), the International OCD Foundation (IOCDF), and the Mayo Clinic. It involves two components:

    • Exposure: Gradually confronting feared thoughts, situations, or objects without avoidance
    • Response Prevention: Resisting the urge to perform compulsions in response to the anxiety

    Over time, ERP helps the brain learn that feared outcomes are either unlikely or tolerable — reducing the anxiety that drives compulsions. A landmark NIH-funded trial found that ERP produced clinically significant improvement in 60 to 80% of patients who completed a full course of treatment.

    The good news: clinical research suggests ERP delivered online is just as effective as in-person ERP for most individuals with mild to moderate OCD. A 2022 randomized controlled trial published in the Journal of Anxiety Disorders found no statistically significant difference in symptom reduction between videoconference-based ERP and face-to-face ERP over a 16-week period.

    Cognitive Behavioral Therapy (CBT) with OCD Focus

    CBT for OCD helps individuals identify and reframe distorted beliefs that fuel obsessions — such as “having a bad thought means I’m a bad person” or “if I don’t check, something terrible will happen.” CBT is often used alongside ERP and is widely available through online platforms.

    Acceptance and Commitment Therapy (ACT)

    ACT teaches psychological flexibility — accepting intrusive thoughts without fusing with them or acting on compulsions. Research suggests ACT may be a useful adjunct or alternative for individuals who struggle with traditional ERP, though it is generally considered a second-line approach for OCD specifically.

    Medication Support

    Online therapy does not replace medication when it’s clinically indicated. The FDA has approved several serotonin reuptake inhibitors (SRIs) for OCD treatment. Many online therapy platforms now offer integrated psychiatric services where a prescriber can evaluate whether medication is appropriate alongside therapy. Always discuss medication decisions with a licensed psychiatrist or physician.


    Advantages of Online Therapy for OCD

    Online therapy offers specific advantages for people with OCD that go beyond simple convenience.

    Access to OCD Specialists

    One of the most significant challenges in treating OCD is finding a clinician trained in ERP. The International OCD Foundation estimates that only a fraction of licensed therapists have advanced training in this technique. Online platforms can connect you with verified ERP-trained therapists regardless of your geographic location — a game changer for people in rural areas or underserved communities.

    Therapy in Your Natural Environment

    OCD is often triggered by specific environments — your home, your car, your workplace. Online therapy allows exposures to be conducted in real-world settings with your therapist present via video, which some clinicians believe may accelerate generalization of treatment gains.

    Reduced Avoidance Barriers

    For many people with OCD, the thought of leaving the house, sitting in a waiting room, or touching surfaces in a clinic triggers anxiety before therapy even begins. Online access removes those barriers and helps people engage with treatment they might otherwise avoid entirely.

    Cost and Schedule Flexibility

    Online platforms often offer more scheduling flexibility and competitive pricing compared to traditional outpatient therapy. Many are now accepted by major insurance plans following the Mental Health Parity and Addiction Equity Act. If you’re exploring insurance coverage for mental health services, our guide on Health Insurance for Mental Health: What’s Actually Covered offers detailed information on what your plan may include.


    Limitations and When Online Therapy May Not Be Enough

    Online therapy is highly effective for mild to moderate OCD, but it is important to be honest about its limitations.

    Research suggests that individuals with severe OCD — particularly those with significant functional impairment, co-occurring psychiatric conditions, or safety concerns — may need a higher level of care. Intensive outpatient programs (IOPs), residential treatment, or in-person care with a specialized OCD center may be more appropriate in these cases.

    Additionally, online therapy may be less suitable if you:

    • Have limited access to reliable internet or private space for sessions
    • Are experiencing suicidal ideation or self-harm behaviors
    • Have a complex psychiatric history requiring close in-person monitoring
    • Need exposures that require specialized in-person tools or settings

    This variation from person to person is real, and a thorough initial evaluation by a licensed clinician is essential before starting any treatment program.


    How to Choose an Online Therapy Platform for OCD

    Not all online therapy platforms are equally equipped to treat OCD. Here’s what to look for:

    • ERP-trained therapists: Confirm that therapists have documented training or certification in ERP for OCD. Ask directly before booking.
    • Licensed professionals: All therapists should hold active licensure (LCSW, LPC, PhD, PsyD) in your state.
    • HIPAA-compliant platform: Ensure all video sessions and communications are encrypted and HIPAA-compliant.
    • Insurance acceptance: Check whether the platform accepts your health insurance, including Medicaid or Medicare if applicable.
    • Availability of psychiatric services: If you may need medication, choose a platform that offers integrated psychiatric evaluation.
    • OCD-specific intake process: Look for platforms that use validated tools like the Yale-Brown Obsessive Compulsive Scale (Y-BOCS) to assess severity at intake.

    Major platforms such as NOCD — which specializes specifically in OCD — as well as BetterHelp, Talkspace (with OCD filtering), and Brightside have expanded their OCD-trained therapist networks significantly in recent years. The IOCDF’s provider directory is also an excellent starting point for finding verified ERP specialists who offer telehealth sessions.


    When to Call Your Doctor or Seek Emergency Care

    OCD itself is not a psychiatric emergency, but certain situations require immediate attention. Contact a healthcare provider or crisis line right away if you or someone you know experiences:

    • Thoughts of suicide or self-harm
    • Inability to care for yourself due to OCD severity (not eating, not leaving the house for days)
    • Sudden, dramatic worsening of OCD symptoms — particularly in children or adolescents, which may signal PANDAS (Pediatric Autoimmune Neuropsychiatric Disorders Associated with Streptococcal Infections)
    • Psychotic features alongside OCD symptoms (requires urgent psychiatric evaluation)

    If you are in crisis, contact the 988 Suicide and Crisis Lifeline by calling or texting 988. For non-emergency mental health concerns, your primary care physician can provide a referral or initial evaluation and help you navigate treatment options.

    At your next routine appointment, consider telling your doctor: “I’ve been experiencing intrusive thoughts and repetitive behaviors that are affecting my daily life. I’d like to be screened for OCD and get a referral to a therapist trained in ERP.”


    Frequently Asked Questions About Online Therapy for OCD

    Is online ERP therapy as effective as in-person ERP?

    For most adults with mild to moderate OCD, clinical evidence indicates that online ERP is comparably effective to in-person ERP. A 2022 randomized controlled trial found no significant difference in outcomes between the two formats over 16 weeks. However, individual variation exists, and very severe cases may benefit from in-person or intensive treatment formats.

    How long does online therapy for OCD typically take?

    Most people with OCD require 12 to 20 sessions of ERP to achieve meaningful symptom reduction, according to the IOCDF. This can span three to five months of weekly or biweekly sessions. Maintenance sessions may be recommended afterward to prevent relapse.

    Can I do online therapy for OCD while also taking medication?

    Yes, and in many cases this combination is recommended. Clinical guidelines from NIMH suggest that the combination of ERP and medication (typically an FDA-approved SRI) is more effective than either treatment alone for moderate to severe OCD. Online platforms that offer integrated psychiatric care can facilitate both simultaneously.

    How do I know if what I’m experiencing is OCD or just anxiety?

    While OCD and anxiety disorders share features, OCD is specifically defined by the presence of both obsessions and compulsions that are distressing and time-consuming. Many people with OCD are also diagnosed with generalized anxiety or other anxiety disorders. A licensed clinician can administer validated tools like the Y-BOCS to provide a proper diagnosis. You may also find our overview of Online Therapy for Depression useful if you’re managing overlapping mood symptoms.

    Does insurance cover online therapy for OCD?

    Many insurance plans — including employer-sponsored plans, Medicaid, and Medicare Advantage — now cover telehealth mental health services under the Mental Health Parity and Addiction Equity Act. Coverage varies by plan and provider, so it’s important to verify your benefits before starting treatment. Our detailed guide on Health Insurance for Mental Health: What’s Actually Covered can help you understand your options.


    Conclusion

    Living with OCD is genuinely hard — but it is also one of the most treatable mental health conditions when the right intervention is applied. Evidence-based online therapy, particularly ERP delivered by a trained and licensed clinician, has strong clinical support and is making specialized care accessible to millions of Americans who previously had nowhere to turn.

    You don’t have to live with hours of rituals, intrusive thoughts, or avoidance behaviors controlling your day. Whether your OCD is mild or has persisted for years, today’s online therapy options offer a real, evidence-backed path forward — from your own home, on your own schedule.

    The first step is speaking with a healthcare provider or licensed therapist who can conduct a proper evaluation. From there, you and your care team can build a treatment plan that fits your life. Recovery is possible, and it starts with reaching out.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • PTSD: Symptoms, Causes, and Treatment Options

    PTSD: Symptoms, Causes, and Treatment Options

    Post-traumatic stress disorder affects more than 13 million Americans each year — and many go years without getting the help they need.

    Introduction

    Marcus was a 44-year-old construction supervisor who seemed fine on the outside. He went to work, came home, watched the game. But every time a car backfired or a coworker dropped something loud, his heart would race, his palms would sweat, and his mind would flash back to the accident he had witnessed three years earlier. He wasn't fine — he was living with PTSD, and he didn't even know it.

    Post-traumatic stress disorder (PTSD) is one of the most misunderstood mental health conditions in the United States. It's not a sign of weakness. It's not something only combat veterans experience. And it is, in most cases, highly treatable.

    In this guide, you'll learn what PTSD actually is, how it develops, what the warning signs look like, and — most importantly — what evidence-based treatments can help you or someone you love start to heal.

    What Is PTSD?

    Post-traumatic stress disorder is a psychiatric condition that can develop after someone experiences or witnesses a traumatic event — such as a serious accident, physical or sexual assault, combat, natural disaster, or the sudden death of a loved one.

    The key distinction between PTSD and a normal stress response is duration and severity. It's completely normal to feel shaken, anxious, or on edge after a traumatic event. Most people recover naturally within a few weeks. With PTSD, however, the symptoms persist for more than one month and interfere significantly with daily life — relationships, work, physical health, and overall well-being.

    According to the National Center for PTSD (part of the U.S. Department of Veterans Affairs), approximately 6 out of every 100 Americans will develop PTSD at some point in their lifetime. Women are more likely to be diagnosed than men — about 10% of women versus 4% of men — though researchers believe that difference may partly reflect underreporting by men.

    PTSD is classified by the Diagnostic and Statistical Manual of Mental Disorders (DSM-5) as a trauma- and stressor-related disorder. It's not a character flaw. It's a diagnosable medical condition rooted in how the brain processes overwhelming experiences.

    Signs and Symptoms of PTSD

    PTSD doesn't look the same in everyone. Symptoms typically fall into four major categories, and a diagnosis generally requires that a person experience symptoms from each category for at least one month.

    1. Re-experiencing Symptoms

    • Intrusive flashbacks — feeling like the trauma is happening again
    • Recurring nightmares about the traumatic event
    • Severe emotional or physical reactions to reminders (elevated heart rate, sweating, shaking)
    • Unwanted, distressing memories that are difficult to control

    2. Avoidance Symptoms

    • Deliberately avoiding people, places, or activities that trigger memories
    • Refusing to talk about the event
    • Withdrawing from relationships and social situations
    • Feeling emotionally numb or detached from others

    3. Negative Changes in Thinking and Mood

    • Persistent feelings of guilt, shame, or self-blame
    • Difficulty remembering key details of the traumatic event
    • Feeling hopeless about the future
    • Loss of interest in activities that used to bring joy
    • Feeling disconnected or estranged from people around you

    4. Hyperarousal and Reactivity Symptoms

    • Being easily startled or "on edge" most of the time
    • Irritability, angry outbursts, or aggressive behavior
    • Trouble concentrating or staying focused
    • Difficulty falling or staying asleep
    • Reckless or self-destructive behavior

    A large-scale study published in the journal JAMA Psychiatry found that individuals with PTSD are significantly more likely to also experience depression, anxiety disorders, and substance use disorders — making early identification and treatment especially important.

    Causes and Risk Factors

    PTSD can follow any event that a person experiences as life-threatening, deeply disturbing, or overwhelming — even if outsiders might view the event differently. Trauma is subjective. What matters is how the nervous system responds.

    Common Traumatic Events That Can Lead to PTSD

    • Military combat or exposure to war
    • Sexual assault or childhood sexual abuse
    • Physical assault or domestic violence
    • Serious accidents (vehicle crashes, workplace injuries)
    • Natural disasters (hurricanes, tornadoes, wildfires)
    • Sudden or violent loss of a loved one
    • Medical trauma (ICU stays, life-threatening diagnoses)
    • Witnessing violence or a traumatic death

    Risk Factors That Increase Vulnerability

    Not everyone who experiences trauma develops PTSD. Research suggests the following factors can increase the likelihood:

    • Biological factors: A family history of anxiety or depression, variations in stress-response hormones (such as cortisol and adrenaline), and genetic predisposition to heightened fear responses
    • Psychological factors: Prior trauma — especially in childhood — history of mental health conditions, limited coping skills
    • Social factors: Lack of social support after the event, ongoing stress, living in high-crime or high-risk environments
    • Severity of the trauma: More prolonged, personal, or repeated trauma (such as ongoing abuse) tends to carry a higher risk than a single isolated event

    According to the CDC's Adverse Childhood Experiences (ACE) study, adults who experienced multiple forms of childhood trauma face significantly elevated risk for a range of mental health conditions, including PTSD, well into adulthood.

    Diagnosis: What to Expect

    If you suspect you or someone you care about may have PTSD, the first step is speaking with a qualified healthcare provider — your primary care physician, a psychiatrist, or a licensed therapist who specializes in trauma.

    There is no blood test or brain scan that diagnoses PTSD. Diagnosis is clinical, meaning it's based on a structured conversation about your experiences, symptoms, and how long they've been occurring.

    What the Diagnostic Process Typically Involves

    • A comprehensive clinical interview reviewing your symptom history
    • Standardized screening tools such as the PCL-5 (PTSD Checklist for DSM-5) or the CAPS-5 (Clinician-Administered PTSD Scale)
    • Ruling out other conditions with similar presentations, such as generalized anxiety disorder, depression, or traumatic brain injury
    • Assessment of how symptoms impact your daily functioning

    You don't need to wait until your symptoms are debilitating to seek help. If you've experienced trauma and have been struggling for more than a few weeks, reaching out to a professional is always the right move. Early diagnosis is associated with better treatment outcomes.

    Treatment Options for PTSD

    The good news — and it's genuinely encouraging — is that PTSD responds very well to evidence-based treatment. Most people who receive appropriate care see significant improvement. This is a condition you don't have to manage alone, and it's one where help genuinely works.

    First-Line Psychotherapy Approaches

    The American Psychological Association, the VA, and the Department of Defense all strongly recommend trauma-focused therapy as the first-line treatment for PTSD.

    • Cognitive Processing Therapy (CPT): Helps you identify and challenge unhelpful beliefs that developed as a result of trauma — such as "It was my fault" or "The world is completely dangerous." Typically delivered over 12 sessions.
    • Prolonged Exposure (PE): Gradually and safely helps you confront trauma-related memories and situations you've been avoiding. Research shows it reduces PTSD symptoms in 60-90% of patients who complete the full course.
    • EMDR (Eye Movement Desensitization and Reprocessing): Uses guided eye movements while a therapist leads you through traumatic memories to reduce their emotional intensity. Supported by multiple meta-analyses as highly effective.
    • Trauma-Focused CBT (TF-CBT): Particularly recommended for children and adolescents, but also used with adults.

    If you're considering therapy through a remote platform, you may want to review resources on online therapy for trauma and PTSD, which explores how virtual care options compare to in-person treatment.

    Medication Options

    The FDA has approved two medications specifically for PTSD: sertraline (Zoloft) and paroxetine (Paxil) — both selective serotonin reuptake inhibitors (SSRIs). Clinical evidence indicates these medications can significantly reduce PTSD symptoms, particularly re-experiencing and hyperarousal.

    Other medications, including SNRIs, prazosin (for nightmares), and in some cases mood stabilizers, may be prescribed off-label depending on your specific symptom profile. Always discuss medication options with your prescribing physician — dosage and regimen are highly individualized.

    Lifestyle Modifications That Support Recovery

    While not a substitute for professional treatment, the following evidence-supported strategies can meaningfully complement your care plan:

    • Regular physical exercise: Studies published by the NIH show that aerobic exercise at least 3-5 times per week can reduce PTSD symptom severity, likely by lowering cortisol and increasing endorphins.
    • Mindfulness and meditation: Mindfulness-based stress reduction (MBSR) has shown moderate effectiveness in reducing hyperarousal and emotional reactivity in PTSD patients.
    • Sleep hygiene: Since sleep disruption is one of the most debilitating symptoms of PTSD, prioritizing consistent sleep schedules, limiting caffeine, and creating a calming bedtime routine can support overall recovery.
    • Reducing alcohol and substance use: Many people with PTSD use substances to self-medicate. This worsens symptoms over time and significantly undermines treatment effectiveness.

    Living With PTSD: Day-to-Day Management and Prevention

    Living with PTSD is challenging, but with the right support structure, most people build meaningful, fulfilling lives. Recovery is rarely linear — good days and hard days are both part of the process.

    Practical Strategies for Daily Life

    • Build a support network: Share your diagnosis with trusted family or friends. Isolation worsens PTSD. You don't have to tell everyone — just a few safe people who can check in.
    • Identify and communicate triggers: Work with your therapist to identify specific triggers and develop a response plan so you're not caught off guard.
    • Create predictability in your routine: PTSD thrives on unpredictability. A consistent daily routine — wake time, meals, activity — can reduce baseline anxiety.
    • Use grounding techniques: When triggered, techniques like the "5-4-3-2-1" method (naming 5 things you can see, 4 you can hear, etc.) can interrupt a flashback or panic response.
    • Engage in creative or somatic outlets: Art therapy, yoga, and journaling have growing research support as adjunct tools for PTSD recovery.

    Can PTSD Be Prevented?

    Prevention isn't always possible, but early intervention after trauma can significantly reduce the risk of developing full PTSD. Research suggests that structured psychological first aid, early access to trauma-informed counseling, and strong social support in the immediate aftermath of a traumatic event can lower long-term risk.

    For individuals in high-risk professions — first responders, military personnel, healthcare workers — proactive mental health check-ins and resilience-building programs have shown promise in reducing PTSD incidence, according to research from the National Institute of Mental Health (NIMH).

    When to Call Your Doctor — Emergency Signs

    Some PTSD symptoms require immediate professional attention. Do not wait for a scheduled appointment if you or someone you know is experiencing:

    • Thoughts of suicide or self-harm — Call 988 (Suicide and Crisis Lifeline) immediately or go to the nearest emergency room
    • Feeling completely disconnected from reality (dissociation that doesn't resolve)
    • Engaging in dangerous or reckless behavior that puts you or others at risk
    • Severe rage episodes or violent behavior
    • Inability to care for yourself (not eating, not leaving bed for days)
    • Escalating substance use combined with emotional breakdown

    At your next routine appointment, consider bringing up:

    • Any new or worsening symptoms since your last visit
    • Whether your current treatment plan feels effective
    • Any side effects from medications you've been prescribed
    • Questions about adding therapy or changing your current therapeutic approach

    You might also find it helpful to understand your mental health coverage before your appointment. Our guide on health insurance for mental health care can help you understand what PTSD treatment your plan may cover.

    Frequently Asked Questions

    Is PTSD a lifelong condition?

    Not necessarily. With appropriate treatment, many people experience significant reduction in symptoms — and some achieve full remission. This varies from person to person based on trauma severity, access to treatment, support systems, and individual resilience. Some people manage occasional flare-ups long-term, while others recover fully.

    Can PTSD develop years after a traumatic event?

    Yes. Delayed-onset PTSD — where symptoms don't appear until 6 months or more after the trauma — is well-documented in clinical literature. It can be triggered by a new stressor, a life transition, or simply the passage of time altering how the brain processes stored trauma.

    Is PTSD only caused by war or combat?

    Absolutely not. While PTSD is commonly associated with veterans — and combat is indeed a significant cause — the condition affects survivors of sexual assault, accidents, abuse, medical crises, natural disasters, and many other traumatic experiences. According to the National Center for PTSD, sexual assault is actually one of the most common causes of PTSD in women.

    How is PTSD different from grief or normal stress?

    Normal grief and stress typically diminish over time as the person processes what happened. PTSD is distinguished by the persistence and severity of symptoms — especially flashbacks, avoidance behaviors, and hyperarousal lasting more than one month — and by significant interference with daily functioning. If you're unsure, a clinical evaluation can clarify what you're experiencing.

    Can children develop PTSD?

    Yes, and it often looks different than adult PTSD. Children may re-enact trauma through play, have frequent nightmares, show regressive behaviors (like bedwetting), or become withdrawn. Trauma-focused CBT is the most well-supported treatment for children and adolescents with PTSD.

    Conclusion

    PTSD is a serious, real, and diagnosable medical condition — but it is also one of the most treatable mental health disorders we know. Whether your trauma happened last year or two decades ago, whether it was a single event or years of ongoing adversity, there are evidence-based paths toward healing.

    You don't have to keep white-knuckling through flashbacks, sleepless nights, or emotional withdrawal. Reaching out to a healthcare provider is an act of courage and self-respect — not weakness. The sooner PTSD is identified and treated, the better the outcomes tend to be.

    Talk to your doctor, find a trauma-informed therapist, and remember: recovery is not only possible — for most people, it is the most likely outcome with the right care.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Health Insurance for Preventive Care: What’s Covered

    Health Insurance for Preventive Care: What’s Covered

    Most Americans are leaving free preventive care on the table — and it could be costing them their health.

    James, 54, hadn’t seen a doctor in six years. He assumed his annual checkups weren’t covered and that he’d face a hefty bill. When he finally scheduled a visit after a friend’s heart attack scare, he discovered something surprising: his insurer had covered preventive screenings all along — including a colonoscopy and cholesterol panel — completely free. He had no idea.

    He’s far from alone. According to the Centers for Disease Control and Prevention (CDC), nearly 1 in 3 American adults skips recommended preventive screenings each year, often because of cost concerns or confusion about health insurance coverage. Yet under current federal law, most health plans are required to cover a comprehensive list of preventive services at no out-of-pocket cost to you.

    This guide breaks down exactly what your health insurance plan must cover under federal guidelines, which screenings apply to your age group, and how to make sure you’re actually using the preventive benefits you’re already paying for. Understanding your health insurance for preventive care coverage could be one of the most important steps you take for your long-term health.

    What Is Preventive Care Coverage — and Why Does It Matter?

    Preventive care refers to health services designed to detect, prevent, or reduce the risk of disease before symptoms appear. This includes routine checkups, vaccinations, laboratory screenings, and counseling sessions aimed at catching health problems early — when they’re far easier and less expensive to treat.

    Under the Affordable Care Act (ACA), most health insurance plans sold in the United States are required to cover a defined set of preventive services without charging a copayment, coinsurance, or deductible — as long as you see an in-network provider. This is a critical distinction: the "free" part only applies when you follow your plan’s network rules.

    The NIH estimates that preventive services — if fully utilized by the U.S. population — could prevent more than 100,000 deaths annually. Yet utilization rates remain stubbornly low, largely driven by confusion about what’s covered and fear of surprise bills.

    It’s worth noting: not all plans fall under ACA rules. Grandfathered plans (those that existed before March 23, 2010 and haven’t made significant changes since) may not be required to cover preventive care without cost-sharing. If you’re unsure, call the member services number on your insurance card.

    What Preventive Services Are Covered at No Cost?

    The federal government relies on three independent bodies to determine which preventive services must be covered. These organizations evaluate clinical evidence and issue recommendations that insurers are then legally required to follow for ACA-compliant plans.

    The three governing bodies are:

    • U.S. Preventive Services Task Force (USPSTF) — focuses on screenings and counseling for adults and children
    • Advisory Committee on Immunization Practices (ACIP) — determines which vaccines must be covered
    • Health Resources and Services Administration (HRSA) — sets standards for women’s preventive health and pediatric care

    Clinical evidence strongly supports this model. A landmark study published through the NIH found that every dollar invested in preventive care returns an average of $5.60 in reduced downstream medical costs — particularly for chronic disease prevention and early cancer detection.

    Here’s a breakdown of what most ACA-compliant plans must cover for adults aged 30–70:

    Cardiovascular Health

    • Blood pressure screening (all adults)
    • Cholesterol screening (adults at increased risk or age 35 and older)
    • Aspirin counseling for cardiovascular prevention (specific age and risk criteria apply)
    • Tobacco use screening and cessation counseling
    • Healthy diet and physical activity counseling for adults with cardiovascular risk factors

    Cancer Screenings

    • Colorectal cancer screening starting at age 45 (colonoscopy, stool-based tests, or CT colonography)
    • Lung cancer screening with low-dose CT scan (adults aged 50–80 with a significant smoking history)
    • Cervical cancer screening (Pap smear and/or HPV testing for women up to age 65)
    • Breast cancer mammography screening (women 40 and older, per updated 2024 USPSTF guidance)
    • Skin cancer counseling for adults at increased risk

    Metabolic and Chronic Disease

    • Diabetes (Type 2) screening for adults aged 35–70 who are overweight or obese
    • Prediabetes and obesity counseling, including referral to intensive behavioral programs
    • Depression screening for all adults
    • Alcohol misuse screening and brief counseling

    Immunizations

    • Annual influenza vaccine
    • Shingles (Zoster) vaccine (recommended at age 50)
    • Pneumococcal vaccine (age 65 and older)
    • Tdap booster (tetanus, diphtheria, pertussis)
    • COVID-19 vaccine (per ACIP schedule)
    • RSV vaccine for adults 60 and older

    This list is not exhaustive. Additional services may apply based on your sex, age, pregnancy status, and individual risk profile. Your insurer’s summary of benefits document — or a call to member services — can clarify your specific entitlements.

    Causes of Coverage Gaps: Why People Miss Out

    If preventive care is legally required to be free, why do so many people skip it? Research suggests several overlapping reasons.

    First, confusion about coverage is rampant. A 2023 survey from the Kaiser Family Foundation found that fewer than 40% of insured adults could correctly identify which preventive services their plan covered without cost-sharing. Many assumed that any doctor visit would trigger a bill.

    Second, the "preventive vs. diagnostic" distinction trips up millions of patients each year. This is a critical point: if you go in for a "routine" colonoscopy but your doctor finds and removes a polyp during the same visit, the procedure may be reclassified as diagnostic — and cost-sharing may apply. This varies significantly by state and insurer. Some states have enacted laws to protect consumers from this reclassification, but federal protections remain limited.

    Third, network confusion plays a major role. Seeing an out-of-network provider for a covered preventive service can result in full cost-sharing, even if the service itself is on the covered list. Always confirm that your provider is in-network before scheduling.

    Fourth, racial and socioeconomic disparities in preventive care utilization are well-documented. The CDC reports that Black and Hispanic adults are significantly less likely to receive recommended cancer screenings compared to white adults — a gap driven by systemic barriers including insurance coverage, transportation, and provider availability.

    How to Use Your Preventive Care Benefits Effectively

    Understanding your coverage is the first step. Using it consistently is what protects your health long-term. Here’s how to make the most of your benefits:

    Schedule your annual wellness visit. This is distinct from a sick visit. An annual wellness exam — sometimes called a "well visit" or "preventive visit" — is covered at no cost for most insured adults. Use this appointment to discuss which screenings are due based on your age, sex, and risk factors. If you also bring up a new symptom or request treatment for a condition at the same appointment, that portion may be billed separately as a sick visit. Be clear with your doctor about the purpose of your visit upfront.

    Know your age-based screening schedule. The USPSTF publishes clear, evidence-based recommendations for each age group. For example, if you’re 45 or older and have never had a colorectal cancer screening, that should be a top priority — colorectal cancer is the second leading cause of cancer-related death in the U.S., according to the American Cancer Society, and is highly treatable when caught early.

    Verify before you go. Call your insurer before any preventive appointment. Confirm that the specific service (use the exact CPT billing code if possible), the provider, and the facility are all covered under your plan’s preventive care benefit. This one step can prevent surprise bills.

    Take advantage of counseling benefits. Many plans now cover brief behavioral counseling sessions for tobacco cessation, alcohol misuse, obesity, and depression — at no cost. These aren’t just "nice to haves": clinical evidence from the NIH shows that structured counseling significantly improves outcomes in each of these areas.

    For those managing ongoing conditions like diabetes, it’s also worth reading how health insurance for chronic conditions works alongside preventive benefits — the two often overlap in important ways.

    Medicare and Preventive Care: Special Considerations for Adults 65+

    If you’re on Medicare, your preventive care benefits work differently than commercial insurance — and it’s essential to understand the distinctions to avoid unexpected costs.

    Medicare Part B covers a "Welcome to Medicare" visit within the first 12 months of enrollment, as well as an annual "Wellness Visit" each year thereafter. Both are free if you see a participating provider. Medicare also covers a robust list of screenings including mammograms, colonoscopies, bone density scans, cardiovascular disease screenings, diabetes screenings, and lung cancer CT scans for eligible beneficiaries.

    However, the diagnostic reclassification issue is particularly significant for Medicare patients. Until recently, a colonoscopy that found a polyp could be reclassified as a diagnostic procedure — meaning you’d owe 20% of the Medicare-approved cost. Legislation passed in recent years has been phasing in stronger protections, but the rules remain in transition. Confirm the current policy with your Medicare plan before scheduling.

    Medicare Advantage (Part C) plans are required to cover all the same preventive services as Original Medicare — and many plans offer additional preventive benefits such as dental, vision, and hearing coverage. Compare plans carefully during the annual open enrollment period (October 15 – December 7) to ensure your preventive care needs are fully met.

    When to Call Your Doctor — or Your Insurer

    Preventive care is by definition proactive, but there are moments when you need to act quickly rather than wait for your next scheduled visit:

    • Emergency warning signs — chest pain, sudden shortness of breath, stroke symptoms (face drooping, arm weakness, speech difficulty), or signs of severe allergic reaction following a vaccine should all prompt a call to 911 immediately.
    • New or worsening symptoms — if you develop symptoms between preventive visits, don’t wait. These should be evaluated as a clinical concern, not deferred to a wellness visit.
    • Coverage disputes — if you receive an unexpected bill for a service you believe should be covered at no cost, contact your insurer’s member services department and request a formal review. You have the right to appeal denials of coverage for preventive services under federal law.
    • Screening overdue by more than one year — if you’ve missed a recommended screening (colonoscopy, mammogram, etc.), bring it up at your next physician visit and request a referral. Early detection remains the most powerful tool in chronic disease and cancer management.

    If mental health screenings or counseling are part of your preventive care needs, you may also want to review what your plan covers in that area — our guide on health insurance for mental health care walks through the coverage rules in detail.

    Frequently Asked Questions

    Does my deductible apply to preventive care services?
    For ACA-compliant plans, no. Covered preventive services must be provided without cost-sharing — meaning your deductible, copay, and coinsurance do not apply, as long as you receive the service from an in-network provider and the visit is billed as preventive. If additional services are rendered during the same visit (such as lab work for a symptom you mention), those may be billed separately and subject to your deductible.

    What’s the difference between a preventive visit and a sick visit?
    A preventive visit is a scheduled wellness exam where no new symptoms or conditions are addressed. A sick visit occurs when you seek care for a specific complaint or symptom. If both occur in the same appointment, your provider may split the billing into a preventive component (covered) and a medical component (subject to cost-sharing). Ask your doctor’s office how they bill combined visits.

    Are preventive lab tests always free?
    Only if they are ordered as part of a covered preventive service by an in-network provider. For example, a lipid panel (cholesterol test) ordered as a routine preventive screening is typically covered at no cost. The same test ordered to monitor a known condition like high cholesterol may be billed as a diagnostic service. This variation from person to person is one of the most common sources of billing confusion.

    Does health insurance cover vaccines for adults?
    Yes. Under the ACA, all ACIP-recommended vaccines must be covered at no cost for adults on ACA-compliant plans. This includes flu shots, shingles vaccines, COVID-19 vaccines, and more. On Medicare, Part B covers most vaccines related to disease prevention, while Part D covers others (including the shingles vaccine). Check your specific plan for the complete vaccine schedule.

    What if I don’t have insurance — can I still get preventive care?
    Yes, though at reduced access. Federally Qualified Health Centers (FQHCs) offer sliding-scale fee services based on income and are available in most communities across the U.S. The CDC’s National Breast and Cervical Cancer Early Detection Program also provides free or low-cost screenings for qualifying individuals. Visit the Health Resources and Services Administration (HRSA) website to find a low-cost clinic near you.

    Conclusion

    Preventive care is one of the most powerful tools you have for protecting your long-term health — and under current federal law, most of it is already paid for through your health insurance plan. The challenge isn’t access for most insured Americans; it’s awareness.

    Understanding what your plan covers, confirming network status before appointments, and staying current with age-appropriate screenings are practical steps anyone can take starting today. Whether you’re 35 and due for a blood pressure check or 60 and overdue for a colonoscopy, the evidence is clear: early detection saves lives.

    Talk to your primary care physician at your next visit about which preventive services are right for your age, sex, and health history. Don’t leave these benefits unused — they exist specifically to keep you healthier for longer.


    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.