Blog

  • Insulin Resistance: Signs, Causes & How to Reverse It

    Insulin Resistance: Signs, Causes & How to Reverse It

    Understanding insulin resistance is one of the most important steps you can take to protect your long-term metabolic health — and millions of Americans have it without knowing.

    Marcus, 47, had been feeling exhausted after every meal for years. His doctor told him his blood sugar was "borderline" and that he should "watch what he eats." But nobody explained why his body was struggling — or that he was already in the early stages of a process that affects an estimated 88 million American adults, according to the CDC.

    That process is called insulin resistance, and it sits at the very heart of type 2 diabetes management. If you have been told your blood sugar is slightly elevated, or that you have prediabetes, or if you are simply trying to understand how your body handles glucose, this guide is written for you.

    You will learn exactly what insulin resistance is, how to recognize its warning signs, what drives it, how physicians diagnose and treat it, and — most importantly — what concrete, evidence-based steps you can take starting today to support your metabolic health and reduce your risk of progressing to type 2 diabetes.

    What Is Insulin Resistance?

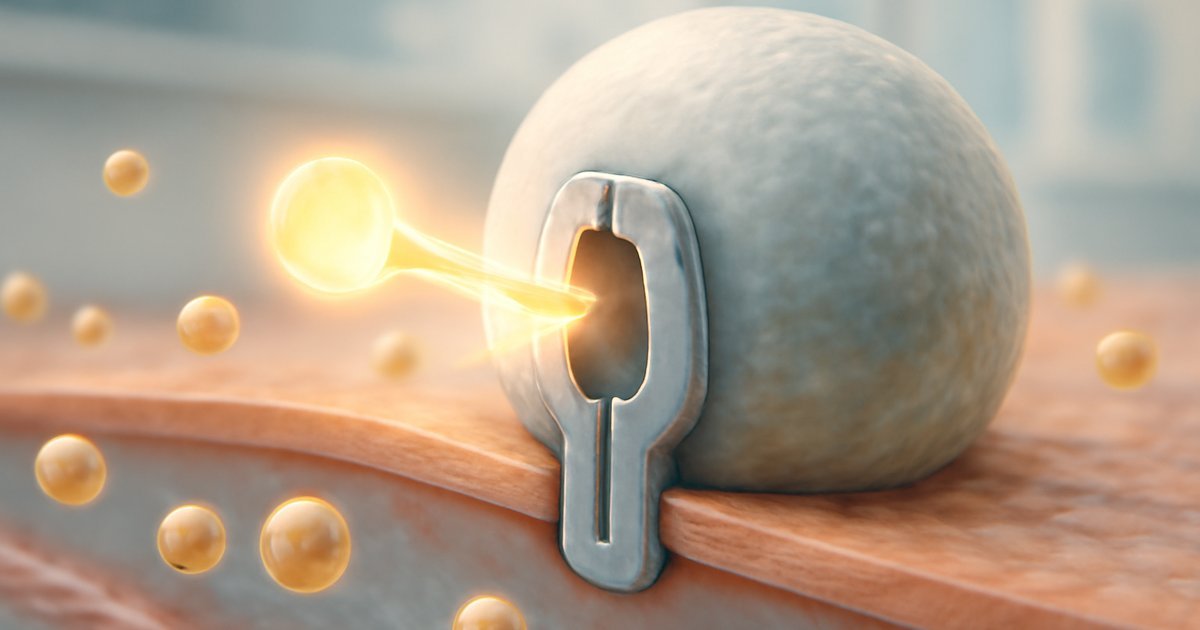
    Insulin is a hormone produced by the pancreas. Its primary job is to act like a key — unlocking your muscle, liver, and fat cells so that glucose (sugar from food) can enter and be used for energy.

    When you develop insulin resistance, those cellular "locks" stop responding normally to the insulin key. Your cells essentially ignore the signal. In response, your pancreas works harder and pumps out more insulin to compensate. For a while, this keeps your blood sugar relatively normal — but it puts enormous strain on your pancreas.

    Over time, the pancreas can no longer keep up with the demand. Blood sugar begins to rise. First you develop prediabetes. Then, if left unaddressed, type 2 diabetes.

    According to the NIH, approximately 1 in 3 American adults has prediabetes — the direct result of insulin resistance — and more than 80% of them are unaware of it. This makes insulin resistance one of the most underdiagnosed metabolic conditions in the United States.

    Signs and Symptoms of Insulin Resistance

    One of the challenges with insulin resistance is that it often develops silently. Many people feel "fine" for years while the condition progresses. However, there are early warning signs worth knowing.

    Early and common signs include:

    • Persistent fatigue, especially after carbohydrate-rich meals
    • Difficulty losing weight, particularly around the abdomen
    • Intense sugar or carbohydrate cravings
    • Increased hunger shortly after eating
    • Brain fog or difficulty concentrating
    • Elevated blood pressure or borderline-high triglycerides
    • Skin changes: dark, velvety patches in skin folds (a condition called acanthosis nigricans), commonly found on the neck, armpits, or groin

    Signs that may indicate progression toward prediabetes or type 2 diabetes:

    • Frequent urination, especially at night
    • Increased thirst
    • Slow-healing cuts or bruises
    • Tingling or numbness in hands or feet
    • Blurry vision
    • Recurring infections (urinary tract, skin, or yeast infections)

    A landmark study published in the journal Diabetes Care found that people with insulin resistance often show abnormal lipid panels — specifically high triglycerides and low HDL (good) cholesterol — years before blood sugar levels become clinically elevated. This is why your doctor may flag a routine cholesterol panel as an early metabolic warning sign.

    Causes and Risk Factors

    Insulin resistance does not have a single cause. Research suggests it develops from a combination of genetic, lifestyle, and environmental factors working together over time.

    Genetic and biological factors:

    • Family history of type 2 diabetes
    • Ethnicity: Black, Hispanic, Native American, and Asian American adults face disproportionately higher risk, according to the CDC
    • Polycystic ovary syndrome (PCOS), which is strongly linked to insulin resistance in women
    • History of gestational diabetes
    • Age: risk increases significantly after 45

    Lifestyle and environmental factors:

    • Physical inactivity — muscle cells that are regularly exercised are significantly more insulin-sensitive
    • Excess body fat, particularly visceral fat (fat stored deep around internal organs in the abdomen)
    • Diets high in ultra-processed foods, refined carbohydrates, and added sugars
    • Chronic sleep deprivation — research from the University of Chicago found that just four nights of poor sleep can reduce insulin sensitivity by as much as 25%
    • Chronic stress and elevated cortisol levels
    • Smoking

    It is worth emphasizing: having risk factors does not mean you are destined to develop diabetes. This condition is highly modifiable, and early action makes a measurable difference. For more on how physical activity directly lowers blood sugar, see our guide on Exercise and Diabetes: How Physical Activity Controls Blood Sugar.

    Diagnosis: What to Expect

    Insulin resistance itself is not directly tested with a single definitive lab value in standard clinical practice. Instead, physicians typically identify it through a combination of measurements and screening tests.

    Key diagnostic tools include:

    • Fasting Blood Glucose: A blood sample taken after at least 8 hours without food. A result of 100–125 mg/dL indicates prediabetes; 126 mg/dL or higher on two occasions indicates type 2 diabetes.
    • Hemoglobin A1C (HbA1c): Reflects your average blood sugar over the past 2–3 months. A result of 5.7–6.4% indicates prediabetes; 6.5% or higher indicates diabetes.
    • Fasting Insulin Level: Some physicians order this alongside glucose to calculate a measure of insulin resistance called HOMA-IR (Homeostatic Model Assessment of Insulin Resistance). This is not universally standardized but can be clinically informative.
    • Lipid Panel: High triglycerides (above 150 mg/dL) and low HDL are common metabolic markers associated with insulin resistance.
    • Blood Pressure Measurement: Hypertension frequently co-occurs with insulin resistance as part of metabolic syndrome.
    • Waist Circumference: The American Heart Association considers a waist of more than 40 inches in men or 35 inches in women a significant clinical risk marker.

    The American Diabetes Association recommends that adults aged 35 to 70 who are overweight or have additional risk factors get screened for prediabetes and diabetes during routine care. If your results are borderline or if you have symptoms, do not wait — advocate for screening at your next appointment.

    Treatment Options for Insulin Resistance

    The good news is that insulin resistance is one of the most treatable metabolic conditions, particularly when caught early. Clinical evidence strongly supports both lifestyle-based approaches and, when appropriate, pharmacological intervention.

    Conventional Medical Treatments:

    Metformin is the most widely studied medication for insulin resistance and prediabetes. The landmark NIH-funded Diabetes Prevention Program (DPP) trial demonstrated that metformin reduced the risk of progressing from prediabetes to type 2 diabetes by 31% over three years. Your physician will determine whether medication is appropriate for your individual situation.

    For people who have already developed type 2 diabetes alongside insulin resistance, a growing class of medications — including GLP-1 receptor agonists and SGLT2 inhibitors — have shown significant benefits not only for blood sugar control but also for cardiovascular and kidney protection, according to the American Diabetes Association’s 2025–2026 Standards of Care.

    Lifestyle Modifications (First-Line Approach):

    The same Diabetes Prevention Program trial found that structured lifestyle change — specifically, 150 minutes per week of moderate exercise and a 5–7% reduction in body weight — reduced the risk of progressing to type 2 diabetes by an impressive 58%. That outperformed metformin alone.

    • Dietary changes: Clinical evidence indicates that reducing refined carbohydrates and added sugars, increasing dietary fiber, and prioritizing lean proteins and healthy fats meaningfully improves insulin sensitivity. The Mediterranean diet and low-glycemic-index approaches have both shown strong results in clinical trials.
    • Physical activity: Both aerobic exercise (brisk walking, cycling, swimming) and resistance training independently improve insulin sensitivity. Research suggests that even a 10-minute walk after meals can reduce post-meal blood sugar spikes.
    • Weight management: Losing even 5–10% of body weight can produce clinically significant improvements in insulin sensitivity, according to the CDC’s National Diabetes Prevention Program.
    • Sleep optimization: Prioritizing 7–9 hours of quality sleep per night is an underappreciated metabolic intervention. Poor sleep is consistently linked to worsened insulin resistance. Our article on Weight Loss and Sleep: Why Rest Is Key to Losing Fat offers helpful practical strategies.
    • Stress management: Chronic stress elevates cortisol, which directly counteracts insulin signaling. Practices such as mindfulness, structured breathing, and regular physical activity all help moderate cortisol levels.

    Living With Insulin Resistance: Day-to-Day Management

    Managing insulin resistance is a long-term commitment — but it does not have to feel overwhelming. Small, consistent habits compound into significant metabolic change over months and years.

    Practical daily strategies:

    • Eat meals at consistent times to support stable blood sugar rhythms
    • Pair carbohydrates with protein, fiber, or healthy fat at every meal to blunt glucose spikes
    • Aim for at least 30 minutes of moderate movement most days — even breaking it into three 10-minute walks counts
    • Limit alcohol, which can interfere with glucose regulation and insulin signaling
    • Monitor your progress: ask your doctor to recheck your A1C or fasting glucose every 3–6 months if you are managing prediabetes
    • Keep a simple food and activity log — research suggests that self-monitoring improves outcomes

    If you are managing additional weight-related challenges alongside insulin resistance, our article on Weight Loss After 40: Why It’s Harder and What Works addresses the unique metabolic factors that come into play as you age.

    Remember: this varies from person to person. What works well for one individual may need to be adjusted for another based on medications, other health conditions, preferences, and genetics. Your care team is your most important partner in this process.

    When to Call Your Doctor — Emergency Signs

    Most of the time, insulin resistance and prediabetes are managed through scheduled appointments. However, certain symptoms require urgent or emergency attention.

    Call your doctor promptly if you notice:

    • Blood sugar readings consistently above 200 mg/dL (if you are monitoring at home)
    • Unexplained weight loss
    • Progressive numbness, tingling, or pain in feet or hands
    • Worsening blurry vision
    • Recurring infections that are difficult to resolve

    Seek emergency care immediately if you experience:

    • Extreme thirst combined with confusion or disorientation
    • Fruity-smelling breath and nausea or vomiting (possible signs of diabetic ketoacidosis)
    • Rapid breathing, severe abdominal pain
    • Loss of consciousness or inability to be awakened
    • Blood sugar above 300 mg/dL with symptoms

    These symptoms may indicate a serious complication requiring immediate medical intervention. Do not wait to see if they resolve on their own.

    Frequently Asked Questions About Insulin Resistance

    Can insulin resistance be reversed?
    Research suggests that insulin resistance can be significantly improved — and in many cases brought back to normal ranges — through sustained lifestyle changes, particularly weight loss, regular exercise, and dietary modification. The word "reversed" should be understood carefully: in most cases it means achieving and maintaining normal blood sugar levels, not that your underlying genetic susceptibility disappears. Consistency over time is what drives lasting results.

    Is insulin resistance the same as type 2 diabetes?
    No — but insulin resistance is typically the underlying mechanism that leads to type 2 diabetes when left unmanaged. You can have insulin resistance and prediabetes without having type 2 diabetes. Early identification and intervention at the prediabetes stage can prevent or significantly delay the development of diabetes.

    What foods are worst for insulin resistance?
    Clinical evidence indicates that refined carbohydrates (white bread, white rice, sugary cereals), sugar-sweetened beverages, and ultra-processed snack foods cause the largest and fastest blood sugar spikes, worsening insulin resistance over time. Most physicians and registered dietitians recommend prioritizing whole grains, vegetables, legumes, lean proteins, and healthy fats.

    Can thin or normal-weight people have insulin resistance?
    Yes. While excess body fat — particularly visceral fat — is a major driver, insulin resistance can occur in individuals with a normal BMI, particularly those who are sedentary, have a family history of diabetes, or carry metabolic risk factors. This is sometimes called "metabolically unhealthy normal weight." Lab testing is the only reliable way to identify it.

    How long does it take to improve insulin sensitivity?
    This varies from person to person, but clinical evidence indicates that meaningful improvements in insulin sensitivity can occur within 2–4 weeks of consistent aerobic exercise and dietary changes. More significant improvements in A1C or fasting glucose are typically measurable within 3–6 months of sustained lifestyle change.

    Taking Control of Your Metabolic Health

    Insulin resistance is not a life sentence — it is a signal. Your body is telling you that something needs to change, and the evidence is clear that change is possible at almost any stage of the process.

    Whether you are managing prediabetes, recently diagnosed with type 2 diabetes, or simply trying to understand a borderline lab result, knowledge is your most powerful tool. Work with your physician to get the right tests, understand your numbers, and build a plan that fits your real life.

    Small daily choices — a walk after dinner, choosing whole grains over refined ones, getting to bed an hour earlier — add up to measurable metabolic improvements over time. You do not have to do everything perfectly. You just have to keep moving in the right direction, consistently, with qualified medical support by your side.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.


  • Weight Loss and Sleep: Why Rest Is Key to Losing Fat

    Weight Loss and Sleep: Why Rest Is Key to Losing Fat

    The link between sleep and weight loss is backed by decades of clinical research — and it may be the missing piece in your health strategy.

    Mark, 47, had been eating well and exercising four times a week for two months. The scale barely moved. His doctor asked a simple question: “How much sleep are you getting?” Mark admitted he averaged about five hours a night. That conversation changed everything. Within weeks of improving his sleep, his weight loss stalled no more.

    If you have been doing everything “right” and still struggling to lose weight, your sleep habits may be quietly working against you. According to the CDC, more than one-third of American adults regularly get less than the recommended seven hours of sleep per night. Research increasingly shows that poor sleep is not just an energy problem — it is a metabolic problem that directly impacts your ability to lose fat and maintain a healthy weight.

    In this article, you will learn exactly how sleep affects weight loss, what happens inside your body when you are sleep-deprived, and what practical steps you can take to make rest a genuine part of your weight management plan.

    What Is the Sleep-Weight Connection?

    The relationship between sleep and weight is bidirectional and deeply physiological. Poor sleep does not just make you tired — it disrupts hormones, alters metabolism, increases appetite, and reduces your capacity to make healthy decisions.

    Sleep is divided into several stages, including light sleep, deep sleep (slow-wave sleep), and REM (rapid eye movement) sleep. Each stage plays a specific role in recovery, hormone regulation, and cognitive function. When you consistently cut sleep short, you lose critical time in these restorative phases.

    According to the National Institutes of Health (NIH), adults need between seven and nine hours of sleep per night for optimal health. Yet the American Sleep Association reports that 50 to 70 million US adults have a sleep disorder, with chronic sleep deprivation being one of the most widespread public health issues in the country.

    The connection to weight is clear: a 2022 meta-analysis published in the journal Obesity Reviews found that short sleep duration was significantly associated with a higher risk of obesity in both adults and children, independent of other lifestyle factors.

    How Sleep Affects Your Hunger Hormones

    Two hormones play a central role in appetite regulation: ghrelin and leptin. Sleep deprivation throws both of these off balance in ways that make weight loss much harder.

    • Ghrelin is often called the “hunger hormone.” It signals your brain that it is time to eat. When you are sleep-deprived, ghrelin levels rise — meaning you feel hungrier than usual, often craving calorie-dense foods.
    • Leptin is the “satiety hormone” that tells your brain you are full and have enough energy stored. Sleep deprivation lowers leptin levels, so your body does not receive the signal to stop eating.

    Clinical evidence from a landmark study at the University of Chicago found that participants who slept only 5.5 hours per night had 14.9% higher ghrelin levels and 15.5% lower leptin levels compared to those who slept 8.5 hours. The result? They consumed significantly more calories without realizing it.

    Beyond ghrelin and leptin, poor sleep also elevates cortisol — the primary stress hormone. Elevated cortisol promotes fat storage, particularly around the abdominal area. If you have also been under psychological pressure, you may want to explore how metabolism and hormonal signals interact with weight management for a fuller picture.

    Sleep Deprivation and Caloric Intake: What the Research Shows

    It is not just about feeling hungrier. Research suggests that sleep-deprived individuals are drawn specifically to high-fat, high-sugar foods, and they tend to eat more of them — particularly at night.

    A study from the American Journal of Clinical Nutrition found that sleep-restricted adults consumed an average of 385 extra calories per day compared to well-rested counterparts. Over a week, that adds up to more than 2,600 additional calories — nearly enough to gain a pound of body fat.

    The brain’s reward centers are also affected. MRI studies have shown that sleep deprivation increases activity in the brain regions associated with pleasure and reward when viewing high-calorie food images. Essentially, your sleep-deprived brain assigns greater emotional value to junk food, making it harder to resist.

    This is compounded by impaired prefrontal cortex function when you are under-slept — the part of the brain responsible for impulse control and decision-making. Clinical evidence indicates that even one night of poor sleep can measurably reduce your ability to make sound dietary choices the following day.

    The Impact on Physical Activity and Fat Burning

    Weight loss is not only about what you eat — it is about how efficiently your body uses energy. Sleep plays a direct role in physical performance and body composition.

    When you are sleep-deprived:

    • Your perceived exertion during exercise increases, meaning workouts feel harder and you are more likely to quit early or skip them altogether.
    • Muscle recovery slows significantly. Growth hormone, which is primarily released during deep sleep, is critical for muscle repair and fat metabolism. Less deep sleep means less growth hormone and slower progress.
    • Your body preferentially burns muscle over fat for energy when it is sleep-stressed. A study from the Annals of Internal Medicine found that sleep-deprived dieters lost 55% less fat and 60% more muscle mass compared to well-rested dieters on the same caloric deficit.

    This finding is particularly relevant if strength training is part of your routine. You may find it useful to read about how weight loss and body composition shift with age, since the interplay between sleep, muscle mass, and metabolism becomes even more pronounced after 40.

    Sleep Quality vs. Sleep Quantity: Both Matter

    It is not just about how many hours you sleep — the quality of those hours matters equally. Fragmented sleep, frequent awakenings, or untreated sleep disorders like obstructive sleep apnea can prevent you from reaching the deep and REM stages your body needs.

    Obstructive sleep apnea (OSA) is a condition in which the airway partially or fully collapses during sleep, causing repeated interruptions in breathing. The American Academy of Sleep Medicine estimates that OSA affects approximately 30 million Americans, and a significant percentage remain undiagnosed.

    OSA is strongly associated with weight gain, insulin resistance, and metabolic syndrome. Research suggests that treating OSA with CPAP therapy (continuous positive airway pressure) can improve insulin sensitivity and support weight management efforts, though results vary from person to person.

    Other factors that reduce sleep quality include:

    • Alcohol consumption in the evening (disrupts REM sleep)
    • Blue light exposure from screens within one to two hours of bedtime
    • Caffeine consumed after 2 p.m.
    • Irregular sleep and wake schedules
    • Unmanaged stress or anxiety

    Practical Strategies to Improve Sleep for Weight Loss

    The good news is that sleep is one of the most modifiable health behaviors. Consistent, science-backed changes to your sleep habits can meaningfully support your weight loss goals. Here is what clinical evidence supports:

    1. Prioritize a Consistent Sleep Schedule

    Going to bed and waking up at the same time every day — including weekends — helps regulate your circadian rhythm (your internal 24-hour biological clock). Research from the American Academy of Sleep Medicine shows that consistent sleep timing is associated with lower body fat percentage, independent of total sleep duration.

    2. Optimize Your Sleep Environment

    Your bedroom should be cool (between 60–67°F is considered optimal by most sleep researchers), dark, and quiet. The Mayo Clinic recommends reserving your bedroom exclusively for sleep and intimacy to strengthen the mental association between your bed and rest.

    3. Limit Evening Eating

    Clinical evidence indicates that late-night eating is associated with poorer sleep quality and greater fat storage. Try to finish your last meal at least two to three hours before bed. This is also consistent with several time-restricted eating protocols that support weight management.

    4. Reduce Stimulants and Screen Time

    The NIH recommends avoiding caffeine after early afternoon and minimizing screen use one to two hours before bedtime. Blue light from phones and tablets suppresses melatonin production, delaying sleep onset and reducing sleep quality.

    5. Manage Stress Actively

    Elevated cortisol from chronic stress directly impairs sleep and promotes abdominal fat storage. Practices such as diaphragmatic breathing, progressive muscle relaxation, or mindfulness meditation have clinical support for improving sleep quality and reducing cortisol levels.

    6. Be Mindful of Alcohol

    Many people use alcohol to unwind and believe it helps them sleep. While it may help you fall asleep faster, clinical evidence consistently shows that alcohol fragments sleep architecture, reducing time in REM sleep and increasing nighttime awakenings.

    When to Call Your Doctor or Seek Evaluation

    Some sleep issues go beyond lifestyle adjustments and require medical evaluation. You should contact your doctor if you experience:

    • Loud, chronic snoring — this may indicate obstructive sleep apnea
    • Gasping or choking during sleep reported by a partner
    • Excessive daytime sleepiness that interferes with daily function
    • Inability to fall or stay asleep most nights for more than three weeks (consistent with clinical criteria for insomnia)
    • Restless leg syndrome — uncomfortable sensations in the legs that worsen at night
    • Persistent weight gain despite adequate diet and exercise, which may warrant a hormonal or metabolic evaluation

    Be sure to tell your doctor about your sleep patterns at your next visit. Bring specific information: what time you go to bed, when you wake up, how often you wake during the night, and how you feel in the morning. This detail helps your provider assess whether a sleep study (polysomnography) may be appropriate.

    Frequently Asked Questions

    Can I lose weight just by sleeping more?

    Sleep alone is not a weight loss intervention, but improving sleep quality and duration removes a major physiological barrier to fat loss. Most physicians recommend addressing sleep as part of a comprehensive approach that includes nutrition and physical activity.

    How much sleep do I need for optimal weight management?

    The CDC and NIH recommend seven to nine hours per night for adults. Research suggests that consistently sleeping fewer than six hours per night is associated with a 30% higher risk of obesity compared to those sleeping seven to nine hours.

    Does napping help if I did not sleep well at night?

    Short naps of 20 to 30 minutes may restore alertness and reduce cortisol, but they do not fully compensate for the hormonal disruptions caused by chronic nighttime sleep loss. Clinical evidence indicates that napping does not restore the restorative effects of full-cycle overnight sleep.

    Can treating sleep apnea help me lose weight?

    Research suggests that CPAP treatment for obstructive sleep apnea can improve insulin sensitivity, reduce fatigue (making exercise more feasible), and support metabolic health. However, weight loss outcomes vary from person to person, and CPAP is not a standalone weight loss treatment.

    Is it normal for my weight loss to plateau when I am sleep-deprived?

    Yes. Clinical evidence strongly indicates that sleep deprivation blunts the body’s ability to burn fat effectively, disrupts hunger hormones, and increases caloric intake. Addressing sleep is often one of the first steps many physicians recommend when a weight loss plateau occurs without an obvious dietary explanation.

    Putting It All Together

    Sleep is not a passive activity — it is an active, biologically essential process that regulates hormones, metabolism, appetite, and cognitive function. If you have been working hard on your nutrition and exercise and still struggling with weight, your sleep habits deserve serious attention.

    The science is clear: sleeping seven to nine hours of quality sleep per night supports healthier hunger hormones, better workout performance, more efficient fat burning, and stronger impulse control around food. This is not a shortcut — it is foundational health.

    Start with one or two changes from the strategies above, discuss any persistent sleep issues with your healthcare provider, and treat rest as the non-negotiable pillar of your weight management plan that it truly is. Progress is possible, and small, consistent improvements in sleep can create a ripple effect across your entire health.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Online Therapy for Anxiety: What Works and What to Expect

    Online Therapy for Anxiety: What Works and What to Expect

    Anxiety affects more Americans than any other mental health condition — and a growing body of evidence shows that effective treatment is now available from your living room.

    Consider Marcus, 44, a project manager in Atlanta who had been waking up at 3 a.m. with a racing heart and a mental checklist he couldn’t turn off. He knew something was wrong, but the idea of sitting in a waiting room, taking time off work, and explaining himself to a stranger felt overwhelming. So he waited. For two years, he waited.

    His story isn’t unusual. According to the National Institute of Mental Health, anxiety disorders affect approximately 40 million adults in the United States every year — making them the most common mental health condition in the country. Yet fewer than 37% of those affected receive treatment.

    Online therapy for anxiety has emerged as one of the most significant shifts in mental health care in recent decades. In this guide, you’ll learn what the research says about its effectiveness, what types of anxiety it can treat, how to choose the right platform, and exactly what to expect when you start.

    What Is Online Therapy for Anxiety?

    Online therapy — also called teletherapy, telemental health, or virtual therapy — delivers professional psychological counseling through digital platforms. Sessions typically take place via secure video call, phone, or asynchronous messaging, depending on the provider and platform.

    For anxiety specifically, online therapy most commonly uses Cognitive Behavioral Therapy (CBT), a structured, evidence-based approach that helps you identify and change the thought patterns and behaviors driving your anxiety. Other modalities used include Acceptance and Commitment Therapy (ACT), Exposure and Response Prevention (ERP), and mindfulness-based interventions.

    It’s important to understand that online therapy is not a watered-down version of in-person care. A 2022 meta-analysis published in the Journal of Anxiety Disorders found that internet-delivered CBT produced outcomes comparable to face-to-face therapy for generalized anxiety disorder, panic disorder, and social anxiety — with effect sizes that most researchers considered clinically meaningful.

    According to the American Psychological Association, more than 75% of people who try psychotherapy for anxiety experience some measurable benefit. Online delivery expands access to that proven care significantly.

    Types of Anxiety That Online Therapy Can Address

    Anxiety is not a single condition. The DSM-5 — the diagnostic standard used by US mental health professionals — identifies several distinct anxiety disorders, and online therapy has demonstrated effectiveness across most of them.

    • Generalized Anxiety Disorder (GAD): Persistent, excessive worry about everyday matters — work, health, finances, relationships — lasting six months or more.
    • Panic Disorder: Recurrent, unexpected panic attacks accompanied by fear of future attacks or their consequences.
    • Social Anxiety Disorder: Intense fear of social or performance situations due to fear of embarrassment or judgment. (Learn more about social anxiety disorder here.)
    • Health Anxiety (Illness Anxiety Disorder): Preoccupation with having or developing a serious illness despite medical reassurance.
    • Separation Anxiety: Excessive fear or distress about separation from attachment figures, which also affects adults.
    • Specific Phobias: Marked fear or anxiety about a specific object or situation (heights, flying, needles, etc.).
    • Agoraphobia: Fear and avoidance of situations where escape might be difficult if panic occurs.

    A licensed online therapist will conduct a clinical assessment during your first session to determine your specific diagnosis and the most appropriate treatment approach. This process varies from person to person, and your therapist will tailor the plan accordingly.

    Causes and Risk Factors for Anxiety

    Understanding what drives anxiety helps you make sense of why therapy — rather than willpower alone — is usually necessary for lasting relief.

    Anxiety disorders arise from a complex interaction of biological, psychological, and environmental factors. Clinical evidence indicates no single cause explains all cases.

    Biological factors include:

    • Genetic predisposition — having a first-degree relative with an anxiety disorder increases your risk
    • Imbalances in neurotransmitters such as serotonin, norepinephrine, and GABA
    • Overactivity in the amygdala, the brain region responsible for processing fear
    • Chronic medical conditions such as thyroid disorders, cardiovascular disease, and diabetes

    Psychological and environmental factors include:

    • Childhood trauma or adverse childhood experiences (ACEs)
    • Chronic stress at work, in relationships, or related to finances
    • Major life transitions — job loss, divorce, relocation, retirement
    • Substance use or withdrawal (alcohol and benzodiazepines are notable contributors)
    • Prolonged social isolation

    The CDC has noted that anxiety significantly increased across US adult populations following the COVID-19 pandemic, with rates of anxiety symptoms three to four times higher in 2020–2022 compared to pre-pandemic baselines. While those rates have moderated, they remain elevated — particularly among adults aged 35–60 managing career, caregiving, and financial pressures simultaneously.

    How Online Therapy for Anxiety Is Diagnosed and Matched

    One common concern adults have about online therapy is whether they’ll receive a proper clinical assessment — or just be handed a chatbot and a worksheet.

    Reputable online therapy platforms employ licensed mental health professionals, including licensed clinical social workers (LCSWs), licensed professional counselors (LPCs), licensed marriage and family therapists (LMFTs), and psychologists (PhDs or PsyDs). Psychiatrists (MDs) who can prescribe medication are also available on some platforms.

    Your first session typically involves a clinical intake assessment covering:

    • Current symptoms and how long they’ve been present
    • How anxiety affects your daily functioning, sleep, work, and relationships
    • Personal and family mental health history
    • Previous treatment experiences
    • Any co-occurring conditions such as depression or substance use

    Validated screening tools such as the GAD-7 (Generalized Anxiety Disorder 7-item scale) are frequently used to measure symptom severity at intake and at regular intervals throughout treatment, giving both you and your therapist an objective way to track progress.

    Research suggests that the therapeutic alliance — the quality of the relationship between patient and therapist — is one of the strongest predictors of outcome in anxiety treatment. Most platforms allow you to switch therapists if the fit isn’t right, which is an important feature to look for when choosing a service.

    Treatment Options: What Online Therapy for Anxiety Actually Involves

    Effective online therapy for anxiety is structured, collaborative, and skills-based. Here’s what clinical evidence supports:

    Cognitive Behavioral Therapy (CBT)

    CBT is the gold-standard psychotherapy for anxiety disorders. A landmark NIH-funded review found CBT significantly outperformed control conditions in over 270 randomized controlled trials for anxiety. In online formats, CBT typically involves weekly 45–50 minute video sessions, between-session exercises (journaling, thought records, behavioral experiments), and regular progress review.

    Exposure Therapy

    For panic disorder, phobias, and health anxiety, exposure therapy — gradually confronting feared situations in a controlled, therapeutic way — is often integrated into CBT. Research from the Mayo Clinic confirms that exposure-based techniques remain among the most effective tools available for anxiety reduction, including when delivered virtually.

    Acceptance and Commitment Therapy (ACT)

    ACT helps you change your relationship with anxious thoughts rather than fighting them. Clinical evidence indicates ACT is particularly effective for GAD and chronic worry, and it translates well to online formats because of its emphasis on mindfulness practices you can build into daily life.

    Medication (When Appropriate)

    Online therapy platforms that include psychiatric services can facilitate medication management for anxiety. First-line medications typically recommended by psychiatrists include SSRIs (selective serotonin reuptake inhibitors) and SNRIs. These are often most effective when combined with psychotherapy. Most physicians recommend against relying on medication alone for long-term anxiety management without behavioral support.

    Note: Specific dosing decisions are always made by a licensed prescriber based on your individual medical history. Never adjust or discontinue psychiatric medication without consulting your doctor.

    Lifestyle Modifications as Complements

    Research suggests that regular aerobic exercise can reduce anxiety symptoms by 20–30% — comparable in some studies to the effects of medication for mild to moderate anxiety. Sleep hygiene, caffeine reduction, and structured relaxation practices (diaphragmatic breathing, progressive muscle relaxation) are evidence-supported complements to professional treatment, not replacements.

    Living With Anxiety: Practical Day-to-Day Management

    Therapy is most effective when supported by consistent daily habits. Most licensed therapists will help you build an individualized plan, but the following are commonly recommended across the clinical literature:

    • Sleep consistency: Anxiety and sleep are bidirectionally linked. The NIH identifies poor sleep as both a symptom and a driver of anxiety. Maintaining a consistent sleep-wake schedule — even on weekends — is a foundational recommendation.
    • Physical activity: Aim for at least 150 minutes of moderate-intensity activity per week, per CDC guidelines, which also benefits cardiovascular health and metabolic function.
    • Caffeine and alcohol awareness: Both can significantly worsen anxiety symptoms. Research suggests tracking your intake and discussing it with your therapist or physician.
    • Social connection: Isolation amplifies anxiety. Maintaining regular contact with trusted people — even through digital means — is associated with better mental health outcomes.
    • Mindfulness practice: Even 10 minutes of daily mindfulness has shown measurable reductions in anxiety symptoms in multiple clinical trials, according to research from Johns Hopkins.

    If you’re also navigating relationship stress as part of your anxiety experience, online therapy for relationship issues may be a helpful complementary resource to explore with your therapist.

    When to Call Your Doctor or Seek Emergency Care

    Online therapy is appropriate for mild to moderate anxiety. However, certain symptoms require immediate medical or psychiatric attention.

    Seek emergency care immediately if you experience:

    • Thoughts of suicide or self-harm
    • Inability to care for yourself or others in your care
    • A panic attack you cannot distinguish from a cardiac event (chest pain, shortness of breath, arm pain — always rule out cardiac causes first)
    • Psychosis, severe disorientation, or loss of contact with reality
    • Alcohol or drug withdrawal symptoms combined with severe anxiety

    Schedule an urgent appointment with your doctor or psychiatrist if:

    • Your anxiety has significantly worsened despite therapy
    • You are unable to leave your home or perform basic daily functions
    • You are using alcohol or substances to manage anxiety symptoms
    • You suspect a medical condition (thyroid disorder, cardiac arrhythmia, adrenal issues) may be contributing to your symptoms

    What to tell your doctor: Bring a brief written summary of your symptoms — when they occur, how long they last, and how they affect your daily life. Mention any medications or supplements you’re taking, and let your doctor know you are engaged in or seeking online therapy. This coordination of care improves outcomes significantly.

    Frequently Asked Questions

    Is online therapy as effective as in-person therapy for anxiety?
    For most types of anxiety disorders, research suggests yes. Multiple meta-analyses — including studies referenced by the NIH — have found internet-delivered CBT produces outcomes comparable to face-to-face therapy for GAD, panic disorder, and social anxiety. Severe anxiety or complex co-occurring conditions may benefit from in-person care.

    How long does online therapy for anxiety take to work?
    This varies from person to person. Many people notice meaningful symptom improvement within 8–12 sessions of structured CBT. Some conditions — particularly those with trauma components or long-standing patterns — may require longer treatment. Clinical evidence suggests that completing a full course of therapy, rather than stopping when you feel slightly better, leads to more durable results.

    Does health insurance cover online therapy for anxiety?
    Many US health insurance plans now cover telemental health services, particularly following federal parity laws and expanded telehealth provisions post-2020. Coverage varies by plan and provider. Contact your insurer directly to verify coverage, and look for platforms that accept your insurance or provide superbills for reimbursement. Understanding your health insurance benefits is a critical first step before starting care.

    What’s the difference between online therapy and therapy apps?
    Online therapy connects you with a licensed human therapist in real-time or asynchronous sessions. Therapy apps may offer guided programs, mood tracking, or AI-driven tools — which can complement professional care but are not a substitute for licensed clinical treatment. For diagnosable anxiety disorders, working with a licensed professional is the clinical standard of care.

    Can online therapy help anxiety that’s related to grief or loss?
    Yes. Grief frequently triggers or intensifies anxiety symptoms, and many therapists specialize in both. If grief is central to your experience, you may want to explore resources specifically addressing that intersection. Online therapy for grief and loss is a well-documented area of telehealth with strong clinical support.

    Conclusion

    Living with anxiety doesn’t have to mean managing it alone — or managing it poorly because access to care feels out of reach. Online therapy has made evidence-based treatment more accessible, more flexible, and more affordable than at any point in the history of mental health care.

    The research is clear: structured psychological therapy, particularly CBT, works for anxiety disorders. And delivered through a secure digital platform by a licensed professional, it can work for you too.

    The most important step is the first one — reaching out to a qualified professional. Whether that means starting with your primary care physician, contacting your insurance to find covered providers, or signing up for a reputable telehealth platform, getting proper support is both possible and worthwhile.

    You don’t have to wait two years, like Marcus did.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Bipolar Disorder in Adults: Symptoms, Types & Treatment

    Bipolar Disorder in Adults: Symptoms, Types & Treatment

    Bipolar disorder affects millions of Americans — and for many, the road to an accurate diagnosis takes years of misdiagnosis and confusion.

    Consider Marcus, a 42-year-old accountant from Ohio. For most of his adult life, he cycled between weeks of explosive energy — barely sleeping, taking on five projects at once, feeling invincible — and stretches of deep, paralyzing depression where he could barely get out of bed. His doctor initially diagnosed him with depression. It wasn’t until his third psychiatrist, nearly a decade later, that he finally heard the words: bipolar disorder.

    Marcus’s story is far from rare. According to the National Institute of Mental Health (NIMH), approximately 4.4% of U.S. adults will experience bipolar disorder at some point in their lives — that’s nearly 11 million Americans. Yet the average delay between symptom onset and correct diagnosis is still estimated at six to ten years.

    In this guide, you’ll learn exactly what bipolar disorder is, how to recognize its symptoms, what causes it, how it’s diagnosed, and what modern treatment options can help you or someone you love live a full, stable life.

    What Is Bipolar Disorder?

    Bipolar disorder — formerly known as manic-depressive illness — is a chronic brain condition characterized by dramatic, cyclical shifts in mood, energy, activity levels, and the ability to carry out everyday tasks. These shifts go far beyond the ordinary emotional ups and downs most people experience.

    The condition exists on a spectrum, and clinicians recognize several distinct types:

    • Bipolar I Disorder: Defined by at least one full manic episode lasting seven days or more, which may be severe enough to require hospitalization. Depressive episodes typically follow.
    • Bipolar II Disorder: Involves a pattern of depressive episodes and hypomanic episodes (less severe than full mania) but no full manic episodes.
    • Cyclothymic Disorder (Cyclothymia): A milder form marked by numerous periods of hypomanic and depressive symptoms over at least two years, though these don’t meet the full criteria for a hypomanic or depressive episode.
    • Other Specified / Unspecified Bipolar Disorders: Bipolar-like symptoms that don’t fit the above categories but still cause clinically significant distress.

    According to the NIMH, bipolar disorder is among the top 20 leading causes of disability worldwide. It affects men and women roughly equally, though the pattern of episodes can differ. Women, for instance, tend to experience more depressive episodes and rapid cycling (four or more mood episodes per year).

    Understanding which type you have is critical — because treatment strategies differ significantly between them.

    Signs and Symptoms of Bipolar Disorder

    One of the reasons bipolar disorder is so frequently misdiagnosed is that people often seek help only during depressive episodes — which can look nearly identical to major depression. Clinicians may never hear about the manic or hypomanic phases unless they specifically ask.

    Symptoms of a Manic Episode

    • Unusually elevated, expansive, or irritable mood lasting at least one week
    • Decreased need for sleep (feeling rested after only 3 hours)
    • Racing thoughts and rapid, pressured speech
    • Grandiosity — inflated self-esteem or feeling unusually special or powerful
    • Increased goal-directed activity or physical agitation
    • Impulsive or reckless behavior (excessive spending, risky sexual activity, poor financial decisions)
    • Distractibility — attention jumping from one thing to another

    Symptoms of a Depressive Episode

    • Persistent sad, empty, or hopeless mood
    • Loss of interest or pleasure in activities once enjoyed
    • Fatigue or loss of energy nearly every day
    • Significant changes in appetite or weight
    • Sleep disturbances — insomnia or sleeping too much
    • Difficulty concentrating, remembering, or making decisions
    • Feelings of worthlessness or excessive guilt
    • Thoughts of death or suicide

    Hypomanic Episodes

    Hypomanic episodes mirror manic symptoms but are less severe and shorter in duration (at least four days). Importantly, they don’t cause the same level of functional impairment — which is why people with Bipolar II often don’t recognize hypomania as a problem. They may even feel productive and energized during these periods.

    A 2019 analysis published in the Journal of Affective Disorders found that patients with bipolar disorder spent significantly more time in depressive states than in manic or hypomanic states — underscoring why depression is often the presenting complaint.

    ⚠️ Red flag: If you or someone you know is experiencing thoughts of suicide or self-harm during a depressive phase, this requires immediate professional attention. Call or text 988 (the Suicide & Crisis Lifeline) or go to your nearest emergency room.

    Causes and Risk Factors

    Bipolar disorder doesn’t have a single cause. Research suggests it results from a complex interaction of genetic, neurological, and environmental factors.

    Genetic Factors

    Bipolar disorder has one of the strongest genetic links of any psychiatric condition. According to research supported by the NIH, individuals with a first-degree relative (parent, sibling) with bipolar disorder have a 5 to 10 times higher risk of developing it themselves. Twin studies suggest heritability rates between 60% and 80%.

    Brain Structure and Neurochemistry

    Neuroimaging studies have identified differences in brain structure and function in individuals with bipolar disorder, particularly in areas governing emotional regulation, impulse control, and decision-making — including the prefrontal cortex and amygdala. Imbalances in neurotransmitters such as dopamine, serotonin, and norepinephrine are also strongly implicated.

    Environmental and Lifestyle Triggers

    • High-stress life events (job loss, divorce, bereavement)
    • Disrupted sleep patterns — a major trigger for both manic and depressive episodes
    • Substance use — alcohol and drug use can trigger or worsen episodes
    • Hormonal changes — particularly relevant for women during postpartum periods and menopause
    • Trauma and adverse childhood experiences (ACEs)

    It’s worth noting that this varies from person to person — some individuals have frequent episodes triggered by identifiable stressors, while others cycle with no clear external cause.

    Diagnosis: What to Expect

    There is no blood test or brain scan that diagnoses bipolar disorder. Diagnosis is based on a comprehensive clinical evaluation — and it takes time and expertise to get right.

    The Diagnostic Process

    Your doctor or mental health provider will typically:

    • Conduct a thorough psychiatric interview, reviewing your mood history, symptoms, sleep patterns, and behaviors
    • Use structured diagnostic tools such as the Mood Disorder Questionnaire (MDQ) or the DSM-5 criteria (Diagnostic and Statistical Manual of Mental Disorders, 5th Edition)
    • Rule out other conditions — including thyroid disorders, neurological conditions, ADHD, major depressive disorder, and substance use disorders — that can mimic bipolar symptoms
    • Order blood tests and possibly a thyroid panel to exclude medical causes
    • Gather collateral history from family members when possible, since patients may not recall or recognize past manic episodes

    Who Should You See?

    While your primary care physician is a great starting point, a psychiatrist is the most qualified specialist to diagnose and manage bipolar disorder. If you’ve been treated for depression without adequate response, or if you’ve experienced what could be manic episodes, it’s worth asking for a psychiatric evaluation specifically.

    The American Psychiatric Association recommends that a bipolar disorder diagnosis never be made based on symptoms during a single episode alone — longitudinal observation matters.

    Treatment Options for Bipolar Disorder

    Here’s the good news: bipolar disorder is highly treatable. Most people with the condition can achieve significant symptom stabilization and lead productive, meaningful lives — especially when treatment is started early and maintained consistently.

    Mood Stabilizing Medications

    Medication is the cornerstone of bipolar treatment. The most commonly used classes include:

    • Mood stabilizers — Lithium remains the gold-standard treatment for bipolar disorder, with decades of evidence supporting its effectiveness in preventing both manic and depressive episodes. Valproate and lamotrigine are also widely used.
    • Atypical antipsychotics — Medications such as quetiapine, olanzapine, and aripiprazole are FDA-approved for bipolar disorder and may be used alone or in combination with mood stabilizers.
    • Antidepressants — These are used cautiously and typically only alongside a mood stabilizer, as they can trigger manic episodes if used alone.

    According to a landmark meta-analysis in The Lancet, lithium was associated with a significant reduction in suicide risk compared to other treatments — one of its most clinically important benefits.

    Important: Never adjust or stop your medication without consulting your prescribing physician. Discontinuing mood stabilizers abruptly can trigger severe episodes.

    Psychotherapy

    Clinical evidence strongly supports psychotherapy as a complement to medication in bipolar disorder management. The most effective approaches include:

    • Cognitive Behavioral Therapy (CBT): Helps identify and reframe distorted thinking patterns and develop coping strategies for mood episodes.
    • Interpersonal and Social Rhythm Therapy (IPSRT): Focuses on stabilizing daily routines — especially sleep schedules — which are tightly linked to mood regulation in bipolar disorder.
    • Family-Focused Therapy (FFT): Involves family members in the treatment process, improving communication and reducing relapse triggers at home.
    • Psychoeducation: Teaching patients and families about the illness, its triggers, and early warning signs is proven to reduce hospitalizations.

    Lifestyle as a Complement

    Research indicates that structured lifestyle habits meaningfully support mood stability:

    • Maintaining consistent sleep and wake times (even on weekends)
    • Regular aerobic exercise, which clinical evidence suggests reduces depressive symptoms
    • Avoiding alcohol and recreational drugs entirely
    • Stress management practices such as mindfulness and relaxation techniques
    • Keeping a mood journal to track patterns and triggers

    If you’re exploring therapy options, our guide on Online Therapy for Grief and Loss offers helpful context on how virtual mental health support can fit into your care plan. Many platforms now offer specialized bipolar-informed therapy delivered remotely.

    Living With Bipolar Disorder

    Managing bipolar disorder is a long-term commitment — but it is absolutely manageable. Many people with the condition build successful careers, meaningful relationships, and rich lives. The key lies in ongoing self-awareness, consistent treatment, and a strong support network.

    Practical Day-to-Day Strategies

    • Create a crisis plan: Work with your mental health team to document early warning signs and agreed-upon action steps before a crisis occurs.
    • Build a sleep sanctuary: Sleep disruption is one of the most powerful triggers for mood episodes. Prioritize sleep hygiene as a medical necessity, not a luxury.
    • Communicate with your employer (if comfortable): The Americans with Disabilities Act (ADA) may entitle you to reasonable workplace accommodations.
    • Lean on peer support: Organizations like the Depression and Bipolar Support Alliance (DBSA) offer free support groups both in-person and online across the U.S.
    • Track your mood daily: Apps like Daylio or eMoods can help you identify patterns that you and your doctor can act on early.

    You may also find value in understanding how mood disorders often appear alongside other conditions. Our article on Social Anxiety Disorder explores how anxiety frequently co-occurs with bipolar disorder — something clinicians now routinely screen for.

    Prevention of Episode Relapse

    According to the NIMH, maintaining medication adherence is the single most powerful predictor of long-term stability in bipolar disorder. Research suggests that up to 40% of people with bipolar disorder stop their medications within the first year — often during a period of feeling well. This is one of the most common causes of relapse.

    Work with your doctor to set realistic expectations: feeling stable doesn’t mean the medication is no longer needed. It usually means it’s working.

    When to Call Your Doctor — Emergency Signs

    Certain situations require immediate medical attention. Do not wait for a scheduled appointment if you or someone you love is experiencing:

    • Thoughts of suicide or self-harm
    • Psychotic symptoms — hallucinations, delusions, severely disorganized thinking
    • A manic episode so severe the person cannot care for themselves or is putting others at risk
    • Complete refusal to eat, sleep, or take prescribed medications over multiple days
    • Signs of medication toxicity (lithium toxicity symptoms include tremors, confusion, nausea, and coordination problems)

    📞 In a mental health emergency: Call 988 (Suicide & Crisis Lifeline), 911, or go to your nearest emergency room. You can also text "HELLO" to 741741 (Crisis Text Line).

    What to tell your doctor at your next visit:

    • Any new symptoms since your last visit — including subtle mood changes
    • Sleep pattern disruptions
    • Side effects from current medications
    • Any significant stressors in your life
    • Whether you’ve used alcohol or any other substances

    Frequently Asked Questions

    Can bipolar disorder be cured?

    Bipolar disorder is a chronic condition — there is currently no cure. However, research consistently shows that with appropriate treatment (medication, therapy, and lifestyle adjustments), most people achieve significant long-term stability. Think of it similarly to how diabetes is managed: it requires ongoing attention, but it does not have to define or limit your life.

    Is bipolar disorder the same as mood swings?

    No. Most people experience ordinary mood fluctuations throughout the day or week. Bipolar disorder involves distinct episodes — lasting days to weeks — of mania, hypomania, or depression that represent a clear departure from baseline functioning and often impair relationships, work, or personal safety.

    Can children and teenagers have bipolar disorder?

    Yes, though it can be more difficult to diagnose in younger people because symptoms often overlap with ADHD, adolescent behavior, and other mood disorders. The American Academy of Child and Adolescent Psychiatry recommends comprehensive evaluation by a child psychiatrist when bipolar disorder is suspected in minors.

    What happens if bipolar disorder goes untreated?

    Untreated bipolar disorder is associated with significantly worse outcomes — including more frequent and severe episodes, increased risk of substance use disorders, damaged relationships, occupational difficulties, and a substantially elevated risk of suicide. According to the NIMH, up to 30 times higher suicide risk compared to the general population has been reported in studies of untreated bipolar disorder.

    Does bipolar disorder get worse with age?

    This varies considerably from person to person. For some individuals, episodes may become more frequent without treatment — a phenomenon called "kindling." For others, episodes may decrease in severity over time, particularly with consistent treatment and strong social support. Early diagnosis and treatment are associated with better long-term outcomes.

    Conclusion

    Bipolar disorder is one of the most misunderstood — and underdiagnosed — conditions in American mental health. But it is also one of the most treatable. With the right combination of medication, psychotherapy, lifestyle structure, and professional support, millions of people with bipolar disorder go on to thrive.

    If you recognize yourself or someone you love in these pages, the most important step you can take right now is to make that appointment. Talk to your primary care physician or ask for a referral to a psychiatrist. Bring your notes. Share your full history — including the highs, not just the lows.

    You deserve an accurate diagnosis. You deserve effective treatment. And you deserve a life that isn’t defined by your diagnosis — but supported by the right care to help you live it fully.

    For more on how mental health conditions often intersect, explore our in-depth coverage of OCD in Adults, which frequently co-occurs with mood disorders like bipolar disorder.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Health Insurance for Prescription Drugs: What’s Covered

    Health Insurance for Prescription Drugs: What’s Covered

    Health Insurance for Prescription Drugs: What’s Covered

    Understanding your prescription drug benefits could save you thousands of dollars — and keep you on the medications you actually need.

    Margaret, 64, was managing her rheumatoid arthritis well — until her insurer switched her specialty biologic medication to a higher tier on the formulary. Overnight, her monthly out-of-pocket cost jumped from $45 to $680. She had never heard the word "formulary" before. She had no idea her plan could change which medications it covered, or at what cost, during the plan year.

    If that scenario sounds familiar, you are not alone. According to the Kaiser Family Foundation, nearly 29% of American adults report not taking their medications as prescribed because of cost — and many of those cost barriers stem directly from confusion about how prescription drug coverage works within their health insurance plan.

    In this guide, you will learn exactly how prescription drug coverage functions inside your health plan, what a formulary is and why it matters, how drug tiers affect your wallet, and what your rights are when your plan denies coverage for a medication your doctor prescribed.


    What Is Prescription Drug Coverage in Health Insurance?

    Prescription drug coverage — sometimes called Part D (in the Medicare context) or a pharmacy benefit — is the component of your health insurance plan that pays a portion of the cost of medications your doctor prescribes. Most employer-sponsored plans, marketplace plans under the Affordable Care Act (ACA), and Medicare plans include some form of prescription drug coverage, though the specifics vary widely.

    The Affordable Care Act established prescription drugs as one of the ten essential health benefits that most health plans sold in the individual and small group markets must cover. This was a landmark shift — before the ACA, many plans either excluded drug coverage or imposed lifetime caps that left patients unprotected.

    According to the CDC, approximately 131 million Americans — nearly half the adult population — use at least one prescription medication regularly. For people managing chronic conditions like hypertension, diabetes, depression, or asthma, consistent access to medications is not optional. It is central to staying well and avoiding hospitalizations that cost far more than the prescriptions themselves.

    Understanding this benefit is, in a very real sense, a health matter — not just a financial one.


    What Is a Formulary — and Why Does It Control Your Coverage?

    A formulary is a list of prescription drugs that your insurance plan has agreed to cover. Think of it as your plan’s approved medication catalog. If your medication is on the formulary, your plan will help pay for it. If it is not, you may be paying the full retail price out of pocket — which can be staggering for specialty medications.

    Formularies are not static. Insurance companies can update them annually — and sometimes mid-year — adding or removing drugs, or shifting medications to more expensive tiers. The NIH’s National Library of Medicine notes that formulary changes are one of the leading drivers of non-adherence, particularly among patients over 50 managing multiple chronic conditions.

    Here is what you need to know about how formularies are structured:

    • Covered drugs are listed by tier (see next section)
    • Non-formulary drugs may require prior authorization or an exception request
    • Generic vs. brand-name distinctions are central to which tier a drug lands on
    • Your plan’s formulary is available on your insurer’s website or by calling member services

    Before enrolling in any health plan during open enrollment, one of the most important steps you can take is to search your specific medications on each plan’s formulary — not just compare premiums.


    Drug Tiers: How Your Costs Are Determined

    Most health insurance plans organize covered medications into cost tiers — typically between three and six levels. The higher the tier, the more you pay out of pocket. Here is a general breakdown of how most plans structure their drug tiers:

    • Tier 1 — Preferred Generics: Lowest cost, often $0–$15 per fill. These are off-patent drugs that are chemically identical to brand-name versions but cost a fraction of the price.
    • Tier 2 — Non-Preferred Generics or Preferred Brands: Moderate cost, often $20–$60 per fill. These may include brand-name drugs that have a preferred status with the insurer due to rebate agreements.
    • Tier 3 — Non-Preferred Brands: Higher cost, often $50–$150 per fill. These are brand-name drugs for which a generic equivalent may exist.
    • Tier 4 — Specialty Medications: Highest cost — often 20–33% coinsurance rather than a flat copay, which can mean hundreds or thousands of dollars per fill. This tier typically includes biologics, cancer treatments, and complex disease-modifying drugs.

    A 2024 analysis by the Commonwealth Fund found that patients on specialty medications often face annual out-of-pocket costs exceeding $5,000 even with insurance coverage — a figure that has driven calls for federal spending caps on out-of-pocket drug costs.

    The good news: the Inflation Reduction Act of 2022 capped out-of-pocket drug costs for Medicare beneficiaries at $2,000 per year beginning in 2025 — a historic change for seniors managing complex medication regimens.


    Types of Prescription Drug Plans: What’s Available to You

    Your access to prescription drug coverage depends largely on what type of health insurance you have. Here is a clear breakdown:

    Employer-Sponsored Health Plans

    Most Americans under 65 receive health insurance through their employer. These plans typically include integrated prescription drug coverage with formularies negotiated by the employer’s plan administrator. According to the Kaiser Family Foundation’s 2024 Employer Health Benefits Survey, 91% of covered workers had prescription drug benefits included in their employer plan.

    ACA Marketplace Plans

    Plans sold on the Health Insurance Marketplace (Healthcare.gov) must cover prescription drugs as an essential health benefit. Bronze, Silver, Gold, and Platinum plans all include drug coverage, but cost-sharing differs significantly. Low-income enrollees who qualify for cost-sharing reduction (CSR) subsidies may pay substantially less for their medications on Silver plans.

    Medicare Part D

    Medicare Part D is a standalone prescription drug plan available to Medicare beneficiaries. It is offered by private insurers approved by the Centers for Medicare & Medicaid Services (CMS). As of 2025, the $2,000 annual out-of-pocket cap and new Medicare Drug Price Negotiation Program — which allows Medicare to negotiate prices directly with manufacturers — have significantly reshaped costs for many seniors. If you are nearing 65, understanding Part D during your Initial Enrollment Period is critical to avoiding late enrollment penalties.

    Medicaid

    Medicaid covers prescription drugs for eligible low-income individuals and families. Coverage details vary by state, but all state Medicaid programs are required to cover a broad range of drugs. Some states offer more generous formularies than others.


    Prior Authorization, Step Therapy, and Quantity Limits

    Even when a drug appears on your plan’s formulary, your insurer may impose additional requirements before they agree to cover it. These are among the most frustrating — and least-understood — aspects of prescription drug coverage.

    Prior Authorization (PA)

    Prior authorization means your insurance company requires your doctor to submit documentation proving that a medication is medically necessary before they will cover it. This process can take days to weeks and sometimes results in denial even when your physician has clearly prescribed the medication for a legitimate reason.

    According to the American Medical Association, 94% of physicians report that prior authorization causes delays in care, and 33% say it has led to serious adverse events for patients.

    Step Therapy ("Fail First")

    Step therapy requires you to try — and fail — on a cheaper medication before your insurer will cover the one your doctor originally prescribed. For example, you might be required to try two generic antidepressants before your plan will cover the brand-name medication your psychiatrist recommended.

    Many states have passed step therapy reform laws giving patients the right to request exemptions, particularly when step therapy would delay treatment for a serious condition.

    Quantity Limits

    Your plan may limit how much of a medication you can receive per fill or per month — sometimes fewer pills than your doctor prescribed. This is especially common with pain medications, sedatives, and certain specialty drugs.

    If any of these barriers are affecting your access to medication, your doctor can submit an exception or appeal request on your behalf. You also have the right to formally appeal any coverage denial — and insurers are required to respond within specific time frames under federal law.


    How to Reduce Your Prescription Drug Costs

    There are practical, legitimate strategies that can lower what you pay for medications — even within the constraints of your current plan.

    • Ask for generics: If your doctor prescribes a brand-name drug, ask whether a therapeutically equivalent generic is available. Generics are FDA-approved and held to the same efficacy and safety standards as brand-name drugs.
    • Use GoodRx or similar discount programs: These are not insurance, but they can sometimes reduce your cost below your insurance copay — particularly for common generics. You can compare prices and use the lower option.
    • Check for manufacturer assistance programs: Many pharmaceutical companies offer Patient Assistance Programs (PAPs) or copay assistance cards for brand-name or specialty drugs. Your doctor’s office or a social worker can help you apply.
    • Use a 90-day supply: Many plans charge less per pill when you order a 90-day supply through mail-order pharmacy versus a 30-day retail fill.
    • Review your plan at open enrollment: If your medications have moved to a higher tier, a different plan — even with a higher premium — may cost you less overall if it covers your drugs at a lower tier.
    • Request a formulary exception: If your drug is not covered or is on a high tier, your physician can submit a formulary exception request documenting medical necessity. These are sometimes approved.

    For more on how health insurance intersects with specific conditions, our guide on Health Insurance for Cancer Care: What’s Covered explores how drug coverage applies in oncology — where medication costs can be especially significant.


    When to Call Your Doctor or Take Action Immediately

    Prescription drug coverage issues become urgent health matters in certain situations. Do not wait if:

    • You have stopped taking a critical medication because of cost — tell your doctor immediately. Abruptly stopping medications like corticosteroids, beta-blockers, antiepileptics, or antidepressants can cause serious withdrawal effects or disease relapse.
    • Your coverage was denied for a medication treating a serious condition — request an expedited appeal. Federal law requires expedited reviews when a standard review timeline would seriously jeopardize your health.
    • You experience a health crisis you believe is linked to being unable to access your medication — go to an emergency room or urgent care and inform your treatment team.
    • Your plan changes mid-year and a critical medication is no longer covered — contact your state insurance commissioner’s office or a benefits counselor immediately.

    At your next routine appointment, bring a complete list of all your current medications and ask your doctor to review whether any lower-cost alternatives might work equally well for your situation. This conversation is more productive than most patients expect.

    If you are approaching Medicare eligibility, this is also the time to discuss your medication list with a Medicare counselor. Our related guide on Health Insurance for Maternity & Newborn Care is a useful companion resource if you are navigating coverage decisions at life transitions more broadly.


    Frequently Asked Questions

    What happens if my medication is not on my plan’s formulary?

    If your drug is not on the formulary, you have several options: your doctor can request a formulary exception, you can appeal the coverage denial, you can ask if a covered alternative is therapeutically equivalent, or you can use a discount program and pay out of pocket. Non-formulary does not automatically mean impossible to get covered — it means you have to advocate for it.

    Can my insurance company change my drug coverage mid-year?

    Generally, insurers are not allowed to remove drugs that patients are actively taking mid-year without notice — federal and state regulations provide some protection. However, changes can occur at plan renewal. Always check your formulary before your plan renews each year during open enrollment.

    Is prescription drug coverage the same in all ACA marketplace plans?

    No. While all marketplace plans must cover prescription drugs as an essential health benefit, the specific drugs covered, the tier structure, and the cost-sharing amounts vary significantly between plans — even within the same metal tier. Always check the specific formulary for each plan before enrolling.

    Does Medicare Part D cover all my medications?

    Not necessarily. Each Part D plan has its own formulary. Medicare requires that Part D plans cover at least two drugs in most therapeutic categories, and they must cover all drugs in six protected classes (including cancer drugs and antidepressants), but coverage varies. Compare plans annually using the Medicare Plan Finder tool at Medicare.gov.

    What is the Medicare out-of-pocket cap for prescription drugs in 2025?

    Beginning in 2025, Medicare beneficiaries have an annual out-of-pocket cap of $2,000 for prescription drugs covered under Part D. This was established by the Inflation Reduction Act of 2022 and represents one of the most significant changes to Medicare drug coverage in decades. The cap applies only to covered Part D drugs, not drugs purchased outside the plan.


    Conclusion

    Prescription drug coverage is one of the most consequential — and most confusing — components of your health insurance plan. From formularies and drug tiers to prior authorization and appeals, understanding how this system works puts you in a stronger position to protect both your health and your finances.

    You do not need to navigate this alone. Your doctor’s office, your insurer’s member services team, and a licensed benefits counselor or social worker can all help you advocate for coverage when barriers arise. The most important step is never quietly stopping a medication because of cost without first talking to your healthcare provider about alternatives.

    Review your formulary every year at open enrollment. Ask questions. Appeal denials. Know your rights. Consistent access to the medications you need is not a luxury — it is a foundation of long-term health.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Exercise and Diabetes: How Physical Activity Controls Blood Sugar

    Exercise and Diabetes: How Physical Activity Controls Blood Sugar

    Physical activity is one of the most powerful — and underused — tools for managing type 2 diabetes every single day.

    Marcus, 54, had been managing type 2 diabetes for six years. He took his metformin faithfully, watched his carbs, and checked his blood sugar regularly. But his A1C — a key measure of average blood sugar over three months — kept hovering above 8%. Then his endocrinologist suggested something simple: a 20-minute walk after dinner, five nights a week. Within three months, his A1C dropped to 7.1%.

    His story isn't unique. According to the CDC, more than 38 million Americans are living with diabetes, and the vast majority have type 2. What many don't realize is that exercise and diabetes management are deeply connected — not as an optional add-on, but as a clinically proven strategy for lowering blood sugar, improving insulin sensitivity, and reducing long-term complications.

    In this guide, you'll learn exactly how physical activity affects blood sugar, which types of exercise work best, how to stay safe while working out with diabetes, and practical tips for building a sustainable routine.

    Why Exercise Matters So Much for Diabetes Management

    Type 2 diabetes is characterized by insulin resistance — a condition where your body's cells don't respond well to insulin, the hormone that allows glucose (sugar) to enter cells for energy. As a result, glucose builds up in the bloodstream, leading to high blood sugar levels.

    Exercise directly addresses this problem. When your muscles contract during physical activity, they can absorb glucose from the bloodstream without needing insulin. This makes exercise one of the few tools that lowers blood sugar independently of insulin function.

    A landmark meta-analysis published through NIH databases found that structured exercise programs reduced A1C levels by an average of 0.67% in adults with type 2 diabetes — comparable to the effect of some oral medications. When combined with dietary changes, the impact is even more significant.

    Beyond blood sugar control, regular physical activity helps reduce cardiovascular risk (heart disease is the leading cause of death in people with diabetes), supports weight management, lowers blood pressure, and improves mood and energy levels — all critical elements of long-term diabetes wellness.

    How Exercise Lowers Blood Sugar: The Physiology

    Understanding what happens inside your body during exercise can help you make smarter choices about your routine.

    During aerobic exercise (like walking, cycling, or swimming), your muscles increase their demand for glucose. They pull sugar directly from your bloodstream and also stimulate your cells to become more sensitive to insulin — an effect that can last 24 to 72 hours after a single workout session.

    During resistance training (like lifting weights or using resistance bands), you build lean muscle mass. Muscle tissue is metabolically active — meaning it burns more glucose at rest than fat tissue does. More muscle means better long-term glucose uptake, even when you're not exercising.

    Research from the American Diabetes Association (ADA) indicates that combining both aerobic and resistance exercise produces significantly greater improvements in A1C and insulin sensitivity than either type alone.

    It's also worth noting that exercise has an acute (immediate) blood sugar-lowering effect. Many people with type 2 diabetes see their blood sugar drop 20 to 50 points during or right after moderate aerobic activity — though this varies from person to person depending on fitness level, medication, and baseline glucose.

    Best Types of Exercise for Diabetes Control

    Not all exercise is created equal when it comes to blood sugar management. Here's what clinical evidence supports:

    Aerobic Exercise

    The ADA recommends at least 150 minutes of moderate-intensity aerobic activity per week for adults with type 2 diabetes. That breaks down to about 30 minutes, five days a week — or three 10-minute walks spread throughout the day, which research suggests may be equally effective.

    • Brisk walking — the most accessible option; proven to lower post-meal blood sugar
    • Cycling (stationary or outdoor) — low impact, easy on joints
    • Swimming — ideal for those with neuropathy or joint pain
    • Dancing — enjoyable, sustainable, and effective
    • Water aerobics — gentle and effective for older adults

    Moderate intensity means you're breathing harder than usual but can still hold a conversation. A good target is reaching 50–70% of your maximum heart rate.

    Resistance Training

    Clinical evidence from Johns Hopkins Medicine suggests that resistance training two to three times per week significantly improves insulin sensitivity and helps maintain muscle mass — which tends to decline with age and can worsen glucose control.

    • Free weights or machines at the gym
    • Resistance bands (affordable and home-friendly)
    • Bodyweight exercises (squats, lunges, push-ups)
    • Yoga and Pilates (also improve flexibility and stress levels)

    High-Intensity Interval Training (HIIT)

    Emerging research suggests that HIIT — short bursts of intense effort alternated with rest — can be highly effective for improving blood sugar and cardiovascular fitness, even in less time than traditional aerobic workouts. However, HIIT may cause blood sugar spikes in some individuals, particularly those on insulin. Always consult your doctor before starting HIIT if you have diabetes.

    Exercise Safety: What Every Diabetic Should Know

    Exercising with diabetes is generally safe — and strongly encouraged — but requires some precautions to prevent dangerous blood sugar swings.

    Before You Exercise

    • Check your blood sugar before starting. Most physicians recommend checking if your glucose is below 100 mg/dL or above 250 mg/dL before exercising, as both extremes require caution.
    • If your blood sugar is below 100 mg/dL, have a small snack (such as 15 grams of carbohydrates) before beginning.
    • If your blood sugar is above 250 mg/dL with ketones present, postpone exercise and contact your healthcare provider.

    During Exercise

    • Keep fast-acting glucose sources nearby (glucose tablets, juice, or regular soda) in case of hypoglycemia — low blood sugar.
    • Stay hydrated. Dehydration can raise blood sugar levels.
    • If you feel dizzy, shaky, confused, or unusually fatigued, stop immediately and check your glucose.

    After Exercise

    • Check your blood sugar within 30 minutes of finishing.
    • Be aware of delayed hypoglycemia — blood sugar can continue to drop for up to 24 hours after intense or prolonged activity, particularly in people on insulin or certain medications.
    • Rehydrate and refuel with a balanced snack if needed.

    According to the Mayo Clinic, people with diabetic neuropathy (nerve damage in the feet) should wear proper supportive footwear during exercise and inspect their feet after every session to prevent unnoticed injuries from progressing to serious complications. For more on how diabetes affects your feet and nerves, see our related article on Diabetic Retinopathy: Protect Your Vision With Diabetes, which also covers how systemic complications affect daily life.

    Building a Sustainable Exercise Routine With Diabetes

    Starting an exercise program is exciting. Sticking with it is the real challenge. Here are evidence-based strategies to help you build lasting habits:

    Start small and build gradually. If you haven't been active, begin with 10 minutes of walking per day and add five minutes each week. Research from the Cleveland Clinic shows that even short bouts of activity — broken into three 10-minute segments — provide meaningful metabolic benefits.

    Schedule workouts like appointments. Consistency matters more than intensity. Pick specific times that work with your daily routine and treat them as non-negotiable.

    Track your blood sugar responses. Logging your glucose before and after different types of workouts helps you understand your unique patterns and optimize your routine accordingly. This connects directly with your overall diabetes management strategy, including understanding how lifestyle factors like alcohol also affect your numbers.

    Find activities you enjoy. Sustainable exercise is enjoyable exercise. Whether it's pickleball, gardening, or ballroom dancing — if you love it, you'll do it consistently.

    Work with your healthcare team. Before dramatically increasing activity levels, talk to your doctor or a certified diabetes care and education specialist (CDCES). They can help you adjust medications, set safe target blood sugar ranges for exercise, and tailor a plan to your fitness level and health status.

    Consider cardiac screening first. Because people with type 2 diabetes have elevated cardiovascular risk, the ADA recommends that those who are sedentary and over 40 discuss cardiac evaluation with their doctor before starting a vigorous exercise program.

    Exercise and Weight Management in Diabetes

    For many people with type 2 diabetes, weight management is a key goal — and exercise plays an important supporting role. While diet tends to have a stronger direct effect on weight loss, exercise is crucial for maintaining weight loss over time and preserving muscle mass during calorie restriction.

    A combination of aerobic exercise and resistance training has been shown in multiple NIH-funded studies to produce more durable improvements in body composition and metabolic health than either approach alone.

    It's worth noting, however, that exercise alone rarely produces dramatic weight loss — especially in the short term. The real metabolic magic happens when physical activity complements a thoughtful eating plan. If you're struggling with weight and diabetes, speaking with a registered dietitian familiar with diabetes can make a significant difference. You may also find our article on Weight Loss and Metabolism: What You Can Actually Change helpful for understanding the broader picture.

    When to Call Your Doctor or Seek Emergency Care

    Exercise is safe for most people with diabetes, but certain situations require immediate medical attention:

    Red flags requiring emergency care:

    • Blood sugar below 54 mg/dL that doesn't respond to glucose treatment
    • Loss of consciousness or severe confusion during or after exercise
    • Chest pain, pressure, or shortness of breath during activity
    • Severe dizziness or fainting
    • Symptoms of diabetic ketoacidosis (DKA): nausea, vomiting, fruity-smelling breath, rapid breathing

    Call your doctor soon if you notice:

    • Consistent blood sugar spikes after exercise (rather than drops)
    • Foot sores, blisters, or injuries that are slow to heal
    • Frequent hypoglycemia episodes around workout times
    • Joint pain or discomfort that limits your ability to exercise
    • Your A1C isn't improving despite consistent activity

    Frequently Asked Questions

    How quickly does exercise lower blood sugar?
    For most people with type 2 diabetes, blood sugar begins to drop within 10–20 minutes of starting moderate aerobic exercise. The full effect can last 24 to 48 hours post-workout due to improved insulin sensitivity. Individual responses vary, so monitoring your glucose before and after is the best way to understand your personal pattern.

    Is it safe to exercise if my blood sugar is high?
    It depends. Moderate exercise is generally safe if your blood sugar is between 150–250 mg/dL and you feel well. However, if your glucose is above 250 mg/dL and you have ketones in your urine, exercise can actually worsen the situation. Always follow your healthcare provider's specific guidelines for your situation.

    Can exercise replace diabetes medication?
    For some people in early-stage type 2 diabetes, significant lifestyle changes — including regular exercise and dietary modification — can reduce the need for medication. However, this is a decision that must be made with your physician. Never stop or reduce diabetes medication without medical supervision.

    What if I have neuropathy or joint pain that limits exercise?
    Low-impact options like swimming, water aerobics, chair-based exercises, and upper-body resistance training can be effective even with significant physical limitations. A physical therapist familiar with diabetes can design a safe program tailored to your abilities.

    How do I prevent low blood sugar during exercise?
    Checking your glucose before exercise, carrying fast-acting carbohydrates, avoiding exercise at peak insulin action times (if you use insulin), and working with your care team to adjust medication timing are all effective strategies. Clinical evidence suggests that exercising after meals — when blood sugar is naturally elevated — may also reduce hypoglycemia risk for many individuals.

    Conclusion

    Exercise isn't a luxury add-on for people managing diabetes — it's one of the most clinically validated tools available for improving blood sugar control, reducing A1C, and protecting long-term health. Whether you start with a 15-minute walk after dinner or a structured gym program, the key is consistency over intensity.

    Your body responds to movement in powerful ways, regardless of your age or fitness level. The research is clear: regular physical activity improves insulin sensitivity, supports heart health, aids weight management, and enhances quality of life — all areas where diabetes poses significant risk.

    Work with your healthcare team to build a plan that fits your life, monitor your blood sugar around activity, and give yourself credit for every step forward. Progress, not perfection, is what leads to lasting change.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Weight Loss After 40: Why It’s Harder and What Works

    Weight Loss After 40: Why It’s Harder and What Works

    Weight Loss After 40: Why It Gets Harder and What Actually Works

    Aging changes your body’s fat-burning machinery — but targeted strategies can still deliver real, lasting results.

    Margaret, 52, had maintained the same weight for most of her adult life. Then, seemingly overnight, she gained 18 pounds without changing her diet or exercise habits. "I’m doing everything I used to do," she told her doctor. "Nothing is working anymore." Her story is remarkably common. According to the National Institute on Aging, most adults gain an average of one to two pounds per year between their 40s and 60s — even without overeating. That slow, steady accumulation isn’t a personal failure. It’s biology.

    But biology is not destiny. Understanding exactly why weight loss after 40 becomes more challenging — and which evidence-based strategies actually address those changes — puts you back in control. In this guide, you’ll learn what happens to your body as you age, how those changes affect your metabolism and fat storage, and what clinical evidence says works best for adults managing weight in midlife and beyond.


    What Changes About Your Body After 40?

    Weight gain in midlife isn’t just about eating more or moving less. Several biological shifts converge in your 40s and 50s to make fat storage easier and fat loss harder. Understanding these mechanisms is the first step toward working with your body instead of against it.

    Muscle mass declines — a process called sarcopenia. After age 30, adults lose roughly 3 to 5 percent of their muscle mass per decade, according to the NIH. By your 40s and 50s, this loss is measurable and meaningful. Muscle is metabolically active tissue, meaning it burns calories even at rest. Less muscle means a lower resting metabolic rate (RMR) — the number of calories your body needs just to keep your heart beating, lungs breathing, and organs functioning.

    Hormonal shifts play a major role. In women, the perimenopause and menopause transition — which typically begins in the mid-to-late 40s — leads to declining estrogen levels. Research published in the journal Obesity and cited by the Mayo Clinic confirms that lower estrogen promotes fat redistribution from the hips and thighs to the abdomen, where it’s more metabolically dangerous. In men, testosterone levels decline gradually after age 35 to 40, contributing to reduced muscle mass and increased visceral fat.

    Insulin sensitivity decreases. Aging is associated with reduced cellular response to insulin — the hormone that regulates blood sugar. When cells become less sensitive to insulin, the body produces more of it. Higher insulin levels favor fat storage, particularly around the midsection. The American Diabetes Association notes that insulin resistance increases significantly with age, even in people who are not diabetic.

    Sleep quality worsens. Adults over 40 frequently experience disrupted sleep architecture. Poor sleep raises levels of ghrelin (a hunger-stimulating hormone) and lowers leptin (a satiety hormone), creating a hormonal environment that drives overeating. A landmark NIH-funded study found that sleeping fewer than six hours per night was associated with significantly higher rates of obesity in adults across all age groups.


    Signs That Age-Related Weight Gain Is Happening

    Recognizing the pattern early gives you more options. Here’s what age-related weight gain typically looks like:

    Early signs:

    • Clothes fitting tighter around the waist despite no major dietary changes
    • Fatigue at activity levels that previously felt easy
    • Slower recovery after exercise
    • Increased cravings, especially for carbohydrates and sweets
    • Noticing weight creep of 1 to 3 pounds per year without explanation

    Signs that warrant medical evaluation:

    • Rapid, unexplained weight gain of 10 or more pounds in a short period
    • Swelling in the legs or abdomen alongside weight gain
    • Extreme fatigue, hair loss, cold intolerance, or constipation (possible thyroid issues)
    • Increased thirst, frequent urination, or blurred vision (possible blood sugar issues)
    • Shortness of breath with minimal exertion

    A 2023 analysis published through the Cleveland Clinic found that up to 30 percent of adults who attributed weight gain solely to aging had an undiagnosed contributing condition — most commonly hypothyroidism or prediabetes — that was identified only after medical evaluation.


    Causes and Risk Factors for Midlife Weight Gain

    While hormonal and metabolic shifts are universal with aging, several factors accelerate weight gain and make loss more difficult:

    Sedentary behavior: The CDC reports that adults over 50 are more likely than younger adults to meet criteria for physical inactivity. As careers peak and family responsibilities shift, structured exercise often decreases — just as the body needs it most.

    Stress and cortisol: Midlife frequently brings heightened chronic stress — caregiving for aging parents, career pressure, financial concerns. Chronic stress elevates cortisol, which research suggests promotes abdominal fat storage and increases appetite for high-calorie foods. (For a deeper dive into how cortisol affects your weight, see our article Weight Loss and Stress: How Cortisol Blocks Your Progress.)

    Medications: Many medications commonly prescribed to adults over 40 — including certain antidepressants, beta-blockers, corticosteroids, and antihistamines — list weight gain as a side effect. Never stop a prescribed medication without consulting your physician, but do discuss any concerns about medication-related weight changes.

    Dietary patterns: Research from Harvard Health suggests that as adults age, their dietary habits often shift toward more processed foods, larger portions, and fewer vegetables — not because of carelessness, but because of time constraints, taste changes, and reduced meal planning.

    Genetics: Genetic predisposition plays a role in where the body stores fat and how readily it releases it. This varies from person to person, and some individuals are more metabolically vulnerable to midlife weight gain than others.


    Diagnosis: Getting the Right Medical Picture

    Before diving into any weight loss plan, getting a thorough medical evaluation is strongly recommended — especially for adults over 40. This is not optional box-checking. It’s essential for identifying reversible causes and ensuring your approach is safe and personalized.

    Tests your doctor may order include:

    • Thyroid function panel (TSH, T3, T4): Hypothyroidism — an underactive thyroid — is a common and treatable cause of unexplained weight gain, especially in women over 40.
    • Fasting glucose and HbA1c: These tests screen for prediabetes and type 2 diabetes, both of which affect metabolism and fat storage.
    • Lipid panel: Cholesterol levels often shift in midlife and carry weight management implications.
    • Hormone levels: Estrogen, testosterone, DHEA, and cortisol panels can reveal deficiencies or imbalances contributing to weight gain.
    • Body composition assessment: Standard BMI (Body Mass Index) does not distinguish between fat and muscle. A DEXA scan or bioelectrical impedance analysis gives a clearer picture of how much of your body weight is fat versus lean muscle.

    The U.S. Preventive Services Task Force recommends that all adults with a BMI of 30 or higher be referred for intensive behavioral counseling interventions, and that those with a BMI of 25 or higher with at least one cardiovascular risk factor be screened and offered support.


    Treatment Options That Actually Work After 40

    Clinical evidence is clear: no single approach works for everyone. The most effective weight management plans in midlife combine medical oversight with targeted lifestyle strategies. Here’s what the evidence supports:

    Resistance Training — Non-Negotiable After 40

    If you’re only doing cardio, you’re missing the most important tool for midlife weight loss. Resistance training — using weights, resistance bands, or bodyweight exercises — rebuilds and preserves muscle mass, which directly raises your resting metabolic rate.

    A landmark meta-analysis published in the British Journal of Sports Medicine found that resistance training two to three times per week significantly improved body composition in adults over 50, independent of caloric restriction. Research suggests aiming for at least two sessions per week, targeting all major muscle groups. (For a complete breakdown, visit our article Weight Loss and Metabolism: What You Can Actually Change.)

    Protein Intake — Strategic, Not Extreme

    Older adults have higher protein requirements than younger adults because protein synthesis efficiency declines with age. The NIH recommends that adults over 50 aim for 1.0 to 1.2 grams of protein per kilogram of body weight daily — higher than the standard recommendation of 0.8 grams — to preserve muscle during weight loss.

    Clinical evidence indicates that distributing protein across meals (rather than concentrating it at dinner) optimizes muscle protein synthesis. Lean poultry, fish, eggs, Greek yogurt, legumes, and low-fat dairy are excellent sources. Protein also increases satiety, helping you consume fewer calories without feeling deprived.

    Caloric Adjustment — Modest Deficit, Not Crash Dieting

    Because resting metabolic rate decreases with age, the caloric intake that maintained your weight at 30 may cause gradual weight gain at 50. Most physicians recommend a modest caloric deficit of 300 to 500 calories per day — enough to promote fat loss while preserving muscle and energy levels.

    Crash dieting — severe caloric restriction below 1,200 calories for women or 1,500 for men — is particularly harmful in midlife. The Mayo Clinic notes that very low-calorie diets accelerate muscle loss in older adults, making long-term weight regain more likely.

    Mediterranean-Style Eating Pattern

    Among dietary patterns, the Mediterranean diet has the strongest evidence base for midlife adults. A 2022 study published in the New England Journal of Medicine and referenced by NIH found that a Mediterranean diet rich in olive oil, vegetables, whole grains, legumes, and lean fish reduced visceral fat and cardiovascular risk markers significantly in adults over 45.

    This eating pattern naturally lowers glycemic load (the blood sugar impact of meals), addresses insulin resistance, and supports gut microbiome health — all of which become increasingly relevant after 40.

    Prescription Medications — A Legitimate Option

    For adults with a BMI of 30 or higher, or 27 or higher with a related health condition, FDA-approved weight loss medications may be appropriate. GLP-1 receptor agonists — a class of medications that includes semaglutide — have demonstrated significant and sustained weight loss in clinical trials. These are prescription medications and must be managed by a qualified physician.

    Clinical evidence indicates that medications work best as part of a comprehensive plan that includes dietary changes and physical activity. Ask your doctor whether medication is appropriate for your specific health profile.


    Living With Midlife Weight Challenges: Day-to-Day Strategies

    Sustainable weight management after 40 requires habits that fit into real life — not a 12-week program you abandon in January.

    Prioritize sleep aggressively. Research suggests that improving sleep quality from six to eight hours per night can reduce daily caloric intake by 270 to 500 calories — without any conscious dietary effort. Establish a consistent sleep schedule, limit screens before bed, and keep your bedroom cool and dark.

    Manage stress with intentionality. Mindfulness-based stress reduction (MBSR) has been shown in NIH-funded studies to lower cortisol levels and reduce emotional eating in adults over 40. Even 10 minutes of daily meditation, journaling, or breathing exercises can create measurable hormonal changes over time.

    Increase non-exercise activity thermogenesis (NEAT). NEAT refers to all the calories burned through everyday movement — walking, standing, fidgeting, housework. Research from the Mayo Clinic suggests NEAT can account for up to 350 extra calories burned daily. Take stairs, park farther away, stand at your desk, and walk during phone calls.

    Stay hydrated. Dehydration is often misread as hunger in older adults. Drinking adequate water (typically eight to ten cups daily, though this varies from person to person) before meals has been shown to reduce caloric intake in multiple controlled studies.

    Track without obsessing. Food journaling — even casually — helps identify patterns of overeating that happen unconsciously. Apps like those aligned with CDC-recommended dietary guidelines can provide useful structure without becoming a source of anxiety.


    When to Call Your Doctor: Red Flags and What to Discuss

    Most midlife weight gain is gradual and responds to lifestyle intervention. But certain situations require prompt medical attention:

    Seek immediate care if you experience:

    • Unexplained weight gain of 10 or more pounds in two weeks or less
    • Severe leg swelling alongside rapid weight gain (may indicate heart or kidney disease)
    • Chest pain, shortness of breath, or heart palpitations during any activity
    • Signs of thyroid storm or adrenal crisis: extreme anxiety, rapid heart rate, fever, confusion

    At your next appointment, bring up:

    • Any medications you suspect may be contributing to weight gain
    • Changes in energy, mood, sleep, or appetite
    • Your interest in body composition testing beyond standard BMI
    • Whether a referral to a registered dietitian or obesity medicine specialist is appropriate
    • Whether any FDA-approved medications for weight management are right for you

    Frequently Asked Questions About Weight Loss After 40

    Q: Is it really harder to lose weight after 40, or is that just an excuse?
    A: It’s genuinely harder — this is physiology, not a mindset problem. Hormonal shifts, declining muscle mass, and reduced metabolic rate are measurable biological changes documented by the NIH and major medical centers. That said, these changes are manageable with the right strategies. It takes more intentional effort, not different character.

    Q: Should I do more cardio to lose weight after 40?
    A: Cardio supports heart health and burns calories, but resistance training is more important for midlife weight loss. Building and maintaining muscle mass raises your resting metabolic rate, which has a greater long-term impact. Clinical evidence suggests combining both for optimal results — three days of resistance training plus two to three days of moderate cardio per week is a well-studied approach.

    Q: Can menopause cause permanent weight gain?
    A: Menopause itself doesn’t cause weight gain directly, but the hormonal changes associated with it — particularly declining estrogen — promote fat redistribution to the abdomen. Research published through Johns Hopkins and the Mayo Clinic indicates that women who maintain consistent resistance training and dietary habits through the menopause transition gain significantly less abdominal fat than those who don’t.

    Q: Do I need to eat less as I age, or just eat differently?
    A: Both, to some degree. Because your resting metabolic rate decreases, your total caloric needs decline modestly with age. However, the quality and composition of what you eat matters at least as much as quantity. Prioritizing protein, fiber, and healthy fats while reducing ultra-processed foods addresses both caloric and hormonal factors simultaneously.

    Q: Are weight loss medications safe for adults over 50?
    A: FDA-approved weight loss medications have been studied in adults over 50 and can be safe and effective for appropriate candidates. Individual suitability depends on your health history, current medications, kidney and liver function, and other factors. This is a conversation to have with your physician — never start or stop any medication without professional guidance.


    The Bottom Line

    Weight loss after 40 is genuinely more challenging — but it is absolutely achievable. The biology is working against some of your old habits, which means those old habits need to evolve, not just intensify. Rebuilding muscle through resistance training, eating adequate protein, following an anti-inflammatory dietary pattern, optimizing sleep, and managing stress are not optional extras — they’re the foundation of effective midlife weight management.

    You don’t need to be perfect. You need to be consistent, informed, and medically supported. Start with a conversation with your doctor, get the right baseline labs, and build a plan that reflects your actual biology — not the body you had at 30. Small, evidence-based changes made sustainably over time produce results that last.

    For more strategies on how metabolic function affects your weight loss journey, explore our guide on Weight Loss and Metabolism: What You Can Actually Change. And if stress is a persistent barrier, our deep dive into Weight Loss and Stress: How Cortisol Blocks Your Progress is worth reading next.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Online Therapy for Relationship Issues: Does It Work?

    Online Therapy for Relationship Issues: Does It Work?

    When communication breaks down at home, your mental and physical health often follow — and modern teletherapy may be the bridge back to connection.

    Marcus and Diana, both in their early 40s, had not had a real conversation in months. Between demanding jobs, two kids, and the quiet distance that years of unresolved conflict can build, they felt more like roommates than partners. They wanted couples counseling but could not coordinate schedules — until their family doctor suggested online therapy as a starting point.

    Their story is far from unique. According to the American Association for Marriage and Family Therapy (AAMFT), roughly 50% of all couples experience significant relationship distress at some point, yet fewer than one in four ever seek professional help. Barriers like cost, stigma, geographic access, and logistical challenges keep millions from getting support that could meaningfully improve their lives.

    Online therapy for relationship issues — delivered via video sessions, messaging platforms, or app-based tools — has emerged as one of the most practical solutions to that access gap. In this guide, you will learn what the research actually says about its effectiveness, how it compares to in-person counseling, who benefits most, what to expect, and how to choose a qualified provider.

    What Is Online Therapy for Relationship Issues?

    Online therapy for relationship issues — also called teletherapy, e-therapy, or virtual couples counseling — refers to professional psychotherapy delivered remotely through HIPAA-compliant video conferencing, phone sessions, or asynchronous text-based messaging with a licensed mental health professional.

    It is not chatbot advice or wellness apps. It involves real, licensed clinicians — typically licensed marriage and family therapists (LMFTs), licensed clinical social workers (LCSWs), or licensed professional counselors (LPCs) — using evidence-based modalities such as Emotionally Focused Therapy (EFT), the Gottman Method, or Cognitive Behavioral Couples Therapy (CBCT).

    According to the NIH’s National Center for Complementary and Integrative Health, telehealth use in the United States surged dramatically in recent years and has stabilized at a level far above pre-pandemic baselines. Mental health services, including couples and individual relationship counseling, represent one of the most common telehealth use cases among US adults aged 18 to 64.

    Relationship issues treated through online therapy commonly include communication breakdowns, infidelity recovery, sexual dissatisfaction, parenting conflicts, financial disagreements, intimacy loss, and premarital counseling. Individual therapy for issues affecting relationships — such as attachment disorders, anxiety in relationships, or recovery from past trauma — is also widely available through online platforms.

    Signs Your Relationship Could Benefit From Therapy

    Many couples wait an average of six years after problems begin before seeking therapy, according to research cited by the Gottman Institute. That delay often allows patterns to become deeply entrenched. Recognizing early warning signs matters.

    Early warning signs that therapy could help:

    • Conversations consistently end in criticism, defensiveness, or stonewalling
    • You feel emotionally disconnected or misunderstood most of the time
    • Physical or emotional intimacy has significantly decreased
    • You replay the same arguments without resolution
    • You avoid talking about finances, parenting, or future plans
    • One or both partners feel contempt toward the other
    • Trust has been broken by dishonesty, infidelity, or hidden behavior

    More advanced signs requiring prompt attention:

    • Thoughts of separation or divorce are frequent
    • One partner is using substances to cope with relationship stress
    • Sleep, appetite, or work performance are being affected by relationship conflict
    • Children are visibly affected by household tension
    • Any form of emotional or verbal abuse is present

    A 2022 meta-analysis published in the Journal of Marital and Family Therapy found that couples who began therapy within the first two years of noticing significant distress had substantially better outcomes than those who waited longer — reinforcing the value of acting early.

    ⚠️ Important: Online therapy is not appropriate when there is any presence of domestic violence, physical abuse, or active safety threats. If you or someone you know is in danger, please contact the National Domestic Violence Hotline at 1-800-799-7233 immediately.

    Does Online Couples Therapy Actually Work? What the Research Says

    This is the question most couples ask first — and the evidence is genuinely reassuring.

    A landmark randomized controlled trial published in the Journal of Consulting and Clinical Psychology found that internet-delivered relationship education and counseling produced clinically significant improvements in relationship satisfaction, communication quality, and individual mental health outcomes compared to waitlist controls.

    The American Psychological Association (APA) has affirmed that telehealth formats produce outcomes comparable to in-person care for a broad range of mental health conditions, including relationship-focused therapy. Importantly, therapeutic alliance — the quality of the bond between therapist and client, which is one of the strongest predictors of therapy success — appears to be preserved in video-based sessions.

    Research from the Cleveland Clinic and Mayo Clinic also supports the use of EFT and Gottman Method approaches delivered online, noting that structured, evidence-based modalities translate well to the virtual format when delivered by trained clinicians.

    Individual variation matters here. Some couples adapt immediately to video sessions; others find the absence of shared physical space with the therapist slightly less comfortable. Clinical evidence suggests that couples who engage consistently — attending sessions regularly and completing between-session exercises — see the strongest outcomes regardless of delivery format.

    Online vs. In-Person Couples Therapy: Key Differences

    Understanding how these formats differ helps you make an informed choice rather than assuming one is universally superior.

    Accessibility: Online therapy removes geographic barriers entirely. Rural couples, partners who travel frequently for work, and individuals with mobility limitations all benefit. The CDC has noted that mental health care access disparities are particularly pronounced in rural US counties — online therapy directly addresses this gap.

    Scheduling flexibility: Many online platforms offer evening and weekend availability, which is critical for working couples who cannot leave their offices mid-day for a 50-minute appointment.

    Cost: Online therapy is often more affordable than in-person care, though pricing varies widely by platform and provider. Some platforms charge $200–$400 per month for weekly sessions, compared to $150–$300 per session out-of-pocket in many US cities. Insurance coverage for telehealth mental health services has expanded significantly under post-pandemic parity laws.

    Comfort and openness: Some couples report that being in their own home during sessions actually lowers their defenses and makes it easier to be honest. Others find home distractions challenging. This varies significantly from person to person.

    Limitations to acknowledge: Online therapy may be less effective when one partner has significant hearing or vision impairments, unreliable internet access, or when the couple cannot find private space at home. Therapists also cannot observe full body language as easily via video, which can limit some nonverbal clinical assessment.

    How to Choose a Qualified Online Couples Therapist

    Not all platforms are equal, and the credential of your therapist matters enormously for YMYL-level health outcomes.

    Look for these qualifications:

    • Licensed Marriage and Family Therapist (LMFT) — specializes specifically in relational therapy
    • Licensed Clinical Social Worker (LCSW) or Licensed Professional Counselor (LPC) with documented couples therapy experience
    • Training in evidence-based modalities: EFT, Gottman Method Level 1 or 2, CBCT, or Integrative Behavioral Couples Therapy (IBCT)
    • State licensure matching your state of residence (required for legal practice)
    • HIPAA-compliant platform with secure, encrypted video technology

    Questions to ask before your first session:

    • What couples therapy modality do you use, and why?
    • How many couples have you treated, and what is your approach to infidelity or trauma?
    • Do you offer individual sessions alongside couples work if needed?
    • What does your cancellation policy look like?

    Reputable platforms include those that verify therapist licenses, offer therapist matching based on your concerns, and provide transparent pricing. Always verify any therapist’s license independently through your state’s licensing board website.

    If you’re also navigating personal mental health challenges alongside relationship issues, exploring resources like online therapy for grief and loss or online therapy for OCD may provide useful context on what to expect from virtual mental health care more broadly.

    What to Expect: Your First Online Couples Therapy Sessions

    Understanding the process reduces anxiety and helps both partners commit.

    Intake and assessment (Sessions 1–2): Most couples therapists begin with a structured assessment of relationship history, presenting concerns, individual mental health backgrounds, and each partner’s goals. Many therapists will schedule one individual session with each partner early in the process to understand private concerns that may not surface together.

    Pattern identification (Sessions 3–6): The therapist will begin identifying recurring interaction cycles — the demand-withdraw pattern, criticism-defensiveness loops, or emotional disconnection — that are maintaining distress. EFT, for example, focuses on underlying emotional needs driving surface-level conflict.

    Skill-building and restructuring (Sessions 7+): This phase focuses on practical communication skills, vulnerability, and rebuilding emotional safety. Between-session exercises — conversations, journaling prompts, or structured check-ins — are commonly assigned and strongly correlated with better outcomes.

    Most couples in research settings show measurable improvement within 12–20 sessions, though this varies considerably. Some couples benefit from brief interventions of 6–8 sessions; others engage in longer-term work, particularly when infidelity, trauma, or individual mental health conditions are involved.

    Living With Relationship Challenges: Day-to-Day Strategies

    Therapy is most effective when supported by daily habits that reinforce what you are learning in sessions.

    Practice the 5:1 ratio: Gottman Institute research consistently shows that stable relationships maintain at least five positive interactions for every one negative one. Intentionally increasing small acts of appreciation, humor, and affection measurably shifts relational dynamics.

    Schedule uninterrupted connection time: Even 20 minutes per day of phone-free, non-logistical conversation — no discussions of bills, schedules, or children’s activities — builds the emotional bank account that sustains relationships under stress.

    Manage your individual mental health proactively: Anxiety, depression, ADHD, and unprocessed trauma all profoundly affect relationship functioning. Individual therapy alongside couples work is often recommended. Research from Johns Hopkins suggests that treating individual anxiety disorders in one partner significantly improves relationship satisfaction for both.

    Learn to recognize physiological flooding: When heart rate exceeds roughly 100 beats per minute during conflict, rational processing deteriorates. Taking structured 20-minute breaks — not silent withdrawals, but agreed pauses — before returning to a conversation is an evidence-based strategy endorsed by most major couples therapy modalities.

    Understanding how individual mental health interacts with relationship dynamics is important. For example, if social avoidance or anxiety is affecting your ability to connect, learning more through resources like social anxiety disorder symptoms, causes, and treatment may provide valuable context for your therapy journey.

    When to Contact a Doctor or Mental Health Professional Immediately

    While online therapy is effective for most relationship challenges, certain situations require immediate professional escalation.

    Seek emergency care or crisis support if:

    • Either partner is expressing suicidal thoughts or self-harm urges related to relationship distress
    • Physical violence or threats of violence are occurring — contact the National Domestic Violence Hotline: 1-800-799-7233
    • A partner’s substance use is escalating into dependency or creating safety risks
    • A child in the home may be at risk due to parental conflict or behavior

    Contact your therapist or physician soon if:

    • Relationship stress is significantly impairing sleep, appetite, or daily function for more than two weeks
    • You notice signs of depression or anxiety that are worsening alongside relationship difficulties
    • One partner refuses to participate in therapy and the situation is deteriorating

    Your primary care physician is also a valuable first contact. Research from the CDC confirms that chronic relationship stress is associated with elevated cortisol, higher blood pressure, and compromised immune function — making relationship health a genuine medical concern, not just an emotional one.

    Frequently Asked Questions

    Can online therapy work if only one partner is willing to participate?
    Yes. Individual therapy focused on relationship dynamics — sometimes called relationship therapy for one — can be highly effective. A skilled therapist can help one partner change their communication patterns, manage their own emotional responses, and sometimes shift the dynamic even without the other partner in the room. Research suggests this approach produces meaningful improvements in relationship satisfaction for the participating partner.

    Does insurance cover online couples therapy?
    Coverage varies by plan. Under federal mental health parity laws, insurers who cover mental health benefits must cover them comparably to medical benefits. Many plans now cover telehealth therapy, including couples counseling when there is a diagnosable condition present. Contact your insurer directly and ask specifically about coverage for LMFT services delivered via telehealth. Medicare and many Medicaid plans also offer expanded telehealth mental health coverage as of recent policy updates.

    How is online couples therapy different from a relationship app or self-help program?
    Apps and self-help programs can be useful complements, but they are not therapy. Licensed therapists provide personalized clinical assessment, adapt interventions to your specific dynamic, can diagnose co-occurring mental health conditions, and are legally and ethically accountable for your care. Research consistently shows that therapist-guided treatment produces significantly better outcomes than self-directed digital tools alone.

    What if we live in different locations — can we still do couples therapy online?
    This is one of the most significant advantages of online therapy. Partners in long-distance relationships, couples where one partner travels frequently, or those temporarily living apart can all participate in the same session from different locations. The therapist will need to be licensed in the state where each partner is physically located at the time of the session, so confirm this with your provider.

    How long does online couples therapy typically take?
    This varies considerably based on the nature and severity of the issues involved. Some couples addressing specific communication challenges see meaningful improvement in 8–12 sessions. Those navigating infidelity, significant trauma, or long-standing patterns may benefit from 6 months to a year or more of consistent work. Most therapists recommend evaluating progress together at regular intervals — typically every 6–8 sessions — rather than committing indefinitely without reassessment.

    Conclusion

    Relationship health is not separate from physical and mental health — it is woven into both. Chronic relationship distress raises stress hormones, disrupts sleep, undermines immune function, and significantly increases the risk of depression and anxiety. Taking your relationship health seriously is not a luxury; it is part of comprehensive self-care.

    Online therapy for relationship issues has a growing, credible evidence base. It is accessible, flexible, and — when delivered by qualified, licensed professionals using evidence-based methods — genuinely effective for a wide range of couples and individuals navigating relational challenges.

    The most important step is the first one: reaching out. Whether you start with your primary care doctor, a telehealth platform, or a recommendation from a trusted source, getting support sooner rather than later gives you the best chance of real, lasting change.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Social Anxiety Disorder: Symptoms, Causes & Treatment

    Social Anxiety Disorder: Symptoms, Causes & Treatment

    Social Anxiety Disorder: Symptoms, Causes & Treatment

    Social anxiety disorder is one of the most common — and most underdiagnosed — mental health conditions in the United States, affecting millions of adults who silently struggle through everyday interactions.

    Introduction

    Marcus, 41, had been turning down promotions for years. Not because he lacked the skills — his managers said he was brilliant — but because every time he imagined speaking in a meeting or leading a team, his chest tightened, his palms sweated, and a voice in his head told him he would embarrass himself beyond recovery. He told himself he was just "introverted." It took a conversation with his primary care doctor to learn he had social anxiety disorder.

    According to the National Institute of Mental Health (NIMH), social anxiety disorder affects approximately 15 million American adults, making it the second most common anxiety disorder in the United States. Yet fewer than 5% of people with social anxiety seek treatment in the year following onset, and the average person waits more than a decade before getting help.

    If you recognize yourself in Marcus’s story, this guide is for you. You’ll learn exactly what social anxiety disorder is, how it differs from ordinary shyness, what the latest clinical evidence says about causes and treatment, and — most importantly — when and how to take the next step toward real relief.

    What Is Social Anxiety Disorder?

    Social anxiety disorder (SAD) — also called social phobia — is a chronic mental health condition characterized by intense, persistent fear of social situations in which you might be observed, judged, or embarrassed by others. This goes far beyond everyday nervousness before a job interview or a first date.

    For people with social anxiety disorder, the fear is disproportionate to the actual situation and is significant enough to interfere with daily functioning — at work, in relationships, and in routine activities like eating at a restaurant, signing a check in front of a cashier, or making a phone call.

    The American Psychiatric Association’s Diagnostic and Statistical Manual of Mental Disorders (DSM-5) classifies SAD as an anxiety disorder. The fear must be present for six months or longer and must cause meaningful distress or impairment to qualify as a diagnosable condition.

    According to the Anxiety and Depression Association of America (ADAA), social anxiety disorder affects 7.1% of the U.S. adult population in any given year, with onset most commonly occurring around age 13. It affects people of all genders, races, and income levels.

    The reason this condition matters so profoundly: left untreated, social anxiety disorder dramatically increases the risk of depression, substance use disorders, and career and relationship impairment — making early recognition and treatment critically important.

    Signs and Symptoms of Social Anxiety Disorder

    One of the reasons social anxiety disorder goes undiagnosed for so long is that its symptoms can look a great deal like shyness or introversion. But clinical social anxiety is qualitatively different — it involves anticipatory dread, physical symptoms, and behavioral avoidance that actively limits your life.

    Emotional and cognitive symptoms (early to moderate):

    • Intense fear of being judged, humiliated, or rejected in social situations
    • Excessive worry for days or weeks before an upcoming social event
    • Persistent belief that you will say something embarrassing or act awkwardly
    • Replaying social interactions afterward and analyzing everything that went "wrong"
    • Fear of showing visible anxiety symptoms (blushing, trembling, sweating) in public

    Physical symptoms:

    • Racing heartbeat or palpitations before or during social situations
    • Sweating, trembling, or shaking
    • Blushing or flushing of the skin
    • Shortness of breath or a feeling of tightness in the chest
    • Nausea, stomach upset, or dizziness
    • Dry mouth or difficulty speaking clearly

    Behavioral symptoms (often more severe over time):

    • Avoiding social situations entirely or enduring them with extreme distress
    • Relying on alcohol or other substances to get through social events
    • Turning down opportunities for advancement, relationships, or new experiences
    • Limiting life activities to a small, "safe" comfort zone

    A landmark study published in the Archives of General Psychiatry found that individuals with social anxiety disorder are significantly more likely to be unemployed, earn lower incomes, and report lower quality of life than those without the condition — underscoring the real-world impact of this diagnosis beyond social discomfort.

    Important note: Symptoms vary significantly from person to person. Some people fear only one specific situation — such as public speaking — while others experience generalized social anxiety across nearly all interpersonal interactions. This variation affects how the condition is treated.

    Causes and Risk Factors

    Social anxiety disorder does not have a single cause. Current research suggests it develops from a complex interaction of genetic predisposition, brain chemistry, temperament, and life experiences.

    Biological and genetic factors:

    Research from the NIH indicates that social anxiety disorder runs in families, suggesting a heritable component. Studies of twins show that genetics may account for roughly 30–40% of the risk for developing social anxiety. People with social anxiety also show heightened activity in the amygdala — the brain’s fear-processing center — in response to social cues, even neutral ones, compared to individuals without the disorder.

    Temperament and early development:

    Children who exhibit behavioral inhibition — a tendency to withdraw from unfamiliar people, situations, or objects — are at elevated risk of developing social anxiety disorder later in life. Research from Harvard Medical School has identified this temperamental pattern as one of the strongest early predictors of the condition.

    Environmental and experiential factors:

    • A history of bullying, teasing, or public humiliation, particularly in childhood or adolescence
    • Overprotective or highly critical parenting styles
    • Traumatic or embarrassing social experiences
    • Growing up in an environment where social performance was heavily scrutinized

    Comorbid risk factors:

    Social anxiety disorder frequently coexists with other mental health conditions. The NIMH reports that approximately 20% of adults with social anxiety disorder also meet the criteria for major depressive disorder. Comorbidity with generalized anxiety disorder, panic disorder, and alcohol use disorder is also well-documented.

    Social media and digital culture may also be contributing factors in modern adults. Emerging clinical research suggests that excessive comparison behavior on social platforms can amplify existing social anxiety tendencies, though this area is still being actively studied.

    Diagnosis: What to Expect

    There is no blood test or brain scan that diagnoses social anxiety disorder. Diagnosis is made clinically, based on a structured interview with a qualified mental health professional or a physician trained in psychiatric assessment.

    What the diagnostic process typically involves:

    • A detailed interview about your symptoms, their duration, and their impact on daily life
    • Standardized screening tools, such as the Liebowitz Social Anxiety Scale (LSAS) or the Social Phobia Inventory (SPIN)
    • A review of your medical history to rule out physical conditions that mimic anxiety (such as hyperthyroidism or cardiac arrhythmia)
    • Assessment of whether the fear is tied to specific situations or is more generalized

    Your doctor may also ask about substance use, since some people with undiagnosed social anxiety disorder begin using alcohol or medications as a coping mechanism — a pattern that can complicate both diagnosis and treatment.

    When to seek a diagnosis:

    You should consider speaking with your primary care physician or a mental health professional if your fear of social situations has lasted six months or more, causes you significant distress, and is interfering with your work, relationships, or quality of life. Early diagnosis leads to significantly better outcomes.

    Treatment Options for Social Anxiety Disorder

    The good news is clear: social anxiety disorder is highly treatable. According to the Mayo Clinic, the majority of people with social anxiety disorder experience meaningful symptom improvement with appropriate treatment. The most effective approaches combine psychotherapy with medication, though individual responses vary.

    Psychotherapy — First-Line Treatment:

    Cognitive Behavioral Therapy (CBT) is the gold-standard psychotherapeutic treatment for social anxiety disorder, supported by decades of clinical evidence. CBT works by helping you identify and challenge distorted thought patterns — such as catastrophizing social situations — and gradually exposing you to feared situations in a controlled, structured way (a process called exposure therapy).

    A comprehensive meta-analysis published in Psychological Medicine found that CBT produced significant and lasting improvements in social anxiety symptoms, with effects maintained at follow-up assessments up to two years later.

    Exposure-based CBT typically involves:

    • Building a "fear hierarchy" — a ranked list of feared situations from least to most anxiety-provoking
    • Gradually confronting those situations, starting with the least frightening
    • Learning to tolerate discomfort without avoidance, allowing the anxiety response to diminish naturally

    For those who cannot access in-person therapy, research increasingly supports the effectiveness of online CBT platforms. You can learn more about this approach in our guide to Online Therapy for OCD: Does It Really Work?, which covers overlapping therapeutic principles used in anxiety treatment.

    Medication:

    Several classes of medication are clinically approved and evidence-supported for social anxiety disorder:

    • SSRIs (Selective Serotonin Reuptake Inhibitors): Considered first-line pharmacological treatment. The FDA has approved specific SSRIs for social anxiety disorder. These medications typically take two to six weeks to show full effect.
    • SNRIs (Serotonin-Norepinephrine Reuptake Inhibitors): Another approved first-line option with a similar evidence profile.
    • Beta-blockers: Sometimes used situationally for performance-specific anxiety (such as public speaking), though not approved for generalized social anxiety disorder.
    • Benzodiazepines: May be considered in specific cases but carry risks of dependence and are generally not recommended as a long-term solution by most clinical guidelines.

    Always discuss medication options, benefits, and risks in detail with your prescribing physician or psychiatrist. Never adjust or discontinue psychiatric medications without medical guidance.

    Combination therapy: Clinical evidence from Johns Hopkins and other leading institutions consistently shows that combining CBT with medication produces better outcomes for many patients than either approach alone.

    Living With Social Anxiety Disorder: Day-to-Day Management

    Managing social anxiety disorder is not only about what happens in a therapist’s office or with medication. Day-to-day lifestyle practices play a meaningful complementary role — though they should always be used alongside, not instead of, professional treatment.

    Evidence-based lifestyle strategies:

    • Regular aerobic exercise: A meta-analysis in the journal Depression and Anxiety found that regular exercise produces significant reductions in anxiety symptoms. The American Heart Association recommends at least 150 minutes of moderate-intensity aerobic activity per week — a target that also supports mental health.
    • Mindfulness-based practices: Mindfulness-Based Stress Reduction (MBSR) has been studied in clinical trials and shows modest but meaningful benefit for anxiety symptoms. Apps, online courses, and in-person programs are all accessible options.
    • Sleep hygiene: Chronic sleep deprivation amplifies anxiety reactivity. Prioritizing seven to nine hours of quality sleep per night supports emotional regulation and stress resilience. Our article on Weight Loss and Stress: How Cortisol Blocks Your Progress explores how chronic stress and poor sleep interact — relevant reading for anxiety management as well.
    • Limiting alcohol and caffeine: Both substances can worsen anxiety symptoms. Alcohol may feel like short-term relief but disrupts the brain’s anxiety-regulation systems with regular use.
    • Gradual social exposure: Practicing small social challenges consistently — not avoiding them — helps retrain the brain’s threat-detection system over time.

    Building a support network: Connecting with others who understand social anxiety — through support groups, therapy groups, or trusted friends — can reduce isolation and reinforce progress made in therapy.

    When to Call Your Doctor or Seek Emergency Care

    Social anxiety disorder is a serious condition, and there are specific situations that require prompt professional attention.

    Schedule an appointment with your doctor or mental health provider if:

    • Your social anxiety is limiting your ability to work, maintain relationships, or perform daily tasks
    • You have been avoiding treatment for years and recognize that avoidance is shrinking your world
    • You are using alcohol or other substances to cope with anxiety before or during social situations
    • You have noticed worsening symptoms of depression alongside social anxiety
    • Your current treatment plan does not seem to be working after a reasonable trial period

    Seek emergency care or contact a crisis line immediately if:

    • You are experiencing thoughts of self-harm or suicide — social anxiety disorder is associated with elevated suicide risk, particularly when comorbid with depression
    • You are in a state of severe psychological crisis or unable to care for yourself

    If you or someone you know is in crisis, contact the 988 Suicide and Crisis Lifeline by calling or texting 988 (available 24/7 in the United States).

    When speaking with your doctor at your next appointment, be specific: describe which situations trigger your anxiety, how long this has been going on, and how it’s affecting your daily functioning. The more precise you can be, the more effectively your care team can help.

    Frequently Asked Questions

    Is social anxiety disorder the same as being shy?

    No. Shyness is a personality trait that many people experience to varying degrees without significant impairment. Social anxiety disorder is a clinical condition that causes intense, disproportionate fear, significant distress, and meaningful interference with daily functioning. Many shy people never develop social anxiety disorder, and not everyone with social anxiety disorder was notably shy as a child.

    Can social anxiety disorder go away on its own?

    For most adults, social anxiety disorder does not resolve on its own without treatment. In fact, without intervention, the pattern of avoidance tends to reinforce and worsen the anxiety cycle over time. Clinical evidence strongly supports early treatment for better long-term outcomes. However, with appropriate therapy and support, many people experience significant and lasting improvement.

    How long does treatment for social anxiety disorder take?

    This varies from person to person. A standard course of CBT for social anxiety disorder is typically 12 to 20 sessions, though some people benefit from longer-term therapy. Medication may be recommended for months to years depending on severity and response. Many people begin noticing improvement within the first few weeks of treatment.

    Can social anxiety disorder affect my physical health?

    Yes. Chronic anxiety activates the body’s stress response system over long periods, which research suggests can contribute to elevated blood pressure, disrupted sleep, gastrointestinal issues, and immune system dysregulation. Managing your mental health is an important component of overall physical wellness. For context on how chronic stress affects broader health, see our article on PTSD: Symptoms, Causes, and Treatment Options, which covers overlapping stress-response mechanisms.

    Is online therapy effective for social anxiety disorder?

    Research suggests that online CBT is effective for social anxiety disorder, with outcomes comparable to in-person therapy for many patients. The accessibility of online therapy — removing barriers like travel, scheduling, and in-person interaction — may actually make it a practical first step for people whose anxiety makes attending in-person appointments difficult.

    Conclusion

    Social anxiety disorder is not a character flaw, a weakness, or a permanent limitation on the life you deserve to live. It is a well-defined, clinically recognized condition with robust evidence-based treatments that help millions of Americans reclaim their confidence, relationships, and opportunities.

    Whether you’ve been silently avoiding situations that matter to you for years, or you’ve only recently started to wonder if your anxiety goes beyond normal nervousness, the most important step is the same: talk to a healthcare professional. A primary care physician, psychologist, or psychiatrist can assess your symptoms, explain your options, and help you build a treatment plan tailored to your specific needs and goals.

    Recovery is not only possible — for most people with social anxiety disorder, it is the expected outcome with the right support.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Health Insurance for Cancer Care: What’s Covered

    Health Insurance for Cancer Care: What’s Covered

    Health Insurance for Cancer Care: What’s Covered

    Understanding your coverage before a diagnosis can save you time, money, and critical delays in treatment.

    Introduction

    When David, 54, felt a lump under his arm during a routine shower, his first instinct wasn’t to call his doctor — it was to wonder what his health insurance would actually cover. Like millions of Americans, he had a plan but wasn’t sure what it meant in a real health crisis.

    According to the American Cancer Society, approximately 2 million new cancer cases are diagnosed in the United States every year. Cancer is not a condition that affects "someone else." It touches nearly every family in America — and the financial burden that comes with it can be devastating without the right health insurance in place.

    This guide is designed to help you understand how health insurance for cancer screening and treatment works in the US, what services are typically covered, where gaps commonly occur, and how to be your own best advocate when navigating your plan. Whether you’re currently healthy and planning ahead or facing a recent diagnosis, knowing your coverage is one of the most powerful steps you can take.


    What Is Cancer Coverage Under Health Insurance?

    Cancer coverage refers to the benefits your health insurance plan provides for cancer-related screening, diagnosis, treatment, and follow-up care. In the United States, coverage is governed by a combination of federal law, state mandates, and the specific terms of your individual plan.

    The Affordable Care Act (ACA), enacted in 2010, was a turning point in cancer-related coverage. It requires all ACA-compliant plans to cover certain preventive screenings — like mammograms and colorectal cancer screenings — at no cost to the patient when performed in-network.

    However, "covered" doesn’t mean "free." Depending on your plan type — HMO, PPO, EPO, or High-Deductible Health Plan (HDHP) — your out-of-pocket exposure for cancer treatment can range from manageable to financially overwhelming.

    The NIH’s National Cancer Institute estimates that total cancer care expenditures in the US exceed $200 billion annually. Understanding what your plan actually pays — and what you owe — is essential before you ever step foot in an oncologist’s office.


    What Cancer Screenings Are Typically Covered?

    Preventive cancer screenings are among the most important benefits your plan may offer — and under the ACA, many of them must be covered at 100% with no cost-sharing when you use in-network providers.

    Common screenings that ACA-compliant plans must cover:

    • Mammograms — recommended annually or biennially for women aged 40–74, depending on your doctor’s guidance
    • Colorectal cancer screening — colonoscopy, stool-based tests (like FIT or Cologuard), typically starting at age 45
    • Pap smear and HPV testing — for cervical cancer prevention in women aged 21–65
    • Low-dose CT scan for lung cancer — for adults aged 50–80 with a significant smoking history, per USPSTF guidelines
    • Prostate-specific antigen (PSA) testing — coverage varies; discuss appropriateness with your doctor
    • Skin cancer counseling — behavioral counseling for high-risk individuals under 24

    A 2023 report from the CDC confirmed that early-stage cancer detection through routine screening significantly improves survival outcomes across multiple cancer types, including breast, colon, and cervical cancers.

    Important caveat: If your doctor orders additional tests after an abnormal screening — such as a biopsy or diagnostic imaging — those follow-up services may be billed as diagnostic (not preventive), which can trigger your deductible and cost-sharing. Always ask your provider how a test will be coded before it happens.


    What Cancer Treatments Does Insurance Cover?

    Once a cancer diagnosis is confirmed, the range of treatments — and what your insurance will pay for — becomes significantly more complex. Most comprehensive health plans cover standard, evidence-based cancer treatments, but coverage details vary widely.

    Treatments commonly covered by health insurance:

    • Surgery — tumor removal, biopsies, reconstructive procedures (coverage of reconstruction after mastectomy is federally mandated under the Women’s Health and Cancer Rights Act)
    • Chemotherapy — including infused drugs administered in a clinical setting; oral chemotherapy coverage has historically been inconsistent but is improving with oral parity laws in many states
    • Radiation therapy — external beam radiation, brachytherapy, and stereotactic radiosurgery
    • Immunotherapy and targeted therapy — newer biologics and checkpoint inhibitors; coverage depends heavily on FDA approval status and your plan’s formulary
    • Hormone therapy — for hormone-sensitive cancers like breast and prostate cancer
    • Stem cell and bone marrow transplants — often covered for certain blood cancers, though prior authorization is almost always required
    • Palliative and supportive care — pain management, anti-nausea medication, mental health support

    According to a study published by the American Journal of Managed Care, patients with comprehensive insurance coverage were significantly more likely to initiate cancer treatment within 30 days of diagnosis compared to those with limited or no coverage — an interval that is clinically meaningful for many cancer types.

    Research suggests that prior authorization delays — the process by which insurers approve treatments before they’re rendered — affect cancer patients disproportionately. In 2022, the American Medical Association reported that 93% of physicians said prior authorization had delayed necessary care for their patients.


    Understanding Your Out-of-Pocket Costs for Cancer Care

    Even with comprehensive insurance, cancer treatment can generate substantial out-of-pocket expenses. Understanding the financial structure of your plan is critical.

    Key terms to know:

    • Deductible — the amount you pay before insurance kicks in (common deductibles range from $1,500 to $7,000+)
    • Out-of-pocket maximum — the annual cap on your cost-sharing; for 2025, ACA plans cap this at $9,450 for individuals and $18,900 for families
    • Copay vs. coinsurance — copays are flat fees per visit; coinsurance is a percentage of the cost you owe after your deductible is met
    • In-network vs. out-of-network — using out-of-network oncologists or cancer centers can dramatically increase your costs
    • Formulary — your plan’s list of covered drugs; if your oncologist prescribes a drug not on the formulary, you may face a denial or high cost-sharing

    The American Cancer Society’s Cancer Action Network has found that cancer patients in the US spend, on average, $5,000 to over $10,000 in out-of-pocket costs annually — even with insurance. This figure can climb far higher for complex or prolonged treatment courses.

    Clinical evidence indicates that financial toxicity — the economic burden caused by medical costs — is an independent predictor of worse cancer outcomes, affecting treatment adherence, mental health, and even survival rates.


    Medicare, Medicaid, and Cancer Coverage

    For adults aged 65 and older, or those with qualifying disabilities, Medicare is the primary health insurer — and understanding how it covers cancer care is especially important.

    Medicare and cancer:

    • Medicare Part A covers inpatient hospital stays for surgeries and procedures
    • Medicare Part B covers outpatient chemotherapy, infused drugs, radiation, and physician services
    • Medicare Part D covers oral prescription drugs, including some oral chemotherapy agents
    • Medicare Advantage (Part C) — private plans that bundle A, B, and often D; network restrictions apply and vary significantly by plan

    The Centers for Medicare & Medicaid Services (CMS) reports that cancer-related services account for a disproportionately high share of Medicare spending, reflecting both the aging of the US population and the increasing cost of newer cancer therapies.

    For lower-income individuals, Medicaid provides cancer screening and treatment coverage, though the scope of benefits varies by state. In states that expanded Medicaid under the ACA, uninsured cancer patients gained significantly improved access to diagnosis and treatment.


    Living With Cancer: Managing Insurance Throughout Treatment

    A cancer diagnosis doesn’t end your insurance challenges — in many ways, it begins them. Ongoing treatment, follow-up appointments, and survivorship care all require continued engagement with your plan.

    Practical steps to manage your coverage during cancer treatment:

    • Verify your network before every appointment. Cancer care often involves multiple specialists — surgeons, oncologists, radiologists, pathologists — and even one out-of-network provider can trigger unexpected bills.
    • Request a written treatment plan. Share it with your insurance company and ask for written confirmation of what will and won’t be covered before treatment begins.
    • Track all authorizations and appeals deadlines. If your insurer denies a treatment, you have the right to appeal. The ACA mandates both internal and external appeals processes.
    • Ask about patient assistance programs. Many pharmaceutical manufacturers offer financial assistance for expensive cancer drugs. Your oncology social worker can help connect you to these resources.
    • Request an oncology nurse navigator or social worker. Major cancer centers often have staff specifically trained to help patients navigate insurance issues.

    Most physicians recommend reviewing your insurance plan annually during open enrollment — especially if your cancer treatment is ongoing or you anticipate changes in your care team.

    If you are managing another chronic condition alongside cancer, you may find our guide on Health Insurance for Preventive Care: What’s Covered useful for understanding how your overall benefits work together.


    When to Call Your Insurance Company — and When to Escalate

    Knowing when to contact your insurer — and how — is a skill that cancer patients and caregivers must develop quickly.

    Contact your insurance company immediately if:

    • Your oncologist recommends a treatment and you’re unsure if it’s covered
    • You receive a prior authorization denial for a recommended medication or procedure
    • You’re referred to a specialist who may be out of network
    • You receive a bill that seems inconsistent with your Explanation of Benefits (EOB)
    • You’re considering a second opinion at a different cancer center

    Escalate or seek help if:

    • Your appeal is denied and you believe the denial is medically unjustified
    • Your treatment is being delayed due to prior authorization bottlenecks
    • You suspect balance billing from an out-of-network provider (the No Surprises Act of 2022 may protect you)
    • You can no longer afford your premiums due to inability to work during treatment

    State insurance commissioners, patient advocacy organizations like the Patient Advocate Foundation, and legal aid services can all assist when standard appeals fail. You are not without recourse — and advocating for yourself is entirely appropriate and often necessary.

    For related reading on navigating specialty care coverage, see our article on Health Insurance for Maternity & Newborn Care: Full Guide, which walks through similar advocacy strategies in another high-stakes medical context.


    Frequently Asked Questions

    Q: Does health insurance cover genetic testing for cancer risk (like BRCA testing)?
    A: Many plans cover genetic testing when it is ordered by a physician based on a personal or family history that meets established clinical criteria. The ACA requires coverage of BRCA counseling and testing for women at elevated risk. However, coverage varies — always confirm with your insurer and request a predetermination of benefits before testing.

    Q: Can I be denied coverage or charged more because I’ve had cancer?
    A: No. Under the ACA, insurers cannot deny coverage, charge higher premiums, or impose lifetime limits based on a pre-existing condition, including a cancer history. This protection applies to all ACA-compliant plans sold in the individual and employer markets. For more on pre-existing condition protections, you may also want to read about how preventive care coverage works within these plans.

    Q: Does insurance cover clinical trials?
    A: The ACA requires most health insurers to cover routine patient costs associated with approved clinical trials — meaning visits, labs, and standard care are covered even if the experimental treatment itself is not. Medicare also covers qualifying clinical trial costs. Always confirm your specific plan’s policy before enrolling in a trial.

    Q: What happens to my insurance if I lose my job during cancer treatment?
    A: You have several options. COBRA allows you to continue your employer’s group coverage for up to 18 months (you pay the full premium). A job loss also qualifies as a Special Enrollment Period for ACA marketplace plans, where you may be eligible for subsidies based on your income. Medicaid may be an option if your income drops significantly. Acting within 60 days of losing employer coverage is critical.

    Q: Is cancer rehabilitation (like physical therapy after surgery) covered by insurance?
    A: Most comprehensive health plans cover cancer rehabilitation services — including physical therapy, occupational therapy, speech therapy, and lymphedema treatment — when deemed medically necessary. Coverage limits (number of sessions per year) vary by plan. Clinical evidence indicates that rehabilitation significantly improves functional outcomes and quality of life for cancer survivors, and most physicians recommend discussing it with your oncology team as part of your survivorship care plan.


    Conclusion

    Facing cancer — whether as a patient, a caregiver, or someone managing hereditary risk — is one of the most challenging experiences a person can endure. Your health insurance is not a perfect safety net, but it is a powerful tool when you understand how to use it.

    By knowing what screenings are covered, how treatment authorizations work, what your out-of-pocket maximums protect you from, and when to escalate a denial, you position yourself to receive timely, appropriate care without unnecessary financial devastation.

    Research consistently shows that access to comprehensive health coverage improves cancer outcomes — earlier diagnosis, faster treatment initiation, and better adherence to care. Advocacy matters. Review your plan annually, ask questions before procedures, and never hesitate to challenge a denial that stands between you and medically recommended care.

    Your health is worth fighting for — and knowing your coverage is the first step.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.