Tag: prediabetes

  • Insulin Resistance: Signs, Causes & How to Reverse It

    Insulin Resistance: Signs, Causes & How to Reverse It

    Understanding insulin resistance is one of the most important steps you can take to protect your long-term metabolic health — and millions of Americans have it without knowing.

    Marcus, 47, had been feeling exhausted after every meal for years. His doctor told him his blood sugar was "borderline" and that he should "watch what he eats." But nobody explained why his body was struggling — or that he was already in the early stages of a process that affects an estimated 88 million American adults, according to the CDC.

    That process is called insulin resistance, and it sits at the very heart of type 2 diabetes management. If you have been told your blood sugar is slightly elevated, or that you have prediabetes, or if you are simply trying to understand how your body handles glucose, this guide is written for you.

    You will learn exactly what insulin resistance is, how to recognize its warning signs, what drives it, how physicians diagnose and treat it, and — most importantly — what concrete, evidence-based steps you can take starting today to support your metabolic health and reduce your risk of progressing to type 2 diabetes.

    What Is Insulin Resistance?

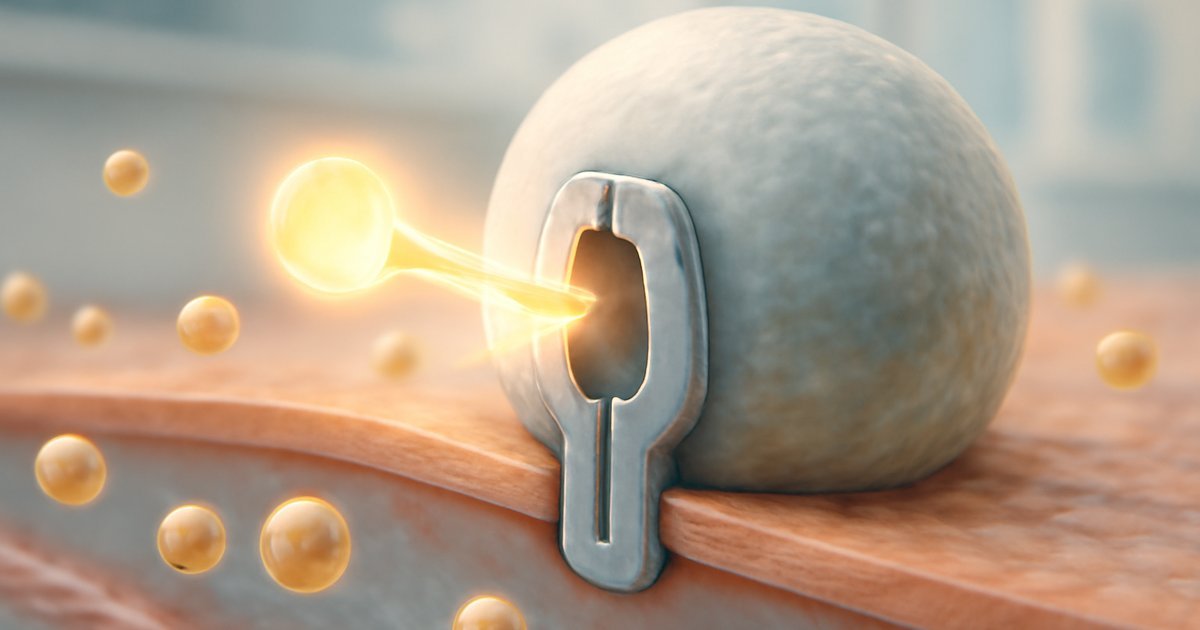
    Insulin is a hormone produced by the pancreas. Its primary job is to act like a key — unlocking your muscle, liver, and fat cells so that glucose (sugar from food) can enter and be used for energy.

    When you develop insulin resistance, those cellular "locks" stop responding normally to the insulin key. Your cells essentially ignore the signal. In response, your pancreas works harder and pumps out more insulin to compensate. For a while, this keeps your blood sugar relatively normal — but it puts enormous strain on your pancreas.

    Over time, the pancreas can no longer keep up with the demand. Blood sugar begins to rise. First you develop prediabetes. Then, if left unaddressed, type 2 diabetes.

    According to the NIH, approximately 1 in 3 American adults has prediabetes — the direct result of insulin resistance — and more than 80% of them are unaware of it. This makes insulin resistance one of the most underdiagnosed metabolic conditions in the United States.

    Signs and Symptoms of Insulin Resistance

    One of the challenges with insulin resistance is that it often develops silently. Many people feel "fine" for years while the condition progresses. However, there are early warning signs worth knowing.

    Early and common signs include:

    • Persistent fatigue, especially after carbohydrate-rich meals
    • Difficulty losing weight, particularly around the abdomen
    • Intense sugar or carbohydrate cravings
    • Increased hunger shortly after eating
    • Brain fog or difficulty concentrating
    • Elevated blood pressure or borderline-high triglycerides
    • Skin changes: dark, velvety patches in skin folds (a condition called acanthosis nigricans), commonly found on the neck, armpits, or groin

    Signs that may indicate progression toward prediabetes or type 2 diabetes:

    • Frequent urination, especially at night
    • Increased thirst
    • Slow-healing cuts or bruises
    • Tingling or numbness in hands or feet
    • Blurry vision
    • Recurring infections (urinary tract, skin, or yeast infections)

    A landmark study published in the journal Diabetes Care found that people with insulin resistance often show abnormal lipid panels — specifically high triglycerides and low HDL (good) cholesterol — years before blood sugar levels become clinically elevated. This is why your doctor may flag a routine cholesterol panel as an early metabolic warning sign.

    Causes and Risk Factors

    Insulin resistance does not have a single cause. Research suggests it develops from a combination of genetic, lifestyle, and environmental factors working together over time.

    Genetic and biological factors:

    • Family history of type 2 diabetes
    • Ethnicity: Black, Hispanic, Native American, and Asian American adults face disproportionately higher risk, according to the CDC
    • Polycystic ovary syndrome (PCOS), which is strongly linked to insulin resistance in women
    • History of gestational diabetes
    • Age: risk increases significantly after 45

    Lifestyle and environmental factors:

    • Physical inactivity — muscle cells that are regularly exercised are significantly more insulin-sensitive
    • Excess body fat, particularly visceral fat (fat stored deep around internal organs in the abdomen)
    • Diets high in ultra-processed foods, refined carbohydrates, and added sugars
    • Chronic sleep deprivation — research from the University of Chicago found that just four nights of poor sleep can reduce insulin sensitivity by as much as 25%
    • Chronic stress and elevated cortisol levels
    • Smoking

    It is worth emphasizing: having risk factors does not mean you are destined to develop diabetes. This condition is highly modifiable, and early action makes a measurable difference. For more on how physical activity directly lowers blood sugar, see our guide on Exercise and Diabetes: How Physical Activity Controls Blood Sugar.

    Diagnosis: What to Expect

    Insulin resistance itself is not directly tested with a single definitive lab value in standard clinical practice. Instead, physicians typically identify it through a combination of measurements and screening tests.

    Key diagnostic tools include:

    • Fasting Blood Glucose: A blood sample taken after at least 8 hours without food. A result of 100–125 mg/dL indicates prediabetes; 126 mg/dL or higher on two occasions indicates type 2 diabetes.
    • Hemoglobin A1C (HbA1c): Reflects your average blood sugar over the past 2–3 months. A result of 5.7–6.4% indicates prediabetes; 6.5% or higher indicates diabetes.
    • Fasting Insulin Level: Some physicians order this alongside glucose to calculate a measure of insulin resistance called HOMA-IR (Homeostatic Model Assessment of Insulin Resistance). This is not universally standardized but can be clinically informative.
    • Lipid Panel: High triglycerides (above 150 mg/dL) and low HDL are common metabolic markers associated with insulin resistance.
    • Blood Pressure Measurement: Hypertension frequently co-occurs with insulin resistance as part of metabolic syndrome.
    • Waist Circumference: The American Heart Association considers a waist of more than 40 inches in men or 35 inches in women a significant clinical risk marker.

    The American Diabetes Association recommends that adults aged 35 to 70 who are overweight or have additional risk factors get screened for prediabetes and diabetes during routine care. If your results are borderline or if you have symptoms, do not wait — advocate for screening at your next appointment.

    Treatment Options for Insulin Resistance

    The good news is that insulin resistance is one of the most treatable metabolic conditions, particularly when caught early. Clinical evidence strongly supports both lifestyle-based approaches and, when appropriate, pharmacological intervention.

    Conventional Medical Treatments:

    Metformin is the most widely studied medication for insulin resistance and prediabetes. The landmark NIH-funded Diabetes Prevention Program (DPP) trial demonstrated that metformin reduced the risk of progressing from prediabetes to type 2 diabetes by 31% over three years. Your physician will determine whether medication is appropriate for your individual situation.

    For people who have already developed type 2 diabetes alongside insulin resistance, a growing class of medications — including GLP-1 receptor agonists and SGLT2 inhibitors — have shown significant benefits not only for blood sugar control but also for cardiovascular and kidney protection, according to the American Diabetes Association’s 2025–2026 Standards of Care.

    Lifestyle Modifications (First-Line Approach):

    The same Diabetes Prevention Program trial found that structured lifestyle change — specifically, 150 minutes per week of moderate exercise and a 5–7% reduction in body weight — reduced the risk of progressing to type 2 diabetes by an impressive 58%. That outperformed metformin alone.

    • Dietary changes: Clinical evidence indicates that reducing refined carbohydrates and added sugars, increasing dietary fiber, and prioritizing lean proteins and healthy fats meaningfully improves insulin sensitivity. The Mediterranean diet and low-glycemic-index approaches have both shown strong results in clinical trials.
    • Physical activity: Both aerobic exercise (brisk walking, cycling, swimming) and resistance training independently improve insulin sensitivity. Research suggests that even a 10-minute walk after meals can reduce post-meal blood sugar spikes.
    • Weight management: Losing even 5–10% of body weight can produce clinically significant improvements in insulin sensitivity, according to the CDC’s National Diabetes Prevention Program.
    • Sleep optimization: Prioritizing 7–9 hours of quality sleep per night is an underappreciated metabolic intervention. Poor sleep is consistently linked to worsened insulin resistance. Our article on Weight Loss and Sleep: Why Rest Is Key to Losing Fat offers helpful practical strategies.
    • Stress management: Chronic stress elevates cortisol, which directly counteracts insulin signaling. Practices such as mindfulness, structured breathing, and regular physical activity all help moderate cortisol levels.

    Living With Insulin Resistance: Day-to-Day Management

    Managing insulin resistance is a long-term commitment — but it does not have to feel overwhelming. Small, consistent habits compound into significant metabolic change over months and years.

    Practical daily strategies:

    • Eat meals at consistent times to support stable blood sugar rhythms
    • Pair carbohydrates with protein, fiber, or healthy fat at every meal to blunt glucose spikes
    • Aim for at least 30 minutes of moderate movement most days — even breaking it into three 10-minute walks counts
    • Limit alcohol, which can interfere with glucose regulation and insulin signaling
    • Monitor your progress: ask your doctor to recheck your A1C or fasting glucose every 3–6 months if you are managing prediabetes
    • Keep a simple food and activity log — research suggests that self-monitoring improves outcomes

    If you are managing additional weight-related challenges alongside insulin resistance, our article on Weight Loss After 40: Why It’s Harder and What Works addresses the unique metabolic factors that come into play as you age.

    Remember: this varies from person to person. What works well for one individual may need to be adjusted for another based on medications, other health conditions, preferences, and genetics. Your care team is your most important partner in this process.

    When to Call Your Doctor — Emergency Signs

    Most of the time, insulin resistance and prediabetes are managed through scheduled appointments. However, certain symptoms require urgent or emergency attention.

    Call your doctor promptly if you notice:

    • Blood sugar readings consistently above 200 mg/dL (if you are monitoring at home)
    • Unexplained weight loss
    • Progressive numbness, tingling, or pain in feet or hands
    • Worsening blurry vision
    • Recurring infections that are difficult to resolve

    Seek emergency care immediately if you experience:

    • Extreme thirst combined with confusion or disorientation
    • Fruity-smelling breath and nausea or vomiting (possible signs of diabetic ketoacidosis)
    • Rapid breathing, severe abdominal pain
    • Loss of consciousness or inability to be awakened
    • Blood sugar above 300 mg/dL with symptoms

    These symptoms may indicate a serious complication requiring immediate medical intervention. Do not wait to see if they resolve on their own.

    Frequently Asked Questions About Insulin Resistance

    Can insulin resistance be reversed?
    Research suggests that insulin resistance can be significantly improved — and in many cases brought back to normal ranges — through sustained lifestyle changes, particularly weight loss, regular exercise, and dietary modification. The word "reversed" should be understood carefully: in most cases it means achieving and maintaining normal blood sugar levels, not that your underlying genetic susceptibility disappears. Consistency over time is what drives lasting results.

    Is insulin resistance the same as type 2 diabetes?
    No — but insulin resistance is typically the underlying mechanism that leads to type 2 diabetes when left unmanaged. You can have insulin resistance and prediabetes without having type 2 diabetes. Early identification and intervention at the prediabetes stage can prevent or significantly delay the development of diabetes.

    What foods are worst for insulin resistance?
    Clinical evidence indicates that refined carbohydrates (white bread, white rice, sugary cereals), sugar-sweetened beverages, and ultra-processed snack foods cause the largest and fastest blood sugar spikes, worsening insulin resistance over time. Most physicians and registered dietitians recommend prioritizing whole grains, vegetables, legumes, lean proteins, and healthy fats.

    Can thin or normal-weight people have insulin resistance?
    Yes. While excess body fat — particularly visceral fat — is a major driver, insulin resistance can occur in individuals with a normal BMI, particularly those who are sedentary, have a family history of diabetes, or carry metabolic risk factors. This is sometimes called "metabolically unhealthy normal weight." Lab testing is the only reliable way to identify it.

    How long does it take to improve insulin sensitivity?
    This varies from person to person, but clinical evidence indicates that meaningful improvements in insulin sensitivity can occur within 2–4 weeks of consistent aerobic exercise and dietary changes. More significant improvements in A1C or fasting glucose are typically measurable within 3–6 months of sustained lifestyle change.

    Taking Control of Your Metabolic Health

    Insulin resistance is not a life sentence — it is a signal. Your body is telling you that something needs to change, and the evidence is clear that change is possible at almost any stage of the process.

    Whether you are managing prediabetes, recently diagnosed with type 2 diabetes, or simply trying to understand a borderline lab result, knowledge is your most powerful tool. Work with your physician to get the right tests, understand your numbers, and build a plan that fits your real life.

    Small daily choices — a walk after dinner, choosing whole grains over refined ones, getting to bed an hour earlier — add up to measurable metabolic improvements over time. You do not have to do everything perfectly. You just have to keep moving in the right direction, consistently, with qualified medical support by your side.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Insulin Resistance: Causes, Signs & How to Reverse It

    Insulin Resistance: Causes, Signs & How to Reverse It

    Understanding insulin resistance could be the most important step you take toward protecting your long-term health.

    Marcus, 47, had been feeling exhausted for months. His doctor told him his fasting blood sugar was “borderline,” and that he should “watch what he eats.” He nodded politely — but walked out of the office not entirely sure what was wrong or what to do next. What Marcus had was insulin resistance, a condition that affects an estimated 88 million American adults, according to the CDC. And like most of them, he had no idea.

    Insulin resistance is one of the most common — and most misunderstood — metabolic conditions in the United States. It sits at the very root of type 2 diabetes, heart disease, and a host of other chronic illnesses. The good news? It is detectable early, and with the right approach, many people can significantly improve their insulin sensitivity before it progresses to full-blown diabetes.

    In this guide, you will learn exactly what insulin resistance is, how to recognize its early signs, what causes it, and — most importantly — what evidence-based steps you and your doctor can take together to manage it effectively.

    What Is Insulin Resistance?

    Insulin is a hormone produced by the pancreas. Its primary job is to act like a key, unlocking your body’s cells so that glucose (sugar from food) can enter and be used for energy. When everything works correctly, your cells respond well to insulin’s signal. Blood sugar stays stable, energy levels remain consistent, and your organs function properly.

    Insulin resistance occurs when your cells — particularly in the muscles, fat, and liver — stop responding normally to insulin. Instead of opening up to let glucose in, they essentially ignore the signal. To compensate, your pancreas produces more and more insulin, trying to force the job done. For a while, blood sugar remains normal. But over time, the pancreas cannot keep up, and blood sugar begins to rise.

    According to the National Institutes of Health (NIH), insulin resistance is a core feature of prediabetes and type 2 diabetes. The CDC estimates that 96 million American adults — more than 1 in 3 — have prediabetes, and approximately 80% don’t know it. Left unaddressed, prediabetes progresses to type 2 diabetes within 5 to 10 years in many individuals.

    Insulin resistance does not just affect blood sugar. It is closely linked to high blood pressure, elevated triglycerides, low HDL (“good”) cholesterol, and increased abdominal fat — a cluster of problems collectively known as metabolic syndrome.

    Signs and Symptoms of Insulin Resistance

    One of the most challenging aspects of insulin resistance is that it often produces no obvious symptoms in its early stages. Many people live with it for years without knowing. However, there are warning signs worth paying attention to.

    Early and common signs may include:

    • Persistent fatigue, especially after meals
    • Intense carbohydrate or sugar cravings
    • Difficulty losing weight, particularly around the abdomen
    • Brain fog or difficulty concentrating
    • Slightly elevated fasting blood sugar (100–125 mg/dL, the prediabetes range)
    • High triglycerides or low HDL cholesterol on a blood panel
    • Elevated blood pressure without an obvious cause

    A notable physical sign to know:

    • Acanthosis nigricans — darkened, velvety patches of skin, typically around the neck, armpits, or groin. This is a visible skin change associated with elevated insulin levels and is recognized by clinicians as a physical marker of insulin resistance.

    A 2021 study published in the journal Diabetes Care found that individuals with insulin resistance frequently show metabolic abnormalities — including elevated fasting insulin levels — years before blood sugar rises into the diabetic range. This underscores the importance of early detection through routine lab work rather than waiting for symptoms to worsen.

    Red flag symptoms that require prompt medical attention:

    • Fasting blood sugar consistently above 126 mg/dL
    • Extreme thirst and frequent urination
    • Blurred vision
    • Unexplained weight loss
    • Numbness or tingling in the hands or feet

    If you experience any of these, contact your healthcare provider without delay — these may indicate that type 2 diabetes has already developed.

    Causes and Risk Factors

    Insulin resistance does not have a single cause. It develops through a combination of genetic predisposition, lifestyle factors, and environmental influences. Understanding what raises your risk is the first step toward prevention.

    Lifestyle-related risk factors:

    • Physical inactivity — Skeletal muscle is the body’s largest consumer of glucose. When muscles are sedentary, they become less sensitive to insulin. The American Diabetes Association (ADA) identifies physical inactivity as one of the most modifiable risk factors for insulin resistance.
    • Excess body fat — Particularly visceral fat (the deep fat surrounding your organs). Fat cells, especially in the abdomen, release inflammatory chemicals that interfere with insulin signaling. Research from Harvard Health suggests that even a 5–7% reduction in body weight can meaningfully improve insulin sensitivity.
    • Poor diet — Diets high in refined carbohydrates, added sugars, and ultra-processed foods repeatedly spike blood glucose, forcing the pancreas to overproduce insulin. Over time, cells downregulate their response.
    • Chronic sleep deprivation — Even a single night of poor sleep has been shown to reduce insulin sensitivity by up to 25%, according to research cited by the NIH.
    • Chronic stress — The stress hormone cortisol raises blood glucose and impairs insulin action.

    Genetic and biological risk factors:

    • Family history of type 2 diabetes
    • Age 45 or older
    • Race and ethnicity — Black, Hispanic, Asian American, and Native American populations face disproportionately higher risk, according to CDC data
    • History of gestational diabetes or polycystic ovary syndrome (PCOS)

    This variation matters: two people with identical lifestyles may develop insulin resistance at very different rates based on genetics. This is why personalized medical guidance is essential.

    Diagnosis: What to Expect

    There is no single standardized test that diagnoses “insulin resistance” directly as a standalone condition. However, your doctor has several reliable tools to assess it and its metabolic consequences.

    Common tests your doctor may order:

    • Fasting blood glucose — A level between 100 and 125 mg/dL indicates prediabetes; 126 mg/dL or higher on two separate tests indicates type 2 diabetes.
    • Hemoglobin A1C (HbA1c) — Reflects average blood sugar over the past 2–3 months. A result between 5.7% and 6.4% signals prediabetes. You can learn more about what your A1C number means in our detailed guide: A1C Levels Explained: What Every Diabetic Must Know.
    • Fasting insulin level — Not always routine, but an elevated fasting insulin alongside normal blood sugar is a strong indicator of insulin resistance. Your doctor may calculate a HOMA-IR score (Homeostatic Model Assessment of Insulin Resistance) using glucose and insulin values together.
    • Lipid panel — High triglycerides (above 150 mg/dL) and low HDL cholesterol are metabolic hallmarks of insulin resistance.
    • Oral Glucose Tolerance Test (OGTT) — Measures how your body processes glucose over two hours after drinking a sugary solution. Often used in diagnosing gestational diabetes but can reveal prediabetes in non-pregnant adults as well.

    The American Diabetes Association recommends screening for prediabetes and type 2 diabetes in all adults starting at age 35, or earlier if risk factors are present. If you have not been screened recently, discuss this with your physician at your next visit.

    Treatment Options for Insulin Resistance

    The most powerful treatments for insulin resistance combine medical oversight with meaningful lifestyle changes. There is no one-size-fits-all approach — what works best varies from person to person — but the evidence is clear that early, consistent action makes a measurable difference.

    Conventional medical treatments:

    Metformin is the most commonly prescribed medication for prediabetes and early type 2 diabetes in the US. Clinical evidence indicates it works by reducing the liver’s overproduction of glucose and improving the body’s response to insulin. The Diabetes Prevention Program (DPP) — a landmark NIH-funded clinical trial — showed that metformin reduced progression from prediabetes to type 2 diabetes by 31% over three years. Your doctor will determine whether medication is appropriate for your specific situation.

    Newer medication classes, including GLP-1 receptor agonists (such as semaglutide) and SGLT-2 inhibitors, have shown strong clinical evidence not only for improving blood sugar control but also for reducing cardiovascular risk in people with type 2 diabetes. If you are already living with diabetes and managing medications, our article on Optimizing Diabetes Medication Adherence offers practical strategies to help you stay on track.

    Lifestyle modifications — the cornerstone of treatment:

    Physical activity is arguably the most effective tool for improving insulin sensitivity. Muscle contractions during exercise allow glucose to enter cells independently of insulin. The ADA recommends at least 150 minutes of moderate-intensity aerobic exercise per week, plus 2–3 days of resistance training. Research suggests that even a single 30-minute brisk walk can temporarily improve insulin sensitivity in people with prediabetes.

    Dietary changes should focus on reducing refined carbohydrates and added sugars, increasing fiber intake (vegetables, legumes, whole grains), including healthy fats (olive oil, avocado, nuts), and choosing lean proteins. The Mediterranean dietary pattern, in particular, has robust clinical evidence supporting improved insulin sensitivity and reduced risk of type 2 diabetes.

    Weight management remains a high-impact target. The DPP trial demonstrated that a 5–7% reduction in body weight through diet and exercise reduced diabetes risk by 58% in high-risk adults — nearly double the effect of metformin alone. If weight management feels like a persistent challenge, our resource on Sustainable Weight Loss: Habits for Lasting Health provides evidence-based strategies worth exploring with your care team.

    Sleep optimization — Prioritizing 7–9 hours of quality sleep per night is not optional when managing insulin resistance. Clinical evidence consistently links poor sleep to elevated fasting glucose and impaired insulin action.

    Stress management — Chronic stress keeps cortisol levels elevated, which perpetuates insulin resistance. Mindfulness, structured breathing exercises, therapy, and regular physical activity are all evidence-supported approaches.

    Living With Insulin Resistance: Day-to-Day Management

    Managing insulin resistance is not a short-term project — it is an ongoing lifestyle practice. But many people who commit to it experience substantial improvements in energy, weight, and metabolic health within weeks to months.

    Practical daily habits that support better insulin sensitivity:

    • Eat balanced meals that pair carbohydrates with protein and fiber to blunt glucose spikes
    • Avoid long periods of sitting — stand or walk for a few minutes every hour
    • Keep a consistent sleep schedule, even on weekends
    • Limit alcohol, which can worsen insulin resistance and raise triglycerides
    • Monitor your blood sugar if your doctor recommends it — awareness is a powerful motivator
    • Schedule regular follow-up labs (A1C, fasting glucose, lipid panel) at least annually, or as advised

    Prevention matters here too. If you have risk factors but have not yet been diagnosed with prediabetes, the same lifestyle strategies apply. Clinical evidence shows that the earlier you intervene, the more effectively you can protect your metabolic health long-term.

    When to Call Your Doctor: Emergency Signs

    Insulin resistance itself is rarely a medical emergency. However, if it has progressed — or if it is accompanied by other conditions — certain symptoms demand immediate attention.

    Call 911 or go to the emergency room immediately if you experience:

    • Confusion, disorientation, or loss of consciousness (possible hypoglycemia if you take diabetes medications)
    • Chest pain or pressure, shortness of breath, or sudden arm pain (signs of cardiac event, which people with insulin resistance are at higher cardiovascular risk for)
    • Difficulty speaking or sudden weakness on one side of the body (possible stroke)

    Schedule a prompt (non-emergency) appointment with your doctor if you notice:

    • New or worsening fatigue, thirst, or frequent urination
    • Blood sugar readings consistently outside your target range
    • New darkening of the skin around the neck or armpits
    • Unexplained weight changes
    • A fasting glucose reading above 100 mg/dL for the first time

    At your next routine appointment, consider telling your doctor: “I’d like to check my fasting glucose, A1C, insulin level, and full lipid panel. I’m concerned about my risk for insulin resistance and want to be proactive.”

    Frequently Asked Questions

    Q: Can insulin resistance be reversed completely?
    A: Research suggests that insulin resistance — particularly in its early stages — can be significantly improved, and in some cases effectively normalized, through sustained lifestyle changes including weight loss, regular exercise, and dietary modification. However, “reversal” is a complex term, and individual results vary. Most physicians prefer the term “remission” or “improved insulin sensitivity.” Ongoing monitoring remains important even after improvement.

    Q: Is insulin resistance the same as type 2 diabetes?
    A: Not exactly. Insulin resistance is a precursor condition that, if left unmanaged, can progress to type 2 diabetes. Type 2 diabetes is diagnosed when blood sugar reaches chronically elevated levels and the pancreas can no longer compensate. Think of insulin resistance as a warning sign — an opportunity to act before diabetes develops.

    Q: What foods should I avoid if I have insulin resistance?
    A: Clinical guidance generally recommends limiting refined carbohydrates (white bread, white rice, pastries), sugary beverages, ultra-processed snacks, and foods high in added sugars. These foods cause rapid blood glucose spikes that stress the insulin system. This varies from person to person, and a registered dietitian can help you build a personalized eating plan.

    Q: Can thin people develop insulin resistance?
    A: Yes. While excess body fat — especially visceral abdominal fat — is a major risk factor, insulin resistance can occur in people with a normal body weight. This is sometimes called “metabolically unhealthy normal weight” or TOFI (thin outside, fat inside). Genetics, physical inactivity, and diet quality all play a role regardless of body size.

    Q: How long does it take to improve insulin sensitivity?
    A: Clinical evidence indicates that meaningful improvements in insulin sensitivity can occur within 4–12 weeks of consistent aerobic exercise and dietary changes, even before significant weight loss occurs. Muscle-building exercise may show results even sooner. However, maintaining these improvements requires ongoing lifestyle commitment — not a short-term fix.

    The Bottom Line

    Insulin resistance is one of the most prevalent and consequential metabolic conditions affecting American adults today — and one of the most actionable. The path forward is not about perfection; it is about consistent, evidence-based steps taken alongside your healthcare team. From improving your sleep and moving more each day, to working with your doctor on the right screening and treatment plan, every decision compounds over time.

    You do not have to wait until a diabetes diagnosis arrives to take your metabolic health seriously. If Marcus’s story sounds familiar, use it as motivation. Talk to your doctor. Get your labs. Ask questions. Early awareness and informed action are two of the most powerful tools available to you — and they start today.

    Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.


    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • A1C Levels Explained: What Every Diabetic Must Know

    A1C Levels Explained: What Every Diabetic Must Know

    A1C Levels Explained: What Every Diabetic Must Know

    Your A1C number is one of the most powerful predictors of long-term diabetes complications — and understanding it could change how you manage your health every single day.

    Introduction

    When Marcus, 54, was first diagnosed with type 2 diabetes, his doctor kept talking about something called A1C. He nodded along, went home, and Googled it — only to find pages of confusing charts and medical jargon that left him more overwhelmed than before.

    Sound familiar? You are not alone. According to the CDC, more than 38 million Americans are living with diabetes, and tens of millions more have prediabetes — yet surveys consistently show that a significant portion of patients don’t fully understand what their A1C test measures, what their target number should be, or what to do when it’s too high.

    This guide is here to change that. By the end of this article, you will understand exactly what A1C levels mean, how the test works, what your results say about your health, and — most importantly — what practical steps you can take with your doctor to bring your numbers into a healthier range. Whether you were recently diagnosed or have been managing diabetes for years, this is the guide you’ve been looking for.

    What Is the A1C Test?

    The A1C test — also called the hemoglobin A1C, HbA1c, or glycated hemoglobin test — measures your average blood sugar levels over the past two to three months. Unlike a daily fingerstick reading that captures just one moment in time, the A1C gives your doctor a broader snapshot of how well your blood sugar has been controlled over a longer period.

    Here’s how it works in plain terms: sugar (glucose) in your bloodstream naturally attaches to hemoglobin, the protein inside red blood cells that carries oxygen. Because red blood cells live for about 90 days, the A1C test measures what percentage of your hemoglobin has glucose attached to it. The higher your blood sugar has been, the higher the percentage — and the higher your A1C result.

    According to the American Diabetes Association (ADA), the A1C test is one of the primary tools used to diagnose both prediabetes and type 2 diabetes, and it remains the gold standard for monitoring long-term blood sugar management in people already living with the condition.

    For context, a normal A1C for someone without diabetes is typically below 5.7%. An A1C between 5.7% and 6.4% suggests prediabetes, and an A1C of 6.5% or higher on two separate tests is generally used to confirm a diabetes diagnosis, per ADA guidelines.

    Understanding Your A1C Results: What the Numbers Mean

    Seeing a number on your lab report is one thing. Understanding what it actually means for your body is another. Here’s a practical breakdown:

    • Below 5.7% — Normal range. Blood sugar is well-regulated, and diabetes risk is low.
    • 5.7% to 6.4% — Prediabetes. Blood sugar is elevated but not yet at diabetic levels. This is a critical window for lifestyle intervention.
    • 6.5% or higher — Diabetes. Consistent readings at this level confirm a diabetes diagnosis and indicate a need for active management.
    • 7.0% or lower (with diabetes) — This is the general target set by the ADA for most non-pregnant adults with diabetes, as it significantly reduces the risk of complications.
    • Above 9.0% — Signals poor blood sugar control and a substantially elevated risk of serious complications, including kidney damage, nerve damage, and vision problems.

    It’s important to note that A1C targets are not one-size-fits-all. Research suggests that older adults, people with a history of severe hypoglycemia (low blood sugar), or those with other significant health conditions may have individualized targets set higher — for example, below 8.0% — to avoid the risks of blood sugar dropping too low. Always work with your physician to determine what goal is right for you specifically.

    A landmark NIH-supported study, the DCCT (Diabetes Control and Complications Trial), established that lowering A1C levels significantly reduces the risk of diabetic eye disease, kidney disease, and nerve damage. This research became the scientific foundation for why A1C management is central to diabetes care.

    Signs That Your A1C May Be Too High

    A high A1C doesn’t always come with obvious symptoms — which is one reason the condition can quietly cause damage before people realize something is wrong. That said, certain signs can suggest that your blood sugar has been running too high for too long.

    Early or moderate warning signs may include:

    • Increased thirst and frequent urination
    • Unexplained fatigue and low energy
    • Blurred vision that comes and goes
    • Cuts or sores that are slow to heal
    • Recurring infections (especially skin, bladder, or gum infections)
    • Tingling or numbness in the feet or hands (early neuropathy)
    • Increased hunger even after eating

    More advanced signs associated with chronically high A1C:

    • Significant unintended weight loss
    • Persistent foot pain or wounds that won’t heal
    • Decreased kidney function (swelling in legs, changes in urine output)
    • Vision changes that don’t resolve
    • Chest discomfort or shortness of breath (may indicate cardiovascular complications)

    Clinical evidence from the CDC indicates that adults with poorly controlled blood sugar have two to four times the risk of dying from heart disease compared to those without diabetes. This is why monitoring and managing A1C is not just a numbers game — it’s a life-or-death health priority.

    What Causes A1C Levels to Rise?

    Understanding why your A1C climbs helps you take more targeted action. Multiple factors contribute, and they interact in complex ways that vary from person to person.

    Dietary patterns: Consistently eating foods that spike blood sugar — refined carbohydrates, sugary beverages, ultra-processed snacks — keeps glucose levels elevated over time. If you are curious about which foods are most impactful, our article on the Type 2 Diabetes Diet: Best Foods to Control Blood Sugar offers a research-backed deep dive.

    Physical inactivity: Muscle cells use glucose for energy during movement. When you’re sedentary, your body becomes less efficient at removing glucose from the bloodstream, contributing to higher averages.

    Medication adherence: Skipping or inconsistently taking diabetes medications — whether oral drugs or insulin — is a leading cause of rising A1C in people already diagnosed. Never stop or adjust your medications without talking to your doctor first.

    Stress (both physical and emotional): Stress hormones like cortisol and adrenaline directly raise blood sugar. Chronic stress, anxiety, or illness can push A1C higher even when your diet and medications haven’t changed. Research from Harvard Health suggests that psychological stress is a significantly underestimated driver of glucose dysregulation.

    Sleep disruption: Poor sleep — including conditions like sleep apnea — impairs insulin sensitivity and glucose metabolism. A NIH-backed study found that just a few nights of reduced sleep significantly worsened blood sugar control in people with type 2 diabetes.

    Other medical conditions: Thyroid disorders, anemia, and kidney disease can all affect A1C readings. This is why your doctor considers your full health picture, not just one number.

    Carrying excess weight — particularly visceral (belly) fat — is one of the strongest modifiable risk factors for insulin resistance. If this is a concern for you, our guide on How to Lose Belly Fat: A Science-Based Guide offers practical, evidence-based strategies that complement your diabetes management plan.

    How to Lower Your A1C: Treatment Options That Work

    The good news is that A1C levels respond to consistent, sustained effort. A reduction of even half a percentage point can meaningfully lower your risk of complications. Here is what the clinical evidence supports:

    Medications prescribed by your doctor: A wide range of evidence-based medications are available to lower blood sugar and A1C, including metformin (typically the first-line oral medication), SGLT2 inhibitors, GLP-1 receptor agonists, DPP-4 inhibitors, and insulin therapy. Your physician will tailor the medication plan to your specific health profile. Never self-adjust dosages.

    Dietary changes: Clinical evidence consistently shows that reducing refined carbohydrates, increasing fiber intake, and choosing lower-glycemic foods significantly lowers A1C over time. The ADA supports a variety of eating patterns — Mediterranean, low-carbohydrate, and DASH diets — depending on individual preference and metabolic response.

    Regular physical activity: The ADA recommends at least 150 minutes of moderate-intensity aerobic activity per week, spread across most days. Resistance training two to three days per week is also strongly supported. Exercise acts like insulin — it helps muscles pull glucose out of the bloodstream. Research published in Diabetes Care found that structured exercise programs reduced A1C by an average of 0.66% compared to control groups.

    Weight management: Losing as little as 5-10% of body weight can produce meaningful improvements in A1C for overweight adults. For those eligible, metabolic surgery (bariatric surgery) has been shown to achieve dramatic and sustained A1C reductions. Our article on Metabolic Weight Loss: What’s Really Slowing You Down explores how metabolism affects your ability to lose weight and manage blood sugar.

    Continuous glucose monitoring (CGM): Wearable devices that track glucose in real time help patients and doctors identify patterns — when blood sugar spikes, how long it stays elevated, and what triggers the rise. Research suggests that CGM use is associated with significant A1C reductions, particularly in people using insulin.

    Sleep and stress management: Prioritizing seven to nine hours of quality sleep and using evidence-based stress reduction strategies — such as mindfulness, cognitive behavioral techniques, or structured relaxation — can meaningfully support blood sugar control as part of a comprehensive plan.

    Living With Diabetes: Day-to-Day A1C Management

    Managing A1C isn’t just about what happens in the doctor’s office. It’s about building sustainable habits that work in real life — not perfection, but consistency.

    Most physicians recommend an A1C test every three months for people whose blood sugar is not well controlled, and every six months for those who are meeting their targets. Keep a log of your readings over time so you and your doctor can identify trends rather than reacting to a single result.

    Meal timing matters as much as meal content. Eating at consistent times, avoiding skipping meals (which can trigger reactive overeating), and moderating portion sizes all support more stable blood glucose throughout the day.

    Build a support system. Research from the Mayo Clinic shows that people with strong social support — family involvement, diabetes education programs, or peer support groups — tend to achieve better long-term A1C outcomes than those managing alone. Diabetes distress — the emotional burden of living with a chronic condition — is real and common. If you are feeling overwhelmed, anxious, or depressed about your health, know that mental health support is a legitimate and important part of diabetes care.

    Work with a registered dietitian, a certified diabetes care and education specialist (CDCES), or a diabetes management program if those resources are available to you. These professionals are specifically trained to help you translate clinical targets into practical, personalized strategies.

    When to Call Your Doctor or Seek Emergency Care

    Some situations require immediate medical attention — don’t wait for your next scheduled appointment if you notice these warning signs.

    Call your doctor soon if you experience:

    • Your A1C comes back significantly higher than your previous result despite no obvious change in habits
    • Frequent episodes of low blood sugar (hypoglycemia) — shakiness, sweating, confusion — especially if they’re happening during sleep or driving
    • New or worsening numbness, tingling, or pain in your feet or hands
    • Vision changes or eye pain
    • Swelling in your legs or feet that is new or worsening
    • Wounds on your feet that are not healing after one to two weeks

    Go to the emergency room or call 911 immediately if you experience:

    • Severe confusion, disorientation, or loss of consciousness
    • Unresponsiveness to sugar intake during a hypoglycemic episode
    • Rapid breathing, fruity-smelling breath, or extreme nausea and vomiting (possible signs of diabetic ketoacidosis — DKA)
    • Chest pain, sudden severe headache, or difficulty speaking (possible stroke or heart attack, which people with diabetes face higher risk of)

    These are not situations to manage at home or wait out. Diabetic emergencies can escalate quickly. When in doubt, call 911 or get to an emergency facility immediately.

    Frequently Asked Questions

    How often should I get my A1C tested?
    The ADA recommends testing every three months if your diabetes is not well controlled or if your treatment plan has recently changed. If your A1C is consistently at or below your target, testing every six months may be appropriate. Your doctor will advise based on your individual situation.

    Can A1C levels be falsely high or low?
    Yes. Certain conditions can affect the accuracy of A1C readings. Anemia, sickle cell disease, kidney failure, and recent blood transfusions can all distort results. If your A1C doesn’t match how you feel or your daily glucose readings, mention this to your doctor — they may order additional tests to get a clearer picture.

    How fast can A1C change?
    Because the test reflects a two- to three-month average, meaningful changes in A1C typically take at least 90 days to appear. However, clinical evidence indicates that significant dietary and medication changes can produce measurable A1C improvements within three months. Be patient and consistent — the number will respond over time.

    Is a lower A1C always better?
    Not necessarily. While high A1C is dangerous, pushing A1C too low can increase the risk of hypoglycemia, which can be life-threatening, especially in older adults. Most physicians recommend individualized targets — the ADA’s general goal of below 7.0% is not appropriate for everyone. Discuss your specific target with your care team.

    Can prediabetes A1C levels go back to normal?
    Research suggests yes, for many people. The NIH’s landmark Diabetes Prevention Program (DPP) study found that lifestyle changes — including losing 5-7% of body weight and engaging in 150 minutes of moderate activity per week — reduced progression from prediabetes to type 2 diabetes by 58%. Some participants saw their A1C return to the normal range entirely. This does not happen for everyone, but early intervention meaningfully improves the odds.

    Conclusion

    Your A1C number is not a judgment — it’s a tool. It tells you and your doctor how your blood sugar management is working over time, and it gives you a clear, measurable way to track your progress. Whether your number is higher than you’d like right now or you’re working to keep it in a healthy range, the most important thing you can do is stay engaged, stay consistent, and stay connected with your healthcare team.

    Small, sustained changes in nutrition, physical activity, sleep, stress management, and medication adherence add up to real reductions in A1C — and real reductions in your long-term risk of complications. You don’t have to do this alone, and you don’t have to be perfect. You just have to keep moving in the right direction.

    Talk to your doctor at your next visit about your A1C target, how often you should be tested, and what adjustments — if any — make sense for your current plan. That conversation is one of the most valuable things you can do for your long-term health.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.