Nerve damage from diabetes is more common — and more preventable — than most people realize.
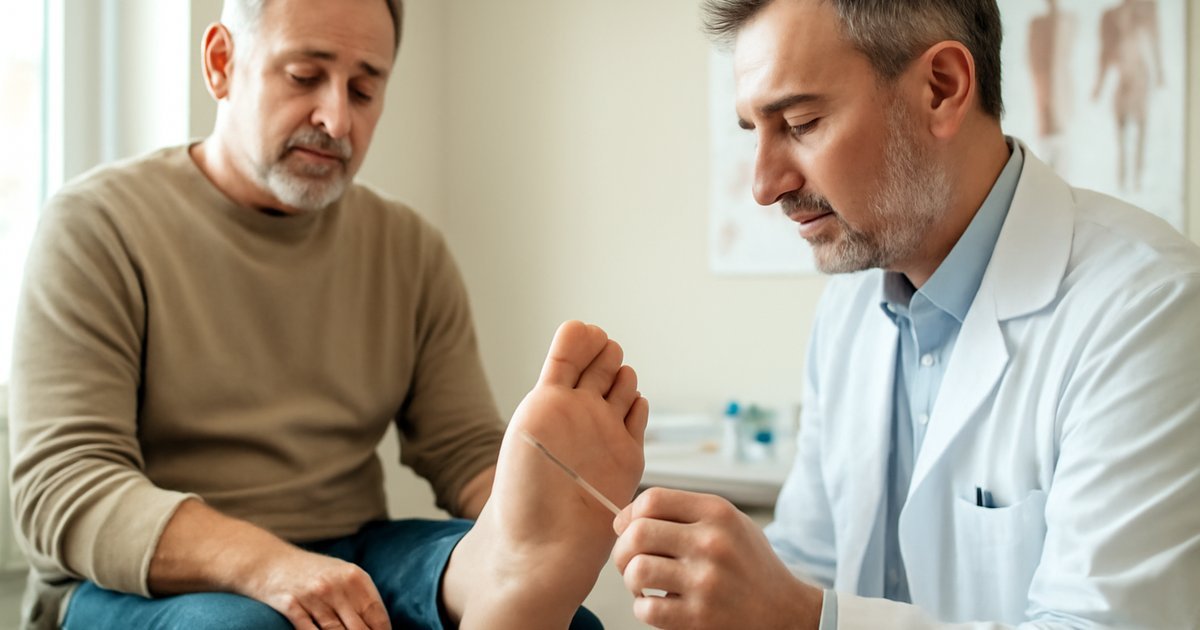
Michael, 54, had been living with type 2 diabetes for about eight years when he noticed something odd: a persistent tingling in his feet, almost like they had "fallen asleep" and never fully woken up. He assumed it was nothing serious. By the time he mentioned it to his doctor, he had already developed a small wound on his right foot that he hadn't even felt forming.
Michael's experience is far from rare. According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), up to 50% of people with diabetes develop some form of diabetic neuropathy — nerve damage caused by prolonged high blood sugar. Yet many people don't recognize the early warning signs until complications have already set in.
In this article, you'll learn what diabetic neuropathy is, how to recognize it early, what causes it, what your doctor can do about it, and — most importantly — how you can take meaningful steps to slow or prevent its progression. This is one of the most common yet underestimated complications of diabetes management, and understanding it could protect your quality of life for decades to come.
What Is Diabetic Neuropathy?
Diabetic neuropathy is a type of nerve damage that develops as a complication of diabetes — both type 1 and type 2. When blood sugar stays elevated for too long, it gradually damages the walls of the tiny blood vessels (called capillaries) that supply your nerves with oxygen and nutrients. Over time, those nerves lose their ability to function properly.
Think of it like a slow power outage: the signals your nerves are supposed to send — pain alerts, touch sensations, organ control — start misfiring or going silent altogether.
There are four main types of diabetic neuropathy:
- Peripheral neuropathy — the most common type, affecting the feet and legs first, then sometimes the hands and arms
- Autonomic neuropathy — affects involuntary body functions like heart rate, digestion, bladder control, and sexual function
- Proximal neuropathy — causes pain in the hips, thighs, or buttocks and may lead to muscle weakness
- Mononeuropathy (focal neuropathy) — sudden damage to a specific nerve, often causing facial or torso pain
The NIDDK estimates that diabetic neuropathy affects between 60% and 70% of people with diabetes at some point during their lives. In the United States, it is one of the leading causes of non-traumatic lower-limb amputations — a sobering statistic that underscores why early detection matters so much.
Signs and Symptoms of Diabetic Neuropathy
Symptoms vary significantly depending on which type of neuropathy you have and how far it has progressed. This variation is one reason it's so often missed in its early stages.
Early symptoms (often subtle):
- Tingling or "pins and needles" sensation in the feet or hands
- Numbness or reduced ability to feel temperature or pain
- Mild burning or aching in the feet, especially at night
- Sensitivity to touch — even light contact from a bedsheet can feel uncomfortable
- Slight muscle weakness in the feet or legs
Advanced or autonomic symptoms:
- Loss of balance or coordination
- Serious foot wounds or ulcers that go unnoticed due to lost sensation
- Digestive problems such as nausea, vomiting, bloating, or gastroparesis (delayed stomach emptying)
- Bladder dysfunction — incomplete emptying or incontinence
- Dizziness or fainting when standing (orthostatic hypotension)
- Sexual dysfunction in men and women
- Irregular heart rate or blood pressure swings
A 2021 clinical review published through the NIH's PubMed database noted that nearly one-third of people with peripheral diabetic neuropathy experience no symptoms at all in the early phase — making routine foot exams at every diabetes appointment an essential, non-negotiable part of care.
Causes and Risk Factors
The primary driver of diabetic neuropathy is chronically elevated blood glucose (blood sugar). High glucose levels trigger a cascade of chemical changes in nerve cells and damage the blood vessels that feed them — a process that unfolds slowly over years.
Key causes include:
- Prolonged hyperglycemia — consistently high blood sugar is the single most important factor
- Inflammation — chronic low-grade inflammation associated with diabetes accelerates nerve damage
- Oxidative stress — an imbalance between free radicals and the body's ability to neutralize them, which harms nerve tissue
- Autoimmune factors — in some cases, the immune system attacks nerve fibers directly
Risk factors that increase your likelihood of developing neuropathy:
- Poor long-term blood sugar control (high A1C levels over many years)
- Duration of diabetes — the longer you have diabetes, the higher the risk
- Obesity and excess abdominal fat
- High blood pressure and high cholesterol
- Smoking — which further restricts blood flow to nerves
- Alcohol use — alcohol is independently toxic to nerve tissue
- Kidney disease (nephropathy), which often coexists with neuropathy
According to the American Diabetes Association (ADA), people who have had diabetes for 25 years or more face a particularly high risk, with prevalence reaching nearly 50% in that population. However, research suggests that aggressive blood sugar management — especially in the first decade after diagnosis — can meaningfully reduce that risk.
Diagnosis: What to Expect
If you mention symptoms like foot tingling, numbness, or burning to your doctor, they will typically conduct a structured neurological evaluation during your office visit. The process is straightforward and usually non-invasive.
Common diagnostic tools include:
- Monofilament test — a thin nylon filament is pressed against different points on your foot to assess touch sensation
- Tuning fork test — evaluates your ability to feel vibrations, a function often lost early in peripheral neuropathy
- Pinprick test — checks pain sensitivity in the feet
- Ankle reflex test — reduced or absent reflexes can indicate nerve damage
- Nerve conduction studies — measures the speed and strength of electrical signals in your nerves; ordered when diagnosis is uncertain or more detailed information is needed
- Electromyography (EMG) — evaluates muscle response to nerve stimulation
- Autonomic function tests — used when autonomic neuropathy is suspected, checking heart rate variability and blood pressure responses
The ADA recommends that all people with type 2 diabetes be screened for peripheral neuropathy at diagnosis and annually thereafter — and that people with type 1 diabetes begin screening five years after their diagnosis. Don't wait for symptoms to appear before asking your doctor to check.
Treatment Options
There is currently no treatment that fully reverses diabetic neuropathy, but multiple approaches — both medical and lifestyle-based — can slow its progression, relieve symptoms, and prevent complications.
Blood sugar control — the foundation of all treatment:
The most powerful intervention is optimizing your glucose levels. Clinical evidence from the landmark Diabetes Control and Complications Trial (DCCT), funded by the NIH, demonstrated that intensive blood sugar management reduced the risk of neuropathy by 60% in people with type 1 diabetes. Similar findings emerged in type 2 diabetes research through the UKPDS (United Kingdom Prospective Diabetes Study). Your doctor may adjust your medications, insulin regimen, or recommend a continuous glucose monitor (CGM) to help achieve better control.
For more on how exercise supports blood sugar control as part of your overall diabetes management plan, see our guide: Exercise and Blood Sugar Control: A Type 2 Diabetes Guide.
Medications for nerve pain:
- Anticonvulsants such as pregabalin (Lyrica) and gabapentin — FDA-approved for diabetic nerve pain, they work by calming overactive pain signals in the nervous system
- Antidepressants such as duloxetine (Cymbalta) — FDA-approved specifically for diabetic peripheral neuropathy pain; also prescribed are tricyclic antidepressants like amitriptyline
- Topical treatments — capsaicin cream and lidocaine patches can offer localized relief for some patients
- Opioid medications — generally used only when other options have failed, due to addiction risk and side effects; most physicians reserve these for severe, refractory pain
Lifestyle modifications that complement medical care:
- Dietary changes — a balanced, lower-glycemic diet supports stable blood sugar; consulting a registered dietitian is highly recommended
- Physical activity — regular moderate exercise improves circulation and may slow nerve damage progression; research suggests even walking 30 minutes five days a week provides measurable benefit
- Smoking cessation — smoking dramatically worsens blood flow to nerves; quitting is one of the most impactful changes you can make
- Limiting alcohol — alcohol is neurotoxic and directly accelerates neuropathy
- Foot care — daily inspection of your feet, appropriate footwear, and prompt treatment of any wound or blister are life-changing habits
If you're also working on weight management — which directly impacts blood sugar — you may find helpful information in our article on Insulin Resistance: Causes, Signs & How to Improve It.
Living With Diabetic Neuropathy: Day-to-Day Management
A diagnosis of diabetic neuropathy is serious, but it doesn't have to define your life. Many people with neuropathy maintain an active, fulfilling lifestyle by building consistent self-care routines and staying in close communication with their healthcare team.
Practical daily habits that make a real difference:
- Inspect your feet every single day — look for redness, swelling, blisters, cuts, or sores. Use a mirror or ask someone to help if needed. Loss of sensation means injuries can develop without you feeling them.
- Wear well-fitting, protective footwear — avoid bare feet, even indoors. Ask your doctor about therapeutic shoes if standard footwear causes pressure points.
- Keep feet clean and moisturized — but avoid lotion between the toes, where moisture can promote infection.
- Monitor your blood sugar regularly — consistent tracking gives you and your care team the data needed to make smart adjustments.
- Manage comorbidities — keeping blood pressure and cholesterol in a healthy range reduces additional vascular stress on your nerves.
- Sleep quality matters — poor sleep can worsen pain perception and disrupt blood sugar regulation. If neuropathy pain disturbs your sleep, discuss this specifically with your doctor. You can also read more about how sleep affects metabolic health in our article: Weight Loss and Sleep: Why Rest Is Key to Losing Weight.
For autonomic neuropathy affecting digestion, your doctor may recommend eating smaller, more frequent meals, avoiding high-fat foods, and adjusting meal timing relative to insulin or medication schedules.
Prevention strategies for those not yet diagnosed:
If you have diabetes but haven't developed neuropathy yet, now is the critical window. Clinical evidence consistently shows that maintaining an A1C below 7% (or the target your doctor sets for you), exercising regularly, not smoking, and attending every recommended screening appointment significantly reduces your lifetime risk of developing significant nerve damage.
When to Call Your Doctor — and Emergency Warning Signs
Diabetic neuropathy can escalate quickly in certain situations. Knowing when to act is not just smart — it's potentially limb-saving.
Schedule a prompt (non-emergency) appointment if you notice:
- New tingling, numbness, or burning in your feet or hands
- Increased pain that isn't relieved by your current medications
- Difficulty walking, balancing, or climbing stairs
- Digestive changes like persistent nausea, early fullness, or unpredictable bowel habits
- New bladder symptoms — difficulty urinating or frequent leakage
- Dizziness when standing up
- Sexual dysfunction that has recently developed or worsened
Seek emergency care immediately if you experience:
- A foot wound, ulcer, or blister that shows signs of infection — redness spreading outward, warmth, pus, or foul odor
- Any foot injury that isn't healing after a few days, even if it seems minor
- Sudden, severe weakness in the legs
- Chest pain, severe dizziness, or fainting (possible autonomic neuropathy affecting the heart)
- Signs of diabetic ketoacidosis (DKA) — extreme thirst, frequent urination, confusion, fruity-smelling breath
The CDC notes that diabetic foot complications result in more than 100,000 lower-limb amputations annually in the United States. The overwhelming majority of these are preventable with early detection, consistent foot care, and timely medical attention.
Frequently Asked Questions About Diabetic Neuropathy
Can diabetic neuropathy be reversed?
In most cases, nerve damage from diabetic neuropathy cannot be fully reversed. However, research suggests that with strict blood sugar control, the progression can be significantly slowed — and in some early cases, partial improvement in nerve function is possible. The goal of treatment is to stop further damage and manage symptoms effectively.
How fast does diabetic neuropathy progress?
This varies considerably from person to person. Progression depends largely on how well blood sugar is controlled over time, how long you've had diabetes, and whether you have additional risk factors like smoking or high blood pressure. Some people see very slow progression over decades; others experience more rapid deterioration if glucose levels remain uncontrolled.
Is diabetic neuropathy painful?
Not always. Some people experience significant burning or stabbing pain, while others feel only numbness with no pain at all. Paradoxically, the absence of pain can be more dangerous because it means you won't notice injuries. Both presentations require medical attention and active monitoring.
What is the best diet for managing diabetic neuropathy?
No single diet has been proven to specifically treat neuropathy, but a diet that supports stable blood sugar levels is central to preventing its progression. Most physicians and registered dietitians recommend a diet rich in vegetables, whole grains, lean proteins, and healthy fats while limiting refined carbohydrates, added sugars, and alcohol. Working with a certified diabetes care and education specialist (CDCES) can help you personalize your approach.
Do I need to see a specialist for diabetic neuropathy?
Your primary care physician or endocrinologist can manage most cases of diabetic neuropathy. However, depending on your symptoms, you may be referred to a neurologist (for complex nerve pain or diagnostic workup), a podiatrist (for foot care), a cardiologist (for autonomic heart involvement), or a gastroenterologist (for gastroparesis). A multidisciplinary approach generally yields the best outcomes.
Conclusion
Diabetic neuropathy is one of the most common and consequential complications of diabetes — but it is far from inevitable. The decisions you make today about blood sugar control, physical activity, foot care, and regular medical screening directly shape your risk and your future quality of life.
If you're already experiencing symptoms, know that effective treatments exist and that working closely with your healthcare team can make a meaningful difference. If you haven't developed neuropathy yet, the window you have right now to protect your nerves is enormously valuable — don't wait for symptoms to appear.
Talk openly with your doctor about your neurological health at every diabetes visit. Ask for a foot exam. Ask about your A1C trend. Ask what your numbers mean for your long-term nerve health. You deserve specific, honest answers — and proactive care every step of the way.
Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.
Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.