
Tag: blood sugar control

  • Diabetes and Neuropathy: Protect Your Nerves Now

    Diabetes and Neuropathy: Protect Your Nerves Now

    Diabetic neuropathy is the most common complication of diabetes — and one of the most preventable if caught early enough.

    Marcus, 54, had been managing type 2 diabetes for nearly a decade. He took his metformin faithfully, watched his diet most of the time, and figured he was doing well enough. Then one morning, he noticed a strange tingling in his feet — almost like they had fallen asleep, but the feeling never fully went away. By the time he mentioned it to his doctor, the nerve damage was already measurable.

    Marcus’s story is far from unique. According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), diabetic neuropathy — nerve damage caused by prolonged high blood sugar — affects up to 50% of people with diabetes. That’s roughly 19 million Americans living with some degree of nerve damage, many of whom don’t recognize the early warning signs until significant damage has already occurred.

    In this guide, you’ll learn what diabetic neuropathy is, how to recognize it early, what causes it, and most importantly, what you can do right now to slow or prevent its progression.

    What Is Diabetic Neuropathy?

    Diabetic neuropathy is a type of nerve damage that occurs as a direct result of chronically elevated blood glucose (blood sugar) levels. Over time, high blood sugar injures the walls of the small blood vessels that supply your nerves with oxygen and nutrients. Without that support, nerves begin to malfunction and eventually die.

    This condition is classified under several types depending on which nerves are affected:

    • Peripheral neuropathy — the most common form, affecting the feet, legs, hands, and arms
    • Autonomic neuropathy — damages nerves that control your heart, bladder, stomach, and sexual organs
    • Proximal neuropathy — affects nerves in the thighs, hips, or buttocks, causing muscle weakness
    • Focal neuropathy — sudden weakness in a specific nerve or group of nerves, often in the head, torso, or leg

    According to the CDC, diabetes is the leading cause of non-traumatic lower limb amputations in the United States — and peripheral neuropathy is the primary driver of that statistic. Understanding the condition is the first step in keeping your nerves healthy for life.

    Signs and Symptoms to Watch For

    Diabetic neuropathy often develops slowly and quietly, which is why it’s frequently overlooked until it reaches a more advanced stage. Research suggests that symptoms can vary significantly from person to person depending on which nerves are affected and for how long.

    Early warning signs (peripheral neuropathy):

    • Tingling or "pins and needles" sensation in the feet or hands
    • Numbness that starts at the toes and slowly moves upward
    • Sensitivity to touch — even a bedsheet can feel painful
    • A burning or stabbing sensation, especially at night
    • Muscle cramps or weakness in the feet and legs

    Signs of more advanced neuropathy:

    • Loss of balance or coordination when walking
    • Ulcers, infections, or wounds on the feet that don’t heal
    • Nausea, vomiting, or bloating (autonomic neuropathy affecting digestion)
    • Dizziness when standing up (orthostatic hypotension)
    • Bladder problems, including incontinence or difficulty emptying the bladder
    • Sexual dysfunction in both men and women

    A landmark study published in Diabetes Care found that more than 30% of people with type 2 diabetes already show measurable nerve conduction abnormalities at the time of their initial diagnosis — before they even realize they have a problem. This highlights just how silently this condition can progress.

    Red flag: if you notice a sore, blister, or wound on your foot that you didn’t feel when it happened, that is a medical emergency. See your doctor immediately.

    Causes and Risk Factors

    The primary driver of diabetic neuropathy is sustained hyperglycemia — chronically elevated blood glucose levels. But several compounding factors accelerate the damage.

    Key risk factors include:

    • Poor blood sugar control over time — the longer your A1C stays elevated, the greater the nerve damage risk
    • Duration of diabetes — the longer you’ve had diabetes, the higher your cumulative risk
    • High blood pressure (hypertension) — damages the small vessels feeding nerves
    • Elevated triglycerides and cholesterol — worsens vascular supply to nerve tissue
    • Obesity — increases systemic inflammation and insulin resistance
    • Smoking — dramatically reduces blood flow to peripheral nerves
    • Kidney disease — impairs the body’s ability to filter toxins that can damage nerves
    • Vitamin B12 deficiency — especially important for patients on long-term metformin, which can deplete B12 levels

    According to the NIH, people who have had diabetes for 25 or more years and have consistently poor glucose control face a neuropathy risk exceeding 50%. Genetics also play a role — some individuals are more predisposed to nerve damage even with modest blood sugar elevations, which is why individual variation in outcomes is well-documented.

    If you’re managing insulin resistance alongside type 2 diabetes, understanding how these factors interact is critical. You can read more about insulin resistance and its role in blood sugar dysregulation here.

    Diagnosis: What to Expect

    If you have diabetes, your doctor should be screening you for neuropathy at least once a year. The American Diabetes Association recommends that all type 2 diabetes patients be screened for peripheral neuropathy at diagnosis, and annually thereafter.

    Common diagnostic tools include:

    • Monofilament test — a soft filament is pressed against the bottom of your foot to assess sensation. Inability to feel it suggests significant nerve loss.
    • Vibration perception test — a tuning fork or electronic device is placed on bony prominences to measure vibration sense
    • Ankle reflex testing — reduced or absent reflexes can indicate nerve damage
    • Nerve conduction studies (NCS) — measures how quickly electrical signals move through your nerves; slower speeds confirm neuropathy
    • Electromyography (EMG) — assesses the electrical activity of muscles, often paired with NCS
    • Autonomic testing — if autonomic neuropathy is suspected, specialized tests assess heart rate variability and sweat gland function

    Your doctor will also review your A1C levels, kidney function, lipid panel, and vitamin B12 levels as part of a comprehensive neuropathy workup. Clinical evidence from Johns Hopkins Medicine suggests that catching neuropathy in its earliest stages — when the tingling is just beginning — offers the greatest window for intervention.

    If you haven’t had a foot exam in the past 12 months, now is the time to schedule one.

    Treatment Options

    There is currently no treatment that fully reverses established diabetic neuropathy — but there is strong clinical evidence that slowing or halting its progression is absolutely achievable with the right management strategy.

    Blood sugar control: the cornerstone of treatment

    The landmark DCCT (Diabetes Control and Complications Trial) and UKPDS (UK Prospective Diabetes Study) both demonstrated that tight glycemic control significantly reduces the risk of developing neuropathy and slows its progression. Keeping your A1C below 7% — as recommended by the American Diabetes Association — is considered the single most effective intervention.

    Medications for pain management:

    • Pregabalin (Lyrica) and gabapentin — FDA-approved for diabetic nerve pain; help calm overactive nerve signals
    • Duloxetine (Cymbalta) — FDA-approved antidepressant that is also effective for neuropathic pain
    • Tricyclic antidepressants — often prescribed off-label for nerve pain; most physicians recommend starting with low doses
    • Topical capsaicin or lidocaine patches — used for localized pain relief without systemic side effects
    • Opioids — generally considered a last resort due to addiction risk and limited long-term efficacy

    Lifestyle-based interventions:

    • Regular aerobic exercise — clinical evidence indicates that consistent physical activity improves nerve fiber density and reduces neuropathic symptoms. Learn more about how exercise controls blood sugar in diabetes management.
    • Anti-inflammatory diet — reducing refined carbohydrates and ultra-processed foods helps stabilize blood glucose and lower systemic inflammation
    • Smoking cessation — smoking constricts blood vessels and dramatically worsens nerve oxygen supply
    • Foot care protocols — daily inspection, moisturizing, appropriate footwear, and prompt wound care are non-negotiable

    Supplements under investigation:

    Research suggests that alpha-lipoic acid — an antioxidant — may offer modest symptomatic relief for diabetic neuropathy, particularly when delivered intravenously. The evidence for oral supplementation is promising but not yet conclusive. Always discuss supplements with your physician before starting, especially if you’re on other medications.

    Living With Diabetic Neuropathy and Prevention Strategies

    Living with neuropathy requires daily vigilance, especially when it comes to your feet. People with significant peripheral neuropathy often cannot feel cuts, blisters, or pressure sores — which means small injuries can escalate into serious infections without any pain signal to alert you.

    Daily foot care essentials:

    • Inspect both feet every day — use a mirror or ask someone for help if needed
    • Wash feet in lukewarm (not hot) water and dry thoroughly between the toes
    • Apply moisturizer to the tops and bottoms of your feet, but not between the toes
    • Wear well-fitting, cushioned shoes — never walk barefoot, indoors or outdoors
    • Check the inside of shoes before putting them on for any foreign objects
    • Trim toenails straight across and file sharp edges — or have a podiatrist do it

    Prevention strategies for those not yet diagnosed with neuropathy:

    • Keep your A1C within your target range — every percentage point matters
    • Control blood pressure and cholesterol aggressively
    • Get your feet examined by a podiatrist at least once a year
    • Ask your doctor to check your B12 levels annually, especially if you take metformin
    • Limit alcohol consumption — excessive drinking can directly damage nerves independent of blood sugar levels
    • Prioritize quality sleep — poor sleep is linked to worsened blood sugar control and increased inflammation, both of which accelerate nerve damage

    Research published in the New England Journal of Medicine confirmed that intensive lifestyle intervention — including regular exercise and sustained weight loss — reduced the incidence of neuropathy in adults with type 2 diabetes, reinforcing that these habits are genuine disease-modifying strategies.

    When to Call Your Doctor — Emergency Signs

    Most neuropathy symptoms can be managed in an outpatient setting, but some situations require prompt or emergency medical attention.

    Call your doctor immediately if you notice:

    • Any wound, sore, or blister on your foot that is not healing within a few days
    • Redness, warmth, or swelling in the foot that is spreading
    • A wound that has become darker, has an odor, or shows signs of infection
    • Sudden severe pain or loss of sensation in a new area
    • Dizziness or fainting when you stand up (possible autonomic neuropathy)
    • New or worsening bladder or bowel problems

    Go to the emergency room if:

    • A foot wound is visibly infected and accompanied by fever or chills
    • You experience sudden loss of vision, severe chest pain, or inability to speak (these may signal diabetic complications beyond neuropathy)

    At your next routine appointment, tell your doctor:

    • Any new tingling, numbness, or burning sensations, even if mild
    • Any changes in your ability to tolerate heat or cold in your extremities
    • Any digestive symptoms, dizziness, or sexual changes that could suggest autonomic involvement

    Frequently Asked Questions

    Can diabetic neuropathy be reversed?
    In most cases, established nerve damage cannot be fully reversed. However, clinical evidence strongly indicates that halting its progression — and sometimes improving mild symptoms — is achievable with tight blood sugar control, lifestyle changes, and appropriate medical treatment. Early intervention offers the best outcomes.

    How fast does diabetic neuropathy progress?
    Progression varies significantly from person to person. In individuals with well-controlled blood sugar and healthy lifestyle habits, progression can be very slow or effectively halted. In those with chronically elevated A1C, high blood pressure, and smoking history, damage can advance noticeably within a few years.

    Does everyone with diabetes develop neuropathy?
    No. While the risk is substantial, not every person with diabetes will develop neuropathy. Risk is strongly tied to duration of diabetes, quality of blood sugar control, and the presence of other complications like hypertension and high cholesterol. Good management dramatically reduces your personal risk.

    Is the tingling in my feet always neuropathy?
    Not necessarily. Other conditions — including vitamin B12 deficiency, hypothyroidism, pinched nerves, and peripheral artery disease — can cause similar symptoms. Your doctor will perform tests to determine the actual cause. Never assume and always seek a proper evaluation.

    Can pain medications cure diabetic neuropathy?
    No. Medications like pregabalin, duloxetine, and gabapentin treat the pain symptoms of neuropathy, but they do not address the underlying nerve damage. The only way to address the root cause is through sustained blood sugar control and cardiovascular risk management.

    Conclusion

    Diabetic neuropathy is serious — but it is not inevitable. The choices you make every day about blood sugar management, physical activity, foot care, and medical follow-up directly shape whether this complication remains a distant risk or becomes a daily reality.

    If you’ve noticed any tingling, numbness, or burning in your extremities, don’t wait. The earlier neuropathy is identified, the more effectively it can be managed. And if you haven’t been formally screened yet, bring it up at your very next appointment.

    Your nerves are quietly doing critical work every second of every day. With the right information and the right medical team behind you, keeping them healthy is absolutely within reach.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Insulin Resistance: Signs, Causes & How to Reverse It

    Insulin Resistance: Signs, Causes & How to Reverse It

    Understanding insulin resistance is one of the most important steps you can take to protect your long-term metabolic health — and millions of Americans have it without knowing.

    Marcus, 47, had been feeling exhausted after every meal for years. His doctor told him his blood sugar was "borderline" and that he should "watch what he eats." But nobody explained why his body was struggling — or that he was already in the early stages of a process that affects an estimated 88 million American adults, according to the CDC.

    That process is called insulin resistance, and it sits at the very heart of type 2 diabetes management. If you have been told your blood sugar is slightly elevated, or that you have prediabetes, or if you are simply trying to understand how your body handles glucose, this guide is written for you.

    You will learn exactly what insulin resistance is, how to recognize its warning signs, what drives it, how physicians diagnose and treat it, and — most importantly — what concrete, evidence-based steps you can take starting today to support your metabolic health and reduce your risk of progressing to type 2 diabetes.

    What Is Insulin Resistance?

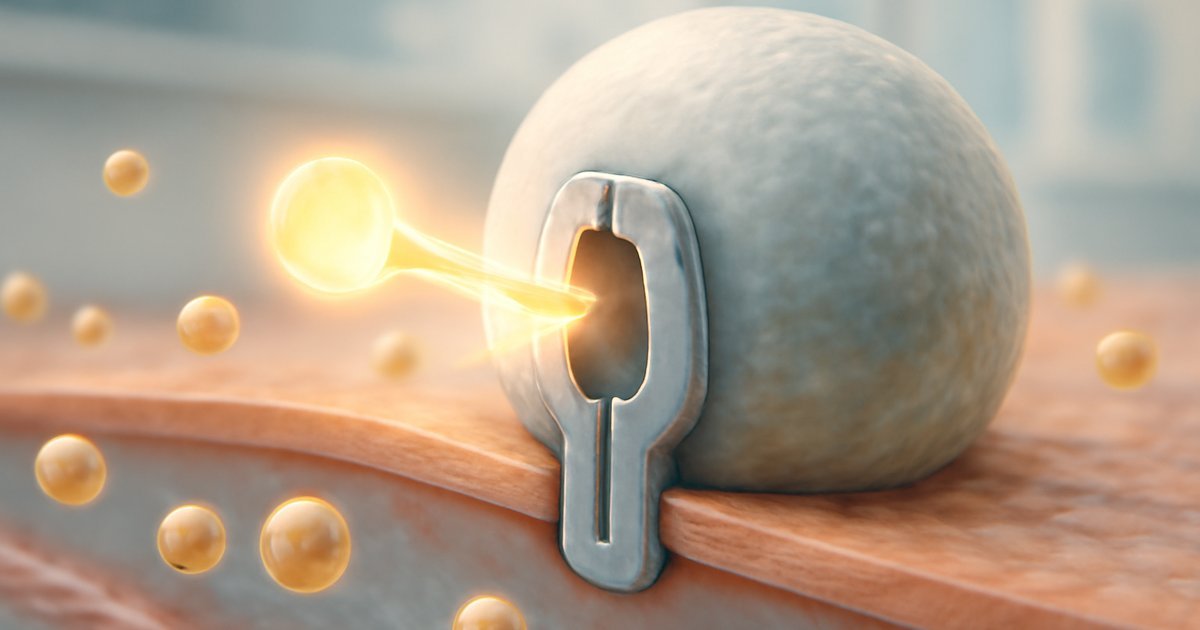
    Insulin is a hormone produced by the pancreas. Its primary job is to act like a key — unlocking your muscle, liver, and fat cells so that glucose (sugar from food) can enter and be used for energy.

    When you develop insulin resistance, those cellular "locks" stop responding normally to the insulin key. Your cells essentially ignore the signal. In response, your pancreas works harder and pumps out more insulin to compensate. For a while, this keeps your blood sugar relatively normal — but it puts enormous strain on your pancreas.

    Over time, the pancreas can no longer keep up with the demand. Blood sugar begins to rise. First you develop prediabetes. Then, if left unaddressed, type 2 diabetes.

    According to the NIH, approximately 1 in 3 American adults has prediabetes — the direct result of insulin resistance — and more than 80% of them are unaware of it. This makes insulin resistance one of the most underdiagnosed metabolic conditions in the United States.

    Signs and Symptoms of Insulin Resistance

    One of the challenges with insulin resistance is that it often develops silently. Many people feel "fine" for years while the condition progresses. However, there are early warning signs worth knowing.

    Early and common signs include:

    • Persistent fatigue, especially after carbohydrate-rich meals
    • Difficulty losing weight, particularly around the abdomen
    • Intense sugar or carbohydrate cravings
    • Increased hunger shortly after eating
    • Brain fog or difficulty concentrating
    • Elevated blood pressure or borderline-high triglycerides
    • Skin changes: dark, velvety patches in skin folds (a condition called acanthosis nigricans), commonly found on the neck, armpits, or groin

    Signs that may indicate progression toward prediabetes or type 2 diabetes:

    • Frequent urination, especially at night
    • Increased thirst
    • Slow-healing cuts or bruises
    • Tingling or numbness in hands or feet
    • Blurry vision
    • Recurring infections (urinary tract, skin, or yeast infections)

    A landmark study published in the journal Diabetes Care found that people with insulin resistance often show abnormal lipid panels — specifically high triglycerides and low HDL (good) cholesterol — years before blood sugar levels become clinically elevated. This is why your doctor may flag a routine cholesterol panel as an early metabolic warning sign.

    Causes and Risk Factors

    Insulin resistance does not have a single cause. Research suggests it develops from a combination of genetic, lifestyle, and environmental factors working together over time.

    Genetic and biological factors:

    • Family history of type 2 diabetes
    • Ethnicity: Black, Hispanic, Native American, and Asian American adults face disproportionately higher risk, according to the CDC
    • Polycystic ovary syndrome (PCOS), which is strongly linked to insulin resistance in women
    • History of gestational diabetes
    • Age: risk increases significantly after 45

    Lifestyle and environmental factors:

    • Physical inactivity — muscle cells that are regularly exercised are significantly more insulin-sensitive
    • Excess body fat, particularly visceral fat (fat stored deep around internal organs in the abdomen)
    • Diets high in ultra-processed foods, refined carbohydrates, and added sugars
    • Chronic sleep deprivation — research from the University of Chicago found that just four nights of poor sleep can reduce insulin sensitivity by as much as 25%
    • Chronic stress and elevated cortisol levels
    • Smoking

    It is worth emphasizing: having risk factors does not mean you are destined to develop diabetes. This condition is highly modifiable, and early action makes a measurable difference. For more on how physical activity directly lowers blood sugar, see our guide on Exercise and Diabetes: How Physical Activity Controls Blood Sugar.

    Diagnosis: What to Expect

    Insulin resistance itself is not directly tested with a single definitive lab value in standard clinical practice. Instead, physicians typically identify it through a combination of measurements and screening tests.

    Key diagnostic tools include:

    • Fasting Blood Glucose: A blood sample taken after at least 8 hours without food. A result of 100–125 mg/dL indicates prediabetes; 126 mg/dL or higher on two occasions indicates type 2 diabetes.
    • Hemoglobin A1C (HbA1c): Reflects your average blood sugar over the past 2–3 months. A result of 5.7–6.4% indicates prediabetes; 6.5% or higher indicates diabetes.
    • Fasting Insulin Level: Some physicians order this alongside glucose to calculate a measure of insulin resistance called HOMA-IR (Homeostatic Model Assessment of Insulin Resistance). This is not universally standardized but can be clinically informative.
    • Lipid Panel: High triglycerides (above 150 mg/dL) and low HDL are common metabolic markers associated with insulin resistance.
    • Blood Pressure Measurement: Hypertension frequently co-occurs with insulin resistance as part of metabolic syndrome.
    • Waist Circumference: The American Heart Association considers a waist of more than 40 inches in men or 35 inches in women a significant clinical risk marker.

    The American Diabetes Association recommends that adults aged 35 to 70 who are overweight or have additional risk factors get screened for prediabetes and diabetes during routine care. If your results are borderline or if you have symptoms, do not wait — advocate for screening at your next appointment.

    Treatment Options for Insulin Resistance

    The good news is that insulin resistance is one of the most treatable metabolic conditions, particularly when caught early. Clinical evidence strongly supports both lifestyle-based approaches and, when appropriate, pharmacological intervention.

    Conventional Medical Treatments:

    Metformin is the most widely studied medication for insulin resistance and prediabetes. The landmark NIH-funded Diabetes Prevention Program (DPP) trial demonstrated that metformin reduced the risk of progressing from prediabetes to type 2 diabetes by 31% over three years. Your physician will determine whether medication is appropriate for your individual situation.

    For people who have already developed type 2 diabetes alongside insulin resistance, a growing class of medications — including GLP-1 receptor agonists and SGLT2 inhibitors — have shown significant benefits not only for blood sugar control but also for cardiovascular and kidney protection, according to the American Diabetes Association’s 2025–2026 Standards of Care.

    Lifestyle Modifications (First-Line Approach):

    The same Diabetes Prevention Program trial found that structured lifestyle change — specifically, 150 minutes per week of moderate exercise and a 5–7% reduction in body weight — reduced the risk of progressing to type 2 diabetes by an impressive 58%. That outperformed metformin alone.

    • Dietary changes: Clinical evidence indicates that reducing refined carbohydrates and added sugars, increasing dietary fiber, and prioritizing lean proteins and healthy fats meaningfully improves insulin sensitivity. The Mediterranean diet and low-glycemic-index approaches have both shown strong results in clinical trials.
    • Physical activity: Both aerobic exercise (brisk walking, cycling, swimming) and resistance training independently improve insulin sensitivity. Research suggests that even a 10-minute walk after meals can reduce post-meal blood sugar spikes.
    • Weight management: Losing even 5–10% of body weight can produce clinically significant improvements in insulin sensitivity, according to the CDC’s National Diabetes Prevention Program.
    • Sleep optimization: Prioritizing 7–9 hours of quality sleep per night is an underappreciated metabolic intervention. Poor sleep is consistently linked to worsened insulin resistance. Our article on Weight Loss and Sleep: Why Rest Is Key to Losing Fat offers helpful practical strategies.
    • Stress management: Chronic stress elevates cortisol, which directly counteracts insulin signaling. Practices such as mindfulness, structured breathing, and regular physical activity all help moderate cortisol levels.

    Living With Insulin Resistance: Day-to-Day Management

    Managing insulin resistance is a long-term commitment — but it does not have to feel overwhelming. Small, consistent habits compound into significant metabolic change over months and years.

    Practical daily strategies:

    • Eat meals at consistent times to support stable blood sugar rhythms
    • Pair carbohydrates with protein, fiber, or healthy fat at every meal to blunt glucose spikes
    • Aim for at least 30 minutes of moderate movement most days — even breaking it into three 10-minute walks counts
    • Limit alcohol, which can interfere with glucose regulation and insulin signaling
    • Monitor your progress: ask your doctor to recheck your A1C or fasting glucose every 3–6 months if you are managing prediabetes
    • Keep a simple food and activity log — research suggests that self-monitoring improves outcomes

    If you are managing additional weight-related challenges alongside insulin resistance, our article on Weight Loss After 40: Why It’s Harder and What Works addresses the unique metabolic factors that come into play as you age.

    Remember: this varies from person to person. What works well for one individual may need to be adjusted for another based on medications, other health conditions, preferences, and genetics. Your care team is your most important partner in this process.

    When to Call Your Doctor — Emergency Signs

    Most of the time, insulin resistance and prediabetes are managed through scheduled appointments. However, certain symptoms require urgent or emergency attention.

    Call your doctor promptly if you notice:

    • Blood sugar readings consistently above 200 mg/dL (if you are monitoring at home)
    • Unexplained weight loss
    • Progressive numbness, tingling, or pain in feet or hands
    • Worsening blurry vision
    • Recurring infections that are difficult to resolve

    Seek emergency care immediately if you experience:

    • Extreme thirst combined with confusion or disorientation
    • Fruity-smelling breath and nausea or vomiting (possible signs of diabetic ketoacidosis)
    • Rapid breathing, severe abdominal pain
    • Loss of consciousness or inability to be awakened
    • Blood sugar above 300 mg/dL with symptoms

    These symptoms may indicate a serious complication requiring immediate medical intervention. Do not wait to see if they resolve on their own.

    Frequently Asked Questions About Insulin Resistance

    Can insulin resistance be reversed?
    Research suggests that insulin resistance can be significantly improved — and in many cases brought back to normal ranges — through sustained lifestyle changes, particularly weight loss, regular exercise, and dietary modification. The word "reversed" should be understood carefully: in most cases it means achieving and maintaining normal blood sugar levels, not that your underlying genetic susceptibility disappears. Consistency over time is what drives lasting results.

    Is insulin resistance the same as type 2 diabetes?
    No — but insulin resistance is typically the underlying mechanism that leads to type 2 diabetes when left unmanaged. You can have insulin resistance and prediabetes without having type 2 diabetes. Early identification and intervention at the prediabetes stage can prevent or significantly delay the development of diabetes.

    What foods are worst for insulin resistance?
    Clinical evidence indicates that refined carbohydrates (white bread, white rice, sugary cereals), sugar-sweetened beverages, and ultra-processed snack foods cause the largest and fastest blood sugar spikes, worsening insulin resistance over time. Most physicians and registered dietitians recommend prioritizing whole grains, vegetables, legumes, lean proteins, and healthy fats.

    Can thin or normal-weight people have insulin resistance?
    Yes. While excess body fat — particularly visceral fat — is a major driver, insulin resistance can occur in individuals with a normal BMI, particularly those who are sedentary, have a family history of diabetes, or carry metabolic risk factors. This is sometimes called "metabolically unhealthy normal weight." Lab testing is the only reliable way to identify it.

    How long does it take to improve insulin sensitivity?
    This varies from person to person, but clinical evidence indicates that meaningful improvements in insulin sensitivity can occur within 2–4 weeks of consistent aerobic exercise and dietary changes. More significant improvements in A1C or fasting glucose are typically measurable within 3–6 months of sustained lifestyle change.

    Taking Control of Your Metabolic Health

    Insulin resistance is not a life sentence — it is a signal. Your body is telling you that something needs to change, and the evidence is clear that change is possible at almost any stage of the process.

    Whether you are managing prediabetes, recently diagnosed with type 2 diabetes, or simply trying to understand a borderline lab result, knowledge is your most powerful tool. Work with your physician to get the right tests, understand your numbers, and build a plan that fits your real life.

    Small daily choices — a walk after dinner, choosing whole grains over refined ones, getting to bed an hour earlier — add up to measurable metabolic improvements over time. You do not have to do everything perfectly. You just have to keep moving in the right direction, consistently, with qualified medical support by your side.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.
  • Exercise and Diabetes: How Physical Activity Controls Blood Sugar

    Exercise and Diabetes: How Physical Activity Controls Blood Sugar

    Physical activity is one of the most powerful — and underused — tools for managing type 2 diabetes every single day.

    Marcus, 54, had been managing type 2 diabetes for six years. He took his metformin faithfully, watched his carbs, and checked his blood sugar regularly. But his A1C — a key measure of average blood sugar over three months — kept hovering above 8%. Then his endocrinologist suggested something simple: a 20-minute walk after dinner, five nights a week. Within three months, his A1C dropped to 7.1%.

    His story isn't unique. According to the CDC, more than 38 million Americans are living with diabetes, and the vast majority have type 2. What many don't realize is that exercise and diabetes management are deeply connected — not as an optional add-on, but as a clinically proven strategy for lowering blood sugar, improving insulin sensitivity, and reducing long-term complications.

    In this guide, you'll learn exactly how physical activity affects blood sugar, which types of exercise work best, how to stay safe while working out with diabetes, and practical tips for building a sustainable routine.

    Why Exercise Matters So Much for Diabetes Management

    Type 2 diabetes is characterized by insulin resistance — a condition where your body's cells don't respond well to insulin, the hormone that allows glucose (sugar) to enter cells for energy. As a result, glucose builds up in the bloodstream, leading to high blood sugar levels.

    Exercise directly addresses this problem. When your muscles contract during physical activity, they can absorb glucose from the bloodstream without needing insulin. This makes exercise one of the few tools that lowers blood sugar independently of insulin function.

    A landmark meta-analysis published through NIH databases found that structured exercise programs reduced A1C levels by an average of 0.67% in adults with type 2 diabetes — comparable to the effect of some oral medications. When combined with dietary changes, the impact is even more significant.

    Beyond blood sugar control, regular physical activity helps reduce cardiovascular risk (heart disease is the leading cause of death in people with diabetes), supports weight management, lowers blood pressure, and improves mood and energy levels — all critical elements of long-term diabetes wellness.

    How Exercise Lowers Blood Sugar: The Physiology

    Understanding what happens inside your body during exercise can help you make smarter choices about your routine.

    During aerobic exercise (like walking, cycling, or swimming), your muscles increase their demand for glucose. They pull sugar directly from your bloodstream and also stimulate your cells to become more sensitive to insulin — an effect that can last 24 to 72 hours after a single workout session.

    During resistance training (like lifting weights or using resistance bands), you build lean muscle mass. Muscle tissue is metabolically active — meaning it burns more glucose at rest than fat tissue does. More muscle means better long-term glucose uptake, even when you're not exercising.

    Research from the American Diabetes Association (ADA) indicates that combining both aerobic and resistance exercise produces significantly greater improvements in A1C and insulin sensitivity than either type alone.

    It's also worth noting that exercise has an acute (immediate) blood sugar-lowering effect. Many people with type 2 diabetes see their blood sugar drop 20 to 50 points during or right after moderate aerobic activity — though this varies from person to person depending on fitness level, medication, and baseline glucose.

    Best Types of Exercise for Diabetes Control

    Not all exercise is created equal when it comes to blood sugar management. Here's what clinical evidence supports:

    Aerobic Exercise

    The ADA recommends at least 150 minutes of moderate-intensity aerobic activity per week for adults with type 2 diabetes. That breaks down to about 30 minutes, five days a week — or three 10-minute walks spread throughout the day, which research suggests may be equally effective.

    • Brisk walking — the most accessible option; proven to lower post-meal blood sugar
    • Cycling (stationary or outdoor) — low impact, easy on joints
    • Swimming — ideal for those with neuropathy or joint pain
    • Dancing — enjoyable, sustainable, and effective
    • Water aerobics — gentle and effective for older adults

    Moderate intensity means you're breathing harder than usual but can still hold a conversation. A good target is reaching 50–70% of your maximum heart rate.

    Resistance Training

    Clinical evidence from Johns Hopkins Medicine suggests that resistance training two to three times per week significantly improves insulin sensitivity and helps maintain muscle mass — which tends to decline with age and can worsen glucose control.

    • Free weights or machines at the gym
    • Resistance bands (affordable and home-friendly)
    • Bodyweight exercises (squats, lunges, push-ups)
    • Yoga and Pilates (also improve flexibility and stress levels)

    High-Intensity Interval Training (HIIT)

    Emerging research suggests that HIIT — short bursts of intense effort alternated with rest — can be highly effective for improving blood sugar and cardiovascular fitness, even in less time than traditional aerobic workouts. However, HIIT may cause blood sugar spikes in some individuals, particularly those on insulin. Always consult your doctor before starting HIIT if you have diabetes.

    Exercise Safety: What Every Diabetic Should Know

    Exercising with diabetes is generally safe — and strongly encouraged — but requires some precautions to prevent dangerous blood sugar swings.

    Before You Exercise

    • Check your blood sugar before starting. Most physicians recommend checking if your glucose is below 100 mg/dL or above 250 mg/dL before exercising, as both extremes require caution.
    • If your blood sugar is below 100 mg/dL, have a small snack (such as 15 grams of carbohydrates) before beginning.
    • If your blood sugar is above 250 mg/dL with ketones present, postpone exercise and contact your healthcare provider.

    During Exercise

    • Keep fast-acting glucose sources nearby (glucose tablets, juice, or regular soda) in case of hypoglycemia — low blood sugar.
    • Stay hydrated. Dehydration can raise blood sugar levels.
    • If you feel dizzy, shaky, confused, or unusually fatigued, stop immediately and check your glucose.

    After Exercise

    • Check your blood sugar within 30 minutes of finishing.
    • Be aware of delayed hypoglycemia — blood sugar can continue to drop for up to 24 hours after intense or prolonged activity, particularly in people on insulin or certain medications.
    • Rehydrate and refuel with a balanced snack if needed.

    According to the Mayo Clinic, people with diabetic neuropathy (nerve damage in the feet) should wear proper supportive footwear during exercise and inspect their feet after every session to prevent unnoticed injuries from progressing to serious complications. For more on how diabetes affects your feet and nerves, see our related article on Diabetic Retinopathy: Protect Your Vision With Diabetes, which also covers how systemic complications affect daily life.

    Building a Sustainable Exercise Routine With Diabetes

    Starting an exercise program is exciting. Sticking with it is the real challenge. Here are evidence-based strategies to help you build lasting habits:

    Start small and build gradually. If you haven't been active, begin with 10 minutes of walking per day and add five minutes each week. Research from the Cleveland Clinic shows that even short bouts of activity — broken into three 10-minute segments — provide meaningful metabolic benefits.

    Schedule workouts like appointments. Consistency matters more than intensity. Pick specific times that work with your daily routine and treat them as non-negotiable.

    Track your blood sugar responses. Logging your glucose before and after different types of workouts helps you understand your unique patterns and optimize your routine accordingly. This connects directly with your overall diabetes management strategy, including understanding how lifestyle factors like alcohol also affect your numbers.

    Find activities you enjoy. Sustainable exercise is enjoyable exercise. Whether it's pickleball, gardening, or ballroom dancing — if you love it, you'll do it consistently.

    Work with your healthcare team. Before dramatically increasing activity levels, talk to your doctor or a certified diabetes care and education specialist (CDCES). They can help you adjust medications, set safe target blood sugar ranges for exercise, and tailor a plan to your fitness level and health status.

    Consider cardiac screening first. Because people with type 2 diabetes have elevated cardiovascular risk, the ADA recommends that those who are sedentary and over 40 discuss cardiac evaluation with their doctor before starting a vigorous exercise program.

    Exercise and Weight Management in Diabetes

    For many people with type 2 diabetes, weight management is a key goal — and exercise plays an important supporting role. While diet tends to have a stronger direct effect on weight loss, exercise is crucial for maintaining weight loss over time and preserving muscle mass during calorie restriction.

    A combination of aerobic exercise and resistance training has been shown in multiple NIH-funded studies to produce more durable improvements in body composition and metabolic health than either approach alone.

    It's worth noting, however, that exercise alone rarely produces dramatic weight loss — especially in the short term. The real metabolic magic happens when physical activity complements a thoughtful eating plan. If you're struggling with weight and diabetes, speaking with a registered dietitian familiar with diabetes can make a significant difference. You may also find our article on Weight Loss and Metabolism: What You Can Actually Change helpful for understanding the broader picture.

    When to Call Your Doctor or Seek Emergency Care

    Exercise is safe for most people with diabetes, but certain situations require immediate medical attention:

    Red flags requiring emergency care:

    • Blood sugar below 54 mg/dL that doesn't respond to glucose treatment
    • Loss of consciousness or severe confusion during or after exercise
    • Chest pain, pressure, or shortness of breath during activity
    • Severe dizziness or fainting
    • Symptoms of diabetic ketoacidosis (DKA): nausea, vomiting, fruity-smelling breath, rapid breathing

    Call your doctor soon if you notice:

    • Consistent blood sugar spikes after exercise (rather than drops)
    • Foot sores, blisters, or injuries that are slow to heal
    • Frequent hypoglycemia episodes around workout times
    • Joint pain or discomfort that limits your ability to exercise
    • Your A1C isn't improving despite consistent activity

    Frequently Asked Questions

    How quickly does exercise lower blood sugar?
    For most people with type 2 diabetes, blood sugar begins to drop within 10–20 minutes of starting moderate aerobic exercise. The full effect can last 24 to 48 hours post-workout due to improved insulin sensitivity. Individual responses vary, so monitoring your glucose before and after is the best way to understand your personal pattern.

    Is it safe to exercise if my blood sugar is high?
    It depends. Moderate exercise is generally safe if your blood sugar is between 150–250 mg/dL and you feel well. However, if your glucose is above 250 mg/dL and you have ketones in your urine, exercise can actually worsen the situation. Always follow your healthcare provider's specific guidelines for your situation.

    Can exercise replace diabetes medication?
    For some people in early-stage type 2 diabetes, significant lifestyle changes — including regular exercise and dietary modification — can reduce the need for medication. However, this is a decision that must be made with your physician. Never stop or reduce diabetes medication without medical supervision.

    What if I have neuropathy or joint pain that limits exercise?
    Low-impact options like swimming, water aerobics, chair-based exercises, and upper-body resistance training can be effective even with significant physical limitations. A physical therapist familiar with diabetes can design a safe program tailored to your abilities.

    How do I prevent low blood sugar during exercise?
    Checking your glucose before exercise, carrying fast-acting carbohydrates, avoiding exercise at peak insulin action times (if you use insulin), and working with your care team to adjust medication timing are all effective strategies. Clinical evidence suggests that exercising after meals — when blood sugar is naturally elevated — may also reduce hypoglycemia risk for many individuals.

    Conclusion

    Exercise isn't a luxury add-on for people managing diabetes — it's one of the most clinically validated tools available for improving blood sugar control, reducing A1C, and protecting long-term health. Whether you start with a 15-minute walk after dinner or a structured gym program, the key is consistency over intensity.

    Your body responds to movement in powerful ways, regardless of your age or fitness level. The research is clear: regular physical activity improves insulin sensitivity, supports heart health, aids weight management, and enhances quality of life — all areas where diabetes poses significant risk.

    Work with your healthcare team to build a plan that fits your life, monitor your blood sugar around activity, and give yourself credit for every step forward. Progress, not perfection, is what leads to lasting change.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Diabetic Retinopathy: Protect Your Vision With Diabetes

    Diabetic Retinopathy: Protect Your Vision With Diabetes

    Millions of Americans with diabetes are unknowingly putting their eyesight at risk — and a simple annual eye exam could change everything.

    Introduction

    Margaret, 54, had managed her type 2 diabetes for over a decade. She took her metformin faithfully, watched her carb intake, and showed up for most of her primary care appointments. But she hadn’t seen an eye doctor in four years — because her vision seemed just fine.

    Then, almost overnight, she noticed blurry patches in her right eye. By the time she finally saw an ophthalmologist, she had moderate diabetic retinopathy in both eyes and was at serious risk of permanent vision loss.

    Margaret’s story is not unusual. According to the CDC, diabetic retinopathy is the leading cause of new blindness among American adults aged 20 to 74. Yet research suggests that up to 90% of diabetes-related vision loss is preventable with timely screening and proper blood sugar management.

    In this guide, you’ll learn exactly what diabetic retinopathy is, how it develops, what symptoms to watch for, and — most importantly — how you can protect your vision starting today.

    What Is Diabetic Retinopathy?

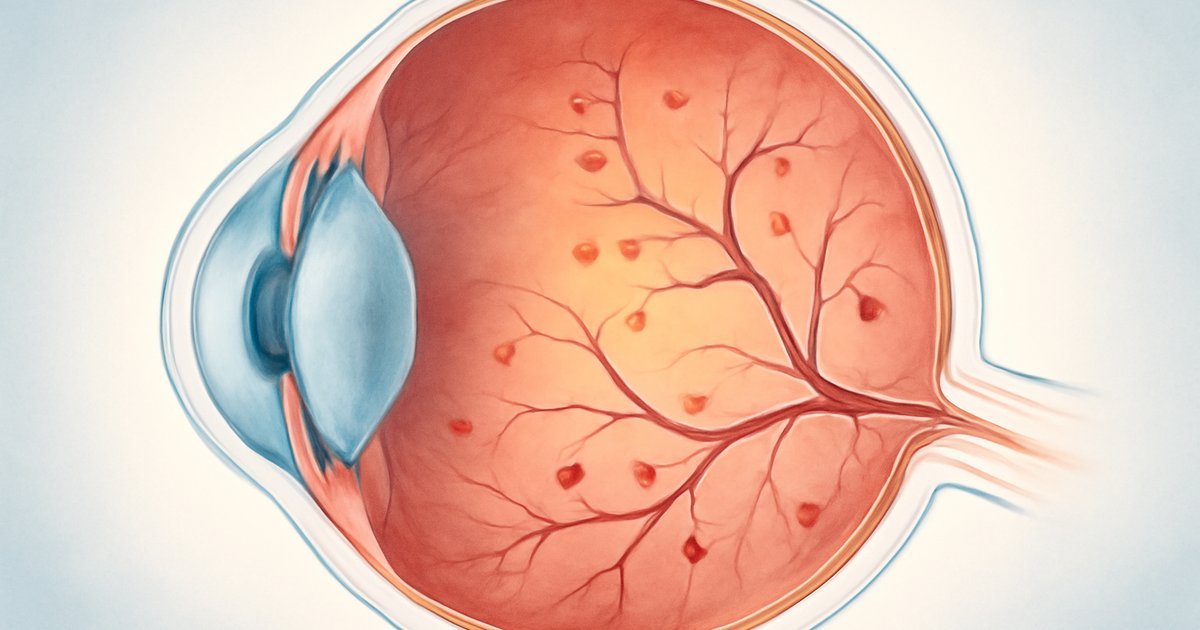
    Diabetic retinopathy is a diabetes complication that damages the blood vessels in the retina — the thin, light-sensitive layer of tissue at the back of your eye. When blood sugar levels remain chronically elevated, those tiny vessels can swell, leak fluid, or grow abnormally, all of which can distort or destroy your vision over time.

    The condition progresses in two main stages. Non-proliferative diabetic retinopathy (NPDR) is the earlier stage, where blood vessels in the retina weaken and may leak. Proliferative diabetic retinopathy (PDR) is the advanced stage, where new, abnormal blood vessels grow on the surface of the retina — a process called neovascularization — which dramatically increases the risk of severe vision loss or detachment of the retina.

    According to the National Eye Institute (NEI), an arm of the NIH, approximately 7.7 million Americans have diabetic retinopathy, and that number is projected to reach nearly 14.6 million by 2050. Both type 1 and type 2 diabetes can cause the condition, though the longer you’ve lived with diabetes, the higher your risk becomes.

    What makes diabetic retinopathy particularly dangerous is that it causes no pain and minimal early symptoms — meaning most people don’t realize anything is wrong until significant damage has already occurred.

    Signs and Symptoms: What to Watch For

    Because diabetic retinopathy often progresses silently, many people only notice symptoms once the disease has advanced. Understanding the full spectrum of warning signs — from subtle early changes to urgent red flags — can help you seek care at the right time.

    Early signs (may be subtle or absent):

    • Slightly blurry vision that comes and goes
    • Difficulty reading fine print or seeing close objects
    • Colors appearing washed out or less vibrant
    • Small dark spots or "floaters" in your field of vision
    • Difficulty seeing well in low-light conditions

    Advanced signs (require urgent medical attention):

    • Sudden or rapid vision loss in one or both eyes
    • A large number of new floaters appearing suddenly
    • Flashes of light in your vision
    • A dark curtain or shadow appearing across part of your visual field
    • Severe blurring that does not improve

    A 2021 clinical study published through the American Academy of Ophthalmology found that nearly 40% of people with type 2 diabetes who were newly diagnosed with retinopathy reported having experienced no noticeable visual symptoms before their diagnosis. This underscores why routine eye exams are so critical — your eyes may be changing even when your vision feels normal.

    Causes and Risk Factors

    The root cause of diabetic retinopathy is sustained high blood sugar. Over time, excess glucose in the bloodstream damages the walls of the small blood vessels that supply the retina. These weakened vessels may swell, develop tiny bulges called microaneurysms, or leak blood and fluid into surrounding retinal tissue.

    But not every person with diabetes develops retinopathy at the same rate or severity. Several factors can significantly increase your risk:

    • Duration of diabetes: The longer you’ve had diabetes, the higher your cumulative risk. The NIH reports that nearly all people with type 1 diabetes and more than 60% of those with type 2 diabetes will develop some degree of retinopathy after 20 years.
    • Poor blood sugar control: Chronically elevated A1C levels (a measure of average blood sugar over roughly three months) are one of the strongest predictors of retinopathy progression.
    • High blood pressure (hypertension): Elevated blood pressure compounds damage to retinal blood vessels and is extremely common among people with diabetes.
    • High cholesterol: Elevated LDL cholesterol increases the likelihood of hard exudates — fatty deposits — forming in the retina.
    • Pregnancy: Gestational diabetes or pre-existing diabetes during pregnancy can accelerate retinopathy development.
    • Smoking: Tobacco use constricts blood vessels and worsens microvascular complications throughout the body, including the eyes.
    • Ethnicity: According to the CDC, African Americans, Hispanic/Latino Americans, and Native Americans face disproportionately higher rates of diabetic eye disease.
    • Kidney disease: Diabetic nephropathy (kidney damage from diabetes) often occurs alongside retinopathy, as both stem from the same microvascular damage mechanisms.

    It’s worth noting that individual variation plays a significant role here. Two people with identical A1C levels and the same duration of diabetes may experience very different rates of retinal damage — which is why personalized care with your healthcare team matters so much.

    Diagnosis: What to Expect at the Eye Doctor

    Diagnosing diabetic retinopathy requires a comprehensive dilated eye exam — a procedure in which your eye doctor uses special drops to widen (dilate) your pupils, giving them a clear view of your retina and the blood vessels within it. This exam is painless, though your vision may remain blurry for a few hours afterward.

    Here’s what the diagnostic process typically involves:

    • Visual acuity test: A standard eye chart test to measure how well you see at various distances.
    • Dilated fundus examination: The doctor uses a special lens to examine the retina, optic nerve, and blood vessels directly.
    • Optical coherence tomography (OCT): A non-invasive imaging scan that produces detailed cross-section images of the retina, allowing detection of swelling (macular edema) and structural changes.
    • Fluorescein angiography: A dye is injected into the arm and photographs track how it flows through the retinal blood vessels, revealing leaks or abnormal growth areas.

    The American Diabetes Association (ADA) recommends that adults with type 2 diabetes get a dilated eye exam at the time of diagnosis and annually thereafter. People with type 1 diabetes should begin annual exams within five years of diagnosis. If retinopathy is detected, your ophthalmologist may recommend more frequent monitoring — sometimes every three to six months.

    If you’ve been skipping these exams, you’re far from alone. Research suggests that fewer than half of Americans with diabetes receive the recommended annual dilated eye exams. Consistent blood sugar monitoring goes hand in hand with eye exams as a cornerstone of diabetes management.

    Treatment Options for Diabetic Retinopathy

    The good news is that diabetic retinopathy responds well to treatment, especially when caught early. Your treatment plan will depend on the stage of the disease and whether diabetic macular edema (swelling at the center of the retina) is present.

    1. Blood sugar and blood pressure management
    For early-stage retinopathy, the most effective "treatment" is tighter control of blood glucose and blood pressure. Clinical evidence from the landmark DCCT (Diabetes Control and Complications Trial) and UKPDS (UK Prospective Diabetes Study) showed that intensive blood sugar control reduced the risk of retinopathy progression by 50–76% compared to conventional management. Most physicians recommend an A1C target below 7% for most adults with diabetes, though your personal target may vary.

    2. Anti-VEGF injections
    For moderate to severe retinopathy or diabetic macular edema, anti-VEGF (vascular endothelial growth factor) therapy is now the standard of care. Medications such as ranibizumab, aflibercept, and bevacizumab are injected directly into the eye to block the growth of abnormal blood vessels and reduce leakage. Clinical trials have shown these injections can significantly stabilize and even improve vision in many patients.

    3. Laser photocoagulation therapy
    Laser treatment has been used for decades to seal leaking blood vessels and shrink abnormal ones. Focal laser treatment targets specific leaking vessels, while panretinal photocoagulation (PRP) treats the peripheral retina to reduce the drive for abnormal vessel growth. While laser therapy is less commonly used as a first-line treatment since anti-VEGF injections became available, it remains an important option in many cases.

    4. Vitrectomy surgery
    In advanced cases where there is bleeding into the vitreous (the gel-like substance filling the eye) or a retinal detachment, a surgical procedure called vitrectomy may be necessary. The surgeon removes the vitreous and any scar tissue, and in some cases reattaches the retina. According to the NIH, vitrectomy significantly improves visual outcomes in patients with severe proliferative diabetic retinopathy when performed in a timely manner.

    5. Lifestyle modifications as complements
    While not a replacement for medical treatment, lifestyle changes provide meaningful support for retinopathy management. Regular physical activity, a diet low in refined carbohydrates and high in antioxidant-rich vegetables, smoking cessation, and stress reduction all contribute to better blood sugar control and vascular health. Emerging research also suggests that omega-3 fatty acids and certain antioxidant nutrients like lutein and zeaxanthin may support retinal health, though clinical evidence is still evolving.

    Living With Diabetic Retinopathy and Preventing Progression

    A diagnosis of diabetic retinopathy doesn’t have to mean inevitable vision loss. With proactive management and the right support team, many people successfully preserve their vision for years — and in some cases, decades.

    Here are practical, evidence-informed strategies for day-to-day management:

    • Keep your A1C in your target range. Work with your doctor to find the right A1C goal for your individual situation. Even a modest reduction in A1C — say, from 9% to 7.5% — can meaningfully slow retinopathy progression.
    • Control your blood pressure. The ADA recommends a blood pressure target of less than 130/80 mmHg for most adults with diabetes. High blood pressure dramatically accelerates retinal vessel damage.
    • Manage cholesterol levels. Elevated LDL cholesterol is linked to harder-to-treat retinal deposits. Statins and dietary changes are commonly recommended.
    • Never skip your annual eye exam. Even if your vision feels perfectly fine. Even if you’ve had no symptoms. This single habit may be the most important thing you can do for your long-term eye health.
    • Quit smoking — or never start. Smoking significantly worsens every diabetes complication, including retinopathy. Speak with your doctor about cessation resources.
    • Tell your eye doctor about all your medications. Some medications can affect the eyes, and your ophthalmologist needs a full picture of your health.
    • Consider adaptive aids if needed. If vision loss affects daily activities, occupational therapists and low-vision specialists can help you adapt and maintain independence.

    It’s also worth connecting your eye care with your broader diabetes management. Your ophthalmologist and endocrinologist or primary care physician should be communicating about your case — don’t hesitate to ask them to coordinate. Managing conditions like diabetes and heart disease risk alongside retinopathy requires a team-based approach.

    When to Call Your Doctor — Emergency Signs

    Some vision changes related to diabetic retinopathy require immediate medical attention. Do not wait for a scheduled appointment if you experience any of the following:

    • Sudden loss of vision in one or both eyes
    • A sudden shower of new floaters or flashes of light
    • A dark shadow, curtain, or veil appearing across any part of your vision
    • Vision that becomes rapidly and severely blurry without an obvious cause

    These symptoms may indicate a vitreous hemorrhage (bleeding inside the eye), retinal detachment, or acute macular edema — all of which are ophthalmologic emergencies that require same-day evaluation. Call your ophthalmologist immediately or go to an emergency room if you cannot reach your eye doctor.

    At your next routine visit — even if no emergencies occur — consider discussing the following with your doctor:

    • Your current A1C and whether your blood sugar management plan needs adjustment
    • Your blood pressure and cholesterol numbers and targets
    • Whether you’re due for a dilated eye exam
    • Any changes in your vision, however minor they may seem
    • Whether lifestyle changes could further reduce your retinopathy risk

    Alcohol use is another factor worth discussing — it can affect blood sugar unpredictably. You can learn more in our detailed overview of how alcohol affects blood sugar in diabetes.

    Frequently Asked Questions

    Can diabetic retinopathy be reversed?
    In some cases, early-stage diabetic retinopathy can partially improve with tighter blood sugar control. However, more advanced stages typically cannot be fully reversed — the goal becomes halting progression and preserving remaining vision. Anti-VEGF injections have shown the ability to improve vision in many patients with diabetic macular edema, but results vary from person to person.

    How fast does diabetic retinopathy progress?
    Progression varies widely depending on individual factors like blood sugar control, blood pressure, duration of diabetes, and genetics. Some people remain in the early non-proliferative stage for many years with minimal change, while others progress more rapidly — especially without consistent medical management.

    Can I develop diabetic retinopathy if my blood sugar is well controlled?
    Research suggests that good blood sugar control significantly reduces risk, but does not eliminate it entirely. Some individuals develop retinopathy even with tight glucose management, particularly if they have other risk factors like hypertension or a long duration of diabetes. This is exactly why annual eye exams remain essential even when your A1C is in range.

    Is diabetic retinopathy the same as diabetic macular edema?
    No — but they’re closely related. Diabetic macular edema (DME) is a specific complication of diabetic retinopathy in which fluid leaks into the macula, the central part of the retina responsible for sharp, detailed vision. DME can occur at any stage of retinopathy and is a leading cause of vision loss in people with diabetes.

    Do anti-VEGF injections hurt?
    Most patients find anti-VEGF eye injections less painful than anticipated. The eye is numbed with anesthetic drops before the procedure, and the injection itself typically takes only seconds. Some patients experience mild pressure or discomfort during or after the injection, but severe pain is uncommon. If you have concerns, discuss them openly with your ophthalmologist.

    Conclusion

    Diabetic retinopathy is one of the most serious — and most preventable — complications of diabetes. The science is clear: consistent blood sugar control, blood pressure management, and annual dilated eye exams are your most powerful tools for protecting your vision.

    If you’ve been putting off an eye exam, let Margaret’s story be your reminder. Vision loss doesn’t announce itself with early warning signs. But the good news is that you have the ability to stay ahead of it — with the right habits, the right care team, and the right information.

    Talk to your primary care physician or endocrinologist about coordinating care with an ophthalmologist, and don’t leave your next appointment without asking about your eye health. Your future self will thank you.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Diabetes and Alcohol: What Every Diabetic Must Know

    Diabetes and Alcohol: What Every Diabetic Must Know

    Diabetes and Alcohol: What Every Diabetic Must Know

    Understanding how alcohol interacts with blood sugar could prevent a dangerous — and surprisingly common — medical emergency.

    Marcus, 54, had managed his type 2 diabetes for six years without a serious incident. Then, at a holiday party, he had a few drinks with dinner — skipped a snack before bed — and woke up at 2 a.m. in a cold sweat, confused and shaking. His wife recognized the signs of low blood sugar and acted quickly. Marcus was lucky. Not everyone is.

    According to the CDC, more than 38 million Americans are living with diabetes, and surveys from the National Institute on Alcohol Abuse and Alcoholism (NIAAA) suggest that adults with diabetes drink at rates similar to the general population. Yet many people with diabetes receive little guidance about how alcohol interacts with blood sugar, medications, and long-term complications.

    This article will walk you through exactly how alcohol affects blood sugar control, which risks matter most, how to drink more safely if you choose to, and when alcohol should be avoided entirely. If you’re managing diabetes — or caring for someone who is — this information could be lifesaving.

    How Alcohol Affects Blood Sugar: The Science Behind the Risk

    To understand why alcohol and diabetes can be a dangerous combination, it helps to know what your liver does when you drink.

    Normally, your liver has two jobs running in the background: processing substances in your blood and releasing stored glucose (glycogen) to keep blood sugar from dropping too low. When you drink alcohol, the liver prioritizes metabolizing the alcohol above everything else — including releasing that stored glucose.

    The result? Blood sugar can drop significantly, especially if you’ve taken insulin or certain oral diabetes medications. This condition — called hypoglycemia (low blood sugar, typically below 70 mg/dL) — can develop slowly over several hours and may occur while you’re asleep, making it particularly dangerous.

    A meta-analysis published in the journal Diabetes Care found that alcohol consumption was associated with a significantly increased risk of hypoglycemic episodes in people with both type 1 and type 2 diabetes, particularly when alcohol was consumed without food. Clinical evidence also indicates that the liver’s glucose-releasing function can remain impaired for up to 24 hours after drinking — meaning the risk doesn’t end when the party does.

    On the flip side, some alcoholic beverages — especially sugary cocktails, sweet wines, beer, and mixed drinks with juice — can cause a temporary spike in blood sugar before the hypoglycemic effect kicks in. This two-phase swing is one of the reasons alcohol makes diabetes management particularly unpredictable.

    Signs and Symptoms: Hypoglycemia vs. Intoxication

    One of the most dangerous aspects of alcohol and diabetes is how easily their symptoms overlap — and how often one is mistaken for the other.

    Symptoms of hypoglycemia include:

    • Shakiness or trembling
    • Sweating, especially at night
    • Dizziness or lightheadedness
    • Confusion or slurred speech
    • Rapid heartbeat
    • Irritability or sudden mood changes
    • Pale or clammy skin
    • In severe cases: unconsciousness or seizure

    Notice that confusion, slurred speech, and unsteady gait — all classic signs of low blood sugar — are also classic signs of alcohol intoxication. Friends, family members, even emergency personnel may misread a hypoglycemic episode as drunkenness, delaying critical treatment.

    Research from the American Diabetes Association (ADA) reinforces that people with diabetes should always carry fast-acting glucose (such as glucose tablets or juice) when drinking and should wear a medical ID bracelet indicating their condition so that first responders can make an accurate assessment quickly.

    If you’re experiencing confusion or shaking and you’re unsure whether it’s low blood sugar or alcohol, treat for low blood sugar first — eating 15 grams of fast-acting carbohydrates — and check your glucose if possible. Never assume it’s just the alcohol.

    Causes of Increased Risk: Who Is Most Vulnerable

    Not all people with diabetes face the same level of risk from alcohol. Several factors increase your vulnerability significantly.

    Medication type matters enormously. People taking insulin or sulfonylureas (a class of oral medications that stimulate insulin production, including glipizide and glimepiride) face the highest risk of alcohol-induced hypoglycemia. The combination of these medications with alcohol’s glucose-suppressing effect on the liver can cause blood sugar to plunge rapidly.

    Drinking on an empty stomach dramatically amplifies this effect. Without food slowing alcohol absorption and providing carbohydrates to maintain blood sugar, the liver’s impaired glucose release becomes critical.

    Additional risk factors include:

    • Long duration of diabetes — people who have had diabetes for many years may have impaired counter-regulatory hormone responses (the hormones that normally kick in to raise blood sugar)
    • Kidney disease or liver disease — both affect how alcohol and glucose are metabolized
    • Autonomic neuropathy — nerve damage affecting internal organ function can blunt the warning symptoms of hypoglycemia
    • Older age — adults over 60 tend to metabolize alcohol more slowly and may have less awareness of hypoglycemia symptoms
    • Skipping meals or eating very little — common when drinking socially

    According to the NIH, heavy alcohol use — defined as more than 14 drinks per week for men and more than 7 per week for women — is also independently associated with worsening insulin resistance and a higher risk of developing diabetic complications. This risk compounds over time.

    Diagnosis and Monitoring: What Your Numbers Tell You

    If you have diabetes and you drink alcohol, consistent blood sugar monitoring becomes even more critical. Your healthcare provider may recommend more frequent checks on days when you drink — and especially before bed.

    Most physicians recommend that people with diabetes who choose to drink alcohol should:

    • Check blood sugar before drinking
    • Check blood sugar during the event if drinking extends more than 1-2 hours
    • Check blood sugar before bed — and eat a carbohydrate-containing snack if glucose is at or below 100 mg/dL
    • Set an alarm or ask a partner to check on you overnight if you’ve consumed more than one drink

    Continuous glucose monitors (CGMs) — devices worn on the skin that track glucose levels in real time — are particularly valuable tools for people who drink. They provide alerts when blood sugar is dropping, even during sleep. For a comprehensive understanding of monitoring tools available to you, our guide on Blood Sugar Monitoring for Type 2 Diabetes covers CGMs, fingerstick devices, and how to interpret your readings.

    Your doctor may also monitor your A1C (a measure of average blood sugar over 2-3 months) more closely if you drink regularly, since chronic alcohol use is associated with greater A1C variability and harder-to-control blood sugar levels.

    Treatment and Management: Drinking More Safely With Diabetes

    The American Diabetes Association does not tell all people with diabetes to abstain from alcohol entirely — but it does provide clear guidelines for those who choose to drink. Here is what clinical evidence supports:

    Stick to moderate drinking limits. The ADA recommends no more than one drink per day for women and two drinks per day for men. One standard drink equals 12 oz of regular beer, 5 oz of wine, or 1.5 oz of spirits.

    Never drink on an empty stomach. Always consume alcohol with a meal or substantial snack containing protein, fat, and complex carbohydrates. This slows alcohol absorption and helps buffer blood sugar drops.

    Choose lower-carbohydrate options. Dry wines, light beers, and spirits mixed with sparkling water or club soda are preferable to sweet cocktails, sugary mixers, or craft beers, which can contain 20-30 grams of carbohydrates per serving and cause unpredictable blood sugar spikes.

    Avoid binge drinking entirely. Consuming four or more drinks in a short period overwhelms the liver’s capacity and dramatically increases hypoglycemia risk over the next several hours. Research suggests that even one heavy episode can destabilize blood sugar control for more than 24 hours.

    Tell someone you trust. When you’re out, let a friend or family member know you have diabetes. Make sure they know the signs of hypoglycemia and what to do — including calling 911 if you become unconscious.

    Talk to your pharmacist and doctor about your medications. Some diabetes medications interact with alcohol beyond hypoglycemia risk. Metformin, for example, carries a rare but serious risk of lactic acidosis (a dangerous buildup of lactic acid in the blood) in people who drink heavily or have liver disease. Your healthcare provider can help you understand your specific medication interactions.

    Pair these strategies with a well-structured eating plan. Our resource on Diabetes Meal Planning: Build a Plate That Controls Blood Sugar can help you build meals that provide a stable glucose foundation — especially on days when you plan to drink.

    Living With Diabetes: Long-Term Alcohol and Complication Risk

    Beyond blood sugar swings, regular alcohol use affects the long-term trajectory of diabetes and its complications in several important ways.

    Heart health: People with diabetes already face two to four times the risk of cardiovascular disease compared to those without, according to the American Heart Association. Heavy alcohol use raises blood pressure, increases triglycerides, and contributes to irregular heart rhythms — all of which worsen cardiovascular risk. Moderate alcohol consumption has been studied for potential heart-protective effects, but most cardiologists and endocrinologists advise against drinking for heart health, particularly in people who already have elevated risk.

    Liver health: The liver plays a central role in both glucose metabolism and detoxification. Non-alcoholic fatty liver disease (NAFLD) — which is closely linked to insulin resistance — is already common in people with type 2 diabetes. Adding alcohol to the equation can accelerate liver damage and worsen insulin resistance further.

    Nerve health: Diabetic peripheral neuropathy (nerve damage, often in the feet and legs) is a complication affecting up to 50% of people with diabetes over their lifetime, according to the NIH. Alcohol is itself a neurotoxin and can accelerate nerve damage independently of blood sugar control — making it a particularly harmful combination for people already managing neuropathy.

    Mental health: Research published in Diabetes Care found that depression is two to three times more common in people with diabetes than in the general population. Alcohol is a central nervous system depressant, and while it may feel like it reduces stress or anxiety in the short term, regular use worsens depression and anxiety over time — making diabetes self-management harder. Stress itself worsens blood sugar control, as explored in our article on how cortisol and stress affect metabolic health.

    When to Call Your Doctor — and When to Call 911

    Some situations require immediate emergency response. Do not wait to call 911 if someone with diabetes who has been drinking shows any of the following:

    • Loss of consciousness or unresponsiveness
    • Seizure
    • Extreme confusion or inability to communicate
    • Blood sugar below 50 mg/dL that does not respond to oral glucose treatment
    • Severe vomiting that prevents oral treatment for low blood sugar

    Call your doctor — non-emergently but promptly — if you notice:

    • Repeated hypoglycemic episodes after drinking, even mild ones
    • Greater-than-usual difficulty controlling blood sugar on days following alcohol use
    • Signs of worsening neuropathy, such as increased numbness or tingling in the feet
    • Any signs of liver problems: yellowing skin, dark urine, abdominal pain
    • You feel you cannot reduce or stop drinking even when you want to

    That last point matters significantly. The NIAAA estimates that approximately 14.5 million Americans aged 12 and older have alcohol use disorder. If alcohol has become difficult to control, speaking honestly with your doctor opens the door to effective, evidence-based treatment options — including behavioral therapy and FDA-approved medications — without judgment.

    Frequently Asked Questions

    Can people with type 2 diabetes drink alcohol at all?
    Many people with well-controlled type 2 diabetes can consume alcohol in moderation — one drink per day for women, two for men — according to ADA guidelines. However, this varies significantly depending on your medications, kidney and liver health, and current blood sugar control. Always discuss this with your physician before drinking.

    Does alcohol raise or lower blood sugar?
    Both, depending on timing and what you drink. In the short term, sugary alcoholic beverages can raise blood sugar. Over the following hours, alcohol suppresses the liver’s ability to release stored glucose, which can cause a significant and dangerous drop in blood sugar — especially overnight. This two-phase effect makes monitoring critical.

    What is the safest alcoholic drink for someone with diabetes?
    Clinical evidence suggests that dry wines, light beers, and spirits mixed with zero-calorie mixers (like sparkling water or diet soda) have less impact on blood sugar than sweet cocktails, regular beer, or sugary mixed drinks. However, no alcohol is entirely safe, and individual responses vary significantly. This varies from person to person based on metabolism, medications, and overall health.

    How long does alcohol affect blood sugar after drinking?
    Research suggests the liver’s glucose-releasing function can be impaired for up to 12-24 hours after drinking. This means a person with diabetes may experience hypoglycemia the morning after a night of drinking — even without feeling intoxicated. Monitoring blood sugar the following morning is strongly recommended.

    Should I adjust my diabetes medication when I drink?
    Never adjust your medication dose on your own based on alcohol consumption. Speak with your doctor or pharmacist about your specific situation. Some adjustments may be appropriate, but this decision requires medical supervision and depends on your specific drug regimen, kidney function, and glucose control history.

    Conclusion

    Alcohol and diabetes can coexist — but only with knowledge, planning, and honest conversations with your healthcare team. The risks are real and specific: hypoglycemia that looks like intoxication, overnight blood sugar crashes, worsening nerve damage, and harder-to-control A1C levels. But the risks are also manageable when you understand them.

    You don’t have to feel isolated or uncertain about this topic. Bring your questions about alcohol to your next doctor’s appointment. Be honest about how much and how often you drink. Ask about your specific medications and what interactions matter for you.

    With the right information and the right support team, you can make informed choices that protect your health — without sacrificing your quality of life.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Diabetes Meal Planning: Build a Plate That Controls Blood Sugar

    Diabetes Meal Planning: Build a Plate That Controls Blood Sugar

    Diabetes Meal Planning: Build a Plate That Controls Blood Sugar

    What you eat at every meal is one of the most powerful tools you have for managing blood sugar — and a smart plan makes it sustainable.

    Why What You Eat Matters More Than You Think

    Marcus, 54, was diagnosed with type 2 diabetes three years ago. His doctor handed him a pamphlet about “eating healthy” and sent him on his way. Within six months, his A1C was still climbing — not because he wasn’t trying, but because “eat healthy” without a real structure is almost impossible to follow consistently.

    Sound familiar? You’re not alone. According to the CDC, more than 38 million Americans are living with diabetes as of the most recent national data, and a significant portion of them struggle with daily blood sugar management — often because no one gave them a clear, practical meal framework.

    Diabetes meal planning isn’t about eating less or giving up everything you love. It’s about building eating patterns that keep your glucose levels steady, support your energy, and reduce long-term complications. In this guide, you’ll learn how to structure your meals, which foods work for you and which work against you, and how to create a realistic plan that fits your actual life — not just a clinical chart.

    What Is Diabetes Meal Planning?

    Diabetes meal planning is a structured approach to choosing foods, portion sizes, and meal timing in a way that helps control blood glucose (sugar) levels throughout the day. Unlike a one-size-fits-all diet, it’s tailored to your body, your medications, your activity level, and your personal food preferences.

    The goal is not perfection — it’s consistency. When your meals are predictable in terms of carbohydrate content, timing, and nutritional balance, your pancreas (or your medication) has a much easier job keeping blood sugar in a healthy range.

    According to the American Diabetes Association (ADA), there is no single “diabetic diet” proven to work best for everyone. Instead, several evidence-based eating patterns — including the Mediterranean diet, low-carbohydrate diets, and the DASH diet — have all shown meaningful benefits for people with type 2 diabetes when followed consistently.

    That said, the foundation of any effective diabetes meal plan comes down to the same core principles: managing carbohydrate intake, prioritizing fiber, choosing quality protein, and limiting processed foods and added sugars.

    How Blood Sugar Responds to What You Eat

    Before building your plate, it helps to understand the basics of how food affects your blood glucose. When you eat carbohydrates — bread, rice, fruit, milk, anything starchy or sweet — your digestive system breaks them down into glucose. That glucose enters your bloodstream, causing blood sugar to rise.

    In people without diabetes, the pancreas releases insulin to move that glucose into cells for energy. In type 2 diabetes, either the pancreas doesn’t produce enough insulin, or the body’s cells don’t respond to it effectively — a condition called insulin resistance. The result: glucose stays elevated in the bloodstream longer than it should.

    A 2023 meta-analysis published through NIH-affiliated researchers confirmed that the type and amount of carbohydrates consumed is one of the strongest dietary predictors of postprandial (after-meal) blood sugar spikes in people with type 2 diabetes. This is why carbohydrate awareness — not necessarily elimination — is central to diabetes meal planning.

    Not all carbohydrates behave the same way. High-fiber, complex carbohydrates (like vegetables, legumes, and whole grains) are digested more slowly, producing a gentler, more gradual rise in blood sugar. Refined carbohydrates (white bread, sugary drinks, pastries) digest rapidly and cause sharp glucose spikes.

    For a deeper look at how carbohydrate counting works in practice, see our guide: Carb Counting for Diabetes: A Complete Beginner’s Guide.

    The Diabetes Plate Method: Simple and Effective

    One of the most practical frameworks recommended by the ADA is the Diabetes Plate Method. It requires no apps, no food scale, and no math — just a standard 9-inch dinner plate and an understanding of food categories.

    Here’s how to build it:

    • Half your plate: non-starchy vegetables — broccoli, spinach, kale, cauliflower, green beans, peppers, cucumbers, tomatoes, zucchini. These are high in fiber and low in carbohydrates, making them the safest foods for blood sugar control.
    • One quarter: lean protein — grilled chicken, fish (especially fatty fish like salmon or sardines), eggs, tofu, legumes, or low-fat dairy. Protein doesn’t raise blood sugar and helps you feel full longer.
    • One quarter: quality carbohydrates — brown rice, quinoa, whole grain bread, sweet potato, corn, or fruit. This is where your blood sugar management lives. Keeping this portion to one-quarter of your plate naturally limits your carbohydrate load per meal.
    • Healthy fats on the side — a small amount of olive oil, avocado, or nuts can support satiety and heart health without raising glucose.
    • Beverage — water, unsweetened sparkling water, or herbal tea. Avoid juice, soda, and sweetened coffee drinks.

    Clinical evidence from Johns Hopkins Medicine supports that visual portion-control tools like the plate method lead to meaningful reductions in post-meal glucose levels in type 2 diabetic patients, particularly when practiced consistently over several months.

    Best and Worst Foods for Blood Sugar Control

    Understanding which foods support your glucose management — and which ones sabotage it — is one of the most empowering steps you can take.

    Foods to Prioritize

    • Non-starchy vegetables: leafy greens, broccoli, asparagus, cauliflower, mushrooms, bell peppers
    • Legumes: lentils, black beans, chickpeas — high in protein and fiber, with a lower glycemic impact than most grains
    • Whole grains: oats, quinoa, farro, barley — slower to digest than refined grains
    • Fatty fish: salmon, mackerel, sardines — rich in omega-3 fatty acids, which research suggests may reduce cardiovascular risk in people with diabetes
    • Berries: blueberries, strawberries, raspberries — lower in sugar than other fruits, high in antioxidants
    • Nuts and seeds: almonds, walnuts, chia seeds, flaxseed — help slow digestion and improve satiety
    • Olive oil: associated with better insulin sensitivity in Mediterranean diet studies

    Foods to Limit or Avoid

    • Sugary beverages: soda, fruit juice, sweetened coffee drinks, energy drinks — cause rapid blood sugar spikes with no nutritional benefit
    • Refined grains: white bread, white rice, regular pasta — digest quickly and cause glucose surges
    • Fried foods: high in unhealthy fats and calories, may worsen insulin resistance over time
    • Highly processed snacks: chips, crackers, cookies — often combine refined carbs with unhealthy fats
    • Added sugars: candy, pastries, sweetened cereals — the ADA recommends minimizing these entirely
    • Alcohol: can cause unpredictable blood sugar swings, particularly if you take insulin or certain oral medications. Always consult your doctor before including alcohol in your routine.

    This varies from person to person — your specific medication regimen, kidney function, and other health factors may influence which foods are most or least appropriate for you. A registered dietitian who specializes in diabetes can personalize this list for your situation.

    Meal Timing and Frequency: Does It Matter?

    Yes — and more than most people realize. Erratic eating patterns, skipping meals, or going long stretches without food can cause blood sugar to drop too low (hypoglycemia) or rebound too high. For most people with type 2 diabetes, eating at consistent times each day helps the body (and any glucose-lowering medications) work more predictably.

    Most clinical guidelines suggest three balanced meals per day, spaced approximately 4 to 6 hours apart. Some people manage well with two smaller snacks between meals to prevent blood sugar dips, while others do better with strict three-meal structures. This is highly individual — what works for one person may not work for another.

    The NIH’s National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) notes that consistent meal timing is particularly important for people using insulin or sulfonylurea medications, as these drugs lower blood sugar on a schedule — and your food intake needs to align accordingly.

    Poor sleep can also disrupt your mealtime hunger cues and insulin sensitivity. If that’s a factor for you, our article on Diabetes and Sleep: How Poor Sleep Raises Blood Sugar is worth reading alongside this guide.

    Reading Food Labels: What to Look For

    One of the most practical skills in diabetes meal planning is learning to read nutrition labels accurately. Here’s what to pay attention to:

    • Total carbohydrates: This is the number that matters most for blood sugar. It includes starches, fiber, and sugars.
    • Dietary fiber: Subtract fiber grams from total carbohydrates to get “net carbs” — a better approximation of how much will actually raise your blood sugar.
    • Added sugars: The FDA now requires this to be listed separately. Aim to keep added sugars as low as possible.
    • Serving size: Everything on the label is per serving — not per package. A bag that seems like one serving often contains two or three.
    • Ingredients list: The closer to the top an ingredient appears, the more of it the product contains. Avoid products that list sugar (or its many aliases: corn syrup, maltose, dextrose, fructose) in the first few ingredients.

    Practical Meal Planning Tips You Can Start This Week

    • Batch cook on weekends: Prepare grains, roasted vegetables, and proteins in advance so healthy meals are accessible on busy weekdays.
    • Keep non-starchy vegetables prepped and ready: Washed, chopped vegetables in the fridge remove the friction of making healthy choices at mealtime.
    • Plan before you shop: Writing out your weekly meals before grocery shopping reduces impulse buys and ensures you have what you need.
    • Use a glucose monitor as feedback: If you test your blood sugar before and two hours after meals, you can identify which specific foods cause larger spikes in your body — this is personalized data no general guide can replicate.
    • Don’t eat carbohydrates alone: Pairing carbs with protein or healthy fat slows digestion and blunts glucose spikes. An apple alone raises blood sugar faster than an apple with a small handful of almonds.
    • Eat slowly and mindfully: Research from Harvard Health suggests that eating more slowly is associated with better portion control and lower post-meal glucose levels.

    When to Call Your Doctor or See a Specialist

    Diabetes meal planning can produce real results, but it works best as part of a comprehensive care plan — not as a replacement for it. Contact your healthcare provider if:

    • Your blood sugar readings remain consistently above or below your target range despite dietary changes
    • You experience frequent hypoglycemia (blood sugar drops below 70 mg/dL), especially with symptoms like shakiness, confusion, sweating, or dizziness
    • You have signs of high blood sugar (hyperglycemia) — extreme thirst, frequent urination, blurred vision, or fatigue — that don’t resolve
    • You are pregnant or planning to become pregnant (gestational diabetes has its own specific nutritional requirements)
    • You have kidney disease, cardiovascular disease, or other conditions that require additional dietary modifications

    Emergency red flags: If you experience confusion, loss of consciousness, extreme weakness, or vomiting alongside abnormal blood sugar readings, call 911 or go to the emergency room immediately. These can be signs of diabetic ketoacidosis (DKA) or severe hypoglycemia — both medical emergencies.

    Ask your doctor for a referral to a Registered Dietitian Nutritionist (RDN) who specializes in diabetes, or a Certified Diabetes Care and Education Specialist (CDCES). Medicare Part B covers Medical Nutrition Therapy (MNT) for people with diabetes — meaning this service may be available to you at no out-of-pocket cost. For more on navigating coverage, see: Health Insurance for Chronic Conditions: What You Need to Know.

    Frequently Asked Questions

    Can people with diabetes eat fruit?

    Yes — but portion size and fruit type matter. Berries, cherries, apples, and citrus fruits tend to have a lower glycemic impact than tropical fruits like mangoes or pineapples. Clinical evidence indicates that whole fruit — not fruit juice — is preferable because fiber slows glucose absorption. Most diabetes nutrition experts suggest limiting fruit servings to about half a cup to one small piece per meal or snack.

    Is a low-carb diet safe for diabetes?

    Research suggests that low-carbohydrate diets can be effective for improving blood sugar control and reducing A1C levels in people with type 2 diabetes. However, if you take insulin or certain diabetes medications, significantly lowering your carbohydrate intake may require medication adjustments to prevent hypoglycemia. Always consult your physician before making a major dietary change.

    Are artificial sweeteners safe for people with diabetes?

    The FDA has approved several non-nutritive sweeteners (stevia, sucralose, aspartame, saccharin) as safe for consumption. They don’t directly raise blood sugar. However, some research suggests that frequent use of artificial sweeteners may influence taste preferences and appetite in ways that could affect long-term dietary patterns. Most physicians recommend using them in moderation rather than as an unlimited free pass.

    How do I handle eating out with diabetes?

    Eating at restaurants is manageable with a few strategies: choose grilled or baked proteins over fried, request sauces and dressings on the side, ask for extra vegetables instead of a starchy side dish, and be cautious with bread baskets and desserts. Many chain restaurants now post nutritional information online, allowing you to review options before you arrive.

    Do I need to count calories or just carbohydrates?

    For most people with type 2 diabetes, carbohydrate awareness is more directly relevant to blood sugar management than calorie counting. That said, overall calorie balance matters for weight management — and weight loss, even modest amounts, can significantly improve insulin sensitivity. Your healthcare team can help you determine which approach is most appropriate for your specific goals.

    The Bottom Line

    Managing diabetes through food doesn’t have to feel like deprivation or constant restriction. It’s about building a consistent, balanced approach — one that gives your body the steady fuel it needs while keeping blood sugar in a range that protects your long-term health.

    Start with the basics: fill half your plate with vegetables, keep your carbohydrate portions controlled and high-fiber, pair them with protein and healthy fat, and eat at consistent times. From there, use your glucose monitor as a personal feedback tool and work with your care team to fine-tune the details.

    Small, sustainable changes practiced daily have a far greater impact on diabetes management than any dramatic short-term effort. You have more control over your blood sugar than you may realize — and building a smart meal plan is one of the most evidence-backed ways to use it.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Carb Counting for Diabetes: A Complete Beginner’s Guide

    Carb Counting for Diabetes: A Complete Beginner’s Guide

    Learning to count carbohydrates can be one of the most empowering tools in your diabetes management plan — and one of the most misunderstood.

    Marcus, 52, was diagnosed with Type 2 diabetes three years ago. His doctor told him to "watch his carbs," but nobody explained what that actually meant. He gave up bread and pasta — and still couldn’t get his blood sugar under control. The problem wasn’t his willpower. It was that he didn’t know that a bowl of oatmeal, a glass of orange juice, and a banana at breakfast could send his glucose numbers soaring just as fast as a slice of cake.

    According to the American Diabetes Association (ADA), carbohydrate counting is one of the most effective meal planning strategies for people with both Type 1 and Type 2 diabetes. Yet surveys suggest that fewer than half of people living with diabetes receive structured nutrition education after their diagnosis.

    In this guide, you’ll learn exactly what carbohydrate counting is, how it affects your blood sugar, how to get started, and practical strategies you can use starting at your very next meal — all grounded in clinical evidence and aligned with current ADA and CDC recommendations.

    What Is Carbohydrate Counting?

    Carbohydrate counting — often called "carb counting" — is a meal planning method that tracks the total grams of carbohydrates you consume at each meal or snack. Unlike generalized "healthy eating" advice, carb counting gives you a specific, measurable way to manage the nutrient that has the most direct and immediate impact on your blood glucose (blood sugar) levels.

    Carbohydrates are one of three macronutrients (along with protein and fat). When digested, they break down into glucose, which enters your bloodstream. For people without diabetes, the pancreas automatically releases enough insulin to manage this glucose surge. For people with diabetes, that process is impaired — making the amount of carbohydrates you eat a critical variable in blood sugar control.

    The CDC reports that approximately 38.4 million Americans — roughly 11.6% of the US population — have diabetes. Of those, an estimated 90-95% have Type 2 diabetes. For all of them, managing carbohydrate intake is a cornerstone of care.

    Carb counting works at two levels:

    • Basic carb counting: Tracking total carbohydrate grams to stay within a consistent daily target set by your healthcare provider or registered dietitian.
    • Advanced carb counting: Used primarily by people on insulin therapy; involves matching insulin doses to the exact amount of carbs consumed at each meal (called an insulin-to-carb ratio).

    This guide focuses on both levels, starting with the fundamentals.

    Why Carbohydrates Matter More Than Other Nutrients

    You’ve probably heard that sugar is bad for diabetes — but the full picture is more nuanced. All carbohydrates raise blood glucose, not just added sugars. That includes naturally occurring carbs in fruit, dairy, legumes, and whole grains.

    Clinical evidence supports this clearly. A 2022 meta-analysis published in Diabetes Care (affiliated with the ADA) found that low-carbohydrate dietary patterns significantly reduced HbA1c levels — a measure of average blood sugar over three months — in adults with Type 2 diabetes. Participants who tracked their carbohydrate intake consistently showed greater glycemic improvement than those who simply received general dietary advice.

    Here’s the key distinction that most people miss:

    • Fat and protein have a minimal and delayed effect on blood glucose.
    • Carbohydrates raise blood sugar within 15 to 60 minutes of eating, depending on the type and amount consumed.

    This is why two meals with identical calorie counts can produce very different blood sugar responses — if one meal is carbohydrate-heavy and the other is protein-and-fat-heavy, your glucose readings afterward will look dramatically different. Understanding this dynamic gives you real, measurable control.

    Identifying Carbohydrates in Your Diet

    One of the biggest hurdles for people new to carb counting is recognizing which foods actually contain significant carbohydrates. Many people are surprised by what’s on the list.

    High-carbohydrate foods to track carefully:

    • Bread, rolls, bagels, crackers, and tortillas
    • Rice, pasta, noodles, and couscous
    • Potatoes, corn, peas, and winter squash
    • Breakfast cereals, oatmeal, and granola
    • Fruit and 100% fruit juice
    • Milk, yogurt, and flavored dairy drinks
    • Dried beans, lentils, and chickpeas
    • Sweets, desserts, candy, and sugary beverages
    • Snack foods like pretzels, chips, and popcorn

    Foods with minimal carbohydrates (generally free or low-impact):

    • Non-starchy vegetables: spinach, broccoli, cauliflower, peppers, zucchini, leafy greens
    • Meat, poultry, and seafood (unbreaded)
    • Eggs
    • Cheese and most nuts
    • Oils and butter

    According to the NIH’s National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), most adults with diabetes are advised to get approximately 45-60 grams of carbohydrates per meal, though this varies significantly based on body size, activity level, medication type, and individual blood sugar response. Your specific target should always be set by your care team.

    How to Read a Nutrition Label for Carb Counting

    The FDA’s updated Nutrition Facts label — now required on all packaged foods in the US — is your best friend for carb counting. Here’s how to read it effectively:

    Step 1: Check the serving size first. All the numbers on the label apply to that specific serving size — not the whole package. A bag of crackers might list 20 grams of carbs per serving, but if you eat two servings, you’ve consumed 40 grams.

    Step 2: Find "Total Carbohydrate." This is the number you count. It includes all types of carbs: starches, sugars, and fiber.

    Step 3: Subtract dietary fiber (optional but useful). Fiber is a carbohydrate that your body cannot fully digest, so it has a much smaller impact on blood sugar. Many dietitians recommend subtracting fiber grams from total carbohydrates to calculate "net carbs." However, this approach varies by individual, and you should confirm it with your dietitian or diabetes educator.

    Step 4: Note added sugars. While added sugars count toward your total carbs, watching them separately is good practice. The ADA recommends minimizing added sugars as part of an overall healthy eating pattern for diabetes.

    For fresh foods without labels — such as fruits, vegetables, and restaurant meals — tools like the USDA FoodData Central database, CalorieKing, or apps like MyFitnessPal and Cronometer can help you estimate carb content accurately.

    Getting Started: Setting Your Carb Budget

    There is no one-size-fits-all carbohydrate target for diabetes. Research suggests that what works for one person may not work for another — this truly varies from person to person. That said, here is how most healthcare providers approach establishing your starting point:

    Work with your care team. A registered dietitian who specializes in diabetes (often called a Certified Diabetes Care and Education Specialist, or CDCES) is your most valuable resource. They will factor in your weight, activity level, medications (especially insulin), kidney function, and personal food preferences to build a realistic carb target.

    Typical starting ranges (general guidelines only):

    • Per meal: 45-60 grams of carbohydrates (for most adults with Type 2 diabetes)
    • Per snack: 15-30 grams
    • Daily total: 130-180 grams (though some individuals do well on lower targets under medical supervision)

    Monitor your response. Checking your blood glucose before a meal and again 1-2 hours after eating is the most direct way to understand how a specific food or meal affects your blood sugar. The ADA recommends a postmeal (postprandial) blood glucose target of less than 180 mg/dL for most non-pregnant adults with diabetes, though individual targets may differ.

    A 2021 systematic review in Nutrients found that structured self-monitoring of blood glucose combined with carbohydrate counting led to significantly better glycemic control in Type 2 diabetes patients compared to monitoring alone — underscoring that both tools work best together.

    Advanced Carb Counting: Insulin-to-Carb Ratios

    If you use rapid-acting insulin at mealtimes — common in Type 1 diabetes and some cases of Type 2 — your doctor may teach you to use an insulin-to-carb ratio (ICR). This means for every X grams of carbohydrate you eat, you take a set number of units of insulin.

    For example, if your ratio is 1:15, you would take 1 unit of rapid-acting insulin for every 15 grams of carbohydrates you eat. A meal with 60 grams of carbs would require 4 units.

    This approach requires accurate carb counting, consistent monitoring, and close communication with your endocrinologist or diabetes care team. Never adjust your insulin doses without medical guidance — this is a medically supervised process. Johns Hopkins Medicine and the Cleveland Clinic both emphasize that ICR-based dosing should be individualized and regularly reassessed as your circumstances change.

    If you’re managing diabetes with sleep issues as well, research suggests poor sleep can independently worsen blood sugar control — you can learn more in our article on Diabetes and Sleep: How Poor Sleep Raises Blood Sugar.

    Living With Diabetes: Practical Carb Counting Tips

    Managing carb counting in real life — at restaurants, holidays, and busy weekdays — takes practice. Here are evidence-informed strategies that make it sustainable:

    Use the plate method as a visual guide. The USDA and ADA both recommend filling half your plate with non-starchy vegetables, one-quarter with lean protein, and one-quarter with a carbohydrate-containing food. This naturally limits carb portions without requiring a scale at every meal.

    Batch cook and label carb amounts. Preparing grains, legumes, and starchy vegetables in advance — and noting the carb count per portion — removes guesswork during busy weeknights.

    Choose high-fiber carbs when possible. Foods high in dietary fiber — like legumes, oats, and non-starchy vegetables — raise blood sugar more slowly than refined carbohydrates. Clinical evidence from Harvard Health and NIH consistently supports fiber-rich diets as beneficial for glycemic control.

    Watch liquid carbohydrates closely. Juice, soda, sports drinks, and even "healthy" smoothies can contain 30-60 grams of carbohydrates in a single serving — often without the fiber that slows glucose absorption. Most diabetes specialists recommend limiting sugary beverages significantly.

    Don’t skip meals. Skipping meals can cause blood sugar to drop too low (hypoglycemia) if you take certain diabetes medications or insulin — and then rebound sharply when you do eat. Consistent meal timing supports more predictable glucose patterns.

    If you’re also interested in how intermittent fasting interacts with diabetes and blood sugar, our guide on Intermittent Fasting for Weight Loss: What the Science Says covers important considerations.

    When to Call Your Doctor or Seek Emergency Care

    Carb counting is a powerful tool, but it doesn’t replace ongoing medical care. Know when to reach out immediately:

    Call your doctor promptly if:

    • Your blood glucose is consistently above 250 mg/dL despite dietary changes
    • You’re experiencing frequent hypoglycemia (blood sugar below 70 mg/dL) after adjusting your eating
    • You feel confused, unusually fatigued, or notice changes in urination or thirst
    • Your A1C isn’t improving despite consistent carb tracking
    • You’re unsure how to adjust your plan when you’re sick or traveling

    Seek emergency care immediately if you experience:

    • Blood glucose above 400 mg/dL with symptoms like vomiting, rapid breathing, or fruity-smelling breath (possible signs of diabetic ketoacidosis — a medical emergency)
    • Severe hypoglycemia with confusion, seizures, or loss of consciousness
    • Chest pain, sudden severe headache, or difficulty speaking alongside abnormal blood sugar readings

    The CDC and American Diabetes Association both emphasize that diabetes complications are largely preventable with consistent monitoring, appropriate medication, and structured lifestyle management — including effective carb counting. You can also read our guide on Diabetes and Kidney Disease: Protect Your Kidneys Now to understand how long-term blood sugar control affects kidney health.

    Frequently Asked Questions

    Q: Do I need to count carbs if I have Type 2 diabetes but don’t use insulin?
    A: Yes — carb counting is beneficial regardless of whether you use insulin. For people managing Type 2 diabetes with oral medications or lifestyle alone, consistent carbohydrate intake helps stabilize blood glucose and reduce A1C. Research suggests that structured carb tracking is one of the most effective non-pharmacological tools for glycemic management.

    Q: Are all carbohydrates equally bad for blood sugar?
    A: No. The type and quality of carbohydrates matter. High-fiber, minimally processed carbs — like legumes, oats, and non-starchy vegetables — raise blood sugar more slowly than refined carbs such as white bread or sugary drinks. Clinical evidence supports choosing whole food sources of carbohydrates whenever possible.

    Q: How many carbs should I eat per day if I have diabetes?
    A: This varies significantly from person to person. The ADA does not endorse one universal carbohydrate target. Most adults with Type 2 diabetes start in the range of 130-180 grams per day, but your physician or registered dietitian should set your individual target based on your medications, weight, activity level, and blood sugar response.

    Q: Can I use a continuous glucose monitor (CGM) to help with carb counting?
    A: Absolutely. A CGM tracks your blood glucose in real time, allowing you to see exactly how different foods and meals affect your levels throughout the day. Many endocrinologists and diabetes educators consider CGMs a powerful complement to carb counting, particularly for people on insulin. The FDA has approved several CGM devices for ongoing use in people with both Type 1 and Type 2 diabetes.

    Q: Is a very low-carb or ketogenic diet safe for people with diabetes?
    A: Research suggests that very low-carbohydrate diets (typically under 50 grams per day) can improve blood sugar control and reduce A1C in some people with Type 2 diabetes. However, these diets carry risks — especially for people on insulin or certain medications — including hypoglycemia and electrolyte imbalances. Always discuss significant dietary changes with your doctor before implementing them.

    Conclusion

    Carbohydrate counting isn’t about restriction for its own sake — it’s about giving yourself accurate information so you can make choices that keep your blood sugar stable and protect your long-term health. Like any skill, it takes practice, and it works best when you have a knowledgeable care team guiding you.

    Start small: read one nutrition label today, log one meal, check your glucose after eating. Build from there. Most people who commit to learning carb counting report feeling more in control of their diabetes — not more deprived. The goal isn’t perfection. It’s consistent, informed management that you can sustain for the long haul.

    Work closely with your physician, endocrinologist, or a certified diabetes care and education specialist to develop a carbohydrate plan that fits your life, your medications, and your health goals.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Diabetes and Sleep: How Poor Sleep Raises Blood Sugar

    Diabetes and Sleep: How Poor Sleep Raises Blood Sugar

    Poor sleep and diabetes form a dangerous cycle — and breaking it may be one of the most underrated moves in blood sugar management.

    Marcus, 54, had been living with type 2 diabetes for six years. He tracked his carbs, took his medication faithfully, and exercised three times a week. Yet his fasting blood sugar readings kept creeping up. His endocrinologist asked one question that changed everything: “How well are you sleeping?”

    Marcus was getting five hours a night — tops. He thought that was just part of getting older. It wasn’t. It was quietly undermining every other effort he was making to manage his diabetes.

    According to the CDC, more than 35% of American adults report sleeping fewer than seven hours per night. Among adults with type 2 diabetes, sleep problems are even more common — and the consequences are measurable in blood glucose levels, insulin sensitivity, and long-term A1C trends.

    In this guide, you’ll learn how sleep directly affects blood sugar control, what the research says, and what practical steps you can take to improve both your sleep and your diabetes outcomes — starting tonight.

    The Connection Between Sleep and Blood Sugar

    Sleep isn’t passive recovery. While you rest, your body is actively regulating hormones, repairing tissues, and resetting metabolic processes — including the ones that govern blood glucose.

    When you don’t sleep enough — or sleep poorly — your body responds with a stress-like hormonal cascade. Cortisol and adrenaline (epinephrine) rise, signaling your liver to release more glucose into the bloodstream. At the same time, insulin sensitivity decreases, meaning your cells become less responsive to insulin’s signal to absorb that glucose.

    The result: higher blood sugar, even if you haven’t eaten anything different.

    A landmark study published in Annals of Internal Medicine found that just four nights of sleep restriction (4.5 hours per night) reduced insulin sensitivity in healthy adults by 16% and reduced the capacity of fat cells to respond properly to insulin by 30%. For someone already managing insulin resistance, that’s a significant added burden.

    Research suggests the relationship runs in both directions: poor sleep worsens diabetes control, and diabetes complications — including neuropathy, nighttime urination, and sleep apnea — disrupt sleep quality. This bidirectional cycle makes addressing sleep a clinical priority, not an afterthought.

    Signs That Poor Sleep May Be Affecting Your Blood Sugar

    You may not immediately connect your blood sugar readings to how you slept the night before. But clinical evidence indicates several signs that sleep disruption is influencing your glucose control:

    Early or mild signs:

    • Fasting blood glucose consistently higher than your target range
    • Stronger cravings for carbohydrates and sugary foods the next day
    • Difficulty concentrating or “brain fog” after a poor night’s sleep
    • Increased hunger despite eating normally
    • Blood sugar spikes after meals that are harder to manage
    • Fatigue that doesn’t improve with rest

    More advanced or persistent signs:

    • A1C creeping upward despite consistent medication use
    • Waking multiple times at night to urinate (possible sign of high blood glucose or uncontrolled diabetes)
    • Witnessed gasping or pauses in breathing during sleep (potential sleep apnea — a major diabetes-related complication)
    • Restless leg sensations at night (may indicate diabetic peripheral neuropathy)
    • Morning headaches and daytime sleepiness despite seven or more hours in bed

    According to a study in Diabetes Care, adults with type 2 diabetes who slept fewer than six hours per night had significantly higher A1C levels than those who slept seven to eight hours, even after adjusting for diet and medication use. This varies from person to person, but the pattern is consistent across multiple large-scale studies.

    Why Diabetes Makes Sleep Harder — and Vice Versa

    One of the most frustrating aspects of diabetes and sleep is how each condition fuels the other. Understanding these mechanisms helps you target the right intervention.

    How diabetes disrupts sleep:

    • Nocturia (nighttime urination): When blood glucose is elevated, your kidneys work overtime to filter excess sugar, causing frequent trips to the bathroom at night.
    • Nocturnal hypoglycemia: Low blood sugar episodes during sleep can cause sweating, heart pounding, or nightmares that wake you up.
    • Peripheral neuropathy: Nerve damage in the legs and feet can cause burning, tingling, or pain that makes it impossible to fall or stay asleep.
    • Obstructive sleep apnea (OSA): Research from the American Diabetes Association indicates that OSA affects up to 70% of people with type 2 diabetes — far higher than the general population rate of 20-30%.

    How poor sleep worsens diabetes:

    • Elevated cortisol raises fasting blood glucose
    • Reduced insulin sensitivity makes medications less effective
    • Sleep deprivation increases ghrelin (hunger hormone) and decreases leptin (satiety hormone), promoting overeating of high-carb foods
    • Chronic sleep loss promotes systemic inflammation, which is a known driver of insulin resistance

    This cycle isn’t inevitable — but it does require active, informed management. For more on how insulin resistance develops, see our article on Diabetes and Kidney Disease: Protect Your Kidneys Now, which covers related metabolic pathways.

    Sleep Disorders Common in People With Diabetes

    Certain sleep disorders are significantly more prevalent among people with diabetes, and identifying them is the first step toward treatment.

    Obstructive Sleep Apnea (OSA)
    OSA occurs when the airway partially or fully collapses during sleep, causing interrupted breathing. Clinical evidence indicates that OSA both worsens insulin resistance and is more likely to develop in people who are overweight — a common comorbidity in type 2 diabetes. The NIH reports that treating OSA with continuous positive airway pressure (CPAP) therapy can meaningfully improve insulin sensitivity and glucose variability in people with diabetes.

    Restless Leg Syndrome (RLS)
    RLS causes uncomfortable sensations in the legs — often described as crawling, tingling, or aching — that worsen at rest and improve with movement. Research suggests that RLS is more common in people with diabetes, partly linked to peripheral neuropathy and iron deficiency.

    Insomnia
    Chronic insomnia — difficulty falling asleep, staying asleep, or waking too early — is more prevalent in adults with diabetes. Anxiety about blood sugar levels, pain from neuropathy, and the metabolic consequences of glucose dysregulation all contribute. Cognitive behavioral therapy for insomnia (CBT-I) is the first-line, evidence-based treatment recommended by the American Academy of Sleep Medicine, and it does not require medication.

    Circadian Rhythm Disruption
    Shift work, irregular schedules, or late-night screen exposure can disrupt your body’s internal clock. Research from Harvard Health indicates that circadian misalignment impairs glucose metabolism independently of total sleep duration.

    What the Research Says: Sleep Duration, Quality, and A1C

    The science connecting sleep and blood sugar is robust and growing stronger every year.

    A 2020 meta-analysis published in Sleep Medicine Reviews — analyzing data from over 36,000 participants — found that both short sleep duration (fewer than six hours) and long sleep duration (more than nine hours) were independently associated with higher rates of type 2 diabetes. The sweet spot: seven to eight hours per night.

    A separate NIH-supported study found that improving sleep quality in adults with type 2 diabetes — through behavioral sleep interventions — led to measurable reductions in A1C at six months, comparable in magnitude to some low-intensity pharmacological interventions.

    Clinical evidence also indicates that slow-wave sleep (deep sleep) is particularly important for glucose metabolism. During deep sleep, growth hormone is released and cortisol is suppressed — conditions that support healthy insulin function. Conditions or substances that suppress deep sleep (including alcohol and certain medications) can impair glucose regulation even when total sleep time seems adequate.

    Most physicians now consider sleep assessment a standard part of comprehensive diabetes care, alongside A1C monitoring, blood pressure, and lipid panels.

    Practical Strategies to Improve Sleep and Blood Sugar Together

    The good news: many strategies that improve sleep quality also directly benefit blood sugar control. These approaches are evidence-based and complement — never replace — your prescribed diabetes treatment plan.

    1. Set a consistent sleep schedule
    Go to bed and wake up at the same time every day, including weekends. Research suggests that consistent sleep timing improves circadian rhythm and reduces cortisol variability, both of which benefit glucose regulation.

    2. Create a glucose-friendly pre-sleep routine
    Avoid large meals or high-glycemic snacks in the two hours before bed. If your care team has approved a small bedtime snack to prevent nocturnal hypoglycemia, choose something with protein and fiber (such as a handful of nuts or low-fat cheese with whole grain crackers) over refined carbohydrates.

    3. Limit alcohol near bedtime
    Alcohol may help you fall asleep but suppresses REM and deep sleep stages, worsens glucose control, and increases the risk of nocturnal hypoglycemia. The American Diabetes Association recommends moderation and always discussing alcohol use with your diabetes care team.

    4. Manage nightly blood sugar proactively
    If nocturnal hypoglycemia or hyperglycemia is waking you up, talk to your doctor. Adjustments to medication timing, dosing, or continuous glucose monitor (CGM) alert settings may reduce nighttime disruptions significantly.

    5. Exercise regularly — but time it right
    Regular physical activity improves both sleep quality and insulin sensitivity. Clinical evidence indicates that moderate aerobic exercise (such as brisk walking for 30 minutes) improves sleep quality in older adults with type 2 diabetes. Avoid vigorous exercise within two to three hours of bedtime, as it may temporarily raise cortisol and delay sleep onset.

    6. Address pain from neuropathy
    If nerve pain is keeping you awake, speak with your doctor about pain management options — including medications, physical therapy, or TENS (transcutaneous electrical nerve stimulation). Unmanaged neuropathy pain is one of the most underreported causes of poor sleep in people with diabetes.

    7. Limit screen exposure before bed
    Blue light from phones, tablets, and televisions suppresses melatonin production, delaying sleep onset. Research from Johns Hopkins suggests that avoiding screens for 60 to 90 minutes before bed meaningfully improves sleep latency (how quickly you fall asleep).

    8. Consider a sleep study if you snore or feel unrefreshed
    If your partner notices that you stop breathing during sleep, or if you wake up tired despite adequate time in bed, ask your doctor about a sleep study to rule out obstructive sleep apnea. Treating OSA with CPAP has been shown to improve glycemic control in multiple clinical trials.

    You may also find it helpful to review our article on Diabetes and Heart Disease: Protecting Your Heart, since sleep quality is also a significant factor in cardiovascular risk — another top concern for people managing diabetes.

    When to Call Your Doctor or Seek Immediate Care

    Most sleep issues related to diabetes can be addressed through your primary care physician or endocrinologist during a scheduled visit. However, some situations require faster action.

    Call your doctor promptly if you notice:

    • Consistently elevated morning blood glucose despite following your treatment plan
    • Waking up multiple times a night to urinate
    • Signs of nocturnal hypoglycemia (waking with sweating, shaking, confusion, or a rapid heartbeat)
    • Persistent burning or pain in the feet or legs that disrupts sleep
    • A partner reporting that you stop breathing or gasp during sleep
    • Excessive daytime sleepiness that interferes with work or safety (including driving)

    Seek emergency care immediately if you experience:

    • Severe hypoglycemia with confusion, loss of consciousness, or inability to swallow
    • Blood glucose readings that are dangerously high and accompanied by nausea, vomiting, or rapid breathing (possible signs of diabetic ketoacidosis — a medical emergency)
    • Chest pain or severe shortness of breath during or after sleep

    At your next routine visit, bring a brief sleep diary — noting your bedtime, wake time, nighttime awakenings, and morning blood glucose readings for one to two weeks. This gives your doctor actionable data rather than general impressions.

    Frequently Asked Questions

    Q: Can one bad night of sleep raise my blood sugar the next morning?
    A: Yes. Research suggests that even a single night of insufficient sleep can elevate fasting blood glucose the following morning, primarily due to increased cortisol and reduced insulin sensitivity. This is usually temporary, but chronically poor sleep compounds these effects significantly.

    Q: Is it safe to take melatonin if I have type 2 diabetes?
    A: Melatonin supplements are generally considered low-risk, but clinical evidence on their direct effect on blood glucose in people with diabetes is mixed. Some studies suggest melatonin may affect insulin secretion. Always consult your physician before starting any supplement, including melatonin, to ensure it is appropriate for your individual situation.

    Q: Does sleep apnea actually affect A1C?
    A: Yes. Multiple clinical studies indicate that untreated obstructive sleep apnea is associated with higher A1C levels, and that treatment with CPAP therapy can improve glycemic control in people with type 2 diabetes. If you suspect sleep apnea, ask your doctor for a referral for a sleep study.

    Q: How many hours of sleep should a person with type 2 diabetes aim for?
    A: Most physicians recommend seven to nine hours per night for adults. Both short sleep (fewer than six hours) and long sleep (more than nine hours) have been associated with worse metabolic outcomes. Quality matters too — fragmented or non-restorative sleep can impair glucose regulation even when total duration seems adequate.

    Q: Are sleeping pills safe to use when you have diabetes?
    A: This varies from person to person and depends heavily on which medication is considered and your full medical history. Some sedative-hypnotic medications can affect blood glucose levels or interact with diabetes medications. Cognitive behavioral therapy for insomnia (CBT-I) is the preferred first-line treatment for chronic insomnia and does not carry these risks. Discuss any sleep aid — prescription or over-the-counter — with your physician before using it.

    Conclusion

    Managing diabetes is about much more than what you eat or which medication you take. Sleep is a foundational pillar of metabolic health — and for people living with type 2 diabetes, it may be the most overlooked lever available.

    The connection between sleep and blood sugar is not a theory; it is backed by decades of clinical evidence. Improving your sleep quality can reduce insulin resistance, support healthier A1C trends, curb cravings, and make every other element of your diabetes management plan more effective.

    You don’t have to overhaul everything at once. Start with one change — a consistent bedtime, a conversation with your doctor about nighttime symptoms, or a sleep study referral. Small, consistent improvements in sleep can produce meaningful improvements in blood sugar control over time.

    Work closely with your diabetes care team. They can help you connect the dots between your sleep patterns and your glucose data — and develop a plan tailored to your specific needs.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.
  • Exercise and Blood Sugar Control: A Type 2 Diabetes Guide

    Exercise and Blood Sugar Control: A Type 2 Diabetes Guide

    Exercise and Blood Sugar Control: A Type 2 Diabetes Guide

    The right physical activity plan can be one of the most powerful tools for managing type 2 diabetes — and your doctor can help you make it work safely.

    Introduction

    Marcus, 54, had been living with type 2 diabetes for six years. He took his medications, watched what he ate, and still felt like his blood sugar levels were on a rollercoaster. Then his endocrinologist suggested something unexpected: a structured 30-minute walk after dinner, five days a week. Within three months, his fasting glucose had dropped noticeably, and his energy levels had improved significantly.

    His story is far from unique. According to the CDC, more than 38 million Americans are currently living with diabetes, and type 2 diabetes accounts for approximately 90-95% of all cases. Yet exercise remains one of the most underutilized tools in blood sugar control for type 2 diabetes.

    In this guide, you will learn exactly how physical activity affects your blood glucose, which types of exercise deliver the greatest benefits, how to exercise safely when you have diabetes, and what warning signs to watch for. Whether you are newly diagnosed or have been managing this condition for years, this information is designed to help you have a more informed conversation with your healthcare team.

    What Is the Connection Between Exercise and Blood Sugar?

    To understand why exercise matters so much in type 2 diabetes management, it helps to first understand what is happening inside your body. Type 2 diabetes is characterized by insulin resistance — a condition in which your cells do not respond efficiently to insulin, the hormone that allows glucose (sugar) to enter your cells for energy. As a result, glucose builds up in the bloodstream, leading to elevated blood sugar levels over time.

    Exercise creates a remarkable biological shortcut. When your muscles contract during physical activity, they can absorb glucose from the bloodstream without requiring insulin to do so. This is sometimes called the "insulin-independent glucose uptake" pathway, and it is one reason why even a single session of moderate exercise can meaningfully lower blood sugar levels for hours afterward.

    Beyond this immediate effect, regular exercise also improves long-term insulin sensitivity — meaning your body becomes better at using the insulin it produces. According to the NIH’s National Institute of Diabetes and Digestive and Kidney Diseases, consistent physical activity is associated with improvements in A1C levels (your three-month blood sugar average), blood pressure, and cardiovascular risk factors — all of which are critical concerns for people managing type 2 diabetes.

    This dual action — immediate glucose-lowering and long-term metabolic improvement — makes exercise uniquely valuable as part of a comprehensive diabetes management plan.

    Signs That Your Blood Sugar Is Being Affected by Exercise

    Understanding how your body responds to exercise is a critical skill when you have type 2 diabetes. Responses vary significantly from person to person, and recognizing the signs helps you stay safe and make informed adjustments with your care team.

    Signs that exercise is helping lower your blood sugar (hypoglycemia risk, especially if on insulin or sulfonylureas):

    • Shakiness or trembling during or after activity
    • Sudden sweating unrelated to exertion
    • Dizziness or lightheadedness
    • Unusual hunger mid-workout
    • Difficulty concentrating or feeling confused
    • Rapid heartbeat without explanation

    Signs that blood sugar may be elevated (hyperglycemia) before or after exercise:

    • Excessive thirst during activity
    • Frequent urination shortly after exercise
    • Fatigue that seems disproportionate to the effort
    • Blurred vision during or after a workout
    • Headache that persists after cooling down

    A 2023 systematic review published in Diabetes Care found that people with type 2 diabetes who monitored their blood glucose before and after exercise sessions were significantly better at identifying patterns and adjusting their activity safely. Most physicians recommend checking your blood sugar before, sometimes during, and after exercise — particularly when you are new to a fitness routine or have recently changed your medications.

    Causes of Blood Sugar Fluctuations During Exercise

    Not all exercise affects blood sugar the same way, and that surprises many people. Several factors determine whether your glucose goes up, down, or stays steady during a workout.

    Type of exercise matters significantly:

    • Aerobic exercise (walking, cycling, swimming) generally lowers blood sugar during and after activity by increasing insulin-independent glucose uptake.
    • High-intensity interval training (HIIT) and resistance training can temporarily raise blood sugar due to the release of stress hormones like cortisol and adrenaline, though glucose typically drops below baseline in the hours following the session.
    • Very intense or competitive exercise can trigger a significant spike in blood glucose due to a strong stress hormone response.

    Other contributing factors include:

    • Your current medications (insulin and sulfonylureas increase hypoglycemia risk during exercise)
    • Time of day (morning exercise on an empty stomach vs. post-meal activity)
    • Duration and intensity of the workout
    • Hydration status
    • Recent food intake
    • Sleep quality and overall stress levels

    According to the American Diabetes Association, people with type 2 diabetes who take insulin should work closely with their endocrinologist or diabetes educator to understand how different exercise types may require medication or carbohydrate intake adjustments. This is individual and should not be self-managed without professional guidance.

    It is also worth noting that if you have been largely sedentary, your body’s response to exercise may shift as you become more physically conditioned — another reason consistent monitoring and regular check-ins with your healthcare provider are so important. If you are also working on insulin resistance alongside diabetes management, you may find our related article on Insulin Resistance: Causes, Signs & How to Improve It particularly helpful.

    Diagnosis and Getting Started: What to Discuss With Your Doctor

    Before starting or significantly changing your exercise routine, a conversation with your physician is essential — especially if you have had type 2 diabetes for several years or have any related complications. This is not about getting permission; it is about getting a personalized plan that is safe and effective for your specific situation.

    Your doctor will likely want to review or order:

    • A current A1C test to understand your average blood sugar control
    • Blood pressure and resting heart rate assessment
    • Kidney function tests (if exercise-induced changes to blood pressure could be a concern)
    • Foot and nerve exam (peripheral neuropathy — nerve damage in the feet — can affect safe exercise choices)
    • Eye exam (severe diabetic retinopathy may limit certain high-intensity activities)
    • Cardiac evaluation if you have cardiovascular risk factors or symptoms

    The Mayo Clinic recommends that people with type 2 diabetes who have been inactive for an extended period consider starting with low-to-moderate intensity activity and gradually increasing duration and intensity over several weeks, with medical guidance. Rushing into intense exercise without preparation increases both injury risk and the chance of significant blood sugar fluctuations.

    Many people find it helpful to work with a Certified Diabetes Care and Education Specialist (CDCES) — a credentialed professional who can design an exercise plan specifically tailored to your glucose patterns, medications, and fitness baseline.

    Treatment Options: The Best Types of Exercise for Blood Sugar Control

    The good news is that you do not need to run marathons or join an expensive gym to see meaningful benefits. Clinical evidence supports several types of exercise as effective for blood sugar management in type 2 diabetes.

    1. Aerobic (Cardiovascular) Exercise

    Walking, swimming, cycling, dancing, and water aerobics all qualify as aerobic exercise — sustained rhythmic activity that elevates your heart rate moderately. The American Diabetes Association recommends at least 150 minutes of moderate-intensity aerobic activity per week for adults with type 2 diabetes, spread across at least three days with no more than two consecutive rest days.

    Research suggests that brisk walking after meals — specifically a 10-15 minute walk within 30 to 60 minutes of eating — can be particularly effective at blunting post-meal blood sugar spikes, which are a significant challenge in type 2 diabetes management.

    2. Resistance (Strength) Training

    Lifting weights, using resistance bands, or doing bodyweight exercises like squats and push-ups builds muscle mass — and more muscle means more tissue capable of absorbing glucose. Clinical evidence from the NIH indicates that resistance training two to three times per week improves insulin sensitivity and glycemic control independently of aerobic exercise. Combining both types appears to produce the greatest overall benefit.

    3. Flexibility and Balance Training

    Yoga and stretching exercises, while not primarily glucose-lowering, offer important complementary benefits: reduced stress hormones (which can raise blood sugar), improved balance (critical for fall prevention in older adults with neuropathy), and better overall adherence to an exercise program.

    4. Breaking Up Sedentary Time

    A growing body of research — including studies referenced by the American Heart Association — suggests that simply breaking up prolonged sitting with brief movement every 30 minutes can reduce blood sugar spikes, even on days when you do not complete a formal workout. Standing, walking to another room, or doing light stretches at regular intervals throughout the day adds up.

    If you are also managing your weight as part of your diabetes plan, our article on Weight Loss After 40: Why It’s Harder and What Works addresses some of the specific challenges many adults in this age group face.

    Living With Type 2 Diabetes: Building a Sustainable Exercise Habit

    Knowing that exercise is beneficial and actually sustaining a consistent routine are very different challenges. Here are practical, evidence-informed strategies that help people with type 2 diabetes make physical activity a lasting part of their lives.

    Start where you are, not where you think you should be. If you have been sedentary, beginning with 10-minute walks is a legitimate and effective starting point. Research suggests that shorter bouts of exercise accumulated throughout the day can be as beneficial as one continuous session for blood sugar control.

    Track your glucose response to different activities. Keeping a simple log of your blood sugar before and after different types and durations of exercise helps you and your doctor identify patterns. Over time, this data becomes one of your most valuable management tools.

    Wear proper footwear and check your feet daily. Peripheral neuropathy (nerve damage that can cause reduced sensation in the feet) is a complication that affects many people with long-term type 2 diabetes. According to the American Diabetes Association, foot injuries that go unnoticed due to reduced sensation can become serious. Well-fitted athletic shoes and daily foot inspections are non-negotiable precautions.

    Stay hydrated. Dehydration can concentrate blood glucose and impair your body’s ability to regulate it. Drink water consistently before, during, and after exercise — not just when you feel thirsty.

    Build in rest and recovery. Overtraining — especially for those new to exercise — can trigger excessive stress hormone release, which may raise blood sugar and increase injury risk. Most clinical guidelines suggest at least one or two rest days per week.

    Prepare for hypoglycemia if you take insulin or sulfonylureas. If your medications put you at risk for low blood sugar, carry a fast-acting carbohydrate source (like glucose tablets or a small amount of juice) during exercise. Know the symptoms and what to do. Discuss a hypoglycemia action plan with your care team before you start a new routine.

    Medication adherence also plays a critical role alongside exercise. For a deeper look at how to stay consistent with your diabetes treatment plan, see our article on Optimizing Diabetes Medication Adherence.

    When to Call Your Doctor or Seek Emergency Care

    Exercise is safe for the vast majority of people with type 2 diabetes when approached thoughtfully — but there are specific situations that require prompt medical attention.

    Contact your doctor before your next workout if you notice:

    • Consistent blood sugar readings above 250 mg/dL before exercise (exercise can raise glucose further in this state)
    • New or unusual chest discomfort, shortness of breath, or palpitations during activity
    • A blister, cut, or sore on your foot that is not healing normally
    • Numbness, tingling, or pain in your feet or legs that has worsened
    • Dizziness or near-fainting episodes during or after exercise
    • Recurring low blood sugar (hypoglycemia) episodes around workouts

    Call 911 or go to the emergency room immediately if you experience:

    • Chest pain, pressure, or tightness — especially with exercise
    • Severe shortness of breath not explained by exertion
    • Loss of consciousness or extreme confusion
    • Blood sugar readings that do not respond to treatment (either dangerously low or exceeding 400 mg/dL with symptoms like nausea, vomiting, or fruity-smelling breath)
    • Signs of diabetic ketoacidosis (DKA) — though more common in type 1, it can occur in some people with type 2 under certain conditions

    Never push through worrying symptoms during a workout. Stopping, checking your blood sugar, and contacting your care team is always the right call.

    Frequently Asked Questions

    Q: How quickly does exercise lower blood sugar in type 2 diabetes?
    A: Research suggests that moderate aerobic exercise can begin lowering blood glucose within 10 to 20 minutes of starting activity, with effects lasting anywhere from two to 24 hours afterward depending on the intensity and duration. Individual responses vary, which is why monitoring is so important.

    Q: Is it safe to exercise if my blood sugar is high?
    A: Most clinical guidelines recommend avoiding vigorous exercise if your blood sugar is above 250 mg/dL, particularly if you have ketones present. Light-to-moderate activity may still be appropriate in some situations, but this is a decision to make with your healthcare provider based on your specific medications and history.

    Q: What is the best time of day to exercise with type 2 diabetes?
    A: There is no single universally "best" time — it varies from person to person based on medications, meals, and glucose patterns. Many people find that post-meal activity (particularly after dinner) effectively controls post-meal blood sugar spikes. Morning exercise can be effective but may require closer glucose monitoring before starting. Track your patterns and discuss them with your doctor.

    Q: Can exercise replace diabetes medication?
    A: For some people in the early stages of type 2 diabetes, significant lifestyle changes — including structured exercise and dietary improvements — have allowed them to reduce or, in some cases under close medical supervision, discontinue certain medications. However, this is always a decision made by a physician based on lab values and clinical assessment. You should never stop or reduce medications without your doctor’s explicit guidance.

    Q: What if I have joint pain or mobility limitations that make exercise difficult?
    A: Many people with type 2 diabetes also deal with arthritis, obesity-related joint strain, or neuropathy that limits traditional exercise. Chair-based exercises, water aerobics, and seated resistance training are all clinically validated alternatives that can meaningfully improve blood sugar control. A physical therapist experienced in diabetes care can design a program around your specific limitations.

    Conclusion

    Exercise is not a cure for type 2 diabetes, but it is one of the most powerful management tools available to you — supported by decades of clinical research and endorsed by every major diabetes organization in the United States.

    The key is building a plan that is realistic, sustainable, and tailored to your current health status, medications, and personal preferences. Whether that means a daily walk after dinner, twice-weekly strength training, or chair-based exercises at home, movement matters — and it starts with a single conversation with your healthcare provider.

    You do not have to overhaul your life overnight. Small, consistent steps — supported by medical guidance and your own growing understanding of how your body responds — can lead to meaningful, lasting improvements in your blood sugar control and overall quality of life.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Insulin Resistance: Causes, Signs & How to Reverse It

    Insulin Resistance: Causes, Signs & How to Reverse It

    Understanding insulin resistance could be the most important step you take toward protecting your long-term health.

    Marcus, 47, had been feeling exhausted for months. His doctor told him his fasting blood sugar was “borderline,” and that he should “watch what he eats.” He nodded politely — but walked out of the office not entirely sure what was wrong or what to do next. What Marcus had was insulin resistance, a condition that affects an estimated 88 million American adults, according to the CDC. And like most of them, he had no idea.

    Insulin resistance is one of the most common — and most misunderstood — metabolic conditions in the United States. It sits at the very root of type 2 diabetes, heart disease, and a host of other chronic illnesses. The good news? It is detectable early, and with the right approach, many people can significantly improve their insulin sensitivity before it progresses to full-blown diabetes.

    In this guide, you will learn exactly what insulin resistance is, how to recognize its early signs, what causes it, and — most importantly — what evidence-based steps you and your doctor can take together to manage it effectively.

    What Is Insulin Resistance?

    Insulin is a hormone produced by the pancreas. Its primary job is to act like a key, unlocking your body’s cells so that glucose (sugar from food) can enter and be used for energy. When everything works correctly, your cells respond well to insulin’s signal. Blood sugar stays stable, energy levels remain consistent, and your organs function properly.

    Insulin resistance occurs when your cells — particularly in the muscles, fat, and liver — stop responding normally to insulin. Instead of opening up to let glucose in, they essentially ignore the signal. To compensate, your pancreas produces more and more insulin, trying to force the job done. For a while, blood sugar remains normal. But over time, the pancreas cannot keep up, and blood sugar begins to rise.

    According to the National Institutes of Health (NIH), insulin resistance is a core feature of prediabetes and type 2 diabetes. The CDC estimates that 96 million American adults — more than 1 in 3 — have prediabetes, and approximately 80% don’t know it. Left unaddressed, prediabetes progresses to type 2 diabetes within 5 to 10 years in many individuals.

    Insulin resistance does not just affect blood sugar. It is closely linked to high blood pressure, elevated triglycerides, low HDL (“good”) cholesterol, and increased abdominal fat — a cluster of problems collectively known as metabolic syndrome.

    Signs and Symptoms of Insulin Resistance

    One of the most challenging aspects of insulin resistance is that it often produces no obvious symptoms in its early stages. Many people live with it for years without knowing. However, there are warning signs worth paying attention to.

    Early and common signs may include:

    • Persistent fatigue, especially after meals
    • Intense carbohydrate or sugar cravings
    • Difficulty losing weight, particularly around the abdomen
    • Brain fog or difficulty concentrating
    • Slightly elevated fasting blood sugar (100–125 mg/dL, the prediabetes range)
    • High triglycerides or low HDL cholesterol on a blood panel
    • Elevated blood pressure without an obvious cause

    A notable physical sign to know:

    • Acanthosis nigricans — darkened, velvety patches of skin, typically around the neck, armpits, or groin. This is a visible skin change associated with elevated insulin levels and is recognized by clinicians as a physical marker of insulin resistance.

    A 2021 study published in the journal Diabetes Care found that individuals with insulin resistance frequently show metabolic abnormalities — including elevated fasting insulin levels — years before blood sugar rises into the diabetic range. This underscores the importance of early detection through routine lab work rather than waiting for symptoms to worsen.

    Red flag symptoms that require prompt medical attention:

    • Fasting blood sugar consistently above 126 mg/dL
    • Extreme thirst and frequent urination
    • Blurred vision
    • Unexplained weight loss
    • Numbness or tingling in the hands or feet

    If you experience any of these, contact your healthcare provider without delay — these may indicate that type 2 diabetes has already developed.

    Causes and Risk Factors

    Insulin resistance does not have a single cause. It develops through a combination of genetic predisposition, lifestyle factors, and environmental influences. Understanding what raises your risk is the first step toward prevention.

    Lifestyle-related risk factors:

    • Physical inactivity — Skeletal muscle is the body’s largest consumer of glucose. When muscles are sedentary, they become less sensitive to insulin. The American Diabetes Association (ADA) identifies physical inactivity as one of the most modifiable risk factors for insulin resistance.
    • Excess body fat — Particularly visceral fat (the deep fat surrounding your organs). Fat cells, especially in the abdomen, release inflammatory chemicals that interfere with insulin signaling. Research from Harvard Health suggests that even a 5–7% reduction in body weight can meaningfully improve insulin sensitivity.
    • Poor diet — Diets high in refined carbohydrates, added sugars, and ultra-processed foods repeatedly spike blood glucose, forcing the pancreas to overproduce insulin. Over time, cells downregulate their response.
    • Chronic sleep deprivation — Even a single night of poor sleep has been shown to reduce insulin sensitivity by up to 25%, according to research cited by the NIH.
    • Chronic stress — The stress hormone cortisol raises blood glucose and impairs insulin action.

    Genetic and biological risk factors:

    • Family history of type 2 diabetes
    • Age 45 or older
    • Race and ethnicity — Black, Hispanic, Asian American, and Native American populations face disproportionately higher risk, according to CDC data
    • History of gestational diabetes or polycystic ovary syndrome (PCOS)

    This variation matters: two people with identical lifestyles may develop insulin resistance at very different rates based on genetics. This is why personalized medical guidance is essential.

    Diagnosis: What to Expect

    There is no single standardized test that diagnoses “insulin resistance” directly as a standalone condition. However, your doctor has several reliable tools to assess it and its metabolic consequences.

    Common tests your doctor may order:

    • Fasting blood glucose — A level between 100 and 125 mg/dL indicates prediabetes; 126 mg/dL or higher on two separate tests indicates type 2 diabetes.
    • Hemoglobin A1C (HbA1c) — Reflects average blood sugar over the past 2–3 months. A result between 5.7% and 6.4% signals prediabetes. You can learn more about what your A1C number means in our detailed guide: A1C Levels Explained: What Every Diabetic Must Know.
    • Fasting insulin level — Not always routine, but an elevated fasting insulin alongside normal blood sugar is a strong indicator of insulin resistance. Your doctor may calculate a HOMA-IR score (Homeostatic Model Assessment of Insulin Resistance) using glucose and insulin values together.
    • Lipid panel — High triglycerides (above 150 mg/dL) and low HDL cholesterol are metabolic hallmarks of insulin resistance.
    • Oral Glucose Tolerance Test (OGTT) — Measures how your body processes glucose over two hours after drinking a sugary solution. Often used in diagnosing gestational diabetes but can reveal prediabetes in non-pregnant adults as well.

    The American Diabetes Association recommends screening for prediabetes and type 2 diabetes in all adults starting at age 35, or earlier if risk factors are present. If you have not been screened recently, discuss this with your physician at your next visit.

    Treatment Options for Insulin Resistance

    The most powerful treatments for insulin resistance combine medical oversight with meaningful lifestyle changes. There is no one-size-fits-all approach — what works best varies from person to person — but the evidence is clear that early, consistent action makes a measurable difference.

    Conventional medical treatments:

    Metformin is the most commonly prescribed medication for prediabetes and early type 2 diabetes in the US. Clinical evidence indicates it works by reducing the liver’s overproduction of glucose and improving the body’s response to insulin. The Diabetes Prevention Program (DPP) — a landmark NIH-funded clinical trial — showed that metformin reduced progression from prediabetes to type 2 diabetes by 31% over three years. Your doctor will determine whether medication is appropriate for your specific situation.

    Newer medication classes, including GLP-1 receptor agonists (such as semaglutide) and SGLT-2 inhibitors, have shown strong clinical evidence not only for improving blood sugar control but also for reducing cardiovascular risk in people with type 2 diabetes. If you are already living with diabetes and managing medications, our article on Optimizing Diabetes Medication Adherence offers practical strategies to help you stay on track.

    Lifestyle modifications — the cornerstone of treatment:

    Physical activity is arguably the most effective tool for improving insulin sensitivity. Muscle contractions during exercise allow glucose to enter cells independently of insulin. The ADA recommends at least 150 minutes of moderate-intensity aerobic exercise per week, plus 2–3 days of resistance training. Research suggests that even a single 30-minute brisk walk can temporarily improve insulin sensitivity in people with prediabetes.

    Dietary changes should focus on reducing refined carbohydrates and added sugars, increasing fiber intake (vegetables, legumes, whole grains), including healthy fats (olive oil, avocado, nuts), and choosing lean proteins. The Mediterranean dietary pattern, in particular, has robust clinical evidence supporting improved insulin sensitivity and reduced risk of type 2 diabetes.

    Weight management remains a high-impact target. The DPP trial demonstrated that a 5–7% reduction in body weight through diet and exercise reduced diabetes risk by 58% in high-risk adults — nearly double the effect of metformin alone. If weight management feels like a persistent challenge, our resource on Sustainable Weight Loss: Habits for Lasting Health provides evidence-based strategies worth exploring with your care team.

    Sleep optimization — Prioritizing 7–9 hours of quality sleep per night is not optional when managing insulin resistance. Clinical evidence consistently links poor sleep to elevated fasting glucose and impaired insulin action.

    Stress management — Chronic stress keeps cortisol levels elevated, which perpetuates insulin resistance. Mindfulness, structured breathing exercises, therapy, and regular physical activity are all evidence-supported approaches.

    Living With Insulin Resistance: Day-to-Day Management

    Managing insulin resistance is not a short-term project — it is an ongoing lifestyle practice. But many people who commit to it experience substantial improvements in energy, weight, and metabolic health within weeks to months.

    Practical daily habits that support better insulin sensitivity:

    • Eat balanced meals that pair carbohydrates with protein and fiber to blunt glucose spikes
    • Avoid long periods of sitting — stand or walk for a few minutes every hour
    • Keep a consistent sleep schedule, even on weekends
    • Limit alcohol, which can worsen insulin resistance and raise triglycerides
    • Monitor your blood sugar if your doctor recommends it — awareness is a powerful motivator
    • Schedule regular follow-up labs (A1C, fasting glucose, lipid panel) at least annually, or as advised

    Prevention matters here too. If you have risk factors but have not yet been diagnosed with prediabetes, the same lifestyle strategies apply. Clinical evidence shows that the earlier you intervene, the more effectively you can protect your metabolic health long-term.

    When to Call Your Doctor: Emergency Signs

    Insulin resistance itself is rarely a medical emergency. However, if it has progressed — or if it is accompanied by other conditions — certain symptoms demand immediate attention.

    Call 911 or go to the emergency room immediately if you experience:

    • Confusion, disorientation, or loss of consciousness (possible hypoglycemia if you take diabetes medications)
    • Chest pain or pressure, shortness of breath, or sudden arm pain (signs of cardiac event, which people with insulin resistance are at higher cardiovascular risk for)
    • Difficulty speaking or sudden weakness on one side of the body (possible stroke)

    Schedule a prompt (non-emergency) appointment with your doctor if you notice:

    • New or worsening fatigue, thirst, or frequent urination
    • Blood sugar readings consistently outside your target range
    • New darkening of the skin around the neck or armpits
    • Unexplained weight changes
    • A fasting glucose reading above 100 mg/dL for the first time

    At your next routine appointment, consider telling your doctor: “I’d like to check my fasting glucose, A1C, insulin level, and full lipid panel. I’m concerned about my risk for insulin resistance and want to be proactive.”

    Frequently Asked Questions

    Q: Can insulin resistance be reversed completely?
    A: Research suggests that insulin resistance — particularly in its early stages — can be significantly improved, and in some cases effectively normalized, through sustained lifestyle changes including weight loss, regular exercise, and dietary modification. However, “reversal” is a complex term, and individual results vary. Most physicians prefer the term “remission” or “improved insulin sensitivity.” Ongoing monitoring remains important even after improvement.

    Q: Is insulin resistance the same as type 2 diabetes?
    A: Not exactly. Insulin resistance is a precursor condition that, if left unmanaged, can progress to type 2 diabetes. Type 2 diabetes is diagnosed when blood sugar reaches chronically elevated levels and the pancreas can no longer compensate. Think of insulin resistance as a warning sign — an opportunity to act before diabetes develops.

    Q: What foods should I avoid if I have insulin resistance?
    A: Clinical guidance generally recommends limiting refined carbohydrates (white bread, white rice, pastries), sugary beverages, ultra-processed snacks, and foods high in added sugars. These foods cause rapid blood glucose spikes that stress the insulin system. This varies from person to person, and a registered dietitian can help you build a personalized eating plan.

    Q: Can thin people develop insulin resistance?
    A: Yes. While excess body fat — especially visceral abdominal fat — is a major risk factor, insulin resistance can occur in people with a normal body weight. This is sometimes called “metabolically unhealthy normal weight” or TOFI (thin outside, fat inside). Genetics, physical inactivity, and diet quality all play a role regardless of body size.

    Q: How long does it take to improve insulin sensitivity?
    A: Clinical evidence indicates that meaningful improvements in insulin sensitivity can occur within 4–12 weeks of consistent aerobic exercise and dietary changes, even before significant weight loss occurs. Muscle-building exercise may show results even sooner. However, maintaining these improvements requires ongoing lifestyle commitment — not a short-term fix.

    The Bottom Line

    Insulin resistance is one of the most prevalent and consequential metabolic conditions affecting American adults today — and one of the most actionable. The path forward is not about perfection; it is about consistent, evidence-based steps taken alongside your healthcare team. From improving your sleep and moving more each day, to working with your doctor on the right screening and treatment plan, every decision compounds over time.

    You do not have to wait until a diabetes diagnosis arrives to take your metabolic health seriously. If Marcus’s story sounds familiar, use it as motivation. Talk to your doctor. Get your labs. Ask questions. Early awareness and informed action are two of the most powerful tools available to you — and they start today.

    Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.


    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.