Category: Diabetes Management

Learn how to manage diabetes with nutrition tips, blood sugar monitoring, medications, healthy habits, and expert guidance.

  • Diabetic Retinopathy: Protect Your Vision With Diabetes

    Diabetic Retinopathy: Protect Your Vision With Diabetes

    Millions of Americans with diabetes are unknowingly putting their eyesight at risk — and a simple annual eye exam could change everything.

    Introduction

    Margaret, 54, had managed her type 2 diabetes for over a decade. She took her metformin faithfully, watched her carb intake, and showed up for most of her primary care appointments. But she hadn’t seen an eye doctor in four years — because her vision seemed just fine.

    Then, almost overnight, she noticed blurry patches in her right eye. By the time she finally saw an ophthalmologist, she had moderate diabetic retinopathy in both eyes and was at serious risk of permanent vision loss.

    Margaret’s story is not unusual. According to the CDC, diabetic retinopathy is the leading cause of new blindness among American adults aged 20 to 74. Yet research suggests that up to 90% of diabetes-related vision loss is preventable with timely screening and proper blood sugar management.

    In this guide, you’ll learn exactly what diabetic retinopathy is, how it develops, what symptoms to watch for, and — most importantly — how you can protect your vision starting today.

    What Is Diabetic Retinopathy?

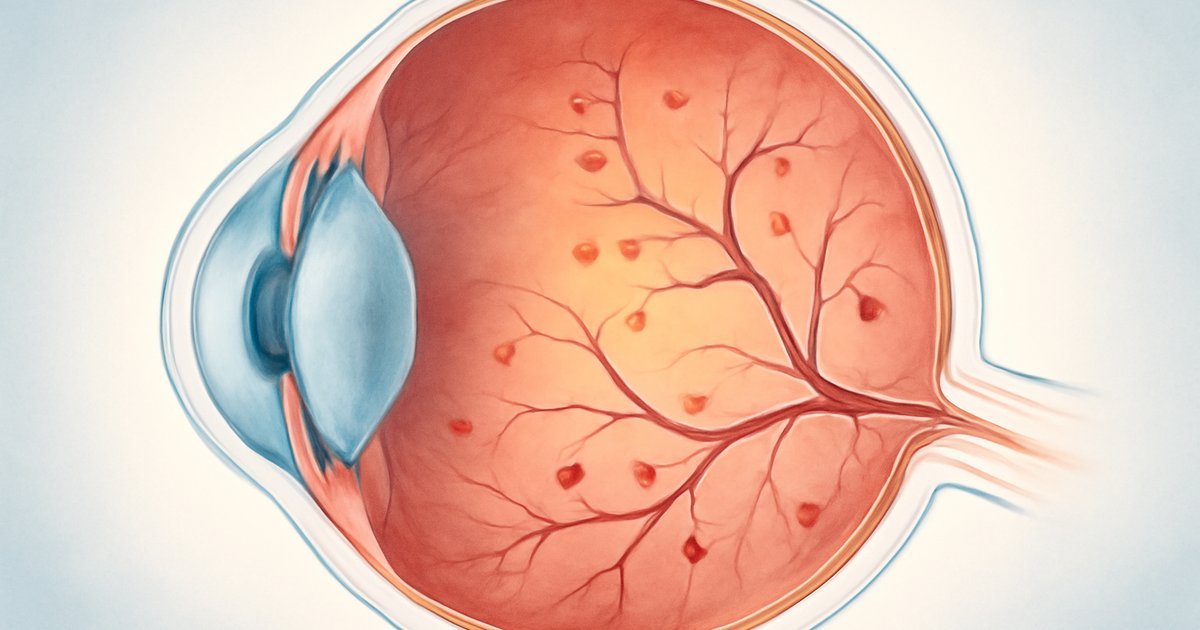
    Diabetic retinopathy is a diabetes complication that damages the blood vessels in the retina — the thin, light-sensitive layer of tissue at the back of your eye. When blood sugar levels remain chronically elevated, those tiny vessels can swell, leak fluid, or grow abnormally, all of which can distort or destroy your vision over time.

    The condition progresses in two main stages. Non-proliferative diabetic retinopathy (NPDR) is the earlier stage, where blood vessels in the retina weaken and may leak. Proliferative diabetic retinopathy (PDR) is the advanced stage, where new, abnormal blood vessels grow on the surface of the retina — a process called neovascularization — which dramatically increases the risk of severe vision loss or detachment of the retina.

    According to the National Eye Institute (NEI), an arm of the NIH, approximately 7.7 million Americans have diabetic retinopathy, and that number is projected to reach nearly 14.6 million by 2050. Both type 1 and type 2 diabetes can cause the condition, though the longer you’ve lived with diabetes, the higher your risk becomes.

    What makes diabetic retinopathy particularly dangerous is that it causes no pain and minimal early symptoms — meaning most people don’t realize anything is wrong until significant damage has already occurred.

    Signs and Symptoms: What to Watch For

    Because diabetic retinopathy often progresses silently, many people only notice symptoms once the disease has advanced. Understanding the full spectrum of warning signs — from subtle early changes to urgent red flags — can help you seek care at the right time.

    Early signs (may be subtle or absent):

    • Slightly blurry vision that comes and goes
    • Difficulty reading fine print or seeing close objects
    • Colors appearing washed out or less vibrant
    • Small dark spots or "floaters" in your field of vision
    • Difficulty seeing well in low-light conditions

    Advanced signs (require urgent medical attention):

    • Sudden or rapid vision loss in one or both eyes
    • A large number of new floaters appearing suddenly
    • Flashes of light in your vision
    • A dark curtain or shadow appearing across part of your visual field
    • Severe blurring that does not improve

    A 2021 clinical study published through the American Academy of Ophthalmology found that nearly 40% of people with type 2 diabetes who were newly diagnosed with retinopathy reported having experienced no noticeable visual symptoms before their diagnosis. This underscores why routine eye exams are so critical — your eyes may be changing even when your vision feels normal.

    Causes and Risk Factors

    The root cause of diabetic retinopathy is sustained high blood sugar. Over time, excess glucose in the bloodstream damages the walls of the small blood vessels that supply the retina. These weakened vessels may swell, develop tiny bulges called microaneurysms, or leak blood and fluid into surrounding retinal tissue.

    But not every person with diabetes develops retinopathy at the same rate or severity. Several factors can significantly increase your risk:

    • Duration of diabetes: The longer you’ve had diabetes, the higher your cumulative risk. The NIH reports that nearly all people with type 1 diabetes and more than 60% of those with type 2 diabetes will develop some degree of retinopathy after 20 years.
    • Poor blood sugar control: Chronically elevated A1C levels (a measure of average blood sugar over roughly three months) are one of the strongest predictors of retinopathy progression.
    • High blood pressure (hypertension): Elevated blood pressure compounds damage to retinal blood vessels and is extremely common among people with diabetes.
    • High cholesterol: Elevated LDL cholesterol increases the likelihood of hard exudates — fatty deposits — forming in the retina.
    • Pregnancy: Gestational diabetes or pre-existing diabetes during pregnancy can accelerate retinopathy development.
    • Smoking: Tobacco use constricts blood vessels and worsens microvascular complications throughout the body, including the eyes.
    • Ethnicity: According to the CDC, African Americans, Hispanic/Latino Americans, and Native Americans face disproportionately higher rates of diabetic eye disease.
    • Kidney disease: Diabetic nephropathy (kidney damage from diabetes) often occurs alongside retinopathy, as both stem from the same microvascular damage mechanisms.

    It’s worth noting that individual variation plays a significant role here. Two people with identical A1C levels and the same duration of diabetes may experience very different rates of retinal damage — which is why personalized care with your healthcare team matters so much.

    Diagnosis: What to Expect at the Eye Doctor

    Diagnosing diabetic retinopathy requires a comprehensive dilated eye exam — a procedure in which your eye doctor uses special drops to widen (dilate) your pupils, giving them a clear view of your retina and the blood vessels within it. This exam is painless, though your vision may remain blurry for a few hours afterward.

    Here’s what the diagnostic process typically involves:

    • Visual acuity test: A standard eye chart test to measure how well you see at various distances.
    • Dilated fundus examination: The doctor uses a special lens to examine the retina, optic nerve, and blood vessels directly.
    • Optical coherence tomography (OCT): A non-invasive imaging scan that produces detailed cross-section images of the retina, allowing detection of swelling (macular edema) and structural changes.
    • Fluorescein angiography: A dye is injected into the arm and photographs track how it flows through the retinal blood vessels, revealing leaks or abnormal growth areas.

    The American Diabetes Association (ADA) recommends that adults with type 2 diabetes get a dilated eye exam at the time of diagnosis and annually thereafter. People with type 1 diabetes should begin annual exams within five years of diagnosis. If retinopathy is detected, your ophthalmologist may recommend more frequent monitoring — sometimes every three to six months.

    If you’ve been skipping these exams, you’re far from alone. Research suggests that fewer than half of Americans with diabetes receive the recommended annual dilated eye exams. Consistent blood sugar monitoring goes hand in hand with eye exams as a cornerstone of diabetes management.

    Treatment Options for Diabetic Retinopathy

    The good news is that diabetic retinopathy responds well to treatment, especially when caught early. Your treatment plan will depend on the stage of the disease and whether diabetic macular edema (swelling at the center of the retina) is present.

    1. Blood sugar and blood pressure management
    For early-stage retinopathy, the most effective "treatment" is tighter control of blood glucose and blood pressure. Clinical evidence from the landmark DCCT (Diabetes Control and Complications Trial) and UKPDS (UK Prospective Diabetes Study) showed that intensive blood sugar control reduced the risk of retinopathy progression by 50–76% compared to conventional management. Most physicians recommend an A1C target below 7% for most adults with diabetes, though your personal target may vary.

    2. Anti-VEGF injections
    For moderate to severe retinopathy or diabetic macular edema, anti-VEGF (vascular endothelial growth factor) therapy is now the standard of care. Medications such as ranibizumab, aflibercept, and bevacizumab are injected directly into the eye to block the growth of abnormal blood vessels and reduce leakage. Clinical trials have shown these injections can significantly stabilize and even improve vision in many patients.

    3. Laser photocoagulation therapy
    Laser treatment has been used for decades to seal leaking blood vessels and shrink abnormal ones. Focal laser treatment targets specific leaking vessels, while panretinal photocoagulation (PRP) treats the peripheral retina to reduce the drive for abnormal vessel growth. While laser therapy is less commonly used as a first-line treatment since anti-VEGF injections became available, it remains an important option in many cases.

    4. Vitrectomy surgery
    In advanced cases where there is bleeding into the vitreous (the gel-like substance filling the eye) or a retinal detachment, a surgical procedure called vitrectomy may be necessary. The surgeon removes the vitreous and any scar tissue, and in some cases reattaches the retina. According to the NIH, vitrectomy significantly improves visual outcomes in patients with severe proliferative diabetic retinopathy when performed in a timely manner.

    5. Lifestyle modifications as complements
    While not a replacement for medical treatment, lifestyle changes provide meaningful support for retinopathy management. Regular physical activity, a diet low in refined carbohydrates and high in antioxidant-rich vegetables, smoking cessation, and stress reduction all contribute to better blood sugar control and vascular health. Emerging research also suggests that omega-3 fatty acids and certain antioxidant nutrients like lutein and zeaxanthin may support retinal health, though clinical evidence is still evolving.

    Living With Diabetic Retinopathy and Preventing Progression

    A diagnosis of diabetic retinopathy doesn’t have to mean inevitable vision loss. With proactive management and the right support team, many people successfully preserve their vision for years — and in some cases, decades.

    Here are practical, evidence-informed strategies for day-to-day management:

    • Keep your A1C in your target range. Work with your doctor to find the right A1C goal for your individual situation. Even a modest reduction in A1C — say, from 9% to 7.5% — can meaningfully slow retinopathy progression.
    • Control your blood pressure. The ADA recommends a blood pressure target of less than 130/80 mmHg for most adults with diabetes. High blood pressure dramatically accelerates retinal vessel damage.
    • Manage cholesterol levels. Elevated LDL cholesterol is linked to harder-to-treat retinal deposits. Statins and dietary changes are commonly recommended.
    • Never skip your annual eye exam. Even if your vision feels perfectly fine. Even if you’ve had no symptoms. This single habit may be the most important thing you can do for your long-term eye health.
    • Quit smoking — or never start. Smoking significantly worsens every diabetes complication, including retinopathy. Speak with your doctor about cessation resources.
    • Tell your eye doctor about all your medications. Some medications can affect the eyes, and your ophthalmologist needs a full picture of your health.
    • Consider adaptive aids if needed. If vision loss affects daily activities, occupational therapists and low-vision specialists can help you adapt and maintain independence.

    It’s also worth connecting your eye care with your broader diabetes management. Your ophthalmologist and endocrinologist or primary care physician should be communicating about your case — don’t hesitate to ask them to coordinate. Managing conditions like diabetes and heart disease risk alongside retinopathy requires a team-based approach.

    When to Call Your Doctor — Emergency Signs

    Some vision changes related to diabetic retinopathy require immediate medical attention. Do not wait for a scheduled appointment if you experience any of the following:

    • Sudden loss of vision in one or both eyes
    • A sudden shower of new floaters or flashes of light
    • A dark shadow, curtain, or veil appearing across any part of your vision
    • Vision that becomes rapidly and severely blurry without an obvious cause

    These symptoms may indicate a vitreous hemorrhage (bleeding inside the eye), retinal detachment, or acute macular edema — all of which are ophthalmologic emergencies that require same-day evaluation. Call your ophthalmologist immediately or go to an emergency room if you cannot reach your eye doctor.

    At your next routine visit — even if no emergencies occur — consider discussing the following with your doctor:

    • Your current A1C and whether your blood sugar management plan needs adjustment
    • Your blood pressure and cholesterol numbers and targets
    • Whether you’re due for a dilated eye exam
    • Any changes in your vision, however minor they may seem
    • Whether lifestyle changes could further reduce your retinopathy risk

    Alcohol use is another factor worth discussing — it can affect blood sugar unpredictably. You can learn more in our detailed overview of how alcohol affects blood sugar in diabetes.

    Frequently Asked Questions

    Can diabetic retinopathy be reversed?
    In some cases, early-stage diabetic retinopathy can partially improve with tighter blood sugar control. However, more advanced stages typically cannot be fully reversed — the goal becomes halting progression and preserving remaining vision. Anti-VEGF injections have shown the ability to improve vision in many patients with diabetic macular edema, but results vary from person to person.

    How fast does diabetic retinopathy progress?
    Progression varies widely depending on individual factors like blood sugar control, blood pressure, duration of diabetes, and genetics. Some people remain in the early non-proliferative stage for many years with minimal change, while others progress more rapidly — especially without consistent medical management.

    Can I develop diabetic retinopathy if my blood sugar is well controlled?
    Research suggests that good blood sugar control significantly reduces risk, but does not eliminate it entirely. Some individuals develop retinopathy even with tight glucose management, particularly if they have other risk factors like hypertension or a long duration of diabetes. This is exactly why annual eye exams remain essential even when your A1C is in range.

    Is diabetic retinopathy the same as diabetic macular edema?
    No — but they’re closely related. Diabetic macular edema (DME) is a specific complication of diabetic retinopathy in which fluid leaks into the macula, the central part of the retina responsible for sharp, detailed vision. DME can occur at any stage of retinopathy and is a leading cause of vision loss in people with diabetes.

    Do anti-VEGF injections hurt?
    Most patients find anti-VEGF eye injections less painful than anticipated. The eye is numbed with anesthetic drops before the procedure, and the injection itself typically takes only seconds. Some patients experience mild pressure or discomfort during or after the injection, but severe pain is uncommon. If you have concerns, discuss them openly with your ophthalmologist.

    Conclusion

    Diabetic retinopathy is one of the most serious — and most preventable — complications of diabetes. The science is clear: consistent blood sugar control, blood pressure management, and annual dilated eye exams are your most powerful tools for protecting your vision.

    If you’ve been putting off an eye exam, let Margaret’s story be your reminder. Vision loss doesn’t announce itself with early warning signs. But the good news is that you have the ability to stay ahead of it — with the right habits, the right care team, and the right information.

    Talk to your primary care physician or endocrinologist about coordinating care with an ophthalmologist, and don’t leave your next appointment without asking about your eye health. Your future self will thank you.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.


  • Diabetes and Alcohol: What Every Diabetic Must Know

    Diabetes and Alcohol: What Every Diabetic Must Know

    Diabetes and Alcohol: What Every Diabetic Must Know

    Understanding how alcohol interacts with blood sugar could prevent a dangerous — and surprisingly common — medical emergency.

    Marcus, 54, had managed his type 2 diabetes for six years without a serious incident. Then, at a holiday party, he had a few drinks with dinner — skipped a snack before bed — and woke up at 2 a.m. in a cold sweat, confused and shaking. His wife recognized the signs of low blood sugar and acted quickly. Marcus was lucky. Not everyone is.

    According to the CDC, more than 38 million Americans are living with diabetes, and surveys from the National Institute on Alcohol Abuse and Alcoholism (NIAAA) suggest that adults with diabetes drink at rates similar to the general population. Yet many people with diabetes receive little guidance about how alcohol interacts with blood sugar, medications, and long-term complications.

    This article will walk you through exactly how alcohol affects blood sugar control, which risks matter most, how to drink more safely if you choose to, and when alcohol should be avoided entirely. If you’re managing diabetes — or caring for someone who is — this information could be lifesaving.

    How Alcohol Affects Blood Sugar: The Science Behind the Risk

    To understand why alcohol and diabetes can be a dangerous combination, it helps to know what your liver does when you drink.

    Normally, your liver has two jobs running in the background: processing substances in your blood and releasing stored glucose (glycogen) to keep blood sugar from dropping too low. When you drink alcohol, the liver prioritizes metabolizing the alcohol above everything else — including releasing that stored glucose.

    The result? Blood sugar can drop significantly, especially if you’ve taken insulin or certain oral diabetes medications. This condition — called hypoglycemia (low blood sugar, typically below 70 mg/dL) — can develop slowly over several hours and may occur while you’re asleep, making it particularly dangerous.

    A meta-analysis published in the journal Diabetes Care found that alcohol consumption was associated with a significantly increased risk of hypoglycemic episodes in people with both type 1 and type 2 diabetes, particularly when alcohol was consumed without food. Clinical evidence also indicates that the liver’s glucose-releasing function can remain impaired for up to 24 hours after drinking — meaning the risk doesn’t end when the party does.

    On the flip side, some alcoholic beverages — especially sugary cocktails, sweet wines, beer, and mixed drinks with juice — can cause a temporary spike in blood sugar before the hypoglycemic effect kicks in. This two-phase swing is one of the reasons alcohol makes diabetes management particularly unpredictable.

    Signs and Symptoms: Hypoglycemia vs. Intoxication

    One of the most dangerous aspects of alcohol and diabetes is how easily their symptoms overlap — and how often one is mistaken for the other.

    Symptoms of hypoglycemia include:

    • Shakiness or trembling
    • Sweating, especially at night
    • Dizziness or lightheadedness
    • Confusion or slurred speech
    • Rapid heartbeat
    • Irritability or sudden mood changes
    • Pale or clammy skin
    • In severe cases: unconsciousness or seizure

    Notice that confusion, slurred speech, and unsteady gait — all classic signs of low blood sugar — are also classic signs of alcohol intoxication. Friends, family members, even emergency personnel may misread a hypoglycemic episode as drunkenness, delaying critical treatment.

    Research from the American Diabetes Association (ADA) reinforces that people with diabetes should always carry fast-acting glucose (such as glucose tablets or juice) when drinking and should wear a medical ID bracelet indicating their condition so that first responders can make an accurate assessment quickly.

    If you’re experiencing confusion or shaking and you’re unsure whether it’s low blood sugar or alcohol, treat for low blood sugar first — eating 15 grams of fast-acting carbohydrates — and check your glucose if possible. Never assume it’s just the alcohol.

    Causes of Increased Risk: Who Is Most Vulnerable

    Not all people with diabetes face the same level of risk from alcohol. Several factors increase your vulnerability significantly.

    Medication type matters enormously. People taking insulin or sulfonylureas (a class of oral medications that stimulate insulin production, including glipizide and glimepiride) face the highest risk of alcohol-induced hypoglycemia. The combination of these medications with alcohol’s glucose-suppressing effect on the liver can cause blood sugar to plunge rapidly.

    Drinking on an empty stomach dramatically amplifies this effect. Without food slowing alcohol absorption and providing carbohydrates to maintain blood sugar, the liver’s impaired glucose release becomes critical.

    Additional risk factors include:

    • Long duration of diabetes — people who have had diabetes for many years may have impaired counter-regulatory hormone responses (the hormones that normally kick in to raise blood sugar)
    • Kidney disease or liver disease — both affect how alcohol and glucose are metabolized
    • Autonomic neuropathy — nerve damage affecting internal organ function can blunt the warning symptoms of hypoglycemia
    • Older age — adults over 60 tend to metabolize alcohol more slowly and may have less awareness of hypoglycemia symptoms
    • Skipping meals or eating very little — common when drinking socially

    According to the NIH, heavy alcohol use — defined as more than 14 drinks per week for men and more than 7 per week for women — is also independently associated with worsening insulin resistance and a higher risk of developing diabetic complications. This risk compounds over time.

    Diagnosis and Monitoring: What Your Numbers Tell You

    If you have diabetes and you drink alcohol, consistent blood sugar monitoring becomes even more critical. Your healthcare provider may recommend more frequent checks on days when you drink — and especially before bed.

    Most physicians recommend that people with diabetes who choose to drink alcohol should:

    • Check blood sugar before drinking
    • Check blood sugar during the event if drinking extends more than 1-2 hours
    • Check blood sugar before bed — and eat a carbohydrate-containing snack if glucose is at or below 100 mg/dL
    • Set an alarm or ask a partner to check on you overnight if you’ve consumed more than one drink

    Continuous glucose monitors (CGMs) — devices worn on the skin that track glucose levels in real time — are particularly valuable tools for people who drink. They provide alerts when blood sugar is dropping, even during sleep. For a comprehensive understanding of monitoring tools available to you, our guide on Blood Sugar Monitoring for Type 2 Diabetes covers CGMs, fingerstick devices, and how to interpret your readings.

    Your doctor may also monitor your A1C (a measure of average blood sugar over 2-3 months) more closely if you drink regularly, since chronic alcohol use is associated with greater A1C variability and harder-to-control blood sugar levels.

    Treatment and Management: Drinking More Safely With Diabetes

    The American Diabetes Association does not tell all people with diabetes to abstain from alcohol entirely — but it does provide clear guidelines for those who choose to drink. Here is what clinical evidence supports:

    Stick to moderate drinking limits. The ADA recommends no more than one drink per day for women and two drinks per day for men. One standard drink equals 12 oz of regular beer, 5 oz of wine, or 1.5 oz of spirits.

    Never drink on an empty stomach. Always consume alcohol with a meal or substantial snack containing protein, fat, and complex carbohydrates. This slows alcohol absorption and helps buffer blood sugar drops.

    Choose lower-carbohydrate options. Dry wines, light beers, and spirits mixed with sparkling water or club soda are preferable to sweet cocktails, sugary mixers, or craft beers, which can contain 20-30 grams of carbohydrates per serving and cause unpredictable blood sugar spikes.

    Avoid binge drinking entirely. Consuming four or more drinks in a short period overwhelms the liver’s capacity and dramatically increases hypoglycemia risk over the next several hours. Research suggests that even one heavy episode can destabilize blood sugar control for more than 24 hours.

    Tell someone you trust. When you’re out, let a friend or family member know you have diabetes. Make sure they know the signs of hypoglycemia and what to do — including calling 911 if you become unconscious.

    Talk to your pharmacist and doctor about your medications. Some diabetes medications interact with alcohol beyond hypoglycemia risk. Metformin, for example, carries a rare but serious risk of lactic acidosis (a dangerous buildup of lactic acid in the blood) in people who drink heavily or have liver disease. Your healthcare provider can help you understand your specific medication interactions.

    Pair these strategies with a well-structured eating plan. Our resource on Diabetes Meal Planning: Build a Plate That Controls Blood Sugar can help you build meals that provide a stable glucose foundation — especially on days when you plan to drink.

    Living With Diabetes: Long-Term Alcohol and Complication Risk

    Beyond blood sugar swings, regular alcohol use affects the long-term trajectory of diabetes and its complications in several important ways.

    Heart health: People with diabetes already face two to four times the risk of cardiovascular disease compared to those without, according to the American Heart Association. Heavy alcohol use raises blood pressure, increases triglycerides, and contributes to irregular heart rhythms — all of which worsen cardiovascular risk. Moderate alcohol consumption has been studied for potential heart-protective effects, but most cardiologists and endocrinologists advise against drinking for heart health, particularly in people who already have elevated risk.

    Liver health: The liver plays a central role in both glucose metabolism and detoxification. Non-alcoholic fatty liver disease (NAFLD) — which is closely linked to insulin resistance — is already common in people with type 2 diabetes. Adding alcohol to the equation can accelerate liver damage and worsen insulin resistance further.

    Nerve health: Diabetic peripheral neuropathy (nerve damage, often in the feet and legs) is a complication affecting up to 50% of people with diabetes over their lifetime, according to the NIH. Alcohol is itself a neurotoxin and can accelerate nerve damage independently of blood sugar control — making it a particularly harmful combination for people already managing neuropathy.

    Mental health: Research published in Diabetes Care found that depression is two to three times more common in people with diabetes than in the general population. Alcohol is a central nervous system depressant, and while it may feel like it reduces stress or anxiety in the short term, regular use worsens depression and anxiety over time — making diabetes self-management harder. Stress itself worsens blood sugar control, as explored in our article on how cortisol and stress affect metabolic health.

    When to Call Your Doctor — and When to Call 911

    Some situations require immediate emergency response. Do not wait to call 911 if someone with diabetes who has been drinking shows any of the following:

    • Loss of consciousness or unresponsiveness
    • Seizure
    • Extreme confusion or inability to communicate
    • Blood sugar below 50 mg/dL that does not respond to oral glucose treatment
    • Severe vomiting that prevents oral treatment for low blood sugar

    Call your doctor — non-emergently but promptly — if you notice:

    • Repeated hypoglycemic episodes after drinking, even mild ones
    • Greater-than-usual difficulty controlling blood sugar on days following alcohol use
    • Signs of worsening neuropathy, such as increased numbness or tingling in the feet
    • Any signs of liver problems: yellowing skin, dark urine, abdominal pain
    • You feel you cannot reduce or stop drinking even when you want to

    That last point matters significantly. The NIAAA estimates that approximately 14.5 million Americans aged 12 and older have alcohol use disorder. If alcohol has become difficult to control, speaking honestly with your doctor opens the door to effective, evidence-based treatment options — including behavioral therapy and FDA-approved medications — without judgment.

    Frequently Asked Questions

    Can people with type 2 diabetes drink alcohol at all?
    Many people with well-controlled type 2 diabetes can consume alcohol in moderation — one drink per day for women, two for men — according to ADA guidelines. However, this varies significantly depending on your medications, kidney and liver health, and current blood sugar control. Always discuss this with your physician before drinking.

    Does alcohol raise or lower blood sugar?
    Both, depending on timing and what you drink. In the short term, sugary alcoholic beverages can raise blood sugar. Over the following hours, alcohol suppresses the liver’s ability to release stored glucose, which can cause a significant and dangerous drop in blood sugar — especially overnight. This two-phase effect makes monitoring critical.

    What is the safest alcoholic drink for someone with diabetes?
    Clinical evidence suggests that dry wines, light beers, and spirits mixed with zero-calorie mixers (like sparkling water or diet soda) have less impact on blood sugar than sweet cocktails, regular beer, or sugary mixed drinks. However, no alcohol is entirely safe, and individual responses vary significantly. This varies from person to person based on metabolism, medications, and overall health.

    How long does alcohol affect blood sugar after drinking?
    Research suggests the liver’s glucose-releasing function can be impaired for up to 12-24 hours after drinking. This means a person with diabetes may experience hypoglycemia the morning after a night of drinking — even without feeling intoxicated. Monitoring blood sugar the following morning is strongly recommended.

    Should I adjust my diabetes medication when I drink?
    Never adjust your medication dose on your own based on alcohol consumption. Speak with your doctor or pharmacist about your specific situation. Some adjustments may be appropriate, but this decision requires medical supervision and depends on your specific drug regimen, kidney function, and glucose control history.

    Conclusion

    Alcohol and diabetes can coexist — but only with knowledge, planning, and honest conversations with your healthcare team. The risks are real and specific: hypoglycemia that looks like intoxication, overnight blood sugar crashes, worsening nerve damage, and harder-to-control A1C levels. But the risks are also manageable when you understand them.

    You don’t have to feel isolated or uncertain about this topic. Bring your questions about alcohol to your next doctor’s appointment. Be honest about how much and how often you drink. Ask about your specific medications and what interactions matter for you.

    With the right information and the right support team, you can make informed choices that protect your health — without sacrificing your quality of life.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Blood Sugar Monitoring for Type 2 Diabetes: A Complete Guide

    Blood Sugar Monitoring for Type 2 Diabetes: A Complete Guide

    Understanding when, how, and why to check your blood glucose can be the difference between managing your diabetes effectively and letting it silently damage your body.

    Marcus, 54, had been living with type 2 diabetes for six years. He checked his blood sugar every morning, saw a number he liked, and assumed everything was fine. It wasn’t until his annual A1C test came back at 8.9% that his doctor explained the truth: a single morning reading tells only a fraction of the story. Marcus’s blood sugar was spiking dramatically after every meal — and he had no idea.

    His experience is far from unique. According to the CDC, more than 38 million Americans have diabetes, and the vast majority have type 2. Of those, millions are monitoring their blood glucose incorrectly — either too infrequently, at the wrong times, or without understanding what the numbers actually mean.

    This guide will walk you through everything you need to know about blood sugar monitoring for type 2 diabetes: how it works, when to check, what your numbers mean, which tools are available in 2026, and when to call your doctor. Whether you’re newly diagnosed or have been managing diabetes for years, this information could fundamentally change how well you control your condition.

    What Is Blood Sugar Monitoring — and Why Does It Matter?

    Blood sugar monitoring — also called blood glucose monitoring — is the process of measuring the concentration of glucose (sugar) in your blood at a specific moment in time. This measurement, typically expressed in milligrams per deciliter (mg/dL), gives you and your healthcare team direct feedback on how your body is managing glucose.

    In type 2 diabetes, the body either doesn’t produce enough insulin or doesn’t use insulin effectively — a condition known as insulin resistance. As a result, glucose builds up in the bloodstream instead of being absorbed by cells for energy. Over time, chronically elevated blood sugar damages blood vessels, nerves, kidneys, eyes, and the heart.

    Monitoring gives you the power to act before that damage accumulates. According to the American Diabetes Association (ADA), regular self-monitoring of blood glucose is a cornerstone of diabetes self-management and helps people make informed decisions about food, activity, medication, and stress management.

    Research suggests that patients who monitor more consistently tend to have better glycemic (blood sugar) control and lower rates of diabetes-related complications — though this varies from person to person depending on treatment plan, lifestyle, and individual physiology.

    Signs That Your Blood Sugar May Be Out of Range

    Your body sends signals when blood glucose is either too high (hyperglycemia) or too low (hypoglycemia). Learning to recognize these signs is essential — especially because symptoms don’t always appear until levels are significantly abnormal.

    Signs of high blood sugar (hyperglycemia):

    • Increased thirst and frequent urination
    • Fatigue or unusual tiredness
    • Blurred vision
    • Slow-healing cuts or sores
    • Headaches
    • Difficulty concentrating

    Signs of low blood sugar (hypoglycemia — below 70 mg/dL):

    • Shakiness or trembling
    • Sweating, chills, or clamminess
    • Rapid heartbeat
    • Dizziness or lightheadedness
    • Sudden hunger or irritability
    • Confusion or difficulty speaking

    A 2023 NIH-supported study found that many adults with type 2 diabetes experience undetected hypoglycemic episodes — particularly at night — without any noticeable symptoms. This is called hypoglycemia unawareness, and it’s one of the strongest arguments for consistent, structured monitoring rather than symptom-based checking alone.

    ⚠️ Red flag: If you experience confusion, loss of consciousness, or seizures related to blood sugar abnormalities, call 911 immediately. These are medical emergencies.

    Understanding Blood Sugar Target Ranges

    Not all blood glucose readings mean the same thing. Context matters enormously — a number that looks concerning in isolation may be appropriate given when and how it was measured.

    The ADA recommends the following general targets for most non-pregnant adults with type 2 diabetes:

    • Before meals (fasting or preprandial): 80–130 mg/dL
    • 1–2 hours after the start of a meal (postprandial): Less than 180 mg/dL
    • A1C (3-month average blood sugar): Below 7% for most adults

    It’s important to note that these are general guidelines. Your physician may set personalized targets based on your age, kidney function, cardiovascular history, hypoglycemia risk, and other individual factors. Clinical evidence indicates that tighter control (lower targets) may reduce complications in some patients but increase hypoglycemia risk in others — making the conversation with your doctor essential.

    The A1C test, administered in a lab or clinic, measures the percentage of hemoglobin in your blood that has glucose attached. It reflects your average blood sugar over approximately two to three months — giving a much broader picture than any single daily reading.

    When and How Often to Check Your Blood Sugar

    One of the most common questions people with type 2 diabetes ask is: How often should I check my blood sugar? The honest answer is that it depends — on your treatment plan, your medication, your individual goals, and what your doctor recommends.

    That said, clinical guidelines offer a useful framework:

    If you take insulin: Most physicians recommend checking before meals, at bedtime, before and after exercise, and whenever you feel symptomatic. This could mean checking 4–8 times per day or more.

    If you use oral medications or manage with lifestyle alone: Monitoring frequency varies widely. Research suggests that structured testing — for example, checking before and 2 hours after specific meals on rotating days — can provide valuable pattern data even without constant daily checking.

    Strategic times to check include:

    • First thing in the morning (fasting)
    • Before and 2 hours after meals
    • Before, during, and after exercise
    • Before bed
    • During illness or high-stress periods
    • Whenever symptoms of hypo- or hyperglycemia appear

    According to the CDC, structured self-monitoring helps people identify specific foods, activities, or times of day that cause problematic spikes or drops. For a practical approach to building meals that work with your monitoring data, see our guide on Diabetes Meal Planning: Build a Plate That Controls Blood Sugar.

    Monitoring Tools: From Traditional Glucometers to CGM Technology

    The tools available for blood sugar monitoring have evolved dramatically. In 2026, people with type 2 diabetes have more options — and more precision — than ever before.

    Traditional Blood Glucose Meters (BGM)

    A blood glucose meter (glucometer) requires a small fingerstick blood sample placed on a test strip. The device reads the glucose level in seconds. These devices are affordable, widely covered by insurance, and accurate when used correctly. They remain the most commonly used monitoring tool in the US for type 2 diabetes.

    Key tips for accurate readings:

    • Wash your hands thoroughly before testing
    • Use the side of your fingertip, not the center
    • Store test strips at room temperature and away from humidity
    • Check the expiration date on your strips
    • Calibrate or replace your meter per manufacturer guidelines

    Continuous Glucose Monitors (CGM)

    Continuous glucose monitors represent a major advancement in diabetes care. A small sensor — worn on the arm, abdomen, or upper back — measures glucose levels in the fluid just under the skin (interstitial fluid) every few minutes, sending readings to a smartphone app or reader device around the clock.

    CGMs allow users to see glucose trends in real time, receive alerts for dangerous highs or lows, and share data with their care team. A 2022 clinical trial published in JAMA found that adults with type 2 diabetes not on intensive insulin therapy who used CGMs experienced significantly greater reductions in A1C compared to those using standard fingerstick monitoring.

    Popular CGM devices available in the US include the Dexcom G7, the Abbott FreeStyle Libre 3, and others approved by the FDA. Coverage through Medicare and private insurance has expanded significantly in recent years, making CGM more accessible to more patients.

    Flash Glucose Monitoring

    Flash glucose monitors work similarly to CGMs but require the user to wave a reader or phone over the sensor to obtain a reading, rather than transmitting continuously. They are generally more affordable than full CGM systems and still provide substantial data compared to fingerstick testing alone.

    If you’re unsure which monitoring approach is right for you, your diabetes care provider or a certified diabetes care and education specialist (CDCES) can help you evaluate options based on your lifestyle, insurance, and clinical needs. Understanding how your monitoring data connects to lifestyle factors — including how carbohydrates affect glucose — is also worth exploring. Our resource on Carb Counting for Diabetes: A Complete Beginner’s Guide can help you connect those dots.

    Living With Diabetes: Making Monitoring Work in Real Life

    Knowing how to monitor is one thing — making it a sustainable habit is another. Many people with type 2 diabetes struggle with the emotional and logistical burden of frequent testing, particularly if their readings are often discouraging.

    Clinical evidence indicates that treating monitoring as information rather than judgment is critical for long-term engagement. A high reading after a meal isn’t a failure — it’s a data point that can guide your next decision.

    Practical strategies to stay consistent:

    • Set a recurring alarm on your phone for monitoring times
    • Keep your meter or CGM reader in a visible, convenient place
    • Use a logbook or diabetes app to track readings alongside meals and activity
    • Review your data with your care team at every visit — bring your meter or app history
    • Ask your pharmacist about automatic refills for test strips and lancets

    Stress, illness, poor sleep, and hormonal fluctuations can all affect blood glucose readings in ways that have nothing to do with your food choices. This varies from person to person, but most physicians recommend checking more frequently during periods of illness or significant life stress.

    Research suggests that regular physical activity is one of the most powerful tools for improving insulin sensitivity and stabilizing blood sugar. For a detailed breakdown of how exercise affects glucose levels, visit our article on Diabetes Meal Planning: Build a Plate That Controls Blood Sugar for complementary dietary strategies.

    When to Call Your Doctor — and Emergency Warning Signs

    Knowing when to seek help is just as important as knowing how to monitor. Some situations require a same-day call to your healthcare provider; others require calling 911 immediately.

    Call your doctor promptly if:

    • Your fasting blood sugar is consistently above 180 mg/dL or below 70 mg/dL
    • You are experiencing frequent hypoglycemic episodes without a clear cause
    • Your A1C result has significantly worsened since your last test
    • You develop new symptoms such as increased urination, extreme thirst, or unexplained weight loss
    • You feel unwell and your blood sugar won’t stabilize despite your usual management
    • Your meter or CGM readings seem inconsistent or inaccurate

    ⚠️ Seek emergency care immediately (call 911) if you or someone nearby experiences:

    • Loss of consciousness or inability to be roused
    • Seizures
    • Severe confusion or disorientation
    • Symptoms of diabetic ketoacidosis (DKA): fruity-smelling breath, severe nausea or vomiting, rapid breathing, extreme fatigue

    The Mayo Clinic emphasizes that DKA, while more common in type 1 diabetes, can occur in people with type 2 diabetes — particularly during illness, under severe physiological stress, or in those taking certain medications. Never ignore these warning signs.

    Frequently Asked Questions

    Q: What is a normal blood sugar level for someone with type 2 diabetes?
    Most physicians and the ADA recommend a fasting target of 80–130 mg/dL and a post-meal target of under 180 mg/dL. Your personal targets may differ based on your age, health history, and medications — always confirm your specific goals with your care team.

    Q: Do I need to check my blood sugar if I’m managing my diabetes with diet alone?
    Research suggests that even people managing type 2 diabetes without medication can benefit from periodic structured monitoring to understand how specific foods, exercise, and stress affect their glucose levels. Discuss an appropriate schedule with your physician.

    Q: Can stress cause blood sugar to spike even if I eat well?
    Absolutely. Stress triggers the release of hormones like cortisol and adrenaline, which cause the liver to release stored glucose into the bloodstream. Clinical evidence confirms that psychological and physical stress can significantly elevate blood glucose levels, independent of diet.

    Q: Is a continuous glucose monitor (CGM) covered by my insurance?
    Coverage varies by plan. As of 2026, Medicare Part B covers CGMs for many people with diabetes who require insulin. Many private insurers have expanded coverage as well. Contact your insurance provider or a CDCES (certified diabetes care and education specialist) to understand your specific benefits.

    Q: How often should I get my A1C tested?
    The ADA recommends A1C testing at least twice a year for people whose blood sugar is well-controlled and meeting their targets. For those whose management has changed or who are not meeting goals, quarterly testing (every 3 months) is often recommended.

    Conclusion

    Blood sugar monitoring is one of the most powerful tools available to anyone living with type 2 diabetes. It transforms invisible, daily biochemical processes into actionable information — giving you and your healthcare team the insight needed to make smarter decisions about food, activity, medication, and overall care.

    Whether you use a traditional glucometer or the latest continuous glucose monitor, the goal is the same: understand your patterns, respond to what the data tells you, and stay connected with your care team. No single reading defines your health — but a consistent commitment to monitoring can genuinely protect it.

    Talk to your doctor or a certified diabetes educator about the monitoring schedule and tools that are right for your specific situation. You deserve a management plan that is tailored to your life — not a generic one-size-fits-all approach.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Diabetes Meal Planning: Build a Plate That Controls Blood Sugar

    Diabetes Meal Planning: Build a Plate That Controls Blood Sugar

    Diabetes Meal Planning: Build a Plate That Controls Blood Sugar

    What you eat at every meal is one of the most powerful tools you have for managing blood sugar — and a smart plan makes it sustainable.

    Why What You Eat Matters More Than You Think

    Marcus, 54, was diagnosed with type 2 diabetes three years ago. His doctor handed him a pamphlet about “eating healthy” and sent him on his way. Within six months, his A1C was still climbing — not because he wasn’t trying, but because “eat healthy” without a real structure is almost impossible to follow consistently.

    Sound familiar? You’re not alone. According to the CDC, more than 38 million Americans are living with diabetes as of the most recent national data, and a significant portion of them struggle with daily blood sugar management — often because no one gave them a clear, practical meal framework.

    Diabetes meal planning isn’t about eating less or giving up everything you love. It’s about building eating patterns that keep your glucose levels steady, support your energy, and reduce long-term complications. In this guide, you’ll learn how to structure your meals, which foods work for you and which work against you, and how to create a realistic plan that fits your actual life — not just a clinical chart.

    What Is Diabetes Meal Planning?

    Diabetes meal planning is a structured approach to choosing foods, portion sizes, and meal timing in a way that helps control blood glucose (sugar) levels throughout the day. Unlike a one-size-fits-all diet, it’s tailored to your body, your medications, your activity level, and your personal food preferences.

    The goal is not perfection — it’s consistency. When your meals are predictable in terms of carbohydrate content, timing, and nutritional balance, your pancreas (or your medication) has a much easier job keeping blood sugar in a healthy range.

    According to the American Diabetes Association (ADA), there is no single “diabetic diet” proven to work best for everyone. Instead, several evidence-based eating patterns — including the Mediterranean diet, low-carbohydrate diets, and the DASH diet — have all shown meaningful benefits for people with type 2 diabetes when followed consistently.

    That said, the foundation of any effective diabetes meal plan comes down to the same core principles: managing carbohydrate intake, prioritizing fiber, choosing quality protein, and limiting processed foods and added sugars.

    How Blood Sugar Responds to What You Eat

    Before building your plate, it helps to understand the basics of how food affects your blood glucose. When you eat carbohydrates — bread, rice, fruit, milk, anything starchy or sweet — your digestive system breaks them down into glucose. That glucose enters your bloodstream, causing blood sugar to rise.

    In people without diabetes, the pancreas releases insulin to move that glucose into cells for energy. In type 2 diabetes, either the pancreas doesn’t produce enough insulin, or the body’s cells don’t respond to it effectively — a condition called insulin resistance. The result: glucose stays elevated in the bloodstream longer than it should.

    A 2023 meta-analysis published through NIH-affiliated researchers confirmed that the type and amount of carbohydrates consumed is one of the strongest dietary predictors of postprandial (after-meal) blood sugar spikes in people with type 2 diabetes. This is why carbohydrate awareness — not necessarily elimination — is central to diabetes meal planning.

    Not all carbohydrates behave the same way. High-fiber, complex carbohydrates (like vegetables, legumes, and whole grains) are digested more slowly, producing a gentler, more gradual rise in blood sugar. Refined carbohydrates (white bread, sugary drinks, pastries) digest rapidly and cause sharp glucose spikes.

    For a deeper look at how carbohydrate counting works in practice, see our guide: Carb Counting for Diabetes: A Complete Beginner’s Guide.

    The Diabetes Plate Method: Simple and Effective

    One of the most practical frameworks recommended by the ADA is the Diabetes Plate Method. It requires no apps, no food scale, and no math — just a standard 9-inch dinner plate and an understanding of food categories.

    Here’s how to build it:

    • Half your plate: non-starchy vegetables — broccoli, spinach, kale, cauliflower, green beans, peppers, cucumbers, tomatoes, zucchini. These are high in fiber and low in carbohydrates, making them the safest foods for blood sugar control.
    • One quarter: lean protein — grilled chicken, fish (especially fatty fish like salmon or sardines), eggs, tofu, legumes, or low-fat dairy. Protein doesn’t raise blood sugar and helps you feel full longer.
    • One quarter: quality carbohydrates — brown rice, quinoa, whole grain bread, sweet potato, corn, or fruit. This is where your blood sugar management lives. Keeping this portion to one-quarter of your plate naturally limits your carbohydrate load per meal.
    • Healthy fats on the side — a small amount of olive oil, avocado, or nuts can support satiety and heart health without raising glucose.
    • Beverage — water, unsweetened sparkling water, or herbal tea. Avoid juice, soda, and sweetened coffee drinks.

    Clinical evidence from Johns Hopkins Medicine supports that visual portion-control tools like the plate method lead to meaningful reductions in post-meal glucose levels in type 2 diabetic patients, particularly when practiced consistently over several months.

    Best and Worst Foods for Blood Sugar Control

    Understanding which foods support your glucose management — and which ones sabotage it — is one of the most empowering steps you can take.

    Foods to Prioritize

    • Non-starchy vegetables: leafy greens, broccoli, asparagus, cauliflower, mushrooms, bell peppers
    • Legumes: lentils, black beans, chickpeas — high in protein and fiber, with a lower glycemic impact than most grains
    • Whole grains: oats, quinoa, farro, barley — slower to digest than refined grains
    • Fatty fish: salmon, mackerel, sardines — rich in omega-3 fatty acids, which research suggests may reduce cardiovascular risk in people with diabetes
    • Berries: blueberries, strawberries, raspberries — lower in sugar than other fruits, high in antioxidants
    • Nuts and seeds: almonds, walnuts, chia seeds, flaxseed — help slow digestion and improve satiety
    • Olive oil: associated with better insulin sensitivity in Mediterranean diet studies

    Foods to Limit or Avoid

    • Sugary beverages: soda, fruit juice, sweetened coffee drinks, energy drinks — cause rapid blood sugar spikes with no nutritional benefit
    • Refined grains: white bread, white rice, regular pasta — digest quickly and cause glucose surges
    • Fried foods: high in unhealthy fats and calories, may worsen insulin resistance over time
    • Highly processed snacks: chips, crackers, cookies — often combine refined carbs with unhealthy fats
    • Added sugars: candy, pastries, sweetened cereals — the ADA recommends minimizing these entirely
    • Alcohol: can cause unpredictable blood sugar swings, particularly if you take insulin or certain oral medications. Always consult your doctor before including alcohol in your routine.

    This varies from person to person — your specific medication regimen, kidney function, and other health factors may influence which foods are most or least appropriate for you. A registered dietitian who specializes in diabetes can personalize this list for your situation.

    Meal Timing and Frequency: Does It Matter?

    Yes — and more than most people realize. Erratic eating patterns, skipping meals, or going long stretches without food can cause blood sugar to drop too low (hypoglycemia) or rebound too high. For most people with type 2 diabetes, eating at consistent times each day helps the body (and any glucose-lowering medications) work more predictably.

    Most clinical guidelines suggest three balanced meals per day, spaced approximately 4 to 6 hours apart. Some people manage well with two smaller snacks between meals to prevent blood sugar dips, while others do better with strict three-meal structures. This is highly individual — what works for one person may not work for another.

    The NIH’s National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) notes that consistent meal timing is particularly important for people using insulin or sulfonylurea medications, as these drugs lower blood sugar on a schedule — and your food intake needs to align accordingly.

    Poor sleep can also disrupt your mealtime hunger cues and insulin sensitivity. If that’s a factor for you, our article on Diabetes and Sleep: How Poor Sleep Raises Blood Sugar is worth reading alongside this guide.

    Reading Food Labels: What to Look For

    One of the most practical skills in diabetes meal planning is learning to read nutrition labels accurately. Here’s what to pay attention to:

    • Total carbohydrates: This is the number that matters most for blood sugar. It includes starches, fiber, and sugars.
    • Dietary fiber: Subtract fiber grams from total carbohydrates to get “net carbs” — a better approximation of how much will actually raise your blood sugar.
    • Added sugars: The FDA now requires this to be listed separately. Aim to keep added sugars as low as possible.
    • Serving size: Everything on the label is per serving — not per package. A bag that seems like one serving often contains two or three.
    • Ingredients list: The closer to the top an ingredient appears, the more of it the product contains. Avoid products that list sugar (or its many aliases: corn syrup, maltose, dextrose, fructose) in the first few ingredients.

    Practical Meal Planning Tips You Can Start This Week

    • Batch cook on weekends: Prepare grains, roasted vegetables, and proteins in advance so healthy meals are accessible on busy weekdays.
    • Keep non-starchy vegetables prepped and ready: Washed, chopped vegetables in the fridge remove the friction of making healthy choices at mealtime.
    • Plan before you shop: Writing out your weekly meals before grocery shopping reduces impulse buys and ensures you have what you need.
    • Use a glucose monitor as feedback: If you test your blood sugar before and two hours after meals, you can identify which specific foods cause larger spikes in your body — this is personalized data no general guide can replicate.
    • Don’t eat carbohydrates alone: Pairing carbs with protein or healthy fat slows digestion and blunts glucose spikes. An apple alone raises blood sugar faster than an apple with a small handful of almonds.
    • Eat slowly and mindfully: Research from Harvard Health suggests that eating more slowly is associated with better portion control and lower post-meal glucose levels.

    When to Call Your Doctor or See a Specialist

    Diabetes meal planning can produce real results, but it works best as part of a comprehensive care plan — not as a replacement for it. Contact your healthcare provider if:

    • Your blood sugar readings remain consistently above or below your target range despite dietary changes
    • You experience frequent hypoglycemia (blood sugar drops below 70 mg/dL), especially with symptoms like shakiness, confusion, sweating, or dizziness
    • You have signs of high blood sugar (hyperglycemia) — extreme thirst, frequent urination, blurred vision, or fatigue — that don’t resolve
    • You are pregnant or planning to become pregnant (gestational diabetes has its own specific nutritional requirements)
    • You have kidney disease, cardiovascular disease, or other conditions that require additional dietary modifications

    Emergency red flags: If you experience confusion, loss of consciousness, extreme weakness, or vomiting alongside abnormal blood sugar readings, call 911 or go to the emergency room immediately. These can be signs of diabetic ketoacidosis (DKA) or severe hypoglycemia — both medical emergencies.

    Ask your doctor for a referral to a Registered Dietitian Nutritionist (RDN) who specializes in diabetes, or a Certified Diabetes Care and Education Specialist (CDCES). Medicare Part B covers Medical Nutrition Therapy (MNT) for people with diabetes — meaning this service may be available to you at no out-of-pocket cost. For more on navigating coverage, see: Health Insurance for Chronic Conditions: What You Need to Know.

    Frequently Asked Questions

    Can people with diabetes eat fruit?

    Yes — but portion size and fruit type matter. Berries, cherries, apples, and citrus fruits tend to have a lower glycemic impact than tropical fruits like mangoes or pineapples. Clinical evidence indicates that whole fruit — not fruit juice — is preferable because fiber slows glucose absorption. Most diabetes nutrition experts suggest limiting fruit servings to about half a cup to one small piece per meal or snack.

    Is a low-carb diet safe for diabetes?

    Research suggests that low-carbohydrate diets can be effective for improving blood sugar control and reducing A1C levels in people with type 2 diabetes. However, if you take insulin or certain diabetes medications, significantly lowering your carbohydrate intake may require medication adjustments to prevent hypoglycemia. Always consult your physician before making a major dietary change.

    Are artificial sweeteners safe for people with diabetes?

    The FDA has approved several non-nutritive sweeteners (stevia, sucralose, aspartame, saccharin) as safe for consumption. They don’t directly raise blood sugar. However, some research suggests that frequent use of artificial sweeteners may influence taste preferences and appetite in ways that could affect long-term dietary patterns. Most physicians recommend using them in moderation rather than as an unlimited free pass.

    How do I handle eating out with diabetes?

    Eating at restaurants is manageable with a few strategies: choose grilled or baked proteins over fried, request sauces and dressings on the side, ask for extra vegetables instead of a starchy side dish, and be cautious with bread baskets and desserts. Many chain restaurants now post nutritional information online, allowing you to review options before you arrive.

    Do I need to count calories or just carbohydrates?

    For most people with type 2 diabetes, carbohydrate awareness is more directly relevant to blood sugar management than calorie counting. That said, overall calorie balance matters for weight management — and weight loss, even modest amounts, can significantly improve insulin sensitivity. Your healthcare team can help you determine which approach is most appropriate for your specific goals.

    The Bottom Line

    Managing diabetes through food doesn’t have to feel like deprivation or constant restriction. It’s about building a consistent, balanced approach — one that gives your body the steady fuel it needs while keeping blood sugar in a range that protects your long-term health.

    Start with the basics: fill half your plate with vegetables, keep your carbohydrate portions controlled and high-fiber, pair them with protein and healthy fat, and eat at consistent times. From there, use your glucose monitor as a personal feedback tool and work with your care team to fine-tune the details.

    Small, sustainable changes practiced daily have a far greater impact on diabetes management than any dramatic short-term effort. You have more control over your blood sugar than you may realize — and building a smart meal plan is one of the most evidence-backed ways to use it.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Carb Counting for Diabetes: A Complete Beginner’s Guide

    Carb Counting for Diabetes: A Complete Beginner’s Guide

    Learning to count carbohydrates can be one of the most empowering tools in your diabetes management plan — and one of the most misunderstood.

    Marcus, 52, was diagnosed with Type 2 diabetes three years ago. His doctor told him to "watch his carbs," but nobody explained what that actually meant. He gave up bread and pasta — and still couldn’t get his blood sugar under control. The problem wasn’t his willpower. It was that he didn’t know that a bowl of oatmeal, a glass of orange juice, and a banana at breakfast could send his glucose numbers soaring just as fast as a slice of cake.

    According to the American Diabetes Association (ADA), carbohydrate counting is one of the most effective meal planning strategies for people with both Type 1 and Type 2 diabetes. Yet surveys suggest that fewer than half of people living with diabetes receive structured nutrition education after their diagnosis.

    In this guide, you’ll learn exactly what carbohydrate counting is, how it affects your blood sugar, how to get started, and practical strategies you can use starting at your very next meal — all grounded in clinical evidence and aligned with current ADA and CDC recommendations.

    What Is Carbohydrate Counting?

    Carbohydrate counting — often called "carb counting" — is a meal planning method that tracks the total grams of carbohydrates you consume at each meal or snack. Unlike generalized "healthy eating" advice, carb counting gives you a specific, measurable way to manage the nutrient that has the most direct and immediate impact on your blood glucose (blood sugar) levels.

    Carbohydrates are one of three macronutrients (along with protein and fat). When digested, they break down into glucose, which enters your bloodstream. For people without diabetes, the pancreas automatically releases enough insulin to manage this glucose surge. For people with diabetes, that process is impaired — making the amount of carbohydrates you eat a critical variable in blood sugar control.

    The CDC reports that approximately 38.4 million Americans — roughly 11.6% of the US population — have diabetes. Of those, an estimated 90-95% have Type 2 diabetes. For all of them, managing carbohydrate intake is a cornerstone of care.

    Carb counting works at two levels:

    • Basic carb counting: Tracking total carbohydrate grams to stay within a consistent daily target set by your healthcare provider or registered dietitian.
    • Advanced carb counting: Used primarily by people on insulin therapy; involves matching insulin doses to the exact amount of carbs consumed at each meal (called an insulin-to-carb ratio).

    This guide focuses on both levels, starting with the fundamentals.

    Why Carbohydrates Matter More Than Other Nutrients

    You’ve probably heard that sugar is bad for diabetes — but the full picture is more nuanced. All carbohydrates raise blood glucose, not just added sugars. That includes naturally occurring carbs in fruit, dairy, legumes, and whole grains.

    Clinical evidence supports this clearly. A 2022 meta-analysis published in Diabetes Care (affiliated with the ADA) found that low-carbohydrate dietary patterns significantly reduced HbA1c levels — a measure of average blood sugar over three months — in adults with Type 2 diabetes. Participants who tracked their carbohydrate intake consistently showed greater glycemic improvement than those who simply received general dietary advice.

    Here’s the key distinction that most people miss:

    • Fat and protein have a minimal and delayed effect on blood glucose.
    • Carbohydrates raise blood sugar within 15 to 60 minutes of eating, depending on the type and amount consumed.

    This is why two meals with identical calorie counts can produce very different blood sugar responses — if one meal is carbohydrate-heavy and the other is protein-and-fat-heavy, your glucose readings afterward will look dramatically different. Understanding this dynamic gives you real, measurable control.

    Identifying Carbohydrates in Your Diet

    One of the biggest hurdles for people new to carb counting is recognizing which foods actually contain significant carbohydrates. Many people are surprised by what’s on the list.

    High-carbohydrate foods to track carefully:

    • Bread, rolls, bagels, crackers, and tortillas
    • Rice, pasta, noodles, and couscous
    • Potatoes, corn, peas, and winter squash
    • Breakfast cereals, oatmeal, and granola
    • Fruit and 100% fruit juice
    • Milk, yogurt, and flavored dairy drinks
    • Dried beans, lentils, and chickpeas
    • Sweets, desserts, candy, and sugary beverages
    • Snack foods like pretzels, chips, and popcorn

    Foods with minimal carbohydrates (generally free or low-impact):

    • Non-starchy vegetables: spinach, broccoli, cauliflower, peppers, zucchini, leafy greens
    • Meat, poultry, and seafood (unbreaded)
    • Eggs
    • Cheese and most nuts
    • Oils and butter

    According to the NIH’s National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), most adults with diabetes are advised to get approximately 45-60 grams of carbohydrates per meal, though this varies significantly based on body size, activity level, medication type, and individual blood sugar response. Your specific target should always be set by your care team.

    How to Read a Nutrition Label for Carb Counting

    The FDA’s updated Nutrition Facts label — now required on all packaged foods in the US — is your best friend for carb counting. Here’s how to read it effectively:

    Step 1: Check the serving size first. All the numbers on the label apply to that specific serving size — not the whole package. A bag of crackers might list 20 grams of carbs per serving, but if you eat two servings, you’ve consumed 40 grams.

    Step 2: Find "Total Carbohydrate." This is the number you count. It includes all types of carbs: starches, sugars, and fiber.

    Step 3: Subtract dietary fiber (optional but useful). Fiber is a carbohydrate that your body cannot fully digest, so it has a much smaller impact on blood sugar. Many dietitians recommend subtracting fiber grams from total carbohydrates to calculate "net carbs." However, this approach varies by individual, and you should confirm it with your dietitian or diabetes educator.

    Step 4: Note added sugars. While added sugars count toward your total carbs, watching them separately is good practice. The ADA recommends minimizing added sugars as part of an overall healthy eating pattern for diabetes.

    For fresh foods without labels — such as fruits, vegetables, and restaurant meals — tools like the USDA FoodData Central database, CalorieKing, or apps like MyFitnessPal and Cronometer can help you estimate carb content accurately.

    Getting Started: Setting Your Carb Budget

    There is no one-size-fits-all carbohydrate target for diabetes. Research suggests that what works for one person may not work for another — this truly varies from person to person. That said, here is how most healthcare providers approach establishing your starting point:

    Work with your care team. A registered dietitian who specializes in diabetes (often called a Certified Diabetes Care and Education Specialist, or CDCES) is your most valuable resource. They will factor in your weight, activity level, medications (especially insulin), kidney function, and personal food preferences to build a realistic carb target.

    Typical starting ranges (general guidelines only):

    • Per meal: 45-60 grams of carbohydrates (for most adults with Type 2 diabetes)
    • Per snack: 15-30 grams
    • Daily total: 130-180 grams (though some individuals do well on lower targets under medical supervision)

    Monitor your response. Checking your blood glucose before a meal and again 1-2 hours after eating is the most direct way to understand how a specific food or meal affects your blood sugar. The ADA recommends a postmeal (postprandial) blood glucose target of less than 180 mg/dL for most non-pregnant adults with diabetes, though individual targets may differ.

    A 2021 systematic review in Nutrients found that structured self-monitoring of blood glucose combined with carbohydrate counting led to significantly better glycemic control in Type 2 diabetes patients compared to monitoring alone — underscoring that both tools work best together.

    Advanced Carb Counting: Insulin-to-Carb Ratios

    If you use rapid-acting insulin at mealtimes — common in Type 1 diabetes and some cases of Type 2 — your doctor may teach you to use an insulin-to-carb ratio (ICR). This means for every X grams of carbohydrate you eat, you take a set number of units of insulin.

    For example, if your ratio is 1:15, you would take 1 unit of rapid-acting insulin for every 15 grams of carbohydrates you eat. A meal with 60 grams of carbs would require 4 units.

    This approach requires accurate carb counting, consistent monitoring, and close communication with your endocrinologist or diabetes care team. Never adjust your insulin doses without medical guidance — this is a medically supervised process. Johns Hopkins Medicine and the Cleveland Clinic both emphasize that ICR-based dosing should be individualized and regularly reassessed as your circumstances change.

    If you’re managing diabetes with sleep issues as well, research suggests poor sleep can independently worsen blood sugar control — you can learn more in our article on Diabetes and Sleep: How Poor Sleep Raises Blood Sugar.

    Living With Diabetes: Practical Carb Counting Tips

    Managing carb counting in real life — at restaurants, holidays, and busy weekdays — takes practice. Here are evidence-informed strategies that make it sustainable:

    Use the plate method as a visual guide. The USDA and ADA both recommend filling half your plate with non-starchy vegetables, one-quarter with lean protein, and one-quarter with a carbohydrate-containing food. This naturally limits carb portions without requiring a scale at every meal.

    Batch cook and label carb amounts. Preparing grains, legumes, and starchy vegetables in advance — and noting the carb count per portion — removes guesswork during busy weeknights.

    Choose high-fiber carbs when possible. Foods high in dietary fiber — like legumes, oats, and non-starchy vegetables — raise blood sugar more slowly than refined carbohydrates. Clinical evidence from Harvard Health and NIH consistently supports fiber-rich diets as beneficial for glycemic control.

    Watch liquid carbohydrates closely. Juice, soda, sports drinks, and even "healthy" smoothies can contain 30-60 grams of carbohydrates in a single serving — often without the fiber that slows glucose absorption. Most diabetes specialists recommend limiting sugary beverages significantly.

    Don’t skip meals. Skipping meals can cause blood sugar to drop too low (hypoglycemia) if you take certain diabetes medications or insulin — and then rebound sharply when you do eat. Consistent meal timing supports more predictable glucose patterns.

    If you’re also interested in how intermittent fasting interacts with diabetes and blood sugar, our guide on Intermittent Fasting for Weight Loss: What the Science Says covers important considerations.

    When to Call Your Doctor or Seek Emergency Care

    Carb counting is a powerful tool, but it doesn’t replace ongoing medical care. Know when to reach out immediately:

    Call your doctor promptly if:

    • Your blood glucose is consistently above 250 mg/dL despite dietary changes
    • You’re experiencing frequent hypoglycemia (blood sugar below 70 mg/dL) after adjusting your eating
    • You feel confused, unusually fatigued, or notice changes in urination or thirst
    • Your A1C isn’t improving despite consistent carb tracking
    • You’re unsure how to adjust your plan when you’re sick or traveling

    Seek emergency care immediately if you experience:

    • Blood glucose above 400 mg/dL with symptoms like vomiting, rapid breathing, or fruity-smelling breath (possible signs of diabetic ketoacidosis — a medical emergency)
    • Severe hypoglycemia with confusion, seizures, or loss of consciousness
    • Chest pain, sudden severe headache, or difficulty speaking alongside abnormal blood sugar readings

    The CDC and American Diabetes Association both emphasize that diabetes complications are largely preventable with consistent monitoring, appropriate medication, and structured lifestyle management — including effective carb counting. You can also read our guide on Diabetes and Kidney Disease: Protect Your Kidneys Now to understand how long-term blood sugar control affects kidney health.

    Frequently Asked Questions

    Q: Do I need to count carbs if I have Type 2 diabetes but don’t use insulin?
    A: Yes — carb counting is beneficial regardless of whether you use insulin. For people managing Type 2 diabetes with oral medications or lifestyle alone, consistent carbohydrate intake helps stabilize blood glucose and reduce A1C. Research suggests that structured carb tracking is one of the most effective non-pharmacological tools for glycemic management.

    Q: Are all carbohydrates equally bad for blood sugar?
    A: No. The type and quality of carbohydrates matter. High-fiber, minimally processed carbs — like legumes, oats, and non-starchy vegetables — raise blood sugar more slowly than refined carbs such as white bread or sugary drinks. Clinical evidence supports choosing whole food sources of carbohydrates whenever possible.

    Q: How many carbs should I eat per day if I have diabetes?
    A: This varies significantly from person to person. The ADA does not endorse one universal carbohydrate target. Most adults with Type 2 diabetes start in the range of 130-180 grams per day, but your physician or registered dietitian should set your individual target based on your medications, weight, activity level, and blood sugar response.

    Q: Can I use a continuous glucose monitor (CGM) to help with carb counting?
    A: Absolutely. A CGM tracks your blood glucose in real time, allowing you to see exactly how different foods and meals affect your levels throughout the day. Many endocrinologists and diabetes educators consider CGMs a powerful complement to carb counting, particularly for people on insulin. The FDA has approved several CGM devices for ongoing use in people with both Type 1 and Type 2 diabetes.

    Q: Is a very low-carb or ketogenic diet safe for people with diabetes?
    A: Research suggests that very low-carbohydrate diets (typically under 50 grams per day) can improve blood sugar control and reduce A1C in some people with Type 2 diabetes. However, these diets carry risks — especially for people on insulin or certain medications — including hypoglycemia and electrolyte imbalances. Always discuss significant dietary changes with your doctor before implementing them.

    Conclusion

    Carbohydrate counting isn’t about restriction for its own sake — it’s about giving yourself accurate information so you can make choices that keep your blood sugar stable and protect your long-term health. Like any skill, it takes practice, and it works best when you have a knowledgeable care team guiding you.

    Start small: read one nutrition label today, log one meal, check your glucose after eating. Build from there. Most people who commit to learning carb counting report feeling more in control of their diabetes — not more deprived. The goal isn’t perfection. It’s consistent, informed management that you can sustain for the long haul.

    Work closely with your physician, endocrinologist, or a certified diabetes care and education specialist to develop a carbohydrate plan that fits your life, your medications, and your health goals.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.
  • Diabetes and Sleep: How Poor Sleep Raises Blood Sugar

    Diabetes and Sleep: How Poor Sleep Raises Blood Sugar

    Poor sleep and diabetes form a dangerous cycle — and breaking it may be one of the most underrated moves in blood sugar management.

    Marcus, 54, had been living with type 2 diabetes for six years. He tracked his carbs, took his medication faithfully, and exercised three times a week. Yet his fasting blood sugar readings kept creeping up. His endocrinologist asked one question that changed everything: “How well are you sleeping?”

    Marcus was getting five hours a night — tops. He thought that was just part of getting older. It wasn’t. It was quietly undermining every other effort he was making to manage his diabetes.

    According to the CDC, more than 35% of American adults report sleeping fewer than seven hours per night. Among adults with type 2 diabetes, sleep problems are even more common — and the consequences are measurable in blood glucose levels, insulin sensitivity, and long-term A1C trends.

    In this guide, you’ll learn how sleep directly affects blood sugar control, what the research says, and what practical steps you can take to improve both your sleep and your diabetes outcomes — starting tonight.

    The Connection Between Sleep and Blood Sugar

    Sleep isn’t passive recovery. While you rest, your body is actively regulating hormones, repairing tissues, and resetting metabolic processes — including the ones that govern blood glucose.

    When you don’t sleep enough — or sleep poorly — your body responds with a stress-like hormonal cascade. Cortisol and adrenaline (epinephrine) rise, signaling your liver to release more glucose into the bloodstream. At the same time, insulin sensitivity decreases, meaning your cells become less responsive to insulin’s signal to absorb that glucose.

    The result: higher blood sugar, even if you haven’t eaten anything different.

    A landmark study published in Annals of Internal Medicine found that just four nights of sleep restriction (4.5 hours per night) reduced insulin sensitivity in healthy adults by 16% and reduced the capacity of fat cells to respond properly to insulin by 30%. For someone already managing insulin resistance, that’s a significant added burden.

    Research suggests the relationship runs in both directions: poor sleep worsens diabetes control, and diabetes complications — including neuropathy, nighttime urination, and sleep apnea — disrupt sleep quality. This bidirectional cycle makes addressing sleep a clinical priority, not an afterthought.

    Signs That Poor Sleep May Be Affecting Your Blood Sugar

    You may not immediately connect your blood sugar readings to how you slept the night before. But clinical evidence indicates several signs that sleep disruption is influencing your glucose control:

    Early or mild signs:

    • Fasting blood glucose consistently higher than your target range
    • Stronger cravings for carbohydrates and sugary foods the next day
    • Difficulty concentrating or “brain fog” after a poor night’s sleep
    • Increased hunger despite eating normally
    • Blood sugar spikes after meals that are harder to manage
    • Fatigue that doesn’t improve with rest

    More advanced or persistent signs:

    • A1C creeping upward despite consistent medication use
    • Waking multiple times at night to urinate (possible sign of high blood glucose or uncontrolled diabetes)
    • Witnessed gasping or pauses in breathing during sleep (potential sleep apnea — a major diabetes-related complication)
    • Restless leg sensations at night (may indicate diabetic peripheral neuropathy)
    • Morning headaches and daytime sleepiness despite seven or more hours in bed

    According to a study in Diabetes Care, adults with type 2 diabetes who slept fewer than six hours per night had significantly higher A1C levels than those who slept seven to eight hours, even after adjusting for diet and medication use. This varies from person to person, but the pattern is consistent across multiple large-scale studies.

    Why Diabetes Makes Sleep Harder — and Vice Versa

    One of the most frustrating aspects of diabetes and sleep is how each condition fuels the other. Understanding these mechanisms helps you target the right intervention.

    How diabetes disrupts sleep:

    • Nocturia (nighttime urination): When blood glucose is elevated, your kidneys work overtime to filter excess sugar, causing frequent trips to the bathroom at night.
    • Nocturnal hypoglycemia: Low blood sugar episodes during sleep can cause sweating, heart pounding, or nightmares that wake you up.
    • Peripheral neuropathy: Nerve damage in the legs and feet can cause burning, tingling, or pain that makes it impossible to fall or stay asleep.
    • Obstructive sleep apnea (OSA): Research from the American Diabetes Association indicates that OSA affects up to 70% of people with type 2 diabetes — far higher than the general population rate of 20-30%.

    How poor sleep worsens diabetes:

    • Elevated cortisol raises fasting blood glucose
    • Reduced insulin sensitivity makes medications less effective
    • Sleep deprivation increases ghrelin (hunger hormone) and decreases leptin (satiety hormone), promoting overeating of high-carb foods
    • Chronic sleep loss promotes systemic inflammation, which is a known driver of insulin resistance

    This cycle isn’t inevitable — but it does require active, informed management. For more on how insulin resistance develops, see our article on Diabetes and Kidney Disease: Protect Your Kidneys Now, which covers related metabolic pathways.

    Sleep Disorders Common in People With Diabetes

    Certain sleep disorders are significantly more prevalent among people with diabetes, and identifying them is the first step toward treatment.

    Obstructive Sleep Apnea (OSA)
    OSA occurs when the airway partially or fully collapses during sleep, causing interrupted breathing. Clinical evidence indicates that OSA both worsens insulin resistance and is more likely to develop in people who are overweight — a common comorbidity in type 2 diabetes. The NIH reports that treating OSA with continuous positive airway pressure (CPAP) therapy can meaningfully improve insulin sensitivity and glucose variability in people with diabetes.

    Restless Leg Syndrome (RLS)
    RLS causes uncomfortable sensations in the legs — often described as crawling, tingling, or aching — that worsen at rest and improve with movement. Research suggests that RLS is more common in people with diabetes, partly linked to peripheral neuropathy and iron deficiency.

    Insomnia
    Chronic insomnia — difficulty falling asleep, staying asleep, or waking too early — is more prevalent in adults with diabetes. Anxiety about blood sugar levels, pain from neuropathy, and the metabolic consequences of glucose dysregulation all contribute. Cognitive behavioral therapy for insomnia (CBT-I) is the first-line, evidence-based treatment recommended by the American Academy of Sleep Medicine, and it does not require medication.

    Circadian Rhythm Disruption
    Shift work, irregular schedules, or late-night screen exposure can disrupt your body’s internal clock. Research from Harvard Health indicates that circadian misalignment impairs glucose metabolism independently of total sleep duration.

    What the Research Says: Sleep Duration, Quality, and A1C

    The science connecting sleep and blood sugar is robust and growing stronger every year.

    A 2020 meta-analysis published in Sleep Medicine Reviews — analyzing data from over 36,000 participants — found that both short sleep duration (fewer than six hours) and long sleep duration (more than nine hours) were independently associated with higher rates of type 2 diabetes. The sweet spot: seven to eight hours per night.

    A separate NIH-supported study found that improving sleep quality in adults with type 2 diabetes — through behavioral sleep interventions — led to measurable reductions in A1C at six months, comparable in magnitude to some low-intensity pharmacological interventions.

    Clinical evidence also indicates that slow-wave sleep (deep sleep) is particularly important for glucose metabolism. During deep sleep, growth hormone is released and cortisol is suppressed — conditions that support healthy insulin function. Conditions or substances that suppress deep sleep (including alcohol and certain medications) can impair glucose regulation even when total sleep time seems adequate.

    Most physicians now consider sleep assessment a standard part of comprehensive diabetes care, alongside A1C monitoring, blood pressure, and lipid panels.

    Practical Strategies to Improve Sleep and Blood Sugar Together

    The good news: many strategies that improve sleep quality also directly benefit blood sugar control. These approaches are evidence-based and complement — never replace — your prescribed diabetes treatment plan.

    1. Set a consistent sleep schedule
    Go to bed and wake up at the same time every day, including weekends. Research suggests that consistent sleep timing improves circadian rhythm and reduces cortisol variability, both of which benefit glucose regulation.

    2. Create a glucose-friendly pre-sleep routine
    Avoid large meals or high-glycemic snacks in the two hours before bed. If your care team has approved a small bedtime snack to prevent nocturnal hypoglycemia, choose something with protein and fiber (such as a handful of nuts or low-fat cheese with whole grain crackers) over refined carbohydrates.

    3. Limit alcohol near bedtime
    Alcohol may help you fall asleep but suppresses REM and deep sleep stages, worsens glucose control, and increases the risk of nocturnal hypoglycemia. The American Diabetes Association recommends moderation and always discussing alcohol use with your diabetes care team.

    4. Manage nightly blood sugar proactively
    If nocturnal hypoglycemia or hyperglycemia is waking you up, talk to your doctor. Adjustments to medication timing, dosing, or continuous glucose monitor (CGM) alert settings may reduce nighttime disruptions significantly.

    5. Exercise regularly — but time it right
    Regular physical activity improves both sleep quality and insulin sensitivity. Clinical evidence indicates that moderate aerobic exercise (such as brisk walking for 30 minutes) improves sleep quality in older adults with type 2 diabetes. Avoid vigorous exercise within two to three hours of bedtime, as it may temporarily raise cortisol and delay sleep onset.

    6. Address pain from neuropathy
    If nerve pain is keeping you awake, speak with your doctor about pain management options — including medications, physical therapy, or TENS (transcutaneous electrical nerve stimulation). Unmanaged neuropathy pain is one of the most underreported causes of poor sleep in people with diabetes.

    7. Limit screen exposure before bed
    Blue light from phones, tablets, and televisions suppresses melatonin production, delaying sleep onset. Research from Johns Hopkins suggests that avoiding screens for 60 to 90 minutes before bed meaningfully improves sleep latency (how quickly you fall asleep).

    8. Consider a sleep study if you snore or feel unrefreshed
    If your partner notices that you stop breathing during sleep, or if you wake up tired despite adequate time in bed, ask your doctor about a sleep study to rule out obstructive sleep apnea. Treating OSA with CPAP has been shown to improve glycemic control in multiple clinical trials.

    You may also find it helpful to review our article on Diabetes and Heart Disease: Protecting Your Heart, since sleep quality is also a significant factor in cardiovascular risk — another top concern for people managing diabetes.

    When to Call Your Doctor or Seek Immediate Care

    Most sleep issues related to diabetes can be addressed through your primary care physician or endocrinologist during a scheduled visit. However, some situations require faster action.

    Call your doctor promptly if you notice:

    • Consistently elevated morning blood glucose despite following your treatment plan
    • Waking up multiple times a night to urinate
    • Signs of nocturnal hypoglycemia (waking with sweating, shaking, confusion, or a rapid heartbeat)
    • Persistent burning or pain in the feet or legs that disrupts sleep
    • A partner reporting that you stop breathing or gasp during sleep
    • Excessive daytime sleepiness that interferes with work or safety (including driving)

    Seek emergency care immediately if you experience:

    • Severe hypoglycemia with confusion, loss of consciousness, or inability to swallow
    • Blood glucose readings that are dangerously high and accompanied by nausea, vomiting, or rapid breathing (possible signs of diabetic ketoacidosis — a medical emergency)
    • Chest pain or severe shortness of breath during or after sleep

    At your next routine visit, bring a brief sleep diary — noting your bedtime, wake time, nighttime awakenings, and morning blood glucose readings for one to two weeks. This gives your doctor actionable data rather than general impressions.

    Frequently Asked Questions

    Q: Can one bad night of sleep raise my blood sugar the next morning?
    A: Yes. Research suggests that even a single night of insufficient sleep can elevate fasting blood glucose the following morning, primarily due to increased cortisol and reduced insulin sensitivity. This is usually temporary, but chronically poor sleep compounds these effects significantly.

    Q: Is it safe to take melatonin if I have type 2 diabetes?
    A: Melatonin supplements are generally considered low-risk, but clinical evidence on their direct effect on blood glucose in people with diabetes is mixed. Some studies suggest melatonin may affect insulin secretion. Always consult your physician before starting any supplement, including melatonin, to ensure it is appropriate for your individual situation.

    Q: Does sleep apnea actually affect A1C?
    A: Yes. Multiple clinical studies indicate that untreated obstructive sleep apnea is associated with higher A1C levels, and that treatment with CPAP therapy can improve glycemic control in people with type 2 diabetes. If you suspect sleep apnea, ask your doctor for a referral for a sleep study.

    Q: How many hours of sleep should a person with type 2 diabetes aim for?
    A: Most physicians recommend seven to nine hours per night for adults. Both short sleep (fewer than six hours) and long sleep (more than nine hours) have been associated with worse metabolic outcomes. Quality matters too — fragmented or non-restorative sleep can impair glucose regulation even when total duration seems adequate.

    Q: Are sleeping pills safe to use when you have diabetes?
    A: This varies from person to person and depends heavily on which medication is considered and your full medical history. Some sedative-hypnotic medications can affect blood glucose levels or interact with diabetes medications. Cognitive behavioral therapy for insomnia (CBT-I) is the preferred first-line treatment for chronic insomnia and does not carry these risks. Discuss any sleep aid — prescription or over-the-counter — with your physician before using it.

    Conclusion

    Managing diabetes is about much more than what you eat or which medication you take. Sleep is a foundational pillar of metabolic health — and for people living with type 2 diabetes, it may be the most overlooked lever available.

    The connection between sleep and blood sugar is not a theory; it is backed by decades of clinical evidence. Improving your sleep quality can reduce insulin resistance, support healthier A1C trends, curb cravings, and make every other element of your diabetes management plan more effective.

    You don’t have to overhaul everything at once. Start with one change — a consistent bedtime, a conversation with your doctor about nighttime symptoms, or a sleep study referral. Small, consistent improvements in sleep can produce meaningful improvements in blood sugar control over time.

    Work closely with your diabetes care team. They can help you connect the dots between your sleep patterns and your glucose data — and develop a plan tailored to your specific needs.

    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Diabetes and Kidney Disease: Protect Your Kidneys Now

    Diabetes and Kidney Disease: Protect Your Kidneys Now

    Diabetes and Kidney Disease: How to Protect Your Kidneys

    Diabetic kidney disease is the leading cause of kidney failure in the United States — but early detection and consistent management can dramatically slow its progression.

    Introduction

    Marcus, 54, had managed his type 2 diabetes for nearly a decade. He took his metformin regularly, watched his carbohydrate intake, and kept his A1C reasonably controlled. What he didn’t know — until a routine lab panel revealed it — was that his kidneys had been quietly losing function for years.

    His story is far from unique. According to the CDC, approximately 1 in 3 adults with diabetes will develop chronic kidney disease (CKD), also called diabetic nephropathy. That’s more than 10 million Americans silently walking around with kidney damage linked directly to their blood sugar levels.

    In this guide, you’ll learn what diabetic kidney disease actually is, how it develops, what early warning signs to watch for, and — most importantly — what steps you can take right now to protect your kidneys and preserve your long-term health. Whether you’ve just been diagnosed with diabetes or you’ve been managing it for years, this information could make a critical difference.


    What Is Diabetic Kidney Disease?

    Diabetic kidney disease, also known as diabetic nephropathy, is a type of chronic kidney disease caused by long-term damage from elevated blood sugar levels. Your kidneys contain millions of tiny filtering units called glomeruli — and high glucose in the bloodstream gradually damages these delicate structures, making them less effective at filtering waste from your blood.

    Over time, proteins that should stay in the blood begin to leak into the urine (a condition called proteinuria or albuminuria), and the kidneys’ overall filtering capacity — measured as glomerular filtration rate, or GFR — declines. Without intervention, this can progress to end-stage renal disease (ESRD), which requires dialysis or a kidney transplant to survive.

    The National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) reports that diabetes is the number one cause of kidney failure in the United States, accounting for nearly 44% of all new ESRD cases each year. This makes diabetic nephropathy not just a complication of diabetes — it’s a public health crisis.

    Both type 1 and type 2 diabetes can cause kidney disease, though type 2 diabetes accounts for the vast majority of cases simply because it’s far more prevalent. The risk increases significantly the longer someone has had diabetes and the less controlled their blood sugar has been over time.


    Signs and Symptoms of Diabetic Kidney Disease

    One of the most dangerous aspects of diabetic nephropathy is that it produces no noticeable symptoms in its early stages. Most people feel completely normal while kidney function is quietly declining — which is why routine screening is so essential for anyone with diabetes.

    Early warning signs (often detected only through lab tests):

    • Microalbuminuria — small amounts of a protein called albumin appearing in urine (this is the earliest detectable sign)
    • Slightly elevated blood pressure readings
    • Mildly reduced GFR on blood work
    • No physical symptoms at all in most cases

    Signs as kidney disease progresses (moderate to advanced):

    • Foamy or bubbly urine (due to excess protein)
    • Swelling (edema) in the feet, ankles, hands, or face
    • Increased fatigue or weakness
    • Loss of appetite or nausea
    • Itchy skin or muscle cramps
    • Difficulty concentrating
    • More frequent urination, especially at night

    Advanced or emergency warning signs:

    • Severe shortness of breath
    • Confusion or mental fogginess
    • Very little or no urination
    • Chest pain or pressure

    A 2023 analysis published through NIH-affiliated research confirmed that patients who are screened annually for albuminuria are significantly more likely to receive timely interventions that slow kidney disease progression. Don’t wait for symptoms — ask your doctor for this test at your next visit.


    Causes and Risk Factors

    The primary driver of diabetic kidney disease is chronically elevated blood glucose — but several overlapping factors accelerate kidney damage and determine who is most at risk.

    Metabolic and disease-related risk factors:

    • Poor long-term blood sugar control: Higher average A1C over years directly correlates with faster kidney decline
    • High blood pressure (hypertension): Affects roughly 70% of adults with type 2 diabetes and is a major independent cause of kidney damage
    • High cholesterol and triglycerides: Lipid abnormalities contribute to blood vessel damage in the kidneys
    • Duration of diabetes: The longer someone has had the condition, the higher the cumulative risk
    • Obesity: Excess body weight increases pressure on the kidneys and worsens insulin resistance

    Genetic and demographic risk factors:

    • Family history of kidney disease or diabetes
    • Race and ethnicity — African Americans, Hispanic Americans, and Native Americans have significantly higher rates of diabetic ESRD, according to the CDC
    • Being over age 50

    Lifestyle risk factors:

    • Smoking — which reduces blood flow to the kidneys and speeds decline
    • High dietary sodium intake, which drives up blood pressure
    • Sedentary lifestyle
    • Frequent use of NSAIDs (such as ibuprofen) without medical supervision

    It’s worth noting that this varies significantly from person to person. Some individuals with decades of diabetes maintain excellent kidney function, while others develop nephropathy within years. Your individual risk profile is best assessed with your healthcare team.


    Diagnosis: What to Expect

    Diagnosing diabetic kidney disease typically involves two key tests that your primary care physician or endocrinologist can order as part of your routine diabetes care.

    Urine albumin-to-creatinine ratio (UACR): This simple urine test measures the amount of albumin (a protein) leaking into your urine. A ratio above 30 mg/g on at least two out of three tests — taken over three months — indicates kidney damage. This is often the earliest sign of nephropathy, detectable years before other symptoms appear.

    Estimated GFR (eGFR): This blood test measures how well your kidneys are filtering waste. A normal eGFR is above 60 mL/min/1.73m². Values below this threshold, sustained over three months, indicate chronic kidney disease. The lower the number, the more impaired the kidney function.

    Additional tests your doctor may order include:

    • Comprehensive metabolic panel (checking creatinine, BUN, and electrolytes)
    • Blood pressure monitoring
    • Lipid panel
    • Kidney ultrasound (to rule out structural problems)

    The American Diabetes Association (ADA) recommends that all adults with type 2 diabetes be screened for kidney disease at diagnosis and every year thereafter. For type 1 diabetes, annual screening should begin five years after diagnosis. If you haven’t been screened recently, talk to your doctor — this is one of the most important tests you can get.


    Treatment Options for Diabetic Kidney Disease

    The good news is that diabetic kidney disease is highly treatable — especially when caught early. A combination of medication management, blood sugar optimization, and lifestyle changes can significantly slow or even stabilize kidney function decline.

    Medications shown to protect the kidneys:

    • ACE inhibitors and ARBs: These blood pressure medications (such as lisinopril or losartan) have a dual benefit — they lower blood pressure AND reduce protein leakage in the urine. Most physicians recommend them as first-line treatment for diabetic kidney disease, even in patients without high blood pressure.
    • SGLT2 inhibitors: A class of diabetes medications that clinical evidence indicates can reduce kidney disease progression, lower the risk of kidney failure, and provide cardiovascular protection. Major trials such as the CREDENCE and DAPA-CKD studies demonstrated significant renal benefits in patients with diabetic nephropathy.
    • GLP-1 receptor agonists: Research suggests these medications may also offer kidney-protective effects alongside blood sugar and weight management benefits.
    • Finerenone (Kerendia): A newer medication approved by the FDA that clinical trials show reduces the risk of kidney disease progression and cardiovascular events in adults with CKD and type 2 diabetes.

    Blood sugar and blood pressure targets:

    Most physicians recommend keeping A1C below 7% for most adults with diabetes to minimize kidney damage risk. Blood pressure targets are generally below 130/80 mmHg for people with diabetes and CKD, per ADA guidelines.

    Lifestyle modifications as a powerful complement:

    • Reducing dietary sodium to under 2,300 mg per day (or lower if recommended by your physician)
    • Following a kidney-friendly diet — often lower in protein, phosphorus, and potassium at advanced CKD stages
    • Quitting smoking — research consistently shows smokers with diabetic nephropathy lose kidney function faster
    • Regular moderate exercise, which improves insulin sensitivity and supports blood pressure control
    • Maintaining a healthy weight

    For more detail on how diabetes and cardiovascular risk interact — since heart and kidney health are closely linked — see our guide on Diabetes and Heart Disease: Protecting Your Heart.


    Living With Diabetic Kidney Disease: Daily Management and Prevention

    Managing diabetic kidney disease is a long game — and the daily habits you build have a compounding effect on your kidney health over years and decades.

    Monitor your blood sugar consistently. Whether you use a traditional glucometer or a continuous glucose monitor (CGM), staying on top of daily blood sugar fluctuations helps you and your care team make smarter decisions. You can read more about best practices in our related article on Diabetic Ketoacidosis: Symptoms, Causes & Prevention.

    Stay hydrated — but ask your doctor about fluid intake limits. At early CKD stages, adequate hydration supports kidney function. At later stages, your nephrologist may recommend fluid restrictions. This is highly individual.

    Avoid nephrotoxic substances. Certain medications and supplements can be hard on the kidneys. Always check with your doctor before taking any over-the-counter pain relievers, herbal supplements, or contrast dyes used in imaging procedures.

    Keep all specialist appointments. If your eGFR drops below 45, your primary care physician will likely refer you to a nephrologist (kidney specialist). This referral is important — don’t delay it. Collaborative care between your endocrinologist and nephrologist is the standard of care for advanced diabetic nephropathy.

    Prevention for those not yet diagnosed with CKD:

    • Get your annual UACR and eGFR tests without fail
    • Prioritize A1C control from the day of diagnosis — every percentage point matters
    • Treat hypertension aggressively and consistently
    • Ask your doctor whether an SGLT2 inhibitor is appropriate for you, given its kidney-protective benefits
    • Eliminate tobacco use completely

    A landmark finding from the UKPDS (United Kingdom Prospective Diabetes Study) demonstrated that intensive blood sugar control in the years immediately following a type 2 diabetes diagnosis produced lasting kidney-protective effects — even years later. Early action truly pays off.


    When to Call Your Doctor — and Emergency Red Flags

    While most diabetic kidney disease progresses slowly, certain symptoms warrant prompt medical attention. Knowing the difference between a routine concern and a medical emergency could save your life or your kidneys.

    Schedule a call or same-day appointment if you notice:

    • Sudden swelling in your legs, ankles, or feet
    • Foamy or discolored urine
    • Significant decrease in how much you urinate
    • Unexplained fatigue, nausea, or loss of appetite lasting more than a few days
    • Blood pressure readings consistently above 140/90 at home
    • Any new medication — prescription or OTC — that you’re unsure is safe for your kidneys

    Go to the emergency room immediately if you experience:

    • Sudden severe shortness of breath or chest pain
    • Confusion, difficulty speaking, or sudden extreme weakness
    • Complete or near-complete stoppage of urination
    • Severe vomiting that prevents you from keeping medications or fluids down
    • Sudden dramatic spike in blood pressure (hypertensive crisis)

    What to tell your doctor at your next visit:

    Bring your home blood pressure log if you have one. Ask specifically for your most recent UACR and eGFR values — and ask what the trend looks like compared to past years. Ask whether your current diabetes medications are the best choices given your kidney function. Be proactive: your kidneys can’t speak for themselves.


    Frequently Asked Questions

    Q: Can you reverse diabetic kidney disease?
    A: In the very earliest stage — called hyperfiltration, or stage G1 with microalbuminuria — research suggests that aggressive blood sugar and blood pressure control can reduce protein leakage and potentially stabilize kidney function. However, once significant structural kidney damage has occurred, the goal shifts to slowing progression rather than reversal. Early detection is critical precisely because of this.

    Q: How fast does diabetic kidney disease progress?
    A: Progression varies significantly from person to person and depends heavily on how well blood sugar, blood pressure, and other risk factors are managed. Some individuals maintain stable kidney function for decades; others progress to advanced CKD within 10 to 15 years of diabetes onset. Consistent treatment and monitoring can dramatically slow the timeline.

    Q: Is dialysis inevitable if I have diabetic nephropathy?
    A: No — dialysis is not an inevitable outcome. Many people with diabetic kidney disease never reach end-stage renal disease, particularly when the condition is caught early and managed effectively. However, without proper treatment, the risk of progression to dialysis is real. That’s why working closely with your healthcare team is essential.

    Q: Are there specific foods I should avoid to protect my kidneys with diabetes?
    A: At early CKD stages, the ADA and NIDDK recommend a diet low in sodium, refined carbohydrates, and ultra-processed foods. At more advanced stages, a registered dietitian specializing in kidney health (a renal dietitian) may recommend limiting foods high in potassium (like bananas and potatoes) and phosphorus (like processed foods and dark sodas). Dietary needs become more personalized as CKD progresses — always work with your care team.

    Q: Can I take ibuprofen or other NSAIDs if I have diabetic kidney disease?
    A: Most physicians recommend avoiding regular use of NSAIDs (such as ibuprofen, naproxen, or aspirin in anti-inflammatory doses) in patients with CKD, as they can reduce blood flow to the kidneys and accelerate damage. Always check with your doctor or pharmacist before taking any over-the-counter pain reliever if you have diabetes or kidney disease.


    Conclusion

    Diabetic kidney disease is one of the most serious — and most preventable — complications of diabetes. The fact that it causes no symptoms in its early stages makes it easy to overlook, but the tools to detect and manage it are right there in your annual lab work.

    You don’t have to accept kidney disease as an inevitable part of having diabetes. With consistent monitoring, the right medications, strategic lifestyle changes, and a proactive partnership with your healthcare team, you can protect your kidneys for years — and decades — to come.

    Marcus, from the beginning of this article, went on to work with his nephrologist and endocrinologist together. His eGFR stabilized. His story doesn’t have to be exceptional — it can be yours too.

    Talk to your doctor today. Ask for your numbers. Take the next step.


    This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.

  • Diabetes and Heart Disease: Protecting Your Heart

    Diabetes and Heart Disease: Protecting Your Heart

    People with type 2 diabetes are two to four times more likely to develop heart disease than those without it — making cardiovascular care one of the most critical parts of diabetes management.

    Why Your Heart and Blood Sugar Are More Connected Than You Think

    Marcus, 54, was doing everything his endocrinologist asked. He was checking his blood sugar daily, watching his carbohydrate intake, and taking his metformin without fail. But at a routine checkup, his cardiologist found early signs of coronary artery disease — the narrowing of the arteries that supply blood to the heart.

    "I thought my diabetes was under control," Marcus said. "I didn’t realize my heart was paying the price."

    His story is far from unusual. According to the American Heart Association, adults with type 2 diabetes face a dramatically elevated risk of heart attack, stroke, and heart failure. The connection between diabetes and heart disease is so strong that many cardiologists and endocrinologists now treat it as a single, unified condition rather than two separate problems.

    In this article, you’ll learn exactly why diabetes raises your cardiovascular risk, what warning signs to watch for, which treatments and lifestyle strategies have the strongest clinical backing, and how to have a productive conversation with your doctor about protecting your heart — starting today.

    What Is the Diabetes-Heart Disease Connection?

    Cardiovascular disease (CVD) is a broad term for conditions that affect the heart and blood vessels, including coronary artery disease, heart failure, and stroke. When blood sugar remains elevated over time — a hallmark of poorly managed or undiagnosed type 2 diabetes — it triggers a cascade of damage throughout the body, with the cardiovascular system bearing a significant burden.

    High blood glucose damages the inner lining of blood vessels, known as the endothelium. This damage makes arteries more prone to inflammation and plaque buildup, a process called atherosclerosis. Over time, narrowed or blocked arteries can lead to heart attacks and strokes.

    According to the Centers for Disease Control and Prevention (CDC), heart disease is the leading cause of death among people with type 2 diabetes in the United States. Roughly 68% of adults over 65 with diabetes die from some form of heart disease.

    Beyond blood sugar, diabetes often travels with other cardiovascular risk factors — high blood pressure, high triglycerides, low HDL ("good") cholesterol, and excess abdominal weight. This clustering of risk factors is known as metabolic syndrome, and it can multiply cardiovascular risk far beyond what any single factor would cause alone.

    Warning Signs: Symptoms That May Signal Heart Trouble in Diabetic Patients

    One of the most dangerous aspects of heart disease in people with diabetes is that it can be silent. Diabetic autonomic neuropathy — nerve damage affecting the body’s automatic functions — can blunt the sensation of chest pain, meaning some people experience what’s called a "silent heart attack" with few or no classic symptoms.

    That said, there are warning signs that should never be ignored:

    Early or subtle warning signs:

    • Unexplained fatigue that worsens with mild activity
    • Shortness of breath during activities that previously felt easy
    • Mild chest discomfort, pressure, or tightness
    • Swollen ankles or feet (a potential sign of heart failure)
    • Dizziness or lightheadedness when standing
    • Heart palpitations or irregular heartbeat

    Advanced or emergency warning signs:

    • Severe chest pain or pressure radiating to the arm, jaw, or back
    • Sudden difficulty breathing at rest
    • Sudden weakness or numbness on one side of the body (stroke)
    • Confusion, slurred speech, or vision changes
    • Loss of consciousness

    A 2022 study published in the journal Circulation found that people with diabetes who experienced a heart attack were significantly less likely to report classic chest pain than those without diabetes, underscoring the importance of routine cardiovascular screening rather than waiting for symptoms.

    Causes and Risk Factors: Why Diabetes Damages the Heart

    The biological pathways linking diabetes to heart disease are well-established and multiple. Understanding them helps explain why treatment must go beyond simply lowering blood sugar.

    Chronic high blood glucose: Excess glucose in the blood reacts with proteins in a process called glycation, stiffening blood vessel walls and promoting inflammation. Over years, this accelerates arterial damage.

    Insulin resistance: In type 2 diabetes, cells become less responsive to insulin. This forces the pancreas to produce more insulin, and chronically elevated insulin levels promote fat storage around the organs (visceral fat), increase blood pressure, and drive inflammatory pathways tied to atherosclerosis.

    Dyslipidemia: Diabetes frequently alters blood fat levels — raising triglycerides and lowering HDL cholesterol — even when total cholesterol appears normal. This combination is particularly damaging to arteries.

    Hypertension: The NIH estimates that approximately 70% of adults with type 2 diabetes also have high blood pressure. Together, the two conditions dramatically increase the workload on the heart and accelerate vascular damage.

    Obesity: Excess body weight, especially central obesity (fat carried around the abdomen), drives insulin resistance and inflammation. The CDC reports that more than 89% of adults diagnosed with type 2 diabetes are overweight or obese.

    Kidney disease: Diabetic kidney disease (nephropathy) independently raises cardiovascular risk, creating a dangerous feedback loop. As the kidneys lose filtering efficiency, blood pressure climbs and fluid balance is disrupted, further stressing the heart.

    If you have a family history of heart disease, are a smoker, or are physically inactive, your risk is further compounded. This variation in individual risk profiles is exactly why your care plan needs to be tailored — and why your conversations with your healthcare team matter so much.

    Diagnosis: How Doctors Assess Cardiovascular Risk in Diabetic Patients

    If you have type 2 diabetes, cardiovascular screening should be a routine part of your care — not something that only happens after symptoms appear. Here’s what to expect:

    Blood pressure measurement: Guidelines from the American Diabetes Association (ADA) recommend that blood pressure be checked at every diabetes-related visit. A target of below 130/80 mmHg is generally recommended for most adults with diabetes.

    Lipid panel (cholesterol test): A fasting blood test measures total cholesterol, LDL, HDL, and triglycerides. Most physicians recommend this at least annually for people with diabetes.

    Kidney function tests: A urine albumin-to-creatinine ratio and estimated glomerular filtration rate (eGFR) assess kidney health and help stratify cardiovascular risk.

    Electrocardiogram (EKG/ECG): A painless test that records the heart’s electrical activity. It can detect irregular rhythms, prior heart attacks, and other abnormalities.

    Stress test or echocardiogram: If your doctor suspects coronary artery disease, imaging or exercise testing may be recommended to evaluate blood flow to the heart.

    Advanced lipid testing: Tests like lipoprotein(a) and apolipoprotein B may be ordered in high-risk individuals to get a more detailed picture of cardiovascular risk beyond standard cholesterol panels.

    The ADA’s Standards of Medical Care in Diabetes recommend that all patients with type 2 diabetes receive a 10-year cardiovascular risk assessment using validated tools like the Pooled Cohort Equations. Don’t hesitate to ask your doctor if this has been calculated for you.

    Treatment Options: Protecting Your Heart While Managing Diabetes

    The good news is that many of the medications and lifestyle changes used to manage blood sugar also directly benefit the heart. This means your treatment plan can do double duty — and that’s a significant opportunity.

    SGLT2 inhibitors: This class of diabetes medications, which includes empagliflozin and dapagliflozin, has shown remarkable cardiovascular benefits in large clinical trials. Research published in the New England Journal of Medicine (the EMPA-REG OUTCOME trial) demonstrated that empagliflozin significantly reduced the risk of cardiovascular death and hospitalization for heart failure in adults with type 2 diabetes and established heart disease. Many cardiologists now consider these medications a cornerstone of treatment for diabetic patients with or at high risk for heart disease.

    GLP-1 receptor agonists: Medications like semaglutide and liraglutide not only improve blood sugar control and support weight loss — they’ve also shown cardiovascular protective effects in clinical trials, reducing rates of heart attack and stroke in high-risk patients.

    Statins: Cholesterol-lowering medications are broadly recommended for most adults with diabetes over 40, regardless of baseline LDL levels, due to their proven ability to reduce cardiovascular events. Clinical evidence from major trials indicates statins can reduce the risk of heart attack in diabetic patients by 25-35%.

    ACE inhibitors or ARBs: These blood pressure medications provide additional protection for the heart and kidneys, making them commonly prescribed for people with both diabetes and hypertension.

    Aspirin therapy: Low-dose aspirin may be recommended for secondary prevention (if you’ve already had a heart attack or stroke), though your doctor will weigh the benefits against bleeding risk on an individual basis.

    Lifestyle modifications: Clinical evidence strongly supports the role of diet, exercise, and weight management in reducing cardiovascular risk in diabetic patients. These are not optional add-ons — they are core components of treatment. For practical guidance on how physical activity lowers blood sugar and supports heart health, see our article on Emotional Eating and Weight Loss: How to Break the Cycle, which also addresses behavioral patterns that affect metabolic health.

    Living With Diabetes and Protecting Your Heart Every Day

    Managing your cardiovascular risk with diabetes isn’t just about medications — it’s about the daily decisions that, over years, make a measurable difference in your heart health.

    Follow a heart-healthy eating pattern: The Mediterranean diet and DASH diet both have strong clinical evidence for reducing blood pressure, improving cholesterol profiles, and supporting blood sugar control. Focus on vegetables, legumes, whole grains, fish, nuts, and olive oil while limiting saturated fat, sodium, and added sugars.

    Move consistently: The ADA recommends at least 150 minutes of moderate-intensity aerobic activity per week, spread across multiple days. Even short walks after meals can meaningfully reduce post-meal blood sugar spikes, which contribute to vascular damage.

    Manage your numbers — all of them: Ask your doctor for targets specific to your situation, but generally aim for an A1C below 7%, blood pressure below 130/80 mmHg, and LDL cholesterol below 70 mg/dL if you have established heart disease.

    Quit smoking: Smoking dramatically amplifies the vascular damage caused by high blood sugar. The CDC notes that smokers with diabetes are three times more likely to die from heart disease than non-smoking diabetic adults. If you smoke, this is the single most impactful change you can make.

    Manage stress: Chronic psychological stress raises cortisol levels, which elevates blood sugar and blood pressure. Mindfulness-based stress reduction (MBSR) and cognitive behavioral therapy (CBT) have both shown benefits for metabolic outcomes in diabetic patients.

    Monitor consistently: Blood glucose monitoring helps you understand how meals, activity, stress, and sleep affect your numbers — and gives your healthcare team the data needed to adjust your plan. For a deeper look at the metrics that matter, our guide on Diabetic Neuropathy: Symptoms, Causes & Management explains how sustained blood sugar elevation causes systemic damage over time.

    Prioritize sleep: Poor sleep quality worsens insulin resistance and raises blood pressure. Adults with diabetes who regularly sleep fewer than 6 hours per night face significantly higher cardiovascular risk, according to research from the NIH.

    When to Call Your Doctor — and Emergency Signs to Act On Immediately

    Managing diabetes and heart risk is an ongoing process, but some situations require urgent action. Knowing the difference between "call the office tomorrow" and "call 911 right now" can be lifesaving.

    Call 911 immediately if you experience:

    • Chest pain, pressure, squeezing, or tightness — even if mild
    • Pain spreading to the jaw, left arm, or upper back
    • Sudden severe shortness of breath
    • Sudden weakness, numbness, or paralysis on one side of the body
    • Sudden confusion, slurred speech, or vision loss
    • Loss of consciousness or near-fainting with chest discomfort

    Contact your doctor soon if you notice:

    • Persistent swelling in your legs or ankles
    • Increasing fatigue with normal activities
    • New or worsening shortness of breath
    • Heart palpitations or irregular heartbeats that are new for you
    • Unexplained dizziness or lightheadedness

    At your next scheduled visit, bring up:

    • Your 10-year cardiovascular risk score (if you don’t know it, ask)
    • Whether you should be on an SGLT2 inhibitor or GLP-1 agonist for heart protection
    • Your most recent cholesterol panel and whether your LDL target is being met
    • Any symptoms that feel new or unusual, even if subtle

    If you’ve experienced a prior cardiovascular event and also have diabetes, you may also want to ask your provider about the signs of acute diabetic emergencies to ensure you’re prepared to recognize and respond to multiple risk scenarios.

    Frequently Asked Questions

    Can managing my blood sugar actually lower my heart disease risk?

    Research suggests that improving blood sugar control — particularly early in the course of diabetes — can reduce cardiovascular risk over time, though the benefit may take years to fully appear. The UKPDS study, one of the landmark diabetes trials, found that early intensive glucose management led to long-term reductions in cardiovascular events. That said, blood sugar is only one of several risk factors to manage. Blood pressure, cholesterol, weight, and smoking status all require attention alongside glucose control.

    Is heart failure different from a heart attack, and are both risks with diabetes?

    Yes — they are distinct conditions, and diabetes raises the risk of both. A heart attack (myocardial infarction) occurs when blood flow to part of the heart muscle is blocked, causing tissue damage. Heart failure is a chronic condition where the heart can’t pump efficiently enough to meet the body’s needs. Clinical evidence strongly links type 2 diabetes to an increased risk of both, which is one reason SGLT2 inhibitors — which reduce hospitalization for heart failure — have become so important in diabetes care.

    How often should I see a cardiologist if I have diabetes?

    This varies significantly from person to person. If you have established heart disease or multiple risk factors, most cardiologists recommend at least annual visits. If your cardiovascular risk is currently low and well-managed through your primary care physician or endocrinologist, direct cardiology referral may not be routine. Ask your primary care provider whether a cardiology evaluation is appropriate for your situation.

    Can weight loss reduce cardiovascular risk in people with type 2 diabetes?

    Clinical evidence strongly indicates that even modest weight loss — 5 to 10% of body weight — can improve blood pressure, cholesterol, blood sugar, and inflammation markers, all of which contribute to cardiovascular risk. The Look AHEAD trial demonstrated meaningful improvements in cardiovascular risk factors among diabetic adults who achieved sustained weight loss through lifestyle changes. Some newer GLP-1 medications that support significant weight loss have also shown direct cardiovascular benefits in clinical trials.

    Are there any supplements that protect the heart in people with diabetes?

    Research suggests that omega-3 fatty acids (fish oil) at prescription doses may reduce triglycerides and, in certain high-risk populations, lower cardiovascular event rates. However, over-the-counter supplement doses vary widely and should not replace prescribed medications. Most physicians recommend focusing on food-based sources of omega-3s — like fatty fish — as part of a heart-healthy diet. Always discuss any supplements with your doctor before adding them to your regimen.

    The Path Forward: Knowledge Becomes Protection

    Living with type 2 diabetes doesn’t mean accepting heart disease as inevitable. The connection between the two conditions is real and serious — but so is the evidence that thoughtful, consistent management can meaningfully reduce your risk.

    The most powerful thing you can do is stay engaged with your healthcare team, understand your numbers, and act early when something feels off. Medications have evolved dramatically, lifestyle interventions have strong clinical backing, and the partnership between you and your providers has never been more capable of delivering real protection.

    You don’t have to navigate this alone. Whether it’s optimizing your treatment plan, making sustainable dietary changes, or simply asking the right questions at your next appointment — every informed step you take is an investment in a healthier heart.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC, NIH, ADA, and American Heart Association guidelines.

  • Diabetic Ketoacidosis: Symptoms, Causes & Prevention

    Diabetic Ketoacidosis: Symptoms, Causes & Prevention

    Diabetic Ketoacidosis: Symptoms, Causes & Prevention

    DKA is one of the most dangerous — and preventable — diabetes emergencies. Here’s what every person with diabetes needs to know.

    Introduction

    Mark, 44, had been managing Type 1 diabetes for over a decade. One winter, a flu that wouldn’t quit left him vomiting and too nauseous to eat. He assumed skipping meals meant he didn’t need insulin. Within 24 hours, he was in the emergency room with diabetic ketoacidosis — a life-threatening condition he later admitted he barely understood, despite living with diabetes for years.

    He’s not alone. According to the CDC, diabetic ketoacidosis (DKA) accounts for approximately 160,000 hospitalizations per year in the United States, with a mortality rate that climbs significantly when treatment is delayed. Yet many people with diabetes — and even some newly diagnosed individuals — don’t fully understand what triggers it, how to recognize it early, or what to do when warning signs appear.

    This guide covers everything you need to know about DKA: what it is, why it happens, how it’s treated, and — most importantly — how to prevent it from becoming a crisis in the first place.

    What Is Diabetic Ketoacidosis?

    Diabetic ketoacidosis is a serious, potentially life-threatening complication of diabetes that occurs when the body produces dangerously high levels of ketones — acidic byproducts of fat breakdown — while blood sugar levels are also critically elevated.

    Here’s the basic biology: your cells need insulin to absorb glucose (blood sugar) for energy. When insulin is severely deficient or completely absent, your body can’t use glucose efficiently. Instead, it starts breaking down fat for fuel. That fat breakdown produces ketones. When ketones accumulate too quickly, they make the blood acidic — a state called ketoacidosis.

    Think of it as a metabolic emergency where multiple systems fail at once: high blood sugar, dehydration, electrolyte imbalance, and acid buildup all happening simultaneously.

    DKA is most common in people with Type 1 diabetes, but it can also occur in people with Type 2 diabetes, particularly during severe illness, infection, or prolonged insulin deficiency. According to the American Diabetes Association (ADA), DKA can develop within hours under the right — or rather, wrong — conditions.

    The condition is serious, but it is also highly preventable with the right knowledge and monitoring habits.

    Signs and Symptoms of DKA

    One of the most important things to understand about DKA is that it usually doesn’t appear out of nowhere. There’s typically a warning window — hours in which early symptoms signal that something is wrong. Recognizing those signals early can make the difference between outpatient management and an ICU stay.

    Early warning signs:

    • Blood sugar consistently above 250 mg/dL
    • Increased thirst and dry mouth
    • Frequent urination
    • Fatigue or unusual weakness
    • Mild nausea
    • Headache
    • Presence of ketones in urine (detectable with at-home test strips)

    Advanced signs — seek emergency care immediately:

    • Vomiting that prevents keeping fluids down
    • Severe abdominal pain
    • Deep, labored, or fruity-smelling breath (called Kussmaul breathing)
    • Extreme confusion or difficulty concentrating
    • Blurred vision
    • Loss of consciousness

    That fruity-smelling breath is a classic DKA sign caused by acetone — one of the ketones being exhaled through the lungs. If you or someone around you with diabetes has that scent along with vomiting or confusion, call 911 immediately.

    A 2022 analysis published in collaboration with NIH-affiliated researchers found that patients who presented to emergency departments with advanced DKA symptoms — particularly altered mental status — had significantly longer recovery times and higher rates of complications compared to those who sought care during the early warning phase.

    Causes and Risk Factors

    DKA doesn’t just happen randomly. There are almost always identifiable triggers. Understanding them gives you a meaningful advantage in preventing the condition.

    Most common causes:

    • Missed or insufficient insulin: This is the leading cause. Whether it’s a skipped dose, a malfunctioning insulin pump, or deliberately reduced doses during illness, inadequate insulin sets the DKA cascade in motion.
    • Illness or infection: When you’re sick, stress hormones like cortisol and glucagon surge — and they counter insulin’s effects. Even if you’re eating less, your insulin needs may actually increase during illness.
    • Newly diagnosed or undiagnosed Type 1 diabetes: DKA is sometimes the first sign that someone has Type 1 diabetes, particularly in children and young adults.
    • Insulin pump failure: Because pump users receive no long-acting insulin backup, a blocked or disconnected infusion set can trigger DKA within hours.

    Risk factors that increase vulnerability:

    • Type 1 diabetes diagnosis
    • History of prior DKA episodes
    • Limited access to healthcare or insulin (a significant public health issue in the US)
    • Alcohol or drug use, which can mask symptoms or interrupt insulin routines
    • Psychological barriers to diabetes self-management, including diabetes burnout
    • Certain medications, including some SGLT2 inhibitors (a class of diabetes drugs), which can trigger a variant called euglycemic DKA — where blood sugars appear normal, but ketones are still dangerously elevated

    According to the CDC, the risk of DKA hospitalization is disproportionately higher among uninsured and underinsured Americans — a sobering reminder that access to insulin and consistent care are central to prevention.

    If you’re managing your diabetes with SGLT2 inhibitors, talk to your doctor about your specific DKA risk. This varies from person to person based on your diabetes type, current health status, and medications.

    Diagnosis: What to Expect

    If DKA is suspected, diagnosis is typically confirmed through a combination of blood and urine tests. Here’s what healthcare providers look for:

    Blood tests:

    • Blood glucose: Usually above 250 mg/dL, though euglycemic DKA can present with lower readings
    • Blood ketones or beta-hydroxybutyrate: Elevated levels confirm ketoacidosis
    • Arterial blood gas (ABG): Measures blood pH — a pH below 7.3 indicates acidosis
    • Basic metabolic panel: Checks electrolytes (especially potassium and sodium), kidney function, and bicarbonate levels

    Urine tests:

    • Urinalysis for ketones and glucose

    At home, if you have diabetes and your blood sugar is above 250 mg/dL and you feel unwell, the Mayo Clinic recommends testing for ketones using over-the-counter urine strips. If your ketone levels are moderate to high and you’re experiencing symptoms, do not wait — go to the emergency room or call your diabetes care team immediately.

    Doctors will also look for the underlying trigger — typically ordering a chest X-ray, blood cultures, or other tests if infection is suspected. Finding and treating the root cause is as important as treating the DKA itself.

    Treatment Options

    DKA requires prompt medical treatment. It cannot be managed safely at home once it has progressed. Treatment is typically administered in a hospital emergency setting and involves three core pillars:

    1. Intravenous (IV) Fluid Replacement

    Dehydration is a hallmark of DKA. Large volumes of IV saline are administered to restore fluid balance, lower blood sugar, and dilute ketone concentration. Clinical evidence indicates that fluid resuscitation is often the single most impactful first step in stabilizing a DKA patient.

    2. Insulin Therapy

    IV insulin is given continuously to stop ketone production and lower blood glucose gradually. Physicians carefully monitor the rate because dropping blood sugar too quickly carries its own risks, including cerebral edema (brain swelling), particularly in children and adolescents.

    3. Electrolyte Replacement

    As insulin drives glucose into cells, potassium follows. This can cause dangerous drops in potassium levels (hypokalemia), which can affect heart rhythm. Potassium, sodium, and phosphate are closely monitored and replaced as needed throughout treatment.

    According to Johns Hopkins Medicine, most adults with moderate DKA recover within 24 to 48 hours with appropriate hospital treatment. However, recovery time varies significantly based on the severity of the episode, the patient’s age, and any underlying complications.

    After acute treatment, the focus shifts to identifying what triggered the episode and adjusting the diabetes management plan to prevent recurrence. This often involves revisiting insulin dosing strategies, education on sick-day management rules, and, in some cases, support for mental health aspects of living with diabetes.

    Living With Diabetes and Preventing DKA

    Prevention is where you have the most power. Research suggests that consistent self-management habits dramatically reduce DKA risk — even for people with Type 1 diabetes who are insulin-dependent every day.

    Stick to your sick-day rules

    Many DKA episodes are triggered by illness. The critical mistake people make is reducing insulin because they’re not eating. This is almost always wrong. Your insulin needs often increase during illness due to stress hormones. Your care team can help you establish personalized sick-day guidelines — including when to test ketones, how to adjust doses, and when to call for help.

    Monitor blood sugar consistently

    Catching rising blood sugar before it becomes critical gives you time to act. Continuous glucose monitors (CGMs) have been shown in clinical studies to significantly reduce DKA hospitalizations among Type 1 diabetes patients by providing real-time alerts. If you use an insulin pump, checking ketones when your glucose unexpectedly rises is part of best-practice management. For more on how monitoring impacts diabetes outcomes, see our guide on Exercise and Blood Sugar Control: A Type 2 Diabetes Guide.

    Never skip insulin doses without medical guidance

    Financial hardship is a real barrier in the US — and it’s one of the leading drivers of preventable DKA hospitalizations. If you’re struggling to afford insulin, talk to your care team about patient assistance programs, generic alternatives, or community health center resources. The ADA maintains a dedicated insulin access program guide.

    Keep ketone test strips at home

    Urine or blood ketone strips are inexpensive and can catch early DKA before it becomes an emergency. Most physicians recommend checking ketones any time your blood sugar is above 250 mg/dL and doesn’t come down with a correction dose, or any time you feel unwell.

    Address the mental health piece

    Diabetes management is emotionally demanding. Burnout, avoidance of monitoring, and disordered eating patterns are all associated with increased DKA risk. If you’re struggling to maintain your routine, speaking with a mental health professional familiar with chronic illness can be genuinely protective. Many people find that addressing the psychological burden of diabetes improves their physical outcomes significantly.

    For those managing complications already linked to long-standing blood sugar issues, our detailed overview of Diabetic Neuropathy: Symptoms, Causes & Management provides additional context on how consistent glucose management protects against diabetes-related damage over time.

    When to Call Your Doctor — and When to Call 911

    Knowing when to escalate is critical. Here’s a practical breakdown:

    Call your diabetes care team (same day) if:

    • Your blood sugar is above 250 mg/dL and isn’t responding to correction doses
    • You have small to moderate ketones but are not vomiting and can keep fluids down
    • You’re sick and unsure whether to adjust your insulin
    • Your insulin pump appears to be malfunctioning

    Go to the emergency room or call 911 immediately if:

    • You have moderate to large ketones AND vomiting
    • You can’t keep any fluids down for more than two hours
    • You’re experiencing confusion, extreme weakness, or difficulty staying awake
    • Blood sugar remains critically high (above 300 mg/dL) and ketones are rising
    • Someone with diabetes loses consciousness
    • You notice fruity or acetone-like breath in yourself or someone else with diabetes

    When speaking to your doctor at your next routine visit, it’s worth discussing your personalized DKA action plan. Ask specifically about your threshold for seeking emergency care, your sick-day insulin adjustments, and what ketone level should prompt you to call the after-hours line.

    Frequently Asked Questions

    Can people with Type 2 diabetes get DKA?

    Yes, though it is less common than in Type 1 diabetes. Type 2 diabetes patients are most at risk during severe illness, significant physiological stress, or if they’ve been prescribed SGLT2 inhibitors (a class of diabetes medication). Euglycemic DKA — where ketones are high but blood sugar appears normal — is a specific concern with this drug class. Always discuss your individual risk with your provider.

    How quickly can DKA develop?

    In people with Type 1 diabetes, DKA can progress from early warning signs to a medical emergency in as little as 6 to 12 hours, particularly if vomiting prevents adequate hydration. For this reason, acting early at the first signs — rather than waiting to see if things improve — is always the right call.

    Is DKA the same as hypoglycemia?

    No. These are opposite emergencies. Hypoglycemia involves dangerously low blood sugar (below 70 mg/dL) and is typically caused by too much insulin or missed meals. DKA involves high blood sugar with ketone buildup from insufficient insulin. The symptoms and treatments are very different, which is why checking your blood sugar first is essential before deciding how to respond.

    Can I prevent DKA if I have Type 1 diabetes?

    In most cases, yes. Clinical evidence strongly supports that consistent blood sugar monitoring, following sick-day management rules, never skipping insulin without medical guidance, and having a clear action plan dramatically reduce DKA risk. Continuous glucose monitors and real-time ketone monitoring tools have improved prevention outcomes significantly in recent years.

    What is the recovery like after a DKA episode?

    Most people recover well with prompt treatment, though fatigue, mental fog, and weakness may persist for several days after discharge. Your care team will typically schedule follow-up within one to two weeks to review what triggered the episode and update your diabetes management plan. This follow-up visit is critically important — DKA recurrence rates are meaningfully reduced when the underlying cause is identified and addressed.

    Conclusion

    Diabetic ketoacidosis is serious — but it is not inevitable. With consistent monitoring, a clear understanding of your warning signs, and a practiced sick-day action plan, most DKA episodes can be prevented or caught early enough to avoid hospitalization.

    The most important thing you can do today is have a frank conversation with your diabetes care team about your personal DKA risk, your ketone monitoring routine, and exactly what steps to take if your blood sugar stops responding to treatment. Knowledge, preparation, and access to care are your best defenses.

    Living with diabetes — whether Type 1 or Type 2 — requires ongoing vigilance, but it also means you have real power to protect yourself. Use it.

    For a broader look at how daily habits connect to your blood sugar control, explore our resource on Exercise and Blood Sugar Control: A Type 2 Diabetes Guide.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.
  • Diabetic Neuropathy: Symptoms, Causes & Management

    Diabetic Neuropathy: Symptoms, Causes & Management

    Nerve damage from diabetes is more common — and more preventable — than most people realize.

    Michael, 54, had been living with type 2 diabetes for about eight years when he noticed something odd: a persistent tingling in his feet, almost like they had "fallen asleep" and never fully woken up. He assumed it was nothing serious. By the time he mentioned it to his doctor, he had already developed a small wound on his right foot that he hadn't even felt forming.

    Michael's experience is far from rare. According to the National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK), up to 50% of people with diabetes develop some form of diabetic neuropathy — nerve damage caused by prolonged high blood sugar. Yet many people don't recognize the early warning signs until complications have already set in.

    In this article, you'll learn what diabetic neuropathy is, how to recognize it early, what causes it, what your doctor can do about it, and — most importantly — how you can take meaningful steps to slow or prevent its progression. This is one of the most common yet underestimated complications of diabetes management, and understanding it could protect your quality of life for decades to come.

    What Is Diabetic Neuropathy?

    Diabetic neuropathy is a type of nerve damage that develops as a complication of diabetes — both type 1 and type 2. When blood sugar stays elevated for too long, it gradually damages the walls of the tiny blood vessels (called capillaries) that supply your nerves with oxygen and nutrients. Over time, those nerves lose their ability to function properly.

    Think of it like a slow power outage: the signals your nerves are supposed to send — pain alerts, touch sensations, organ control — start misfiring or going silent altogether.

    There are four main types of diabetic neuropathy:

    • Peripheral neuropathy — the most common type, affecting the feet and legs first, then sometimes the hands and arms
    • Autonomic neuropathy — affects involuntary body functions like heart rate, digestion, bladder control, and sexual function
    • Proximal neuropathy — causes pain in the hips, thighs, or buttocks and may lead to muscle weakness
    • Mononeuropathy (focal neuropathy) — sudden damage to a specific nerve, often causing facial or torso pain

    The NIDDK estimates that diabetic neuropathy affects between 60% and 70% of people with diabetes at some point during their lives. In the United States, it is one of the leading causes of non-traumatic lower-limb amputations — a sobering statistic that underscores why early detection matters so much.

    Signs and Symptoms of Diabetic Neuropathy

    Symptoms vary significantly depending on which type of neuropathy you have and how far it has progressed. This variation is one reason it's so often missed in its early stages.

    Early symptoms (often subtle):

    • Tingling or "pins and needles" sensation in the feet or hands
    • Numbness or reduced ability to feel temperature or pain
    • Mild burning or aching in the feet, especially at night
    • Sensitivity to touch — even light contact from a bedsheet can feel uncomfortable
    • Slight muscle weakness in the feet or legs

    Advanced or autonomic symptoms:

    • Loss of balance or coordination
    • Serious foot wounds or ulcers that go unnoticed due to lost sensation
    • Digestive problems such as nausea, vomiting, bloating, or gastroparesis (delayed stomach emptying)
    • Bladder dysfunction — incomplete emptying or incontinence
    • Dizziness or fainting when standing (orthostatic hypotension)
    • Sexual dysfunction in men and women
    • Irregular heart rate or blood pressure swings

    A 2021 clinical review published through the NIH's PubMed database noted that nearly one-third of people with peripheral diabetic neuropathy experience no symptoms at all in the early phase — making routine foot exams at every diabetes appointment an essential, non-negotiable part of care.

    Causes and Risk Factors

    The primary driver of diabetic neuropathy is chronically elevated blood glucose (blood sugar). High glucose levels trigger a cascade of chemical changes in nerve cells and damage the blood vessels that feed them — a process that unfolds slowly over years.

    Key causes include:

    • Prolonged hyperglycemia — consistently high blood sugar is the single most important factor
    • Inflammation — chronic low-grade inflammation associated with diabetes accelerates nerve damage
    • Oxidative stress — an imbalance between free radicals and the body's ability to neutralize them, which harms nerve tissue
    • Autoimmune factors — in some cases, the immune system attacks nerve fibers directly

    Risk factors that increase your likelihood of developing neuropathy:

    • Poor long-term blood sugar control (high A1C levels over many years)
    • Duration of diabetes — the longer you have diabetes, the higher the risk
    • Obesity and excess abdominal fat
    • High blood pressure and high cholesterol
    • Smoking — which further restricts blood flow to nerves
    • Alcohol use — alcohol is independently toxic to nerve tissue
    • Kidney disease (nephropathy), which often coexists with neuropathy

    According to the American Diabetes Association (ADA), people who have had diabetes for 25 years or more face a particularly high risk, with prevalence reaching nearly 50% in that population. However, research suggests that aggressive blood sugar management — especially in the first decade after diagnosis — can meaningfully reduce that risk.

    Diagnosis: What to Expect

    If you mention symptoms like foot tingling, numbness, or burning to your doctor, they will typically conduct a structured neurological evaluation during your office visit. The process is straightforward and usually non-invasive.

    Common diagnostic tools include:

    • Monofilament test — a thin nylon filament is pressed against different points on your foot to assess touch sensation
    • Tuning fork test — evaluates your ability to feel vibrations, a function often lost early in peripheral neuropathy
    • Pinprick test — checks pain sensitivity in the feet
    • Ankle reflex test — reduced or absent reflexes can indicate nerve damage
    • Nerve conduction studies — measures the speed and strength of electrical signals in your nerves; ordered when diagnosis is uncertain or more detailed information is needed
    • Electromyography (EMG) — evaluates muscle response to nerve stimulation
    • Autonomic function tests — used when autonomic neuropathy is suspected, checking heart rate variability and blood pressure responses

    The ADA recommends that all people with type 2 diabetes be screened for peripheral neuropathy at diagnosis and annually thereafter — and that people with type 1 diabetes begin screening five years after their diagnosis. Don't wait for symptoms to appear before asking your doctor to check.

    Treatment Options

    There is currently no treatment that fully reverses diabetic neuropathy, but multiple approaches — both medical and lifestyle-based — can slow its progression, relieve symptoms, and prevent complications.

    Blood sugar control — the foundation of all treatment:
    The most powerful intervention is optimizing your glucose levels. Clinical evidence from the landmark Diabetes Control and Complications Trial (DCCT), funded by the NIH, demonstrated that intensive blood sugar management reduced the risk of neuropathy by 60% in people with type 1 diabetes. Similar findings emerged in type 2 diabetes research through the UKPDS (United Kingdom Prospective Diabetes Study). Your doctor may adjust your medications, insulin regimen, or recommend a continuous glucose monitor (CGM) to help achieve better control.

    For more on how exercise supports blood sugar control as part of your overall diabetes management plan, see our guide: Exercise and Blood Sugar Control: A Type 2 Diabetes Guide.

    Medications for nerve pain:

    • Anticonvulsants such as pregabalin (Lyrica) and gabapentin — FDA-approved for diabetic nerve pain, they work by calming overactive pain signals in the nervous system
    • Antidepressants such as duloxetine (Cymbalta) — FDA-approved specifically for diabetic peripheral neuropathy pain; also prescribed are tricyclic antidepressants like amitriptyline
    • Topical treatments — capsaicin cream and lidocaine patches can offer localized relief for some patients
    • Opioid medications — generally used only when other options have failed, due to addiction risk and side effects; most physicians reserve these for severe, refractory pain

    Lifestyle modifications that complement medical care:

    • Dietary changes — a balanced, lower-glycemic diet supports stable blood sugar; consulting a registered dietitian is highly recommended
    • Physical activity — regular moderate exercise improves circulation and may slow nerve damage progression; research suggests even walking 30 minutes five days a week provides measurable benefit
    • Smoking cessation — smoking dramatically worsens blood flow to nerves; quitting is one of the most impactful changes you can make
    • Limiting alcohol — alcohol is neurotoxic and directly accelerates neuropathy
    • Foot care — daily inspection of your feet, appropriate footwear, and prompt treatment of any wound or blister are life-changing habits

    If you're also working on weight management — which directly impacts blood sugar — you may find helpful information in our article on Insulin Resistance: Causes, Signs & How to Improve It.

    Living With Diabetic Neuropathy: Day-to-Day Management

    A diagnosis of diabetic neuropathy is serious, but it doesn't have to define your life. Many people with neuropathy maintain an active, fulfilling lifestyle by building consistent self-care routines and staying in close communication with their healthcare team.

    Practical daily habits that make a real difference:

    • Inspect your feet every single day — look for redness, swelling, blisters, cuts, or sores. Use a mirror or ask someone to help if needed. Loss of sensation means injuries can develop without you feeling them.
    • Wear well-fitting, protective footwear — avoid bare feet, even indoors. Ask your doctor about therapeutic shoes if standard footwear causes pressure points.
    • Keep feet clean and moisturized — but avoid lotion between the toes, where moisture can promote infection.
    • Monitor your blood sugar regularly — consistent tracking gives you and your care team the data needed to make smart adjustments.
    • Manage comorbidities — keeping blood pressure and cholesterol in a healthy range reduces additional vascular stress on your nerves.
    • Sleep quality matters — poor sleep can worsen pain perception and disrupt blood sugar regulation. If neuropathy pain disturbs your sleep, discuss this specifically with your doctor. You can also read more about how sleep affects metabolic health in our article: Weight Loss and Sleep: Why Rest Is Key to Losing Weight.

    For autonomic neuropathy affecting digestion, your doctor may recommend eating smaller, more frequent meals, avoiding high-fat foods, and adjusting meal timing relative to insulin or medication schedules.

    Prevention strategies for those not yet diagnosed:
    If you have diabetes but haven't developed neuropathy yet, now is the critical window. Clinical evidence consistently shows that maintaining an A1C below 7% (or the target your doctor sets for you), exercising regularly, not smoking, and attending every recommended screening appointment significantly reduces your lifetime risk of developing significant nerve damage.

    When to Call Your Doctor — and Emergency Warning Signs

    Diabetic neuropathy can escalate quickly in certain situations. Knowing when to act is not just smart — it's potentially limb-saving.

    Schedule a prompt (non-emergency) appointment if you notice:

    • New tingling, numbness, or burning in your feet or hands
    • Increased pain that isn't relieved by your current medications
    • Difficulty walking, balancing, or climbing stairs
    • Digestive changes like persistent nausea, early fullness, or unpredictable bowel habits
    • New bladder symptoms — difficulty urinating or frequent leakage
    • Dizziness when standing up
    • Sexual dysfunction that has recently developed or worsened

    Seek emergency care immediately if you experience:

    • A foot wound, ulcer, or blister that shows signs of infection — redness spreading outward, warmth, pus, or foul odor
    • Any foot injury that isn't healing after a few days, even if it seems minor
    • Sudden, severe weakness in the legs
    • Chest pain, severe dizziness, or fainting (possible autonomic neuropathy affecting the heart)
    • Signs of diabetic ketoacidosis (DKA) — extreme thirst, frequent urination, confusion, fruity-smelling breath

    The CDC notes that diabetic foot complications result in more than 100,000 lower-limb amputations annually in the United States. The overwhelming majority of these are preventable with early detection, consistent foot care, and timely medical attention.

    Frequently Asked Questions About Diabetic Neuropathy

    Can diabetic neuropathy be reversed?
    In most cases, nerve damage from diabetic neuropathy cannot be fully reversed. However, research suggests that with strict blood sugar control, the progression can be significantly slowed — and in some early cases, partial improvement in nerve function is possible. The goal of treatment is to stop further damage and manage symptoms effectively.

    How fast does diabetic neuropathy progress?
    This varies considerably from person to person. Progression depends largely on how well blood sugar is controlled over time, how long you've had diabetes, and whether you have additional risk factors like smoking or high blood pressure. Some people see very slow progression over decades; others experience more rapid deterioration if glucose levels remain uncontrolled.

    Is diabetic neuropathy painful?
    Not always. Some people experience significant burning or stabbing pain, while others feel only numbness with no pain at all. Paradoxically, the absence of pain can be more dangerous because it means you won't notice injuries. Both presentations require medical attention and active monitoring.

    What is the best diet for managing diabetic neuropathy?
    No single diet has been proven to specifically treat neuropathy, but a diet that supports stable blood sugar levels is central to preventing its progression. Most physicians and registered dietitians recommend a diet rich in vegetables, whole grains, lean proteins, and healthy fats while limiting refined carbohydrates, added sugars, and alcohol. Working with a certified diabetes care and education specialist (CDCES) can help you personalize your approach.

    Do I need to see a specialist for diabetic neuropathy?
    Your primary care physician or endocrinologist can manage most cases of diabetic neuropathy. However, depending on your symptoms, you may be referred to a neurologist (for complex nerve pain or diagnostic workup), a podiatrist (for foot care), a cardiologist (for autonomic heart involvement), or a gastroenterologist (for gastroparesis). A multidisciplinary approach generally yields the best outcomes.

    Conclusion

    Diabetic neuropathy is one of the most common and consequential complications of diabetes — but it is far from inevitable. The decisions you make today about blood sugar control, physical activity, foot care, and regular medical screening directly shape your risk and your future quality of life.

    If you're already experiencing symptoms, know that effective treatments exist and that working closely with your healthcare team can make a meaningful difference. If you haven't developed neuropathy yet, the window you have right now to protect your nerves is enormously valuable — don't wait for symptoms to appear.

    Talk openly with your doctor about your neurological health at every diabetes visit. Ask for a foot exam. Ask about your A1C trend. Ask what your numbers mean for your long-term nerve health. You deserve specific, honest answers — and proactive care every step of the way.


    Medical Disclaimer: This article is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always consult your physician or a qualified healthcare provider before making changes to your health routine or treatment plan.

    Medically reviewed by our editorial health team. Content follows evidence-based standards aligned with CDC and NIH guidelines.